CAM III - Rheumatology pt. 1
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/69

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
70 Terms
Genetic predisposition for RA
HLA-DRB1
Pt has insidious onset of symmetrical peripheral joint pain, > 30 min of morning stiffness, fatigue, fever, subcutaneous nodules. Joints are soft, warm, tender. What is suspected
Rheumatoid arthritis
MC joints affected by RA
MCPs, MTPs, wrists, ankles
RA, splenomegaly, neutropenia
Felty syndrome
Most specific lab for RA
Anti-CCP antibodies
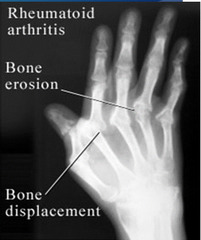
X-ray findings of rheumatoid arthritis
Bone erosion/displacement, joint space loss, ulnar deviation of MCPs, periarticular osteopenia
Initial RA treatment
Steroids (short term until other meds titrated)
NSAIDs
Heat therapy
Activity modification
DMARDs
First line RA treatment
Methotrexate max 20mg/week
How would you treat a patient with RA
Prednisone -> Methotrexate 7.5 mg-15mg PO once weekly
Methotrexate CI
Pregnancy/breastfeeding
Alcoholic liver disease
Untreated hepatitis
Blood dyscrasias
Second line (or adjunct) RA tx
Hydroxychloroquine
Sulfasalazine
Leflunomide
ADE to tx RA w biologics
Reactivation of latent TB and hepatitis
Increased infection risk
Increased malignancy risk
Monitoring for biologic tx in RA
PPD or T-SPOT and hepatitis panel before starting
Quant Gold annually
CBC, LFTs, BMP q8-12 weeks
PE q 12 weeks
12 year old girl with joint pain, swelling, and tenderness lasting > 6 weeks. Patient is complaining of limited ROM and parents are worried about her short stature.
Juvenile idopathic arthritis
JIA - pain, stiffness, swelling affecting 1-4 joints. Most commonly affecting large joints (knee or ankle)
Oligoarthritis

8 y/o w reoccurring fevers 103+, intermittent salmon colored rash, anemia, pain in hands, wrists, knees, ankles. On PE you find hepatosplenomegaly & lymphadenopathy
Systemic onset JIA
Pts w oligoarthritis are at a higher risk of what?
Uveitis or Iritis
Compare and contrast oligoarthritis vs polyarthritis
Oligoarthritis: < 5 joints, often affecting one side of body only, particularly in the knee.
Polyarthritis: > 5 joints, affects weight bearing and other joints including hips, neck, shoulders, jaw. Affects same joint on both sides of body
10 y/o girl presenting with joint pain, back pain and stiffness. You note no obvious swelling on initial exam but further evaluation reveals inflammation where tendons attach to bones.
Enthesitis related arthritis
First line therapy for JIA
NSAIDs
Treatment options for JIA
NSAIDs
Prednisone PO or intra-articular joint injection
MTX
Anakinra (biologic)
Pt complains of episodes of fevers + joint pain (fingers/knees) lasting for days, symptoms disappear spontaneously
Palindromic Rheumatism
What might make a pt with palindromic rheumatism more prone to developing RA
CCP antibodies
Standard of care during palindromic rheumatism attacks
NSAIDs
What can you use to prevent palindromic rheumatism attacks/progression
Hydroxychloroquine
32 y/o female presents with fluctuating daily fevers > 102+. Pt complains of a sore throat, salmon-colored rash on chest, wrist arthritis. On PE she has hepatosplenomegaly
Adult still disease
Adult still disease triad
Spiking fever, arthritis, evanescent rash.
Adult still disease workup
CBC: Anemia + leukocytosis
CMP: elevated LFTs
Ferritin: extremely high > 3000 mg/mL
CRP/ESR elevated
CXR to eval for pericardial effusion
(ANA, CCP, RF will be negative)
Adult still disease 1st line treatment
Prednisone
DMARDs if refractory: MTX, Anakinra, Tocilizumab
Yamaguchi's criteria
Criteria for Adult Still Disease: 5 or more, two or more criteria must be major
Major: fever > 39 C x 7days+, arthralgias x 14days+, typical rash, WBC > 10,000 w > 80% neutrophils

18 y/o male presents with persistent worsening low back pain, prolonged morning stiffness, anterior uveitis. List labs that would support your suspected diagnosis?
HLA-B27+
Elevated ESR/CRP
Negative RF
*ankylosing spondylitis
list the HLA-B27 diseases
PAIR:
Psoriasis/Psoriatic arthritis
Ankylosis spondylitis
IBD
Reactive arthritis (reiter's)
Ankylosing spondylitis PE
Decreased axial ROM (schober test)
Reduced chest expansion
Flattened lumbar lordosis, exaggerated thoracic kyphosis
Tests for ankylosing spondylitis
Schober's Test
Flesche test
Enthesitis with ankylosing spondylitis
Inflammation where tendon meets bone
- achilles tendon common
Ankylosing spondylitis X-ray findings
Bamboo spine
Early changes indicate sacroilitis (Ferguson's view)
Ossification of annulus fibrosis -> bridging syndesmophytes
Calcification of anterior longitudinal ligament
Ankylosing spondylitis treatment
Exercise
NSAIDs (naproxen, ibuprofen, meloxicam, diclofenac)
Methotrexate or sulfasalazine if NSAIDs dont work
Steroids short term for flare ups
Age group that psoriatic arthritis typically presents
30-50 y/o
M=F
Psoriatic Arthritis: DIP joints type
Monoarticular, asymmetric. Inflammation of nail beds -> pitting and onycholysis
Symmetric polyarthritis
Prominent MCP disease, may mimic RA
Arthritis Mutalins (psoriatic arthritis)
Severe deforming arthritis in which osteolysis is marked
Psoriatic spondylitis
Association w HLA-B27 (50%)
Atypical axial skeleton involvement
Sacroilitis
Lumbar spine MC
Pt w psoriasis is complaining of chronic or acute onset peripheral joint sx +/- LBP. What are some physical exam findings you'd expect to see to support the suspected dx
Nail involvement
Dactylitis (sausage digit)
Enthesopathy (achilles tendonitis, plantar fasciitis, medial epicondylitis)

15 y/o girl presents with joint pain and silvery scales on her flexor surfaces
Psoriasis related JIA
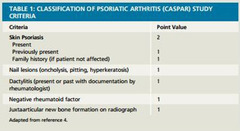
CASPAR criteria
Criteria for psoriatic arthritis
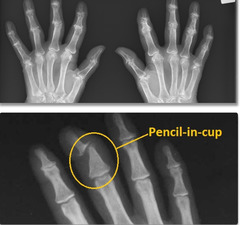
Psoriatic arthritis X-ray findings
pencil in cup deformity
Asymmetric sacroilitis
Atypical syndesmophytes
Psoriatic arthritis treatment
NSAIDs, steroid inj, MTX 7.5-20 mg/week
- NO hydrochloroquine
Pt complaining of asymmetric joint pain in large weight bearing joints following GI infection or STI. On exam you note anterior uveitis, conjunctivitis, urethritis, and mouth ulcers
Reactive arthritis (reiter's syndrome)
Reiter's syndrome labs
HLA-B27+ (50%)
ESR/CRP elevated
RF/CCP negative
Sterile joint fluid
Reactive arthritis treatment
Initial: Doxycycline 100 x 6 mo for chlamydia infection
NSAIDs
SSA BID, MTX q wk
pt with chron's presenting with asymmetric oligoarthritis
IBD-associated spondyloarthritis
IBD-associated spondyloarthritis treatment
TNF inhibitors, Jak inhibitors, Anti-IL 12/23 Ustekinumab
*AVOID NSAIDs, IL-17i (cosentyx, taltz)
Pt presenting with acute onset of severe monoarticular inflammatory arthritis affecting peripheral joints (small joints of feet/hands, ankles, knees, elbows)
Gout
Podagra
gout in the big toe (MTPJ) -> intense pain/redness/swelling
Tophus
Nodular deposit of monosodium urate monohydrate crystals

Secondary causes of gout
CKD, hypothyroidism, HCTZ, alcohol, red meat, shellfish
Uric acid level suspicious for gout
Uric acid > 8 mg/dL
Gout diagnosis
CBC: WBCs high ~40,000
Gram stain, culture synovial fluid
X-ray -> tophi or rat bite marginal joint erosions

Diagnostic for gout
Joint fluid analysis -> rod or needle-shaped, negatively birefringent urate crystals on polarized microscopy
First line tx for gout
NSAIDs (indomethacin)
Gout treatment
Indomethacin (NSAID) -> prednisone -> colchicine
*goal serum uric acid ~6 mg/dL
Tx for acute gout attack
Colchicine (give immediately when sx start)
Gout management between attacks
Colchicine + Allopurinol
Septic arthritis triad
Fever, pain, impaired ROM
Pt is > 60 y/o w crystal-induced arthritis caused by calcium pyrophosphate dihydrate
Pseudogout
Pseudogout triggers
Hyperparathyroidism
Hemochromatosis
Wilson's
Hypomagnesemia
Infections
Pseudogout MC affects what joints
Large joints (knees, wrists)
pseudogout x-ray findings:
chondrocalcinosis (crystals in fibrocartilage/hyaline cartilage)
Pseudogout diagnosis
Light microscopy: weakly positive birefringent calcium pyrophosphate crystals (rhomboid) in joint aspirates.
Pseudogout treatment
NSAIDs, colchicine