Prelim 1
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/63

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
64 Terms
L2 - Why Do We Need Pop Health?
US spends more on healthcare than any other OECD nation but lag behind b/c lower _ & highest _ rate.
life exp ; obesity
3 components of pop health mandate
5% of pop accounts for 50% of spending
6/10 adults have at least 1 chronic disease
7/10 leading death causes prev
Adults receive _% of rec care, clinical care drives only 20% of health outcomes but account for _ of spending
55 ; most
What are some inequities in health outcomes?
14 yr life exp gap b/t Asians & Natives
25 yr life exp gap b/t 2 bus stops in New Orleans
Native women preg-death 3x higher than white women
What is epidemiological transition from 1900 to 2000?
1900: death due to infectious diseases (pneumonia, tuberc., diarrhea)
2000: death due to lifestyle related chronic diseases (heart disease, cancer, stroke)
Real vs. artifact trends in rate
real = changes in age struct/survival/incidence ; artifactual = changes in disease recognition/def/classification/reporting/pop identification
6 parts of traditional paradigm (med model)
treat sickness/reduce symptoms
in-patient/facility centric
speciality driven physicians E&M
siloed
fee for service
payment for vol
6 parts of new paradigm (pop health model)
manage pop/prev + wellness
ambulatory (PC, homes, virtual)
primary care driven/address SDOH
integrated
shared risk/reward
payment for value
What is IHI Triple Aim?
simult. improve health by improving health of pop, care exp, & lower per capita cost
What are 2 key denominators in defining populations?
communities: all persons in region at given time defined geo/shared set of traits (total pop health)
empaneled patients: indv attributed to a provider based on delivery sys utilization (accountable care/pop med)
WHO 1994 def of health
state of complete phys, mental, social wellbeing & not merely absence of disease/infirmity
10 key aspects of pop health management
organized care sys w/care teams that coordinate
cross-sector collab for wellness & prev
upstream SDOH
holistic, patient centered prim care
evidence-based practice
risk strat, patient-centered
tailored, patient-centered care
meaningful use & clinical integration
accountability
health equity
L3 - ACA & Pop Health
What are 4 key policy drivers for 2010 ACA?
access
community & pop based activities
prev & health promotion
quality
What are 4 components of access + each goal/why?
indv mandate: extend health insurance to cover 52 mil uninsured b/c it compels healthy to buy insurance = balance risk pool/lower premiums
Medicaid expansion: extend health insurance coverage to more of low income (but 10 not adopt b/c SC ruling 2021)
state insurance exchanges w/MEC & 60% AV: ensure quality affordable insurance
support for comm health centers (FQHCs): fed doubles funding, boost rev, & inc training opportunities/tuition reimbursement
What is MEC & 60% AV?
min essential coverage = 10 essential health benefits
lab, emergency, prescription drugs, mental health, maternity, pediatric/oral + vision, rehab, ambulatory, prev, hospitalization
insurance needs to pay min 60% of actuarial value (i.e. bronze plan)
What are 3 levers for indv mandate (access)?
indv insurance mandate w/penalty if uninsured (ended 2017)
eliminate med underwriting/denial for pre-existing cond
children on parent insurance til 26
What is the lever for Medicaid expansion (access)?
eliminate Medicaid’s categorical eligibility & replace w/standard income-based eligibility (income below 138% FPL)
What is the lever for state insurance exchanges?
state insurance marketplaces have premium subsidies = quality health insurance affordable for small business & indviduals
What are 4 components of community & pop based activities + each goal?
nat prev strategy: inc # of Americans healthy at every life stage
prevention & public health fund (PPHF): prev chronic diseases & eliminate disparities
incentives for workplace wellness: inc workplace wellness prog
comm health: strengthen comm benefit req for hospitals/CHNAs enforced by IRS
What is the lever for prev & public health fund (comm)?
PPHF is nation’s first mandatory funding stream for primary prev to red risk factors
What is the lever for incentives for workplace wellness (comm)?
small business grants & discounts
What are 4 components of prev & health promotion + each goal?
expand primary healthcare training: inc # of primary care practitioners esp in rural
no cost-sharing for annual USPSTF rec screening
Medicare annual wellness visit
Medicaid expand children’s free prev service to adults
ACOs = accountability for patient pop
What are the 5 levers for expanding primary healthcare training (prev)?
fund PC residency training prog
train new PAs for team-based PC
train NPs for comprehensive PC
state grants to expand PC workforce + tuition reimbursement for high-need
10% bonus to PCPs
What are 3 components of quality?
req national quality strat (triple aim)
create CMMI to test payment/delivery models
authorize value-based payment prog
L4 - Measuring Pop Health Outcomes
For pop health dimension of triple aim, what are the 3 outcome measures?
health outcomes: mortality, health & funct status, healthy life exp
disease burden: incidence/prevalence of major chronic conditions
behavioral (smoking, alc, exercise, diet) & physiological factors (BP, BMI, cholesterol)
What 5 things can mortality data tell us?
how freq ppl die/rate
at what age
causes
how much life lost prematurely
how long ppl can expect to live
What are county health rankings (CHR)?
first pub-available standardized dataset of comm health data at county level organized from upstream to downstream health outcomes
What is Years of Potential Life Lost (YPLL75)? What is race/gender trend in Finger Lakes?
measure of premature mortality which gives greater wt to death at younger age
M have more yrs lost, & African Americans/Latino have most yrs lost
Life exp tables can be visualized into _ and rectangularization of mortality is _
survival curves ; Asian non-Hispanic F most healthy b/c most rectangular curve

What is Health Related Quality of LIfe (HRQOL) using CDC”s Healthy Days?
4 qs to measure self-reported physical & mental health & activity limitations

What are the health indicators for each q?
Self-rated health: % of pop reporting fair/poor
Physically unhealthy days: mean # of unhealthy days (UHD) & frequent physical distress (FPD) which is % of 14+ physically UHDs
Mentally unhealthy days: UHD & frequent mental distress (FMD)
Activity limitations: mean count of ALDs & frequent activity limitation days
What was Humana’s Bold Goal and 4 reasons why they used CDC’s HRQOL?
improve health of communities they serve by 20% by 2020
holistic b/c measure both mental & physical unhealthy days
3rd party validated
measurable ROI ($15.64 inc in monthly cost per unhealthy person)
strong correl b/t SDOH & chronic diseases
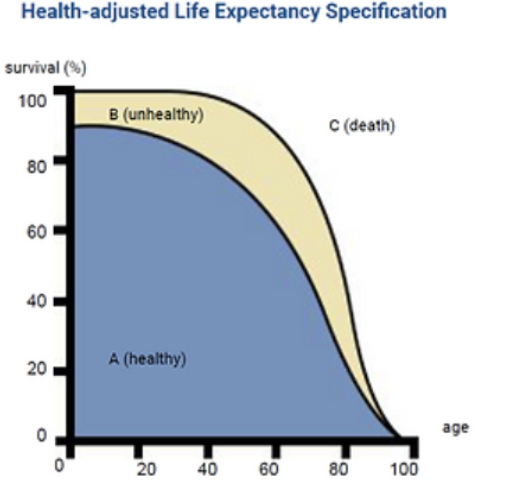
What is healthy life expectancy (HLE)? What is compression of morbidity?
shows how long ppl live in good health (not just how long)
delaying onset of illness til late in life so smaller proportion of life in poor health
What is benchmarking?
b/c single number tells little CHRs provide state & US benchmarks to identify areas of concern
Age-adjusting allows us to _
compare pop w/different age distributions so diff in measures arent’t simply b/c one pop is older
L6 - Sickness & Wealth SDOH
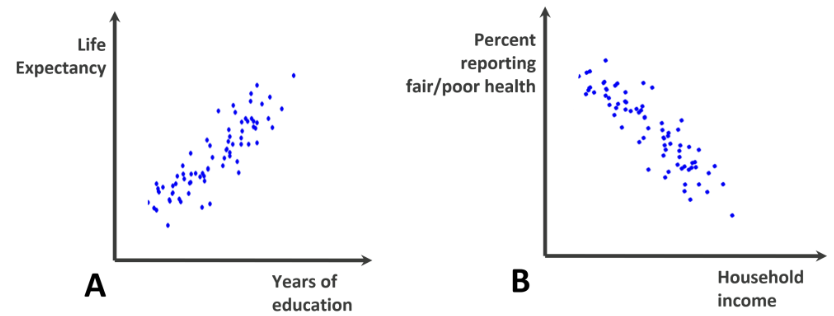
Which graph shows social gradient in healthy & why?
B b/c health improves (% reporting poor health) dec as household income inc
What did Whitehall studies find & what was important about the pop they studied? If we eliminated poverty would we eliminate gradient?
social gradient in health where lower in work hierarchy were unhealthier/greater prob of heart attack
all of pop was employed/pretty homogenous
no b/c same workplace but diff ranks still had gradient
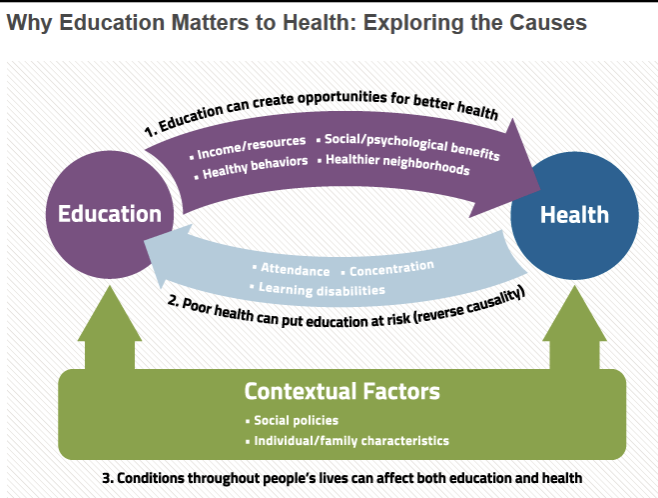
How does Tondra’s story/edu affect health?
edu attainment = health knowledge/literacy/behaviors = nut/exercise/drugs & alc/health management = HEALTH
What are the 3 hypotheses explaining observed correlation b/t SES & health (edu ex)?
social causation hypothesis: SES casually affect health (p)
health selection bias hypothesis” unwell children unable to attain higher SES (b)
confounding (g)
What did Nancy Krieger’s twin study find? Which hypothesis about SES & health does this study support?
controlling for genetics twin pair w/higher income have better health outcomes
social causation b/c lower SES affects health
What did macaque monkey research teach Dr. Shively about power, control, & health?
lower hierarchy monkeys had thicker arteries = worse health b/c less control & more health
What did Dr. Cohen’s cold virus study find? What was the great predictor & graded predictor of adult immune function & health?
higher perceived SES = lower susceptibility to colds
great = ; graded =
Allostatic Load
cumulative burden of chronic stress & life events inc poor health outcome chances

_ poses an additional health burden on POC
racism
SDOH
econ cond, social factors, & phys factors in env which ppl are born, live, learn, play, work, & age shaped by global distribution of money, power, & resources

What is Mary’s story & how policy drives health?
lives in town where 30% below FPL, most don't have high school diploma, & unemployed
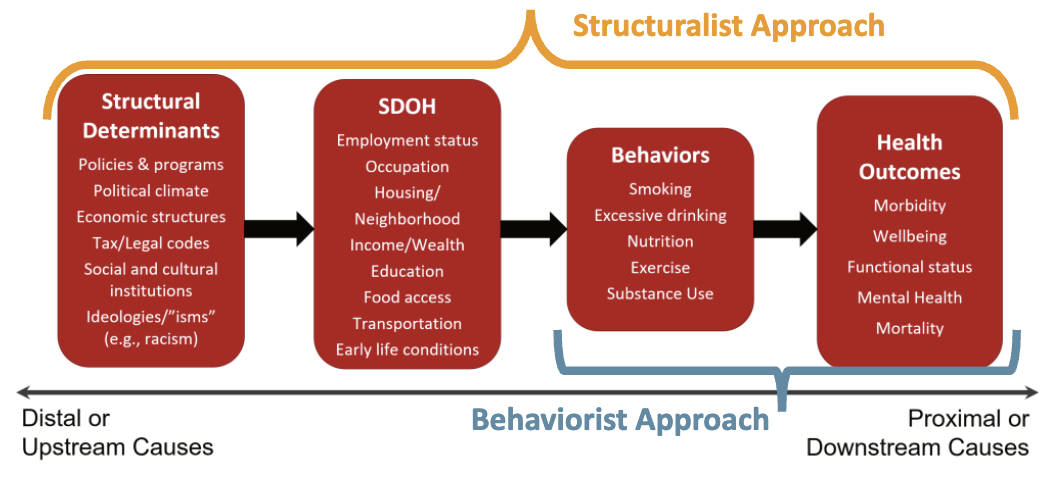
What are some upstream/downstream causes of why some people healthy while others not? Which are structuralist & behaviorist approach?
L7 - Place Matters
Social _ factors are health harming SDOH while social _ factors are health producing SDOH
risk ; protective
What are 3 reasons why place matters?
shape what we’re exposed to = direct health impact
shape what resources/opportunities are available = indirect impacts
place shaped by policy & investment
Built vs. Social Env & examples
built = how design, construction, & building placement within community impact human health (i.e. proximity to env hazards, qual of affordable housing, billboards)
social = behaviors, connections, norms, social capital, & socio-demographic characteristics of ppl in an env that impact health (i.e. violence & crime)

Why did Gwai in Richmond, CA (young, janitor, not smoker, no history) have heart attack/disease?
b/c of chronic stress/worry/env factors = social causation hypothesis
protective factor = community/family support group
Can we change place to change health - High Point Seattle? What’s the impact of Stephen’s “breathe easy unit” on his health/family?
community worked w/city to earn fed grants to rebuild Highland to be integrated w/rest of neighborhood (public lib, clinic, gardens)
low-income most affected by asthma = breathe easy homes w/high ventilation
Why did Richmond become unhealthy?
WWII end = shipyard close = jobs go away (cycle of disinvestment)
fed supported loans only to white (<2% went to nonwhite households) = can’t leave Richmond = upstream factor
What’s the significance of pointing out 10-12 yr old girls having gallbladder removed?
consume more fat/fast food b/c no farmer’s market or supermarket = env is a factor
Food Desert vs. USDA definition
neighborhood w/poor access to healthful foods (i.e. fresh & affordable fruits & veg) that make up healthy diet
low-income census tract (<20% FPL) w/33%+ pop residing at least 1 mi (10 mi if rural) from large grocery store
Required Materials
According to Stiefel & Nolan, what are the 3 dimensions of IHI Triple Aim?
pop health
experience of care
per capita cost
What are the 3 outcome measures for pop health?
health outcomes
disease burden
behavioral & physiological factors
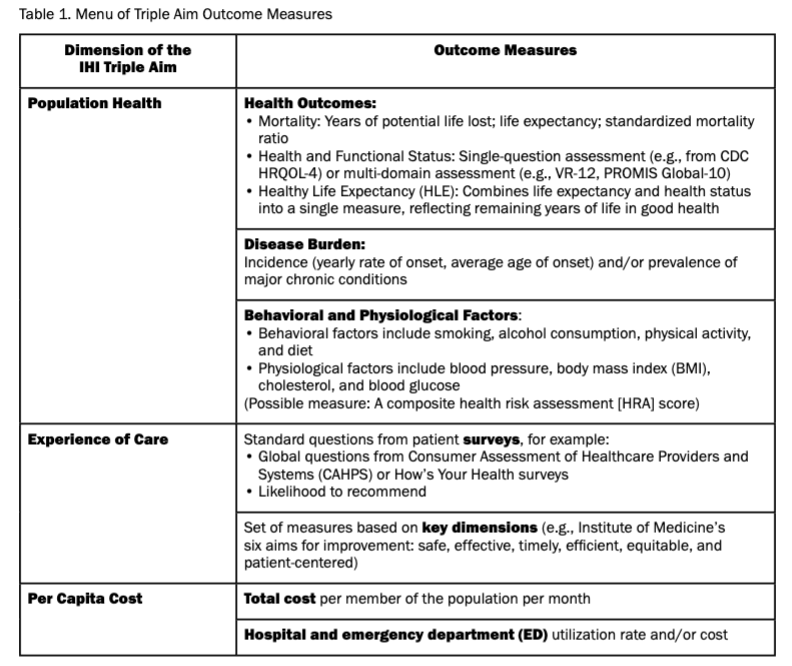
The health outcomes of _ and their combination are ultimate outcome measures for pop health (Stiefel & Nolan)
mortality, health & functional status