Fluoro II pathologies and image critique
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/59

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
60 Terms
crohn’s disease
chronic inflammatory disease of the intestines
appearance of crohn’s disease
inflammation and fibrosis with narrowing
String sign, skipped pattern
Cobblestone appearance
colonic diverticula
outpouchings, herniation of mucosa and submucosa through the muscular layers at points of weakness of the bowel wall
appearance of colonic diverticula
Round or oval outpouchings, tend to be in clusters
Abscesses
Extravasation
diverticulitis
complication of diverticulosis, inflammation of the diverticula
typically in sigmoid region
ulcerative colitis
inflammatory bowel disease
appearance of ulcerative colitis
Earliest detection: fine granularity of the mucosa
Chronic: haustra pattern absent, tubular looking colon
colon cancer appearance
Polyps
Apple core
intussusception
Telescoping of one part of intestinal tract into another because of peristalsis which forces the proximal segment of bowel to move distally w/in the ensheathing outer portion
intussusception appearance
coiled - spring
disk herniation
protrusion of an intervertebral disk
herniated disk appearance
Requires CT, MRI, or myelography to demonstrate impression of the disk on the spinal cord or individual nerve roots
crohn’s disease
pathology?

crohn’s disease
pathology?
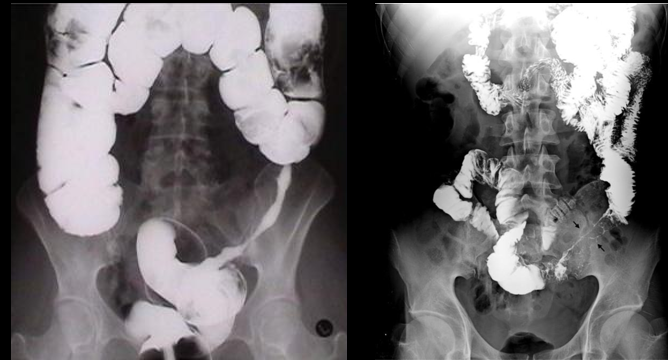
crohn’s disease
pathology?

diverticulosis
pathology?

ulcerative colitis
pathology?
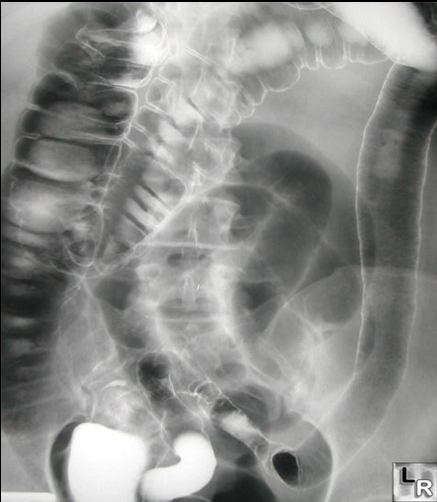
colon cancer (apple core)
pathology?

intussusception
pathology?

PA stomach - 0 minute criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire stomach and duodenal loop
Stomach centered at the level of the pylorus
No rotation of the patient
Penetration of the contrast medium
Surrounding anatomy
Best to see body of stomach; medial, lateral margins
good
PA stomach - 0 minute

RAO stomach critique
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire stomach and duodenal loop
No superimposition of the pylorus and duodenal bulb
Duodenal bulb and loop in profile
Stomach centered at the level of the pylorus
Penetration of the contrast medium
Surrounding anatomy
Best view to see the duodenal bulb filled with barium.
RAO stomach positioning
4” above crest, Bisect spine and lateral border of elevated side, collimate 11x14
PA stomach positioning
4” above crest slightly off center to left, collimate 14 ×17
right lateral stomach critique
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire stomach and duodenal loop
No rotation of the patient, as shown by the vertebrae
Stomach centered at the level of the pylorus
Penetration of the contrast medium
Surrounding anatomy
Best to see the retrogastric area and loop in profile; anterior, posterior margins
right lateral stomach positioning
4” above crest, Bisect axillary line & anterior abdomen, collimate 11x14
BE scout image criteria
All bowel pattern included
Symphysis needs to be included
No rotation
BE RPO critique
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
colon
Left colic flexure and descending colon
Penetration of the contrast medium
no
do you need symph on BE obliques?
left splenic flexure
what flexure is open on a BE RPO?
right side down
how do you mark a BE RPO?
BE LPO criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire colon
Right colic flexure less superimposed or open compared with the AP projection
Ascending colon, cecum, and sigmoid colon
Penetration of the contrast medium
right hepatic flexure
which flexure is open on a BE LPO?
mark left side down
how do you mark a BE LPO?
BE PA criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire colon including the flexure and rectum (two image receptors may be necessary for hypersthenic patients)
Vertebral column centered so that ascending and descending portions of the colon are included
Penetration of the contrast medium
yes
do you need entire large intestine on a BE PA?
yes
do you need symph on a BE PA?
BE PA axial (sigmoid) criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Rectosigmoid area with less superimposition than in PA projection because of angulation of central ray
Transverse colon and both flexures not always included
Penetration of the contrast medium
BE left lateral rectum criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Rectosigmoid area in the center of the image
No rotation of the patient
Superimposed hips and femora
Superior portion of colon not included when the rectosigmoid region is area of interest
Penetration of the contrast medium
deflate balloon
what do you need to do before taking BE left lateral rectum image?
BE post evacuation PA criteria
Same as PA
Entire large intestine is included.
Symphysis included (rectum is on image)
No or minimal rotation (look at ribs, spine and pelvis).
POST
what annotation does your post evacuation PA image need?
Single BE images
scout
PA
LPO
RPO
PA axial sigmoid
left lateral rectum
post evac PA
double BE images
scout
PA
AP
RLD
LLD
PA axial sigmoid
cxt lateral rectum
BE RLD criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Area from the left colic flexure to the rectum
No rotation of patient, as demonstrated by symmetry of the ribs and pelvis
The air inflated portion of the colon is of primary importance and should not be over penetrated
mark up side (left)
how do you mark a BE RLD?
BE LLD criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Area from the left colic flexure to the rectum
No rotation of patient, as demonstrated by symmetry of the ribs and pelvis
The air inflated portion of the colon is of primary importance and should not be over penetrated
mark side up (right)
how do you mark a BE LLD?
AP
how does patient face for RLD?
PA
how does patient face for LLD?
yes
do you need symph for RLD and LLD?
PA
AP or PA?
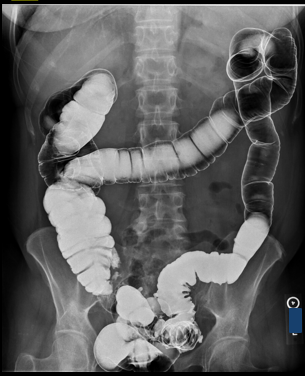
AP
AP or PA?

BE AP (supine) criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire colon including the flexure and rectum (two image receptors may be necessary for hypersthenic patients)
Vertebral column centered so that ascending and descending portions of the colon are included
Penetration of the contrast medium
air
what is seen in the transverse colon in an AP image?
BE PA (prone) criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Entire colon including the flexure and rectum (two image receptors may be necessary for hypersthenic patients)
Vertebral column centered so that ascending and descending portions of the colon are included
Penetration of the contrast medium
barium
what is seen an a BE PA image?
BE PA axial (sigmoid) criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Rectosigmoid area with less superimposition than in PA projection because of angulation of central ray
Transverse colon and both flexures not always included
Penetration of the contrast medium
BE right lateral cxt rectum criteria
Evidence of proper collimation and presence of side marker placed clear of anatomy of interest
Rectosigmoid area visualized and centered
No rotation of the patient
Air-fluid level demonstrated
Enema tip removed for an unobstructed image of the rectum
deflate and take out tip
what do you need to do prior to double BE right lateral cxt rectum image?