Endo Exam 1: Lewis Pituitary/Adrenal
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/64

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
65 Terms
Dopamine antagonists (e.g., ______, ______) cause hyperprolactinemia by antagonizing prolactin secretion
Risperidone, paliperidone
Other drug classes causing drug-induced hyperprolactinemia include ______ (antiemetic), ______/prochlorperazine, ______/reserpine, ______, ______, ______, and protease inhibitors
Metoclopramide, promethazine, methyldopa, BZDs, opioids, H2RAs
Prolactin-stimulating drug classes include ______, ______, ______, estrogens/progestins, 5-HT1 agonists (______), and ______
SSRIs, TCAs, MAOIs, triptans, Verapamil
Among conventional antipsychotics, ______ is most likely to cause hyperprolactinemia, while ______, ______, and ______ are the key ones to know for 2nd generation risk
1st gen antipsychotics, Risperidone, Paliperidone, Olanzapine
______ has a lower risk of causing hyperprolactinemia due to its partial D2 agonist effects; switching to or adding this drug is a management strategy
Aripiprazole
The first step in managing drug-induced hyperprolactinemia is to ______
Remove/stop the offending agent
Medications that cause HPA-axis suppression (secondary adrenal insufficiency) include exogenous steroids (oral, inhaled, topical, intranasal), ______, and progestins such as ______ and ______
Mirtazapine, medroxyprogesterone, megestrol
For hyperprolactinemia, the preferred medical management is a ______ to normalize prolactin, restore gonadal function, decrease Sxs, and decrease tumor size
DA agonist
Bromocriptine's initial dose is 1.25-2.5 mg at ______, increased by 1.25-2.5 mg mg ______, with dosing frequency of ______; half-life is 5-6 hours hours
bedtime, weekly, once daily to TID
Cabergoline's initial dose is 0.25 mg ______, increased by 0.5 mg ______ every ______ weeks, with dosing frequency of ______; half-life is 65 hours (LONG)
twice weekly, weekly, 4, 1-2x weekly
Between the two DA agonists, ______ is preferred over ______ due to better tolerability, better efficacy in normalizing prolactin, and higher frequency of tumor shrinkage
Cabergoline, bromocriptine
For Cushing's syndrome, drug selection is determined by the etiology of the disease (______), individual pt factors (gender, ADRs, DDIs), and ______
ACTH-dependent/independent, cost
Ketoconazole dose range for Cushing's: 200-1200 mg/day. It acts on the adrenal ______ to lower ______ level, and is the most commonly used ______ inhibitor with a generic available
cortex, salt (mineralocorticoid/aldosterone), steroidogenesis
Two additional steroidogenesis inhibitors besides ketoconazole and osilodrostat are Metyrapone and Etomidate (KOME)
KNOW
Pasireotide dose range: 0.3-0.9 mg BID (______), or the long-acting release (LAR) form given as 10 mg ______ every ______
SQ, IM, 4 weeks
Mifepristone dose range: 300-1200 mg/day; this drug is specifically approved to control ______
hyperglycemia
Neuromodulator agents (cabergoline, pasireotide) act ______ (centrally/peripherally) on the pituitary ACTH and are good for ______ (ACTH-dependent/independent) tumors, working via decreased pituitary receptors
Centrally, ACTH-dependent
For adrenal insufficiency, the treatment of choice is ______ replacement, with dosing based on the ______ pattern of endogenous ______
Exogenous glucocorticoid, diurnal, cortisol
Mean adult cortisol production is ______ mg/m²/day, which translates to a hydrocortisone dose of ______ mg/day, cortisone acetate 20-35 mg/day, or prednisolone 3-5 mg/day
5-10, 15-25
If mineralocorticoid replacement is needed for aldosterone deficiency, the drug used is ______ (brand name ______), dosed at 0.05–0.1 mg mg daily, given once daily in the ______.
Fludrocortisone, Florinef, AM
Among glucocorticoids, ______ has the highest potency and ______ has the lowest
Cortisone, Dexamethasone
For a 2-dose glucocorticoid schedule, give ______ of the dose in the AM and ______ of the dose 6–8 hours later
2/3, 1/3
Dopamine agonist adverse effects include ______, ______, and ______; a rare but serious concern is ______ (seen with cabergoline in Parkinson's disease), which is heart valve disease with regurgitation
Nausea, constipation, headache, cardiac valvulopathy
Dopamine agonist withdrawal symptoms (DAWS) upon abrupt discontinuation include ______, depression/fatigue, and ______
Anxiety/panic attack/insomnia, sweating
Ketoconazole carries a Black Box Warning for ______, and package insert recommends ______ ALT monitoring
Hepatotoxicity, weekly
Ketoconazole should be discontinued/dose-decreased if ALT values increase above the upper limit of normal (–) or increase ______% above baseline, or if the patient develops symptoms of ______
7-56, 30, liver failure
Ketoconazole is a strong ______ inhibitor and also carries a Black Box Warning for ______
CYP3A4, QT prolongation
Ketoconazole is contraindicated with antiarrhythmics, Midazolam, Alprazolam, Triazolam, ______, and ______; and should be used with caution with ______ and Warfarin
Lovastatin, Simvastatin, Atorvastatin
Ketoconazole adverse effects include GI intolerance, dermatologic reactions (rash/pruritis), fatigue/myalgias, reversible elevation of hepatic transaminases, and anti-androgenic effects such as ______ (from decreased testosterone production).
Gynecomastia
Osilodrostat may cause hypocortisolism, leading to ______, fatigue, nausea, and headache, as well as dose-dependent ______ prolongation
Adrenal insufficiency, QTc
With osilodrostat, increased cortisol/aldosterone precursor levels cause ______, ______, and ______ (mineralocorticoid effects), while increased androgens cause ______ and ______
Edema, HTN, hypoK, hirsutism, acne
Pasireotide adverse effects include ______, ______ and ______ prolongation, elevated LFTs, cholelithiasis (______), headache, fatigue, and N/V/D.
Hyperglycemia, bradycardia, QT, gallbladder stones
Mifepristone must be avoided in ______ or those trying to become pregnant, as it is a potent ______ antagonist
Pregnancy, progesterone
Mifepristone is a CYP3A4 inhibitor (greater) and CYP2C9 inhibitor (lesser); it is contraindicated with ______ and ______ and the transplant medications ______ and ______
Lovastatin, Simvastatin, Cyclosporine, Tacrolimus
Mifepristone adverse effects include edema/HTN/hypoK (from aldosterone effects), GI effects, fatigue/headache/dizziness, arthralgias, and ______ (from anti-progesterone effects)
Vaginal bleeding
An important physiologic note: aldosterone binds the ______ receptor, but the glucocorticoid receptor ______ (can/cannot) bind cortisol when blocked by mifepristone
Mineralocorticoid, cannot
Chronic glucocorticoid excess (as in over-replacement) can cause adverse effects across systems: Psychiatric → ______ disturbance/psychosis; Skin → ______; CV → ______; MSK → ______; Endocrine → ______ and ______; Ophthalmic → cataract and ______; Developmental → ______
Sleep/Mood, oedema, HTN, osteoporosis, DM, adrenal cortex suppression, narrow-angle glaucoma, growth retardation
Baseline monitoring BEFORE starting a dopamine agonist includes serum ______, ______ (sitting/standing), and ______
Prolactin, BP, echocardiogram
During dopamine agonist therapy, monitor serum prolactin, AEs, and symptom improvement every ______ weeks; once prolactin is normal, measure it every ______ months
4, 6-12
After ______ years of treatment with normal prolactin and no visible tumor, the drug may be discontinued/tapered, with serum prolactin repeated every ______ months
2, 3
Dopamine agonist counseling: take with ______ to reduce GI upset; take the initial bromocriptine dose at ______ due to dizziness/fatigue risk; rise ______ (due to orthostatic hypotension); and do not abruptly discontinue due to risk of ______
Food, bedtime, slowly, DAWS
For diagnosing hypercortisolism, the ______ test is the most useful method to determine excess cortisol; ______ plasma cortisol is not recommended since it requires 2 days of hospitalization; the dexamethasone suppression test uses ______ mg given at ______
24-hour urinary free cortisol (UFC), midnight, 1, night
Cortisol's diurnal rhythm peaks at ______ and is lowest in the ______, but increases later at night
8 am, evening
To determine the cause of Cushing's, check serum ______ level and use imaging (/) for pituitary or adrenal tumor
ACTH, CT/MRI
OSILODROSTAT baseline monitoring includes cortisol level, serum ______ and ______, EKG, and BP; follow-up monitoring includes 24-hr UFC every ______ weeks until clinical response, electrolytes to prevent ______, EKG at ______ after initiating therapy, and ongoing BP/edema/S&Sx of adrenal insufficiency
K, Mg, 2, HypoK, 1 week
PASIREOTIDE baseline monitoring includes urine ______, blood ______, liver function, ECG (QTc/HR), electrolytes, thyroid function (can cause ______), and gallbladder ______; during treatment, monitor blood sugar ______ for the first 2–3 months and liver function ______ for the first 3 months, plus urine cortisol every ______ months
cortisol, sugar, hyperthyroidism, ultrasound, weekly, monthly, 3
Pasireotide counseling should include awareness of ______ Sxs (the "______" — polyuria, polyphagia, etc.), ______ Sxs (abdominal pain, N/V), and proper ______ technique
hyperglycemia, 3 P's, gallbladder stone, SQ
MIFEPRISTONE monitoring includes Cushing Sxs, ______ (watching for it getting too ______), serum ______, and a ______ test; notably, cortisol/ACTH levels are ______ (monitored/not monitored) with this drug
Mifepristone counseling: avoid large amounts of ______ (due to CYP3A4); ______ will not work as well, so use ______ instead; and watch for ______ (muscle cramps/weakness, irregular heartbeat) and ______
Glucose, low, K, pregnancy, not monitored, Grapefruit juice, hormonal contraception, non-hormonal contraception, HypoK, hypoglycemia
Adrenal insufficiency is best confirmed by the ______ test, which (unlike random cortisol) is not affected by diurnal variation; a result showing serum cortisol ______ mcg/dL after stimulation indicates adrenal insufficiency.
ACTH stimulation, <18
A low AM serum cortisol diagnostic of adrenal insufficiency is ______ mcg/dL (< 138 nmol/L), along with an elevated serum ______
<5, ACTH
Glucocorticoid replacement monitoring is mostly based on assessing Sxs every ______ weeks for signs of over- or under-replacement
6-8
Signs of TOO MUCH glucocorticoid include ______, ______, weight ______, ______, and elevated ______
Signs of TOO LITTLE include ______ craving, ______, weight ______, fatigue, and abnormal ______
edema, HTN, Gain, insomnia, glucose, salt, hypotension, loss, Na/K
Ongoing glucocorticoid monitoring parameters include body weight, BP, blood sugar, patient-reported energy, electrolytes (Na/K), eye exams (______ with long-term treatment), bone mineral density, and annual CBC (______ count).
Intraocular pressure, WBC/leukocyte
Glucocorticoid counseling: do not abruptly discontinue (risk of HPA axis suppression); take with ______ to reduce GI upset; take the last dose ______ hours before bedtime; and contact the prescriber for signs of infection, since higher doses may be needed during ______
food, 6, stress/sickness
Glucocorticoids must be tapered rather than stopped abruptly because the body needs time to readjust after ______, which otherwise risks precipitating ______ (since no endogenous cortisol is being made).
HPA axis suppression, adrenal insufficiency
Glucocorticoids should be taken with food because GI upset occurs from inhibition of ______, which normally protect the ______
Prostaglandins, stomach lining
Worked conversion example: A patient takes prednisone 5 mg AM + 2.5 mg PM, and wants to switch to TID hydrocortisone. Total daily dose of prednisone = ______ mg
7.5
The prednisone-to-hydrocortisone (HCT) conversion factor is ______= 4
20/5
The equivalent total daily dose of hydrocortisone = 7.5 mg × 4 = ______ mg.
30
Dividing 30 mg of hydrocortisone into a _____ schedule.
TID

Practice Case (modeled on the TG case in your notes)
Case: JM is a 31-year-old woman who presents to her primary care physician for evaluation of chronic fatigue, unintentional weight loss, and salt cravings over the past 2 months. She also reports occasional dizziness when standing.
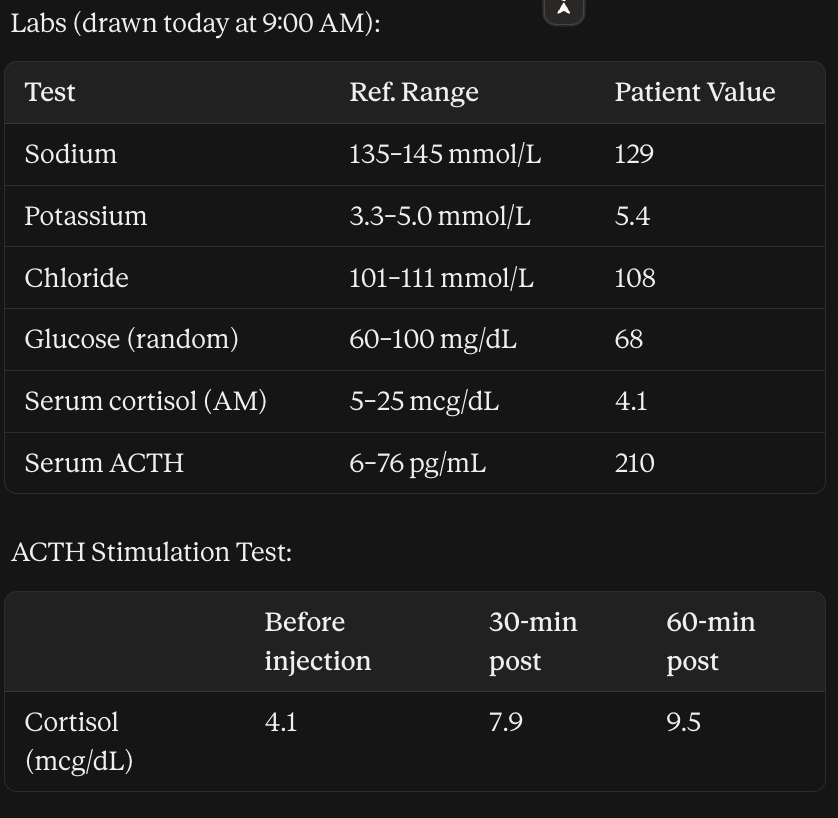
Based on the AM cortisol value and ACTH stimulation test result, does JM meet the diagnostic criteria for adrenal insufficiency? Why or why not? ______
Yes, AM cortisol is <5 and post-stimulation cortisol is <18 at both time points
Practice Case (modeled on the TG case in your notes)
Case: JM is a 31-year-old woman who presents to her primary care physician for evaluation of chronic fatigue, unintentional weight loss, and salt cravings over the past 2 months. She also reports occasional dizziness when standing.
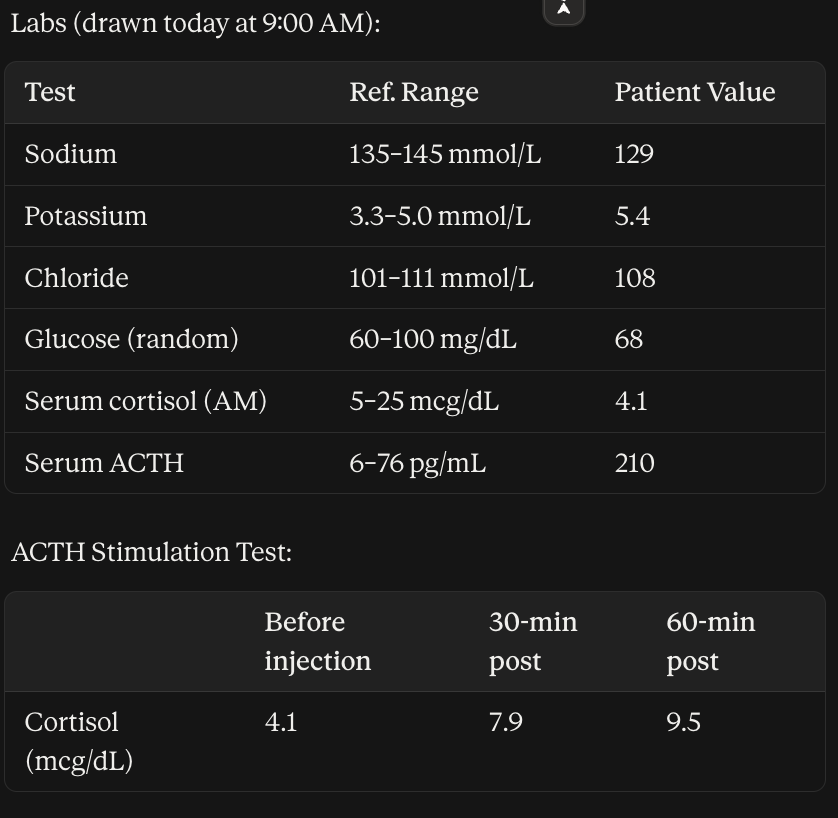
Is JM's elevated ACTH (210 pg/mL) more consistent with primary or secondary adrenal insufficiency? ______
Primary bc the pituitary is trying to stimulate a failing adrenal gland (low cortisol = no negative feedback)
Practice Case (modeled on the TG case in your notes)
Case: JM is a 31-year-old woman who presents to her primary care physician for evaluation of chronic fatigue, unintentional weight loss, and salt cravings over the past 2 months. She also reports occasional dizziness when standing.
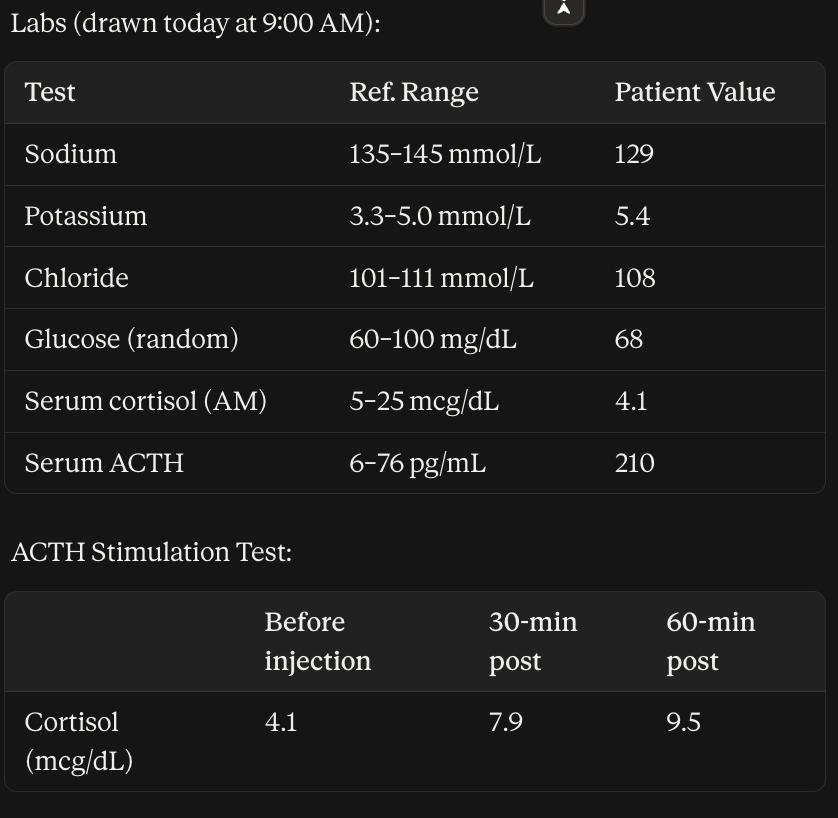
What electrolyte abnormality pattern would you expect with primary adrenal insufficiency (aldosterone deficiency), and does JM's chemistry panel match it? ______
Low Na and High K and JM's labs match it
Practice Case (modeled on the TG case in your notes)
Case: JM is a 31-year-old woman who presents to her primary care physician for evaluation of chronic fatigue, unintentional weight loss, and salt cravings over the past 2 months. She also reports occasional dizziness when standing.
Develop a pharmacotherapy plan for JM (medication, dose, frequency, route) for both glucocorticoid and mineralocorticoid replacement. ______
Hydrocortisone PO divided into 2-3 doses (2/3 AM) for glucocorticoid replacement. Fludrocortisone PO once daily in the AM for mineralocorticoid replacement (aldosterone-deficiency electrolyte pattern)

Practice Case (modeled on the TG case in your notes)
Case: JM is a 31-year-old woman who presents to her primary care physician for evaluation of chronic fatigue, unintentional weight loss, and salt cravings over the past 2 months. She also reports occasional dizziness when standing.
What counseling points should be provided to JM regarding her new glucocorticoid therapy?
______
Take the last dose several hours ______
Never abruptly d/c (risk of ______ from ______ suppression)
Contact prescriber for signs of ______ or ______ since higher doses may be needed during physical stress
Take with food, before bedtime, adrenal crisis, HPA axis, infection, illness