Exam Bank Questions
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/126

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
127 Terms
Why is it important for DH to have good understanding of microorganisms?
Understand oral diseases → Microbes stick to surfaces & leads to gingivitis and perio → immune system reaction
Prevent infection → dental procedures can expose pts to microbes
Maintain infection control → knowledge of microbes help DH properly use sterilization, disinfection, PPE, hand hygiene
Protect pt → some pt have weakened immune system, infectious diseases
Compare & contrast prokaryotic & eukaryotic cells
Prokaryotic:
No nucleus
No organelles
Cell wall: Peptidoglycan
Reproduction: Binary fission
1 circular chromosome
Eukaryotic:
Nucleus
Organelles
Cell wall: cellulose/chitin
Reproduction: Mitosis
Linear chromosome
What are the unique characteristics of bacteria?
Size
Very small, can 2.4×10^11 bacteria /gm of plaque
Large surface to volume ratio → rapid growth + transport
Inhabit vv small ecosystems (dentinal tubules)
Mechanical removal can be difficult
Many diverse species @ single site
Metabolically Diverse
Use full spectrum of nutrients (Carbs, protein, lactate, nylon tires)
Live w or w/out oxygen (aerobic or anaerobic)
Adaptable
Great opportunity for genetic change
Short generation time (time it takes to reproduce) → can divide up to every 40 minutes
Mutation rate 1/106
Genetic info exchanged rapidly
If you give antibiotics, doctors tell you to take them all at once or within a time period because if you don’t, it gives them time to adapt and genetically change so they can become resistant
After becoming resistant, the bacteria can also pass on the gene
Ubiquitous
Ubiquitous → present, appearing, found everywhere at the same time
Present in virtually all environments
Hot underwater fissures that are 300 degrees
Soil, air
Humans → Skin, nose, GI Tract, Genital tract, oral cavit
What does the term “metabolically diverse” mean when describing bacteria?
Explain how bacterial metabolic diversity contributes to their ability to survive in diff environments
Bacteria are able to use full spectrum of nutrients (Carbs, protein, lactate, nylon tires)
Can live w or w/out oxygen (aerobic or anaerobic)
What was the traditional method of classifying bacteria
Staining
Gram stain (Gram + or -)
Ziehl Neelsen → stain used to ID acid-fast bacteria like Mycobacteria tuberculosis
Silver Impregnation staining → Treponema pallidum
Shape
Microscopic
Spherical (cocci)
Rod (baccili)
Macroscopic
Colony
Nutritional Characteristics
What nutrients they consume
Bacteriodes melanogenicus asaccharolyticus → does not ferment carbohydrates
Bacteriodes melanogenicus intermedius → ferments carbohydrates
Fermentation end product
Lactobaccilus species ferments glucose to lactic acid
Cell Wall Comoposition
Ex. Streptococci subdivided based on cell-wall antigens (A-H) w/ the Lancefield Serotypes
DNA Base Composition
Molar Fractions G+C/G+C+A+T
Calculating the % of DNA ratios
Bacteriophage Bacterial virus susceptibility
Classifying bacteria based on whether they are susceptible to certain viruses
Plasmid transfer
Plasmids= small sections of DNA, can be transferred b/w similar grps of bacteria
This is the reason for why bacteria can become resistant to antibiotics
Ex. Enterobacteriaceae bcs bacteria in this family carry plasmids
What are the limitations of traditional bacterial classification and culture-based methods
No sensitivity & poor specificity
Does not ID huge uncultivated majority of microbes
Location: Difficulties in sampling due to physical environment
Organisms mb not capable of adapting in laboratory culture
Lack of essential nutrients, physiological needs/growth factors in culture media. overfeeding, toxicity in culture, inhibitory substances produced by other bacteria, metabolic dependance on other species, disruption of quorum-sensing systems (comm system b/w bacteria to track population density) induced by separation of bacteria, cell in low metabolic state (dormant)
KEY idea is that when you take a sample somewhere, there is thousands of species of bacteria, but you don’t capture all of them, then when you grow them some of them are unable to grow in standard laboratory conditions
Even after successful cultivation, may not be successfully identified
In the traditional method, identification mb heavily based on phenotypic (observable) characteristics, which you compare to reference slides but its so subjective, it might be done incorrectly → Misidentification
Why are some microbes unable to adapt to laboratory conditions?
Organisms mb not capable of adapting in laboratory culture
Lack of essential nutrients, physiological needs/growth factors in culture media. overfeeding, toxicity in culture, inhibitory substances produced by other bacteria, metabolic dependance on other species, disruption of quorum-sensing systems (comm system b/w bacteria to track population density) induced by separation of bacteria, cell in low metabolic state (dormant)
KEY idea is that when you take a sample somewhere, there is thousands of species of bacteria, but you don’t capture all of them, then when you grow them some of them are unable to grow in standard laboratory conditions
What is 16sRNA and why is it important in bacterial identification and classification?
16sRNA=part of machinary that bacteria uses to make proteins from amino acids
16sRNA when bound to ribosomal proteins make 30S subunit of ribosome
Gene that codes for 16sRNA found in all bacteria, part of sequence = conserved, so once the scientist find the conserved part, they can amplify it and look at the variable gene sections to classify the bacteria
Stable + present in all organisms
Sequence must be conserved sufficiently that regions of homology can be clearly established
Must be sufficiently large that info is adequate to make phylogenetic inferences
What is the modern method used to determine bacterial classification & ID bacterial species?
Using gene and molecular biology with 16sRNA and PCR (Polymerase chain reaction) to amplify the DNA
You can use 16S rRNA to determine phylogeny of bacteria (relationship of organisms based on evolution)
Can be used for accurate & rapid identification of known bacterial species (PCR)
16S rRNA to differentiate, quantify, classify unknown species (esp those that cannot be cultivated)
Can be used for phylogenetic reclassification (classifying organism based on how evolutionary related they are) because similar 16sRNA= more similar
Classifying microbes based on evolutionary relationship = more stable, less likely to need additional revision
16sRNA= documents evolutionary history >2000 sequences determined for bacteria but 16sRNA makes up only 0/05% of the genome
What is the mechanism of polymerase chain reaction (PCR)?
Requires:
Template DNA → DNA w/ target sequence
Primers → short DNA sequence that defines region to be amplified
DNA polymerase → heat-stable enzyme like Taq polymerase
Nucleotides (dNTPs) → building block for new DNA
Buffers + ions like Mg3+
3 Steps
Denaturation ~95C
Double stranded DNA separate into 2 single strands
Annealing ~50-65C
Primer bind to complementary sequence on DNA strands
Extension ~72C
DNA polymerase extends the primers and synthesizes new DNA strands
3 steps repeated 25-40 cycles, bcs DNA approx doubles each cycle, target sequence increases exponentially, generated millions of copies
Rapidly identifies viruses like HIV, Hepatitis…if you get poked by needle this is what is used
What are the two major pathways used by bacteria to generate ATP?
CONFIRM W/ NAJAR
Fermentation
No electron transport chain
ATP produced thru substrate-lvl phosphorylation
Organic molecule= final electron acceptor
Net gain= 2 ATP
Used by subg plaque
Respiration
Electron transport chain
ATP produced thru oxidative phosphorylation
External final electron acceptor
Aerobic= O2 is final electron acceptor
Anaerobic= Nitrate is final e- acceptor
Net gain= 38 ATP
How much ATP can be generated thru cellular resp compared w/ fermentation?
Cellular resp can generate 38 ATP and fermentation only 2 ATP
Which is more energetically efficient for bacteria: cellular respiration or fermentation?
Cellular resp=more NRG efficient than fermentation bcs it uses
Glycolysis
Electron transport chain
Oxidative phosphorylation
BUT fermentaiton can be advantageous with external electron acceptor=unavailable bcs bacteria can cont producing ATP w/out electron transport chain
Compare & contrast obligate aerobes, obligate anaerobes, facultative anaerobes, aerotolerant anaerobes
Obligate aerobes= Require O2
Obligate Anaerobes= die in O2
Facultative anaerobes= Respire in O2, ferment other wise (SWITCH)
Aerotolerant Anaerobes= Always ferment BUT have limited capacity to detoxify partial reduction products of O2
What are the sources of carbon and NRG for chemoheterotrophic bacteria?
Chemoheterotrophs include animals, fungi, and most other bacteria
Use oxidation-reduction reactions to produce ATP
Use organic molecules to supply itself with oxygen
What are Koch’s postulates
Microorganism must be demonstrable in all cases of disease
Microorganism must be isolated from diseased animal + grown in pure culture
Microorganism from pure culture must cause disease when inoculated into healthy animal
Experimentally infected animal must contain microorganism

What are the limitations or problems associated with Koch’s postulates?
Not all diseases are caused by microbes!!!
Auto-immune
Cancer
Asymptomatic
For Perio=
Inability to culture all organisms
Difficulties defining + culturing sites of active disease
Lack of animal model system
What is Socransky’s criteria?
Criteria for whether a microbe can be considered a periodontal pathogen
Must be associated w/ disease → increase in # of organisms at diseased site
Must be eliminated/decreased in sites that demonstrate clinical resolution of disease w/ treatment (mechanical or antibiotics)
Must demonstrate host response (alteration in host cellular or humoral immune response)
Must be capable of causing disease in experimental animal model
Must demonstrate virulence factors responsible to enable microbe to cause destruction of periodontal tissue
Name 6 bacterial species commonly found in root canals associated w/ teeth w/ necrotic pulp
Eurobacterium
Lactobacilli spp
Enterococcus
Streptococcus
Actinomyces spp
Peptostreptococcus
Name 5 bacterial species commonly associated with periodontal disease CONFIRM if genus or species
Eikenella
Clostridium
Porphyromonas
Selenomona
Actinobacillus
What is the causative organism of oral thrush (oral candidiasis)? Identify the organism and explain what the presence of oral thrush may indicate about the patient's underlying health or immune status.
Candida albicans which is a naturally occuring fungus in the skin, and oral cavity and is typically kept in check by immune system. It is oppurtunisitic so if immune system down it can turn into overgrowth, meaning pt has compromised immune system
What factors affect microbial growth in oral cavity?
Temperature
Human mouth is 35-36C affects bacterial metabolism, enzyme activity, habitat
Redox potential (anaerobiosis)
Gradients of O2 [ ] and Eh(redox potential) exist in plaque in oral cavity
Some areas in plaque high in O2, deeper= lower
Affects type of microbes that can be found
pH
Most microbes require pH ~7 (Regulated by saliva)
Nutrients
Endogenous saliva → Can be both + and -, helps bring in WBCs but also helps microbes grow by regulating the environment for them
Exogenous saliva → What we eat
Adherence
Chewing + saliva will detach
Soft tissue desquamation limits bacterial load
Hard tissue=high biofilm
Antimicrobial agents & inhibitors
Dentifrices
Mouth rinses
Antibiotics
Host defences
Innate immunity
Non-specific immunity
Specific immunity
What properties of the oral cavity make it suitable habitat for microbial growth?
Oral cavity=suitable habitat for microbial growth bcs it is a continuous culture system, receives constant supply of nutrients from saliva, GCF, desquamated epithelial cells
Also variety of surfaces, like nonshedding tooth surfaces & specialized mucosal surfaces, provide diff environment for microbial attachment and colonization
Saliva provides nutrients + buffering capacity, GCF provides serum-like nutrients + host defense components
What role does saliva play in bacterial growth in oral cavity
Saliva provides nutrients + buffering capacity (buffers salivary pH) for bacteria
BUT saliva also contains antibodies IgG and IgA that can inhibit bacterial growth
What difficulties are encountered when studying oral microbiota?
High species diversity
Surface attachment/Coaggregation → since oral bacteria attach to surfaces, collecting one sample does not guarantee that you sample all
Obligate anaerobes → some oral microbiota do not grow well in lab bcs they die in O2 but will get exposed to O2 if put into lab
Fastidious nutrition → some oral microbiota have specific nutritional requirements
Generation time → some microbes take a vv long time to divide
Identification problem
Difficultues w/ sampling environments
Describe the process of bacterial distribution and colonization in the oral cavity.
6 Stages
Transmission → saliva from mother, food, milk, water
Acquisition → microbes enter mouth and colonize surfaces (epithelial & hard surfaces)
Pioneer species → first organisms to colonize usually (Streptococci, staphylococci, neisseria, veilonella)
Grow until they meet environmental resistance
Physical forces (epithelial shedding, shear forces)
Chemical factors (saliva, Eh <redox>, pH, nutritional requirements
Succession → Metabolic activity of pioneer community modifies environment, makes it suitable for new bacterial populations to colonize
Allogenic factors:
Physical environement
Eruption of teeth
Acrylic obturators for cleft palate (used in pts to mimic palate, provides hard surface for bacteria)
Autogenic factors
Toxic end products
Cryptotypes (receotors)
Receptors/binding sites where pioneer species bacteria attaches and modifies it so other bacteria can stick on it too
Metabolism/Eh
Ex. pioneer bacteria consume o2, Eh decreases, environment becomes more anaerobic and anaerobic bacteria can grow there
Increasing species diveristy
Climax community
Not static (highly dynamic)
Stable due to complexity
What are pioneer species?
First organisms to colonize oral cavity from transmission, typically with saliva from mother, food, milk, water, and grow until they meet environmental resistance factors
Usually streptococci, staphylococci, neisseria, veilonella
What factors cause pioneer species to stop growing or become replaced by other
microorganisms?
Pioneer species=first microbes to grow in oral cavity, initially grow bcs environment is suitable but then as they grow, they encounter environmental resistance factors
Two main categories
1.Physical forces
Epithelial shedding → oral mucosa shed and take other microbes with it
Shear forces → chewing, swallowing, can remove microbes
2.Chemical forces
Saliva → wash away microbes + have antimicrobial components
Eh (redox potential) → environment changes as oxygen in consumed, less suitable for microbes that need oxygen
pH → certain microbes grow in specific pH
Nutritional requirement → Nutrients can become limited or diff nutrients become available
Name 3 examples of pioneer species found in oral cavity
Streptococci, staphylococci, neisseria, veilonella
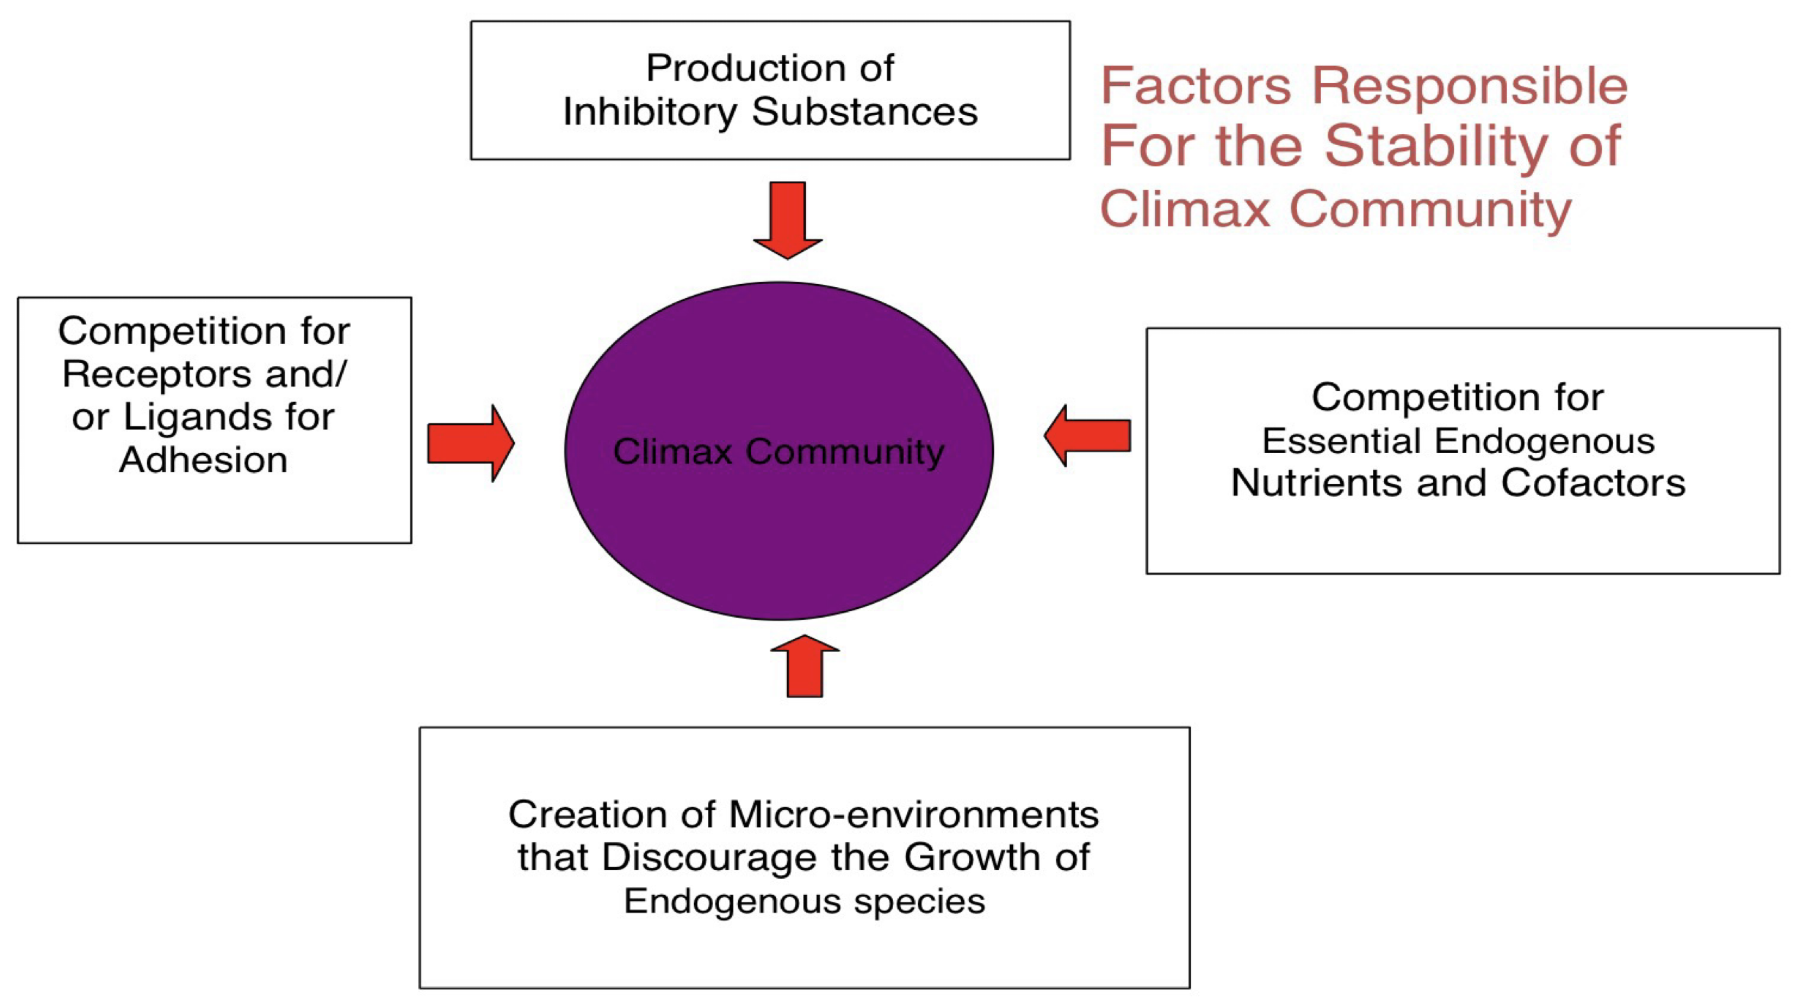
What factors are responsible for maintaining the stability of a climax community?
Explain the factors that contribute to the development and maintenance of a stable
microbial community.
Competition for receptors/ligands for adhesion
Bacteria need to attach to surfaces/other bacteria
Established bacteria=limits ability of other bacteria to colonize
Competition for essential endogenous nutrients/cofactors
Bacteria need nutrients + other substance to grow, established bacteria can use up resources, limit whats available
Production of inhibitory substances
Some bacteria produce substance that inhibit/kill other bacteria
Creation of micro-environment that discourage growth of endogenous specieis
Established species can change local environment and make it difficult for other bacteria to grow like pH, O2 [ ]
What factors can cause/interrupt/disrupt climax community?
EXCEPTIONS
Pregnancy → hormonal changes alter environment
Tooth eruption in children → creates new surfaces
Disease (cancer/immunosuppression) → change in host defense
Denture wearing → artificial surface that changes oral environment
What is the difference between allogenic and autogenic factors?
During the succession stage where the environment changes and the pioneer species evolve there are allogenic and autogenic factors that contribute to the change.
Allogenic factors= environmental changes caused by external physical factors like eruption of teeth, and use of acrylic obturators
Autogenic factors= envionmental factors caused by microbes itself
production of toxic end products
Cryptotypes (receotors)
Receptors/binding sites where pioneer species bacteria attaches and modifies it so other bacteria can stick on it too
Metabolism/Eh
Ex. pioneer bacteria consume o2, Eh decreases, environment becomes more anaerobic and anaerobic bacteria can grow there
What are the major factors involved in the development of dental caries?
Host → have to be susceptible, saliva, tooth anatomy, OH, other host factors
Time → the other factors need to interact in sufficient duration
Microflora → need to have the bacteria that causes caries
Diet → fermentable carbohydrates (which lowers pH of mouth)
Name five cariogenic bacteria
S. mutans
Lactobacilli
S. sobrinus
S. sanguis
S. Mitis
Actinomyces naeslundii
A. casei
Describe the development of dental plaque in the oral cavity.
Explain the process from initial bacterial attachment through the development of a mature plaque biofilm.
a) What factors facilitate attachment of bacteria to acquired pellicle?
b) What are major stages/layers involved in plaque development
a) Factors= Enamel pellicle which is a thin protein rich film formed from saliva & GCF, contains receptors & binding sites for bacteria to attach
Provides host ligands for attachment=, Acidic proline rich (S. mutans), Amylase, Lysozyme, Immunoglobulins, Albumin
AND
electrostatic interactions (Divalent cations, hydrogen bonding, ionic interaction, hydrophobic bonding)
b) First stage= development of supragingival plaque
After tooth is clean, acquired dental pellicle is formed, saliva deposits host proteins & glycoproteins on enamel, creating acquired enamel pellicle. Pionner species bacteria bind to host ligands on dental pellicle (adherence)
Once bacteria attach → begin dividing and aggregate
THEN allow diff bacterial species to attach and COaggregate
Second stage= development of subgingival plaque
Forms when supragingival plaque migrates into sulcus then inlammation creates subgingival environment
Mostly motile bacteria that carry non-motile bacteria in
What is dental plaque?
general term for complex microbial community found on tooth surface
Embedded in matrix of polymers of bacterial & salivary origin
Plaque being calcified is called calculus/tartar
Bacterial members cooperate + signal to each other
Fluid channels carry nutrients + remove waste
What is the difference between aggregation and coaggregation
Aggregation= same type of bacteria clumping together
Co-aggregation= clumping w/ others, diff types of bacteria clumping w each other
One bacteria species attaches to another species within dental plaque
T/F: A 4-mm periodontal pocket contains the same amount of bacteria as a 7-mm
periodontal pocket
FALSE
7mm periodontal pocket generally more bacteria than 4mm because it provides larger, more protected environment for plaque accumulation
Less oxygen= good for subg bacteria
Deeper pocket depth affects amnt + composition of bacteria
T/F: Supragingival plaque can attach more readily than subgingival plaque.
TRUE
Supragingival plaque can adhere to the enamel pellicle which provides ligand and electrostatic bonds directly o the exposed enamel.
Subgingivally, there is less space and oxygen. Access to nutrients and space is more restricted.
T/F: Saliva can have both beneficial and detrimental effects on bacteria in the oral cavity
TRUE:
Saliva provides nutritents
Saliva provides nutrients + buffering capacity (buffers salivary pH) for bacteria
BUT saliva also contains antibodies IgG and IgA that can inhibit bacterial growth
T/F: The generation time of Mycobacterium tuberculosis is approximately 40 minutes
FALSE
Mycobacterium tuberculosis= vv slow gen time ~15-20 hrs
Long generation time makes some microbes difficult to study
What is the average temperature of the oral cavity that supports microbial growth?
Approximately 36–37°C.
Temp is important bcs it affects enzyme activity + metabolic processes
If temp too low= grow too slow
If temp too high= dmg or denature cellular proteins
What are the four electrostatic/physicochemical interactions involved in bacterial adherence and colonization of dental plaque
Divalent cation interactions
Hydrogen bonding
Hydrophobic bonding
Ionic interactions
Explain how changes in the oral environment can influence the microbial community and contribute to dental disease.
In your answer, integrate concepts such as pioneer species, microbial succession, climax communities, plaque development, saliva, diet, and changes in the host environment
Oral cavity= dynamic environment where changes in host environment, saliva, diet, & oral surfaces can alter microbial community.
Pioneer species are are one of the first microbes to colonize the oral cavity.. As they grow, their metabolic activitiy modifies the environment & allows other microbes to colonize. This process is called microbial succession where microbial community changes overtime and develops into a stable climax community.
As microbes attach to tooth surfaces + interact w each other → plaque biofilm develops. Changes in oral environment alter which microbes=favoured.
For example, frequent carbohydrate intake provides nutrients for acid producing bacteria which can lead to caries.
Changes in host environment like salivary flow/composition can affect nutrient availability, buffering capacity, and antimicrobial defenses. Changes in gingival margins and periodontal pockets can create environment that is favourable for species, especially anaerobic species in subgingival pocket areas. Microbial shifts can lead to periodontal disease.
Impaired immune system can also lead to opportunistic infections and allow microbes that usually do not grow there to begin growing
Poor oral hygiene can lead to accumulation of bacteria too because less disruption
What are viruses
Acellular (lacking cells/cell parts)
Obligate intracellular parasites → viruses can only live & reproduce in host cell, not alive
No ATP generating system
No ribosomes or means of protein synthesis
Describe the basic structural components of a virus
Nucleic acid
DNA or RNA (never both)
Capsid (coat protein)
Others: (only some)
Envelope
Enzymes, RT
Reverse transcriptase (enzyme that uses RNA to synthesise complementary DNA strand)
Fill in the blank: Viral specificity is determined by receptor-ligand interactions. ______ are found on the viral capsid or envelope, and _____ are found on the host-cell membrane
Ligands
Receptors
Where are viral binding sites and host-cell receptor sites typically located?
Viral binding sites usually located on surface of virus either capsid or envelope of virus
Uses specific receptors called “spikes”/”peplomeres”
Binding sites on virus must match the receptor site on host
Viruses can only infect narrow range of cells (specific range)
What is a viral capsid?
Made up of capsomeres
Protect viral genome from host endonucleases (enzymes that cut DNA/RNA)
Provide binding sites
What are the 3 major criteria used to classify viruses?
1.Nucleic acid
Viruses can be single stranded or double stranded, and made of DNA or RNA
ssDNA, dsDNA, ssRNA, dsRNA
2.Morphology
Viruses can be 4 shapes: Helical, Polyhedral, Enveloped, Complex
3.Strategy for replication
What are the different methods used to grow animal viruses?
1.Injecting the virus into live animals
Mice, rabbits, guinea pigs
2.Chicken embryos
Most common method, used to make the flu still
3.Cell cultures
Using technology to grow and maintain living cells
Three types → primary cell lines, secondary cell lines, continuous cell lines
Primary cell line
Freshly taken from tissue but die out after a few generation
Diploid cell line
Cell has normal 2 sets of chromosomes
Usually human embryos (high activity, replicate super fast)
Maintained up to 100 generations
What is a continuous cell line
Transformed cancerous cells
Maintained indefinitely
Ex. HeLa cells → piece of tissue from Henrietta ax is 1951 who had cervical cancer (still maintained today)
List and explain the major stages of viral replication
Lytic cycle:
1.Attachment
Binding site on virus must matches receptor sites on host cell (ligand interactions)
2.Penetration
Capsid is removed and viral DNA injected into bacterial cell
3.Biosynthesis
Genome replication, transcription, translation
4.Assembly (maturation)
viral particles assembled
5.Release
Lysis → cell plasma membrane bursts
Lysogenic cycle:
1.Attachment
2.Penetration
3.Integration
Viral genome is integrated into host cell genome
So when host cell replicates itself, it is passively replicating the virus BUT the virus is latent and just hides there
Virus is in a stage of prophage (stage bfr being a complete virus)
*NO BUDDING/NO ASSEMBLY OF NEW VIRUS
4.Biosynthesis
Genome replication
Transcription
Translation
5.Assebly
6.Release
Either through…
Lysis
Budding
Virus can stay latent in the body cells and just budd and create a lot of viruses but then it can become activated by environmental factors and start lysising host cells
What is the difference between the lytic and lysogenic life cycles of viruses?
An extra integration stage in cell replication where Viral DNA/RNA mergers into host cell genome and can remain dormant, copies itself passively along host DNA, and can start replicating and releasing viruses when environmental factors are favourable. Lytic life cycle typically follow through to lysis right away while in the lysogenic stage, once the virus becomes activated, it can also bud or lysis to release the viruses.
What are retroviruses and what is unique about them?
Retroviruses are RNA viruses that make DNA copies of their RNA genome in host cells. Use enzyme called reverse transcriptase to do that and it allows them to hide within our cell’s dd DNA. Is what allows the virus to enter to lysogenic stage
RNA → DNA → mRNA → Protein
Example of retrovirus: Human immunodeficiency virus (HIV)
Explain the process of HIV infection
1.Attachment
HIV gp120 binding site match CD4 receptor sites
CD4 receptor sites found on macrophages, some cells of CNS, T4 Helper cells
2.Penetration
Viral membrane + host cell membrane merge (fusion)
3.Uncoating
Capsid removed, viral genome exposed
4.Integration
Once viral genome integrated = 2 possibilities
Using the reverse transcriptase to convert RNA into DNA to integrate within our cells
Nothing → virus is “latent”, can be latent for days, weeks, months, years
Median latency time= 10 years
ONCED TURN ON=
Biosynthesis
Genome replication
Transcription
Translation
Assembly
Virus particles put together
Release
Budding or lysis
Progressive loss/dysfunction of the WBC
What factors can trigger activation of the integrated HIV genome?
Other infections
Stress/shock to immune system
Drug abuse
Alcohol abuse
Malnutrition
Exercise → lack of/too much
Sunburn
Herpes simplex 1
What are the different routes of HIV transmission?
1.High risk sexual contact
Unprotected vaginal, oral, anal sex
2.Needle
Intravenous drug abuse (sharing dirty needles)
accidental needle sticks
3.Blood to blood contact
Open sores/wounds
Transfusions
Organ transplant
Artificial insemination
4.Mother to child
Placenta
As baby passed thru birth canal
Nowadays if mother has HIV, usually c-section done to protect baby
Breast milk
Once the HIV genome has been integrated into the host-cell genome, what are the two possible outcomes?
1.Nothing
Virus remains latent, can be latent for days, weeks, months, years
Median latency time= 10 yrs
2.Virus is turned on
If environmental factors favourable, the virus can be turned on and enter biosynthesis, assembly and release
What components of saliva can inhibit HIV?
HIV RNA and Proviral DNA have been detected by PCR in saliva BUT there is poor transmission of it through saliva bcs of salivary HIV-1 inhibition
HIV is neutralized
Anti-HIV Antibodies
Broad spectrum innate activities
Lysozyme
Lactoferrin
Defensins
Lactoperoxidases
Viral entrapment + aggregation by mucins (heavy sugar-coated proteins that form the structural component of mucus membranes), inhibits HIV entry into target cell
Really the only way for an HIV infected individual to transmit the virus through saliva is if they had a ulcer on/in the mouth that is bleeding and than that has to come into contact with the healthy person’s ulcer
The virus HAS TO enter the bloodstream
If a person is suspected of being infected w HIV, what is the appropriate testing process?
ELISA is usually If initial ELISA is (+), same sample tested again
If ELISA is (+) AGAIN, then Western Blot test or PCR done
Western blot= Lab method to detect + ID specific proteins, takes the blood proteins and separates them, trying to detect HIV antibody proteins
PCR= amplifies and looks for HIV gene
**In the early stages like if a clinician is poked by a needle, PCR is typically more accurate and is better and catching it sooner than it looks for the HIV gene
T/F: During the first several weeks following HIV infection, tests may produce a false-
negative result even though the person is infected and capable of transmitting the virus.
TRUE because there is a window period between getting infected and when individuals begin producing antibodies. Tests may be negative because the level of HIV antigens, proteins, antibodies are still undetectable. The seroconversion rate is typically 6-8 weeks for antibodies to appear. During that time, the person is considered infected and capable of transmitting HIV
Why has development of an effective HIV vaccine been particularly difficult?
No, HIV mutates too rapidly
Everytime reverse transcriptase is used, it causes at least 1 mutation SO
1 million variants during asymptomatic disease
100 million variants during advanced disease AIDs
So there is no way a single vaccine will be able to target all the genes of HIV
Describe clinical stages of HIV infection
1.Acute infection
Initial infection of HIV from exposure to bodily fluids
Viremia (virus present in blood stream)
Fever
Headaches
Weakness
Muscle & joint aches
Last for ~weeks
Normal CD4= 1200mm³
2.Asymtomatic disease
Virus= “latent” in CD4 cells
Median latency period-10 years
No signs/symptoms (asymptomatic)
HIV positive → antibodies can be detected in blood
Seroconversion= 6-8 weeks (time to make antibodies)
3.Symptomatic disease <can occur after 10 years>
CD4 count <600m³
Viral genome turned on, symptoms begin to appear
Chronic fatigue
Low grade fever
Night sweats
Diarrhea
Weight loss
Susceptible to infection <conditions that we usually don’t see in people, only appearing bcs the immune system is supressed>
Bacterial pneumonia
Meningitis
Oral + vaginal yeast infections
Tuberculosis
Advanced disease (AIDs)
CD4 count <200m³
Severe opportunistic infection
Pneumocysitis carinii pneumonia (PCP) Fungi
Kaposi’s Sarcoma (Cancer of skin + blood vessels)
Toxoplasmosis (brain) protozoan
Cryptosporidiosis (GI tract) protozoan
Other bacterial, fungal, viral infections
What are different types of viral infection?
Two main categories
Acute
Short-term, rapid onset and relatively rapid resolution
Follow lytic sequence of events
Cell exhibit cyotpathic effect (kills cells)
Immune system activated to neutralize infection + eliminates virus
EXAMPLE: INFLUENZA
Persistent
Latent
No infectious virus present
Viral genome present
Can stay latent in nerve ganglion
Virus can be reactivated/gene can be expressed if environmental factors are favourable
Ex. Stress, pregnancy
EXAMPLE: Retroviruses, HSV (Herpes), VZV
Chronic
Infectious virus present
Virus is in circulation, usually not causing too much harm
Usually no tissue pathology
Common for RNA viruses
EXAMPLE. HIV
Slow
Infectious virus present only after LONG incubation period
EXAMPLE: Measles-Subacute Scholerosing, Pan-encephalitis
Does an acute viral infection generally follow a lytic sequence of lysogenic cycle?
Acute viral infection usually follows a lytic sequence because they are short-term, rapid onset and rapid resolution. Similarly, the lytic cycle allows viruses to rapidly replicate, release viruses, and lyse cells. In an acute infection, cells typically exhibit cytopathic effect and there is no incubation phase, which is present in the viruses that follow the lysogenic cycle.
What are prions?
Proteinaceous infectious particle
Misfolded protein
Contains no envelope, capsid coating, or nucleic acids
Usually there are healthy proteins that the brain secretes and releases, but then if a misfolded protein called a prion appears (sporadic, genetic, acquired), it causes other proteins in the brain to become misfolded which creates plaques in the brain and damages neurons
Name 2 diseases caused by prions?
Scrapie (degenerative disorder in sheep)
Creutzfeldt-Jacob disease (CJD)
Kuru (Occurs in tribes in New Guinea)
Bovine Spongiform Encephalopathy (BSE_
Mad cow disease
How does the immune system function to eradicate an infection from the body?
The immune system has two pathways it uses to eradicate an infection from the body. The innate immune system consists of many cells that provides a rapid, non-specific response that targets the microbe. These cells are typically divided into four categories
Phagocytosis: process where a microbe is engulfed by cells like dendritic cells, macrophage, monocytes, polymorphonuclear granulocytes
Complement: Cascade of protein that increase inflammation, opsonize microbes, and forms the MAC (membrane attack complex)
Natural killer cells: kill modified self cells like virus infected or cancerous cells
Soluble proteins
Acute phase proteins → found in blood circulation and increase during infection (Prekallikrein → vasodilation), CRP
Lysozyme → enzymes in tears
Cytokines →
IFN (release by lymphocytes to signal infection)
IL → modulate immune response
Haemopoietic growth factors → regulate haempoiesis, stimulates bone marrow to produce immune cells
The innate immune system typically works minutes to hours following infection. If the pathogen is not irradiated, than the adaptive immune system is activated which is stronger, specific, and has memory.
The first step in the adaptive IR is antigen presentation, this is when antigen presenting cells (APCs) like dendritic, monocytes, and macrophages take up the antigen, process it, and display it onto their MHC Class II molecules. A CD4+/T-helper cell than binds to it through the Th receptor and reads the antigen. Depending on the cytokines and pathogen, it releases cytokines to go down one of two routes.
If the antigen is intracellular, the T-helper cell sends cytokines causing naive T cells to differentiate into Th1 and releases cytokines IFN-gamma and IL12. This activates CD8+/Cytotoxic T-lymphocytes. The infected cells also process the antigen and load it onto MHC Class I molecules, which is read by CD8+/CTL with the help of T-helper cells. The CTL than uses peforins and granzymes to lysis the cell, or uses a death-litigation receptor which programs cell death.
If the antigen is extracellular or soluble, the T-helper cell sends cytokines to activate naive T cells into Th2. The Th2 cells than secrete cytokines like IL4,6,13 which acitvates B cells. Once the antigen binds to the population of B cells with that specific antigen receptor, the B cells also process the antigen by taking it in and loading it onto MHC Class II molecule. This is read by Th2 cells which activate B-cells to proliferate and differentiate into plasma cells which produce antibodies, and memory B cells. Antibodies help eliminate pathogens by neutralizing it, opsonizing it for phagocytosis, and activating the complement system.
How does immune system respond differently to intracellular and extracellular infections?
If the antigen is intracellular, the T-helper cell sends cytokines causing naive T cells to differentiate into Th1 and releases cytokines IFN-gamma and IL12. This activates CD8+/Cytotoxic T-lymphocytes. The infected cells also process the antigen and load it onto MHC Class I molecules, which is read by CD8+/CTL with the help of T-helper cells. The CTL than uses peforins and granzymes to lysis the cell, or uses a death-litigation receptor which programs cell death. This is called the cell-mediated immune response.
If the antigen is extracellular or soluble, the T-helper cell sends cytokines to activate naive T cells into Th2. The Th2 cells than secrete cytokines like IL4,6,13 which acitvates B cells. Once the antigen binds to the population of B cells with that specific antigen receptor, the B cells also process the antigen by taking it in and loading it onto MHC Class II molecule. This is read by Th2 cells which activate B-cells to proliferate and differentiate into plasma cells which produce antibodies, and memory B cells. Antibodies help eliminate pathogens by neutralizing it, opsonizing it for phagocytosis, and activating the complement system. This is called the humoral immune response.
What are the two major antigen-presentation pathways.
MHC Class I, which occurs at the site of infection, it involves infected cells loading the antigen onto MHC Class I molecules and presenting it to Cytotoxic T-lymphocytes
MHC Class II, which occurs in peripheral tissues and lymph nodes where APCs like dendritic, monocytes, macrophages capture antigens and load it onto MHC Class II molecules and present it to T-helper cells
Where does antigen presentation occur?
The first antigen-presentation pathway takes place when the adaptive immune system gets activated. APCs like dendritic, macrophage, monocytes take up the antigen, load it onto their MHC Class II molecules, which is read by T-helper cells which helps sends cytokines to activate either the cell-mediated immune response or humoral immune response.
The second antigen-presentation pathway takes place in either the cell-mediated or humoral immune response. In the cell-mediated immune response, infected cells that have intracellular pathogens in them, process the antigens and load it onto MHC Class I molecules, which is read by Cytotoxic T-lymphocytes that eliminate them. In the humoral immune response, in order for B cells to make antibodies, they have to also process the antigen. B cells will take up the antigen and load it onto MHC Class II molecules which are read by Th2 helper cells to activate them to proliferate into plasma cells to secrete antibodies.
Describe innate and adaptive immunity
The major difference between innate and adaptive immunity is that innate immunity is rapid and non-specific. It does not require antigen-presentation and can target a wide variety of pathogens and can respond as quickly as a few days to hours. However, it is weaker and if it cannot get rid of the pathogen, it will switch to the adaptive immune response which is stronger, specific (antigen-presentation to target specific antigen), and has memory so subsequent exposure can warrant a faster and stronger response.
What components make up the innate immune system?
Typically categorized into four components
Phagocytosis where microbes are engulfed by phagocytes like monocytes, macrophages, PMNs and dendritic cells
Complement system is a cascade of soluble proteins that activate to increase inflammation and bring more lymphocytes over, opsonize pathogens for phagocytosis, and activates a membrane attack complex that lysis pathogens
Natural killer cells do not have antigen receptors, attack modified self cells, and have cytotoxic granules.
Soluble proteins
Acute phase proteins which are found in blood and increase during inflammation like prekallikrein which vasodilates, and CRP
Lysozyme → tears
Cytokines
IFN produced by infected cells to signal immune system
IL → modulate immune system
Haemopoietic growth factor → regulate haemopoesis in bone marrow, can stimulate formation of WBCs
Name 6 types of cell that make up the innate immune system
1.Mast cell
Found in submucosa/dermis, protect epithelial surface from pathogens
Releases substances like
Histamine, SRS-A , Leukotriene → inflammation
Proteases → Break down proteins
Cytotoxic peptides
Heparin → anti-coagulant
2.Macrophage
Monocytes move to tissues can differentiate into macrophages called tissue-bound macrophages, or macrophages already there are resident macrophages
Phagocytose and antigen-presentation
Brian → microglial
Lung → alveolar macrophages
Skin and lymph node → dendritic cells
Liver → kuppfer cells
3.Monocyte
Found in blood circulation
Two activation pathways
1.Classifically activated → monocytes will migrate to tissue if under presence of TFN-gamma or LPS to becoem macrophages → pro-infammatory, antigen-presenting and phagocytoses, recruiting other WBCs. Can also use respiratory burst where it generates reactive oxygen species
2.Alternatively activated → anti-inflammatory, tells immune system to calm down, support tissue regeneration and repair
4.Basophil
Inc in blood during parasitic or allergic rxn
Release enzymes, raise inflammation, chemotaxis of other WBCs
5.Eosinophil
Inc in blood during parasitic or allergic rxn
Release enzymes, raise inflammation, chemotaxis of other WBCs
6.Dendritic
Tissue bound in T-cell region of lymphatic tissue, blood, and other tissues
Phagocytosis & antigen-presenting
7.Polymorphonuclear granulocyte
Eliminate pathogens w/ 3 methods
1.Phagocytosis
2.Lysis of bacteria outside of cell: releasing reactive oxygen species
3.Nuclear extracellular traps (NETs) → PMNs sacrifice themselves, releasing nuclei content w/ bactericidal enzymes that form lethal network outside cell
8.Natural killer cell
No antigen receptors
Target modified self cells like virus cells and tumour cells
Have cytotoxic granules
T/F → With innate immunity, repeated exposure to same pathogen leads to faster and stronger immune response
False, the innate immune system does not target specific antigens, its cells are designed to take on all of them. The cells do not have an antigen-presentation system and no memory system. Therefore, even once the pathogen has been eliminated, the innate immune system has no memory cells that will remember the pathogen and create a stronger and faster response. This is something the adaptive immune system has.
What are the major advantages of adaptive immunity compared with innate immunity
Specific → through antigen-presentation process, the immune cells are directed towards eliminating the specific antigen
Stronger → Activates stronger WBCs like B and T lymphocytes which produce antibodies or activates cytotoxic T lymphocytes
Memory → Memory B and T cells are also produced which helps the immune system “remember” the antigen and what response it used to eliminate it. Subsequent exposures will lead to stronger and quicker response.
What mechanical and chemical barriers contribute to innate immunity
Skin provides physical barrier against pathogens
Mucus membranes like nasal passages and in airway/bronchioles can catch pathogens
Lysozymes in tears, saliva
Acidic pH in vagina, urine, stomach, seminal fluid
What mechanisms do polymorphonuclear leukocytes (PMNs) use to destroy/immobilize bacteria?
1.Phagocytosis
2.Lysis of bacteria outside cell → PMNs releasing reactive oxygen species
3.Nuclear extracellular traps (NETs) → PMNs sacrificing themselves to release nuclei content with bactercidal enzymes creating lethal network
What are the major characteristics and functions of natural killer (NK cells)
Characteristics:
Come from lymphoid lineage and circulate in blood
Part of the innate immune system
No antigen receptors
Contain cytotoxic granulues
Function:
Eliminate modified self cells like virus-infected cells or cancerous cells
Modulate immune system
Produce cytokines
What are the roles of MHC Class I and MHC Class II activation?
MHC Class I interacts with CD8+ or cytotoxic T-lymphocytes. Infected cells load the antigen onto the MHC Class 1 molecule which is read by the T receptors on cytotoxic T-lymphocytes and results in the elimination of the cell
MHC Class II interacts with CD4+ or T-helper cells. APCs like dendritic, macrophage, monocytes process the antigen and load it onto their MHC Class II molecules and is read by the T receptors on Thelper cells which aids in determining whether it is the cell-mediated, or humoral immune system activation
What receptors are involved in phagocytosis?
1.FC receptors: FC receptors on phagocytic cells bind to the FC portion on antibodies
2.C receptor: C receptors on phagocytic cells bind to C3a protein molecules which coat pathogens when the complement system is activated
3.TLR: “Toll-like receptors” bind to components found on pathogen cell surfaces
TLR1/2 → lipoproteins (bacteria)
TL3 → Double-stranded dsRNA
TLR5 → flagellin
TLR9 → unmethylated CpGDNA
Describe the process of phagocytosis
Chemotaxis + adherance of microbe to phagocyte
Ingestion of microbe by phagocyte
Formation of phagosome
Fusion of phagosome w lysosome to form phagolysosome
Digestion of ingested microbe by enzymes
Formation of residual body w/ indigestible material
Discharged waste material
What are neutrophil extracellular traps (NETs)
PMNs sacrifice themselves, releasing nuclei and mixing it with bactericidal enzymes to create lethal network outside of the cell to eliminate microbes
Name 4 types of phagocytic cells
Dendritic cells
Monocyte
Macrophage
PMNs
What are diff types of lymphoid tissues?
Primary lymphoid tissue where lymphocytes mature
1.Thymus → where T lymphocytes mature through positive and negative selection
2.Bone marrow/GALT → Where B lymphocytes mature
Secondary lymphoid tissue → where matured ymphocytes circulate and look out for antigens, move through circulation b/w various organs
Lymph node
Spleen
Skin
Name 5 types of tissue macrophages and ID tissue/organ it is found
1.Brain=microglial
2.Liver=Kupffer cells
3.Blood=circulating monocytes
4.Bone=osteoclasts
5.Skin=Dendritic (Langerhan cells)
EXTRA= Lung=alveolar macrophages
What are the major functions of dendritic cells
Tissue bound, found where in T-cell lymphoid tissues, and other organs
Play a role in circulating to detect for antigens and antigen-presentation
Also phagocytosis
Langerhan cells
Differentiate b/w classically activated and alternatively activated monocytes/macrophages
Classically activated=
When in presence of LPS or TFN-alpha, circulating monocytes will enter tissue where infection is present and differentiate into macrophages. They increase inflammation and tissue damage through non-specific phagocytosis, and releasing cytokines to recruit other WBCs.
Alternatively activated=
Circulating monocytes can also enter area where infection has resolved and release cytokines to promote tissue regeneration and repair, and inflammatory to slow the immune system
What are the different functional roles or modes of blood monocytes?
Circulating monocytes can
1.Phagocytose microbes and debris
2.APC → search for microbe antigens
3.Releasing cytokines to promote inflammation or recruit other immune cells, can also be anti-finflammatory
What are the major roles of anti-inflammatory monocytes
Monocytes can be recruited to areas where infection has resolved, releasing cytokines that slows the immune response (anti-inflammatory), promotes tissue regeneration and repair
What are the major functions of the complement system in innate immunity
1.Increase inflammation → C3a and C5a molecules increase vascular permeability and recruit lymphocytes and other WBCs to area
2.Opsonization → C3b molecules coat pathogens, marking them for phagocytes which can bind to them through C receptors
3.MAC (Molecular attack complex) consisting of C5b6789 which cytolysis microbes by forming pores in the membrane allowing plasma membrane to leak out and water/salt to flow in and compromise the cell integrity
Explain the classical pathway of complement activation
Can be activated via 3 pathways (classical, lectin, alternative)
Classical pathway
Begins with C1 protein complex which has 3 subunits-C1q, C1r, C1s
During infection, C1q can bind to some bacterial surfaces, antibodies on pathogen or CRP *MUST SAY STARTS WITH ANTIBODY ON NAJAR EXAM
C1q binding causes conformational change that activates C1r which activates C1s
C1s than cleaves circulating C4 and C2 into C4a/C4b and C2a and C2b.
C4b covalently binds to pathogen or antibody, than C2b binds to C4b, forming C4bC2b complex called C3 COVERTASE

C3 Covertase than cleaves C3 into C3a and C3b
C3b can do one of two things
First is that many C3b molecules can coat the pathogen surface in process called opsonization, marking it for destruction by phagocytes. Phagocytes have C receptors that recognize the C3b molecule
Second is that C3 binds to C4bC2b complex creating the C5 covertase (C4bC2bC3b) which than cleaves C5 into C5a and C5b
C5a is also released into circulation to recruit phagocytes + increase inflammation
C5b nucleates MEMBRANE ATTACK COMPLEX, binds to C6 forming C5bC6 which then binds to C7 and causes conformation change allowing the C5bC6C7 complex to insert in the pathogen cell membrane
C8 then binds to the complex and causes another conformational change that allows it to insert into the plasma cell membrane
Then C9 polymerizes within cell membrane forming pore that allows water and salt to flow out the cell causing lysis
What are the functions of the complement by-products C3a and C5a?
C3a and C5a play a role in increasing inflammation. It gets released into circulation, increasing vascular permeability and recruiting other WBCs/lymphocytes to the site
What is the membrane attack complex (MAC)
Complex of complement proteins C5bC6C7C8C9 that causes cytolysis in the pathogen. It inserts into the pathogen’s cell and plasma membrane, causing the cell cytoplasm contents to leak out and water and salt to flow in compromising cell integrity.
Define cytolysis
Breaking open/rupturing cell membrane causing cell to die
What is the first requirement for activation of the classical complement pathway
Presence of antibody bound to antigen
2 isotypes IgG and IgM that activate classical pathway
1 IgM= enough to activate complement
2 IgG in close proximity required
What is the sequence of complement protein activation in classical pathway?
C1 → C4 → C2 → C3 → C5 → C6 → C7 → C8 → C9
142356789
What are the functions of antibodies in a Th2-mediated immune response?
1.Neutralize pathogens
2.Enhance phagocytosis by making the pathogens for phagocytes
3.Activating complement system
What are the 2 types of T-lymphocytes?
There are two major types of T-lymphocytes. T-helper cells which are CD4+ assist the immune response by binding to APCs and releasing cytokines to help direct the immune response towards cell-mediated, or antibody mediated response.
In the cell-mediated pathway, they can activate CD8+ cells and enhance co-stimulation b/w APCs and the cyotoxic T-lymphocyte.
In the antibody pathway, they activate B-cells by binding to their MHC Class II molecules with the antigen on it to induce proliferation and differentiation into plasma b cells and memory b cells.
The second type is CD8+ or cytotoxic T lymphocytes. These T cells target cells infected by an intracellular pathogen. They eliminate them by producing perforins and granzymes which kills cells through apoptosis. Another method is through a death-litigation receptor, programming cell death.