NMBs
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/48

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
49 Terms
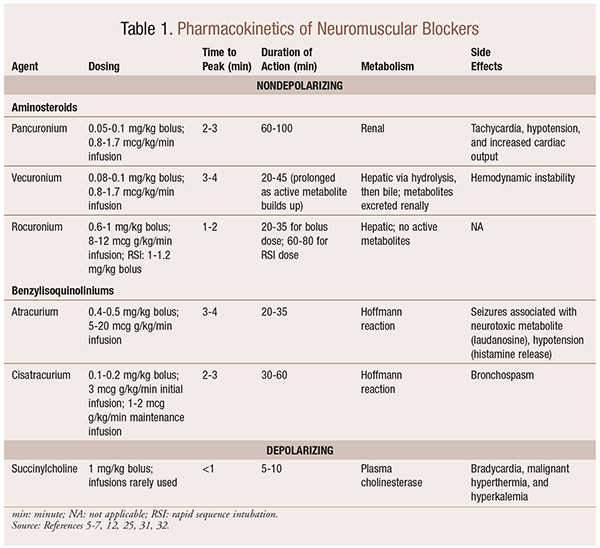
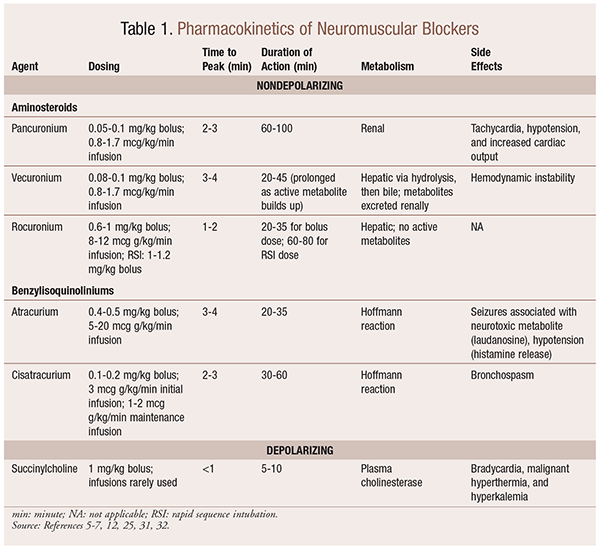
Rocuronium (Dose, time to peak, DOA, Metabolism, AE)
Aminosteroids
Dose: 0.6 - 1.2 mg/kg bolus (RSI 1.2)
Time to peak: 1-2 min
DOA: ~30 min (bolus); ~1 hr (RSI)
Metab: Hepatic >, no active metabolites
Hepatobiliary excretion is the dominant pathway. Rocuronium is taken up by hepatocytes and excreted unchanged into bile.
Renal excretion accounts for a smaller fraction (roughly 10–30% of unchanged drug appears in urine). Renal impairment can prolong its effect but less so than hepatic impairment. (MINIMAL RENAL CLEARANCE; MININAL PROLONGATION IN RENAL DZ + NO ACTIVE METABOLITES)
Hepatic disease (cirrhosis, biliary obs)> PROLONGED PARALYSIS
struction) reduces clearance and can prolong duration of block and delay recovery. Renal failure produces a more modest prolongation, since the hepatobiliary route predominates.
AE:
competetive antag of alpha subunit of nicotinic receptor (muscarinic is glyco/atropine…)
Panrocuronium (Dose, time to peak, DOA, Metabolism, AE)
Aminosteroid
Dose: 0.05 - 0.1 mg/kg bolus
Time to peak: 2-3 min
DOA: 60 - 90 min
Metab: Renal >
Pancuronium is eliminated predominantly by the kidneys as unchanged drug, with limited hepatic metabolism (deacetylation) and a minor biliary route.
Roughly 80% of a dose is excreted unchanged in the urine (ACTIVE METABOLITES unlike roc). Renal failure markedly prolongs the block. Case reports document neuromuscular blockade lasting up to ~60 hours in anephric/acute renal failure patients, especially with large doses and potentiating drugs (
A fraction undergoes hepatic deacetylation. Biliary excretion is small
AE: Tachycardia, HTN, inc CO (The most common and characteristic side effects of pancuronium are cardiovascular—chiefly dose-dependent tachycardia and hypertension—driven by its vagolytic and sympathomimetic actions.)
Vecuronium (Dose, time to peak, DOA, Metabolism, AE)
Aminosteroid
Dose: 0.08 - 0.1 mg/kg bolus
Time to peak: 3-4 min
DOA: 20 - 45 min (prolonged as active metabolite builds up)
Metab: MIXED - Hepatic via hydrolysis, then bile, metabolites renally excreted.
Partially metab by liver with one byproduct that maintains 80% potency. Can build up in pts with liver OR renal failure and cuase residual NMB (panroc also has active metab that can build up with renal/liver insuf; roc has no active metab)
AE: HDiS

Atracurium (Dose, time to peak, DOA, Metabolism, AE)
Benzylisoquinoline
Dose: 0.5 mg/kg bolus
Time to peak: 3-4 min
DOA: 20-35 min
Metab: Hoffman reaction (a nonenzymatic, spontaneous chemical degradation that proceeds at physiological pH and body temperature (base-catalyzed)
Atracurium is unique among nondepolarizing neuromuscular blockers in being eliminated by two organ-independent chemical pathways—Hofmann elimination and nonspecific ester hydrolysis—so its dose need not be reduced in renal or hepatic failure.
Ester hydrolysis — catalyzed by nonspecific plasma esterases (not pseudocholinesterase); its duration is therefore independent of plasma cholinesterase levels and unaffected by pseudocholinesterase deficiency.
No dose adjustment for renal or hepatic failure
TEMPERATURE AND PH DEPENDENT (inc PH and temp speeds degradation)
AE: Histamine release (dose-dependent.), CVD (hypotension, flushing, brady/tachy), bronchospasm
Laudanosine, a major biologically active metabolite lacking neuromuscular blocking activity, causes transient hypotension and, at high doses in animals, CNS excitation (muscle twitching, seizures). It can accumulate during prolonged ICU infusion

Cisatracurium (Dose, time to peak, DOA, Metabolism, AE)
Benzylisoquinoline
Dose: 0.1 - 0.2 mg/kg bolus
Time to peak: 2-3 min
DOA: 30-60 min
Metab: Hoffman reaction
Hofmann elimination degrades cisatracurium into laudanosine and a monoquaternary acrylate metabolite—neither of which has neuromuscular blocking activity. [1-2]
Unlike atracurium, cisatracurium is not directly degraded by ester hydrolysis
TEMPERATURE AND PH DEPENDENT (inc PH and temp speeds degradation)
AE: slow heart rate, low blood pressure, flushing, and skin rash
Compared with atracurium, cisatracurium produces substantially less histamine

Succinylchoine (Dose, time to peak, DOA, Metabolism, AE)
What is a phase II block
DEPOLARIZING
Dose: 1 mg/kg bolus
Time to Peak: <1min
DOA: 5-10 min
Metab: Plasma cholinesterase
succinylcholine is rapidly hydrolyzed by plasma cholinesterase (pseudocholinesterase) to succinylmonocholine—which retains clinically insignificant depolarizing activity—and then more slowly to succinic acid and choline; about 10% is excreted unchanged in the urine
Genetic or acquired pseudocholinesterase deficiency prolongs block. the condition affects roughly 1 in 3,200–5,000 people.
Heterozygous: 1/30 (slight prolongation ~15 min) Homo: 1/3600 (marked prolongation ~2hrs)
Adv: Bradycardia (most common w/ first dose), malignant hyperthermia, hyperkalemia, Rhabdomyolysis, MYALGIA
no antagonist drug, its blockade must resolve spontaneously
When given to pts with pseudocholinesterase def (or when given in high doses ~5 mg/kg), can casue a phase II block that resembles the block caused by non-depol NMBs, including TOF fade, tetanic fade, and post-tetanic potentiation)
According to the FDA-approved drug label, Phase II block is a transition of succinylcholine's action from its normal depolarizing block (Phase I) to a block that superficially resembles a nondepolarizing block, occurring with larger or repeated/prolonged dosing. [1] Its key features:
Mechanistically, Phase II block reflects a shift in the postsynaptic membrane state. A Phase I block is pure depolarization: succinylcholine binds nicotinic receptors, causing sustained depolarization of the motor endplate that inactivates perijunctional sodium channels and prevents further action potentials. It shows no fade to train-of-four or tetanus and no post-tetanic potentiation, and it is potentiated (not reversed) by anticholinesterases. With cumulative exposure, the membrane repolarizes but remains unexcitable, and the block acquires nondepolarizing characteristics — this is Phase II.
Suggamadex
Termination of effect does not depend on metabolism—rocuronium's action can be rapidly reversed at any depth of block by sugammadex, which encapsulates the intact molecule and promotes its renal excretion
Molecular mechanism in detail — Sugammadex has a hydrophilic exterior and a lipophilic (hydrophobic) inner cavity. The positively charged quaternary ammonium nitrogen of the aminosteroid forms electrostatic bonds with the negatively charged (carboxyl/thio-carboxyethyl) groups lining the interior, and the steroid ring backbone is drawn into the hydrophobic core—encapsulating the molecule in a tight, stable, water-soluble 1:1 complex. [3]
"Chelation" pulls drug away from the junction — By binding free rocuronium/vecuronium in the plasma, sugammadex creates a concentration gradient that draws the relaxant away from the neuromuscular junction back into the circulation, where it too is encapsulated. This directly removes NMBA from the acetylcholine receptors, liberating them so muscle activity returns—a fundamentally different mechanism than neostigmine, which works indirectly by inhibiting acetylcholinesterase to raise synaptic acetylcholine
No cholinergic activity — Because sugammadex does not interact with cholinesterase or muscarinic receptors, it avoids the bradycardia, bronchoconstriction, salivation, and PONV of anticholinesterases and requires no co-administered antimuscarinic (atropine/glycopyrrolate). [3][6]
Selectivity — Binding affinity is rocuronium > vecuronium >> pancuronium. Sugammadex does not bind or reverse benzylisoquinolinium (curariform) agents such as cisatracurium or atracurium, nor does it reverse succinylcholine.

How does each NMB get reversed?
Succinylcholine (depolarizing): No reversal agent. Block must resolve spontaneously via pseudocholinesterase (plasma cholinesterase) metabolism. Acetylcholinesterase inhibitors worsen/prolong it, and sugammadex has no effect. [1-2]
Rocuronium and vecuronium (aminosteroids): Reversed by sugammadex (encapsulates the molecule; highest affinity for rocuronium) or by acetylcholinesterase inhibitors (neostigmine, edrophonium). [1][3]
Pancuronium (aminosteroid): Reversed by neostigmine; only weakly encapsulated by sugammadex. [3]
Cisatracurium, atracurium, mivacurium (benzylisoquinoliniums): Sugammadex is ineffective. Reversed only by an acetylcholinesterase inhibitor (neostigmine). Atracurium/cisatracurium also undergo spontaneous Hofmann elimination, and mivacurium is metabolized by pseudocholinesterase, so block resolves without pharmacologic reversal over time
CCB effect on NMBs
CCBs can augment depolarzing and nondepolarizing NMBs. PARTICULARLY when given concurrently to a CCB naive pt. Consider careful titration in these pts. Chronic CCB user, the effect is insignificant.
Cause mild potentiation.
Calcium ions are used in skeletal and SM contraction. CCBs alter ability to cross cellular membrane leaading to less excitation-contraction. Animal studies have shown CCBs cause progressive dose-related reduction in twitch height.
Calcium channel blockers (CCBs) potentiate neuromuscular blockade primarily by disrupting calcium-dependent acetylcholine (ACh) release presynaptically, with additional postsynaptic effects on the muscle membrane. Neurotransmitter release at the motor nerve terminal depends on voltage-gated calcium entry, so CCBs reduce the calcium influx that triggers ACh exocytosis, lowering the safety margin of transmission and adding to the block produced by any NMB.
Verapamil and diltiazem directly inhibit ACh release by blocking calcium entry into the nerve terminal; verapamil reduces the endplate potential amplitude far more in low-calcium conditions, and the effect is antagonized by raising extracellular calcium—confirming a calcium-dependent presynaptic site
TOF
peripheral nerve stimulator; Stimulus is 0.5 sec apart
The train-of-four (TOF) ratio is the amplitude of the fourth twitch (T4) divided by the first twitch (T1) after four supramaximal 2-Hz stimuli are delivered to a peripheral (usually ulnar) nerve; a decreasing ratio reflects deeper block,
and ≥0.9 is the accepted threshold for adequate recovery and safe extubation. [1-2]
TOF assessment has two distinct outputs that are often conflated: the TOF count (number of visible/palpable twitches, 0–4), used to gauge depth of block during maintenance, and the TOF ratio (a quantitative percentage, T4/T1), used to confirm recovery.
TOF count and receptor occupancy (depth of block during surgery):
Count of 0 (no twitches): deep or profound block; correlates with high receptor occupancy. When TOF is absent, depth is further quantified by post-tetanic count (PTC) — deep block is defined as no TOF response with a PTC of 1–2. [4]
Sequential loss of twitches with increasing depth: T4 disappears first, then T3, T2, and finally T1. [2]
Count of 1–3 twitches: moderate block, corresponding to roughly 75–90% of receptors blocked. Return of the second twitch (T2) is a common target for adequate surgical relaxation and the point at which 2 mg/kg sugammadex or standard neostigmine dosing is appropriate.
TOF ratio and percentages (recovery):
The ratio is a percentage of T1: e.g., a TOF ratio of 0.9 = T4 is 90% of T1.
Historically >0.7 (70%) was considered adequate but is now known to be insufficient — a ratio <0.9 is associated with impaired airway reflexes, hypoxic ventilatory depression, upper-airway obstruction, and aspiration risk. [1][5]
≥0.9 (90%) is the current standard for adequate recovery; when measured by acceleromyography, ratios should ideally be normalized to a baseline (which often exceeds 1.0, e.g., 1.1–1.15) or measured by electromyography. [1]
A critical monitoring caveat: subjective (qualitative) assessment cannot detect fade once the ratio exceeds ~0.4, so a "TOF count of 4 with no palpable fade" spans the entire range of 0.4–1.0 and does not confirm recovery. Only quantitative monitoring reliably confirms a ratio ≥0.9.
NMB on paralyzed limbs
If a paraplegic had gotten NMB with rocuronium, posterior tibial nerve TOF woul be more exaggerated that the ulnar
When using peripheral nerve stimulator to assess TOF ratio after NMB, the response produced by stimulation of a nerve in a PARALYZED extremtity is exaggerated compared to a “normal nerve” (INCREASE TOF ratio)
Paralyzed muscles produce extrajunctional acetylcholine receptors, leading to increased response following stimulation. Greatest effect seen in paralyzed extremities for >3 wks
Which anesthetic gas most significantly augments NMB
Desflurane (as much as 60% in healthy pts)
then sevo > iso > halo > TIVA
Des bc its the least potent volatile agen and therefore present in the highest aqueous concentration at equal levels of MAC as compared with iso and sevo
Most pronounced with aminosteroid non-depolarizers
All volatile agents augemnt NMB directly by causing skeletal muscle relaxation and acting synergistically with NMBD.
Direct: relaxation of skel muscle (particularly when MAC >1). Potentiates medication effect postsyn at nicotinic receptor. Pronounced effect in NM disorders that lead to skel musc weakness (MG)
N2O does not directly relax skeletal muscle
Indirect: synergistic action of inhalation anesthetics at the NMJ with NMBDs
volatile inhaled anesthetics produce skeletal muscle relaxation
Volatile agents enhance the potency of nondepolarizing relaxants (vecuronium, d-tubocurarine, etc.), reducing the dose required and prolonging block. At the receptor level, coapplication of isoflurane or sevoflurane increases the inhibitory effect of NDMRs on the nAChR, possibly by enhancing antagonist affinity—most pronounced at low relaxant concentrations.
The classic teaching is that the potency of volatile agents in augmenting nondepolarizing block runs roughly desflurane ≥ sevoflurane > isoflurane > halothane
Peripheral sites — neuromuscular junction:
Postsynaptic nicotinic acetylcholine receptor (nAChR) block: Isoflurane and sevoflurane directly and reversibly inhibit the muscle nAChR. Isoflurane can block ~50% of receptors within 0.5 ms of ACh exposure, reducing endplate current amplitude—an effect partially relieved by high ACh concentrations. [3-4]
Presynaptic reduction of ACh release: At the mouse NMJ, sevoflurane and isoflurane inhibit sodium-dependent, depolarization-evoked synaptic vesicle exocytosis, likely by acting on tetrodotoxin-sensitive voltage-gated sodium channels upstream of calcium entry; KCl-evoked (Ca-dependent) release was not inhibited, localizing the target to Na⁺ channels. Sevoflurane inhibits this evoked release more than isoflurane, paralleling its stronger clinical relaxation. [1]
SCD pt in labor and in crisis… What drugs are appropiate and inappropiate
Appropiate: Acetamin, opioids, labor epidurals (if the pt is in labor)
NSAIDs to be avoided after 32 wks gestation due to risk of premature ductus arteriosus closure in fetus
NSAIDs are generally avoided in the first trimester (miscarriage risk) and third trimester (premature ductal closure/pulmonary hypertension), which increases reliance on opioids for VOC pain in pregnancy
Prolonged opioid use raises risk of opioid use disorder and neonatal opioid withdrawal syndrome, so a long-term pain management plan should accompany therapy.
MOA of NMBDs
Nicotinc ACh receptor is a ligand gated sodium/potasium channel (5 units; 2 alpha, 1 beta/delta/epsilon)
depol requires 1 ACh to bind to EACH alpha receptor (2 AcH) > Na enters > MEPPs occur » depol and excitation/contraction coupling
All NMBDs act at the postsynaptic nicotinic acetylcholine receptor (nAChR) on the motor endplate, but by two fundamentally different mechanisms—depolarizing (agonist) versus nondepolarizing (competitive antagonist). Both prevent acetylcholine from producing effective endplate depolarization, but the way they do so, and the resulting clinical signatures, differ. [1-2]
Depolarizing agent (succinylcholine)
Acts as an nAChR agonist, mimicking acetylcholine. It binds the α-subunits and opens the ion channel, producing sustained depolarization of the motor endplate—seen clinically as fasciculations. [1][3]
Because it is not hydrolyzed by acetylcholinesterase (only by plasma pseudocholinesterase, more slowly), it remains bound far longer than ACh, keeping the endplate persistently depolarized and refractory. Perijunctional sodium channels inactivate, so no further action potential can propagate → flaccid paralysis (Phase I block). [1-2][4]
Structural work shows succinylcholine stabilizes a desensitized-like, non-conducting receptor state via the classical neurotransmitter site
Nondepolarizing agents (aminosteroids + benzylisoquinoliniums)
Competitive antagonists at the nAChR at motor endplate (outcompetes ACh): they bind the α-subunit(s) but do not open the channel, blocking ACh from binding. If at least one α-subunit is occupied, the channel stays closed, the membrane does not depolarize, and the muscle becomes flaccid. [1][6]
The block is concentration-dependent and competitive—raising ACh (via anticholinesterases like neostigmine) shifts the balance and reverses it. Structurally, rocuronium locks the receptor in a resting, non-conducting state. [2][5]
They additionally block prejunctional α3β2 nicotinic autoreceptors, impairing ACh mobilization/release—the molecular basis of train-of-four and tetanic fade, which distinguishes them from succinylcholine. [4][7]
Two chemical classes, same receptor mechanism, differing pharmacokinetics:
Aminosteroids — rocuronium, vecuronium, pancuronium (hepatic/renal elimination). [8]
Benzylisoquinoliniums — atracurium, cisatracurium (Hofmann elimination), mivacurium (pseudocholinesterase).
****Bind alpha > no activation > no Na channel movment > no depol
Structure of the channel
The muscle-type nAChR is a pentamer of five transmembrane subunits arranged concentrically around a central pore: two α₁ subunits plus one β, one δ, and either ε (adult) or γ (fetal/immature) subunit. [1][3]
The two ACh binding sites sit at subunit interfaces (αδ and αε/αγ) in the extracellular domain. Occupancy of both α-subunit sites by two agonist molecules triggers a concerted conformational change that opens a hydrophobic gate located ~50 Å away, in the middle of the membrane-spanning pore. [4-5]
What flows through it - Once open, the channel is a nonselective cation channel: Na⁺ and Ca²⁺ flow inward and K⁺ flows outward down their electrochemical gradients, depolarizing the endplate. [2]
With normal ACh this is transient (channel open a few milliseconds, then ACh hydrolyzed by acetylcholinesterase). With succinylcholine, which is not metabolized by junctional acetylcholinesterase, the channels are held open/repeatedly activated, producing sustained depolarization — the basis of the depolarizing block and of the K⁺ efflux relevant to the hyperkalemia discussed earlier.

How does glycopyrrolate and neostigmine reverse? When to give each?
(Dose, time to peak, DOA, Metabolism, AE)
Neostigmine reverses the block;
DOESNT Cross BBB (Physostigmine is a tertiary amine. It easily crosses the blood-brain barrier and reverses both central and peripheral anticholinergic effects. This CNS penetration is precisely why physostigmine's clinical niche is the central anticholinergic syndrome)
Competitive acetylcholinesterase inhibitor. Acetylcholinesterase has two active sites: an anionic site that attracts acetylcholine (ACh) and an esteratic site that hydrolyzes it. Neostigmine occupies both sites, preventing the enzyme from binding and degrading ACh
ACh accumulates in the synaptic cleft. The rising concentration of ACh outcompetes the nondepolarizing NMBD for the nicotinic receptor's α-subunit binding site, tipping the competitive equilibrium back toward neuromuscular transmission and restoring muscle function.
Ceiling effect: Once neostigmine has inhibited essentially all available acetylcholinesterase, additional drug produces no further reversal — which is why it cannot reverse deep block and why maximal dosing is capped (~0.08 mg/kg, max 5 mg). Recovery therefore depends both on neostigmine's action and on spontaneous decline in relaxant concentration; it works best given at a TOF count of 4 (minimal block)
Neostigmine raises ACh nonselectively, so ACh also accumulates at muscarinic receptors throughout the body. This produces cholinergic effects: bradycardia, bronchospasm/bronchorrhea, salivation, nausea/vomiting, and increased GI motility. Profound bradycardia and even asystole are the feared cardiac consequences.
Glycopyrrolate is a protective adjunct that offsets neostigmine's muscarinic side effects.
Antimuscarinic (competitive muscarinic receptor antagonist). It blocks ACh at peripheral muscarinic receptors on cardiac muscle (SA/AV node), smooth muscle, and exocrine glands, thereby antagonizing exactly the muscarinic symptoms — bradycardia, bronchospasm, bronchorrhea, hypersalivation, GI hypermotility — that neostigmine would otherwise cause.
Critically, glycopyrrolate has no nicotinic activity, so it does not interfere with neostigmine's reversal of the block at the neuromuscular junction (which is nicotinic). It selectively cancels the unwanted muscarinic effects while leaving the therapeutic nicotinic effect intact.
Pharmacokinetic pairing rationale: Glycopyrrolate is preferred over atropine with neostigmine because its slower onset and duration better match neostigmine's time course, giving smoother heart-rate control (atropine's rapid onset can cause transient tachycardia; it is favored with the faster-acting edrophonium instead)
Administer glycopyrrolate ~0.1 mg/kg (or atropine ~0.01 - 0.02 mg/kg) IV several minutes before or concomitantly with neostigmine, in separate syringes
Key limitation: This anticholinesterase strategy works only for nondepolarizing NMBDs (both steroidal and benzylisoquinolinium). It cannot reverse succinylcholine (it potentiates Phase I block), and unlike sugammadex, neostigmine is the only option for benzylisoquinoliniums like cisatracurium/atracurium.
(Neo doesnt cross BBB vs Physostigmine is a tertiary amine. It easily crosses the blood-brain barrier and reverses both central and peripheral anticholinergic effects. This CNS penetration is precisely why physostigmine's clinical niche is the central anticholinergic syndrome)
Muscarinic vs Nicotinic receptors
Structural and signaling differences
Nicotinic (nAChR) — ionotropic. A pentameric ligand-gated cation channel. ACh binding opens a central pore, allowing Na⁺/Ca²⁺ influx → rapid membrane depolarization. Fast, millisecond-scale signaling. The muscle-type receptor at the NMJ has the subunit composition α1₂β1δε (mature) or α1₂β1δγ (fetal/extrajunctional). [3-4]
Muscarinic (mAChR) — metabotropic. A G-protein-coupled receptor with five subtypes (M1–M5). M1/M3/M5 couple to Gq (activate phospholipase C); M2/M4 couple to Gi (inhibit adenylyl cyclase, modulate K⁺/Ca²⁺ channels). Slower, second-messenger-mediated signaling.
Why this dichotomy matters for reversal
Neostigmine is nonselective — by inhibiting acetylcholinesterase, it raises ACh at both receptor types simultaneously. The nicotinic effect is therapeutic (reverses the block); the muscarinic effect is toxic. [1][8]
The two-drug strategy exploits receptor selectivity. Glycopyrrolate is a pure antimuscarinic — it blocks ACh only at muscarinic receptors (cardiac, smooth muscle, glandular), abolishing bradycardia, bronchospasm/bronchorrhea, and GI hypermotility, while having no nicotinic activity. This leaves neostigmine's nicotinic reversal at the NMJ fully intact. [2][9]
Fasciculations vs. muscarinic signs further illustrate the split: succinylcholine's agonism at the nicotinic endplate produces fasciculations, whereas its stimulation of cardiac muscarinic (and autonomic ganglionic nicotinic) receptors contributes to the bradycardia seen especially with repeat dosing. [10]
What happens when you give neostigmine (reversal) when NM function is fully recovered (TOF ratio >0.9)
Paradoxical respiratory muscle weakness. Due to decreases in tone of upper airway dilator muscles and impairment of diaphragmatic function > leading to dec MV
Neostigmine is a anticholinesterase that competively inhibits AcHase. The increases AcH competes with nondepol NMBs for nicotinc receptors. Bc it inhibits at nicotinic and muscarinic sites, an antimuscanrinic (glyco/atropine) is added to dec brady, GI, complete heart block, asystole, broncospasm
Does NOT cross BBB
Neonate/pediatric considerations with NMB dosing
Effect on immature plasma pseudocholinesterase / renal / hepatic systems
Succs: Infants have relative large volume of distribution and need increased weigth-based dosing of most medications for initial effect. they have large extracellular fluid volumes (~40% TBW).
Larger doses are needed in kids for this reason
2/2 dilution from a larger ECF and more rapid redistribution away from effect sites from their high CO
Muscle relaxants that are hepatically or renally cleared may circulate for longer time in neonates due to immature hepatic/renal enzyme metab.
***Neonates have ~50% of the plasma pseudocholinesterase as adults but this does NOT prolong duration of action of succinylcholine
***Fasciculations are typically absent or minimal in neonates and young infants — this is a well-recognized age-related difference. Visible fasciculations after succinylcholine become common only once skeletal muscle mass is more developed (older children and adults), so neonates generally do not manifest the coarse, generalized fasciculations seen in adults.
***Succinycholine is avoided in kids due to possibility of hyperkalemia from an undiagnosed muscular dystrophy. Reseverved for RSI when needed (but still used)
Why is succinylcholine avoided in kids
Due to possibility of hyperkalemia from an undiagnosed muscular dystrophy. Reseverved for RSI when needed
Rocuronium has begun to replace succ for RSI in kids
Burn Pt NMB / Extrajunctional ACh receptors
Extrajunctional nicotinic ACh receptors (compared to postjunctional nicotinic ACh receptor) have a gamma subunit in place of an epsiolon > causes channel to remain open for longer and excessive potassium efflux
Upregulation of receptors = hypersensitivity to agonists (succ) and hyposensitivity to antag (Nondepol)
Mature AcHR: 2x alpha1, 1x beta1, delta, epsilon
Immature receptors: 2x alpha1, 1x beta1, delta, gamma (with alpha7 receptors)
succ depolarized the alpha7 as well
Decrease nondepol sensitivity (Denervation type beat: ie LMN injury, immobilzation, botulinum, tentanus) > muscle atrophy and increased areas AcHr
Dose and concentration response curve SHIFTS RIGHT
5-16 days after immobilations
10 days after burns
Humans are born with a large number of immature extraunctional nicotinic receptors which can be located at any point along the cell surface of a skeletal muscle (as opposed to post junctional mature receptors which are located within the invaginations presents at the NMJ). After birth, these immature extra junctional nicotinic acetylcholine receptors are quickly replaced by mature, post junctional receptors. The immature, extra junctional receptors that tend to proliferate in the settings of burns/paralysis/critical illness caused susceptibility to hyperkalemia in a setting of succinylcholine use
All burn pts have up regulation of extrajunctional AcH receptors thus have an exaggerated hyperkalemic response after succinycholic
****check if it applies to paralyzed pts
pharmacologic paralysis is itself a recognized cause of extrajunctional AChR upregulation, so patients paralyzed for prolonged periods develop the same predisposition to succinylcholine-induced hyperkalemia as burn patients. The burn injury is only one of a broader family of "denervation-like" states; critically, prolonged neuromuscular blockade produces "chemical denervation" that upregulates receptors through the same final common pathway
In normal innervated mature muscle, AChRs are confined to the junctional (endplate) region. Upregulation with spread of AChRs across the entire sarcolemma — plus expression of immature (α1₂β1δγ) and neuronal α7 isoforms — occurs whenever the muscle is deprived of normal neural/agonist activity, regardless of the specific insult. [1]
Martyn and Richtsfeld explicitly list the triggers as upper or lower motor neuron denervation, chemical denervation by muscle relaxants, drugs, or toxins, immobilization, infection, muscle trauma, and burns — all converging on the same upregulated-receptor phenotype that produces exaggerated K⁺ efflux when depolarized by succinylcholine (and its metabolites/choline acting on the α7 recep
Rhabdo? »»» In states of AChR upregulation (burns, denervation, prolonged immobilization/chemical denervation), the dominant lethal risk is hyperkalemia from potassium efflux across the upregulated receptor-studded membrane, not primarily muscle destruction. Succinylcholine-induced rhabdomyolysis is a related but mechanistically separate entity most strongly tied to underlying myopathy — yet the two overlap and both worsen the hyperkalemia. [1-3]
Two overlapping but distinct pathways
Receptor-upregulation → hyperkalemia (the burn/denervation/paralysis pathway). Depolarization of the widespread junctional, extrajunctional, and α7 receptors drives massive K⁺ efflux. This is fundamentally an ion-flux problem; the muscle membrane is not necessarily disrupted, so overt rhabdomyolysis (CK/myoglobin release) is not the defining feature — hyperkalemic arrest is. [1][4]
Myopathy → hyperkalemic rhabdomyolysis (the DMD/occult-myopathy pathway). Here succinylcholine (and volatile agents) causes actual sarcolemmal breakdown with release of K⁺, CK, and myoglobin. This is the basis of the FDA boxed warning: ventricular dysrhythmias, cardiac arrest, and death from acute hyperkalemic rhabdomyolysis in children later found to have skeletal muscle myopathy such as Duchenne muscular dystrophy. [2-3]
Clostridium botulinum toxin MOA
Cleaves SNARE protein which prevents release fo ACh from storage vessicles in NMJ. PRevents ACh vessicles in presyn neuron to bind with membrane. Leads to muscles weakness/flaccid paralysis
Neuron AP > NA influx & depol > VG Ca2+ channels in axon terminal open > Ca2+ enters cell and interacts wit SNARE proteins of storage vessicles containing AcH > fuses vessicle with cell membrane > release ACh
Heavy and light chains:
Heavy: toxin entry into neuron and fusion with ACH vessicles
Light: cleaves SNARE
Organophosphates & Sarin nerve gas
What kind of paralysis
AcHase inhibitors
Permanently bind to and prevent function of enzyme > build up AcH
Brief spasms or spastic paralysis > then longer lasting flaccid paralysis
Lambert Eaton Syndrome
AI destruction/blockage of VG Ca2+ channels at nerve endings.
Decreases Ca2+ influx into neurons > dec AcH > inadequate muscle depol/weakness
Myasthenia Gravis (MG)
AI autoabs destruction of postjunctional ACh receptors.
Nondepolaring NMBs are prolonged
Depolarizing NMBs are shortened 2/2 decreased number receptors available for blockade (Succs binds both alpha units but many are already occupied)
Duchenne Muscular Dystrophy DMD
Effect on NMB (nondepol + depol)
& Becker?
Inherited X-linked recessive (boys); mutation on dystrophin gene which codes for dystrophin protein in muscle
Severe sx: DMD
Later onset, milder course: Becker MD
Clinical onset of weakness age 2-3 yo
Prox muscles (and LE) affected before distal (and UE)
compensatory calf enlargement (pseudohypertrophy)
Difficult running, jumping, walking up steps.
Gowers sign (hands to get up)
***Results in significant muscle wasting and enhanced sensitivity to nondepolarzing relaxants. Due to the dec functional muscle mass, they have a longer duration and higher rish of post op resp failuree with standard dosing.
****Depolarizing agents must be completely avoided due to sarcolemmal fragility which predisposis to catastrophic rhabdomyolysis and hyperkalemic cardiac arrest
Dilated CM (1/2 pts)
Wheelchair by age 13; Death 20s - 30s
GI tract HYPOmobility/Gastroparesis
Impaired swallowing (inc risk aspiration)
Scoliosis;
poor pulm function
Anticonvulsant and Nondepolarizing NMB
Chronic Anticonvulsant use: attenuates
Carbemazepine
Increased clearance (likely from liver metab)
Acute Anticonvusant use: potentiates
has depressant effect on ACh release (also explains an upregulation of ACh NM receptors with chronic use
Many things can effect the duration of NMBs. Meds can potentiate (inc) or attenuate (dec) duration.

Antibiotics, lithium and Local on the duration of NMB by nondepolarizing agents

Phase I vs Phase II Neuromuscular block
What potentiates and attenuates them
Refers to succinylcholine; can cause 2 differen types of NMB depending on dose and duration of use
Phase I: Depolarizing block
seen in standard intubating doses (1-2 mg/kg)
Succ mimics action of ACh at NMJ and casues sustained (muscle contraction) depol of the postjenctional membrane.
Single twitch height is DECREASED; there is a minimal TOF fade; and TOF ratio is typically >0.7
Antagonized by prior NONDEPOL NMB administration, even small doses. This is why you should increase dose of Succ to 1.5 mg/kg after giving a defasciculating dose of a NMBD. The nondepol NMB binds to the NMJ AcH receptos and therefor competitively inhibs succ
By contrast, ACH inhibitors augement a phase I block. Because they also inhib plasma cholinesterase which is responsible for succ breakdown.
Larger does of succ (>3 -5 mg/kg) or prolonged infusions create phase II (similar to nondepol), OR pts with cholinesterase deficiency
TOD ratio <0.3 and significant tetanic fade
Unlike a phase I block, AcH-inhibitors can antagnonize phase II block, while nondepol will potentiate it

Congenital NM disorders and the effect of Nondepolarizing NMBDs

Congenital NM Disorders and the effect of nondepol and depol NMBs
Prejunctional:
CMT: progressive muscle wasting, denervation/instability > causes proliferation of AcH receptors > hypersensitivity + prolonged paralysis with NMBDs
Succ CI 2/2 hyperkal and cardiac arrest
NMJ:
Postjunctional:
DMD: progressive muscle wasting, denervation/instability > causes proliferation of AcH receptors > hypersensitivity + prolonged paralysis with NMBDs
Succ CI 2/2 hyperkal and cardiac arrest
CMT and DMD are characterized by progressive muscle wasting and denervation > causes proliferation of ACh receptors or severe LOF muscle mass. This leads to hypersensitivity and prolonged paralysis when NMBDs given.
Depol (succ) are STRICTLY CI due to risk of hyperkalemia and cardiac arrest

Myotonia Congenita
What are they resistant to?
The condition is caused by mutations in the CLCN1 gene, which controls chloride channels in muscle cells. Without normal chloride flow, muscle membranes become hyperexcitable and take too long to rest
NMJs demonstrate NORMAL sensitivity to nondepolarizing NMDs BUT cannot abort the spasm as the hyperexcitability is downstream
Sx: muscle stiffness, grip delay, muscle enlargement, diff swallow
Resistant to nondepolarizing NMBs. Skeletal muscle mass is presevered BUT NMBDs cannot prevent or relax a myotonic contracture in these pts bc the underlying pathology is in the sarcolemma NOT the NMJ

ED95
ED95 is the effective dose that produces 95% suppression of twitch height (a 95% reduction in the T1/single-twitch response) in 50% of patients — the standard metric used to compare the potency of neuromuscular blocking agents and to guide intubating dose selection.
Renal failure and NMBD
Renal failure alteres the duration of action fo many NBMDs due to varying degrees of renal excretion
Of the commonly use NMBDs, only succinycholine and cisatracurium have minimal renal excretion and predictable DOA with renal failure pts
IBW/TBW/LBW drugs
IBW: Non depol NMBD
LBW… fentanyl, propofol (induction dose)
TBW: Succinycholine, propofol (maintence), precedex, neostigmine, suggamadex
How much does succinylcholine increase K by
0.5 -1 mEq/L (2/2 depol muscle activity)
Exaggerated hyperkalemia seen in
Burns (>24Hs old up to 1-3 years)
CVA w/ weakness
Total body immobiltiy
GBS
Massive trauma
Decrease the incidence of myalgias with succinylcholine
Pre-treatment with NSAID
Pain is usually inconvinient and last 1-2 days
Exact MOA unknown but can have rhabdo and myoglobinuria
Post-tetanic twitches, how they work

Acceleromyography (AMG)
Quantitative NM monitoring (TOF is qualititative)
highly sensitive + superior
MORE sensitive for residual blockag compared to qualititative
Quantitative (AMG):
MMG/AMG GOLD standard
Yields numerical TOF ration 0-1
Ways to detect residual NM blockade
What TOF ration is adequate recovery?
Clinical:
sustained headlift
sustained handgrip
speak/swallow
spont vent with High TV
poor sensitivity for residual paralysis
Qualitative:
periph nerve stime (TOF).
50 hz tetany visual/tactile fade
100 hz tetany visual/tactile fade (better)
insensitive for residual paralysis
Quantitative (AMG):
MMG/AMG GOLD standard
Yields numerical TOF ration 0-1
TOF >.90-.95
MS pt getting open hysterectomy > best anest plan
General (Prop + roc but any)
Succ CI in MS pts > hyperkalemia
Spinal anesthesia (subarachnoid) relative CI > implicated in postop exacerbations in MS
Epidural and Nerve blocks generally Okay
MS pts may also have prolonged response to nondep NMBs due to loss of mass and weakness OR they may have resistance due to upregualted extrajunctional cholinergic receptors
Carefully monitor NM with peripheral nerve stim
Hypercalcemia effect on induction (NMBD) and hyperparathyroid pts. What to do?
Increase dose of nondepolarizing NMB
Hypercalemia antagonizes their effect by increasing the amount of AcH released att motor end plate (need higher doses)
**conversely, hypocalcemia potentiates it
How body temperature affects EEG activity
Lithium effect on NMBDs
Lithium prolongs actions of BOTH nondepol and depol

Anitbiotics that effect NMBD
Aminoglycosides and clindamycin….
Pseudocholinesterase def
Autosomal recessive
Affects duration of DEPOL NMBs (and mivacurium)
1/5000 white
Precurarization dose
10% of ED95 dose of ANY nondepol prior to succ
ED95 (in context of non depol NMB): drug dose that causes 95% twitch supression in 50% of pop
Why: succ fasciculations can increase IAP and risk of aspirations
Adv: reduces potency of succ and delays onset
***inc dose of intubation from 1 to 1.5

ED - effective dose
Meds affect different ppl differently
ED50 is median effective dose that will produce an effect in 50% of pop
ED95 (in context of non depol NMB): drug dose that causes 95% twitch supression in 50% of pop

More on physiology of NMJ signaling
