Fluid-Filled Monitoring Systems
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/38

Earn XP
Description and Tags
Exam 2
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
39 Terms
Hemodynamic monitoring
Describes the relationship between pressure, flow and resistance
Assess cardiac function, vascular function, perfusion, and response to therapy
Pascal’s Principle
Pressure applied to a enclosed fluid is transmitted undiminished to every portion of the fluid and the vessel walls of the containing vessel
Monitoring: patient → catheter → fluid → column → transducer
Incompressible fluid, rigid tubing, and no air
Poiseuille’s law
Flow through a cylindrical tube is
directly proportional to the pressure difference and the fourth power of the radius
inversely proportional to the fluid’s viscosity and the tube’s length
Flow is dependent on radius, length, and viscosity/resistance of fluid
Cross Sectional Areas of vessel
i. Aorta – 2.5 cm²
ii. Small Arteries – 20cm²
iii. Arterioles 40 cm²
iv. Capillaries – 2500 cm²
v. Venules – 250 cm²
vi. Small veins cm²
vii. Venae cava – 8 cm²
Capillaries have the largest cross-sectional area due to have billions in the body
Cross-sectional Area and velocity
The same volume of blood must pass through all vessels
Velocity is inversely proportional to vascular cross-sectional area
velocity/speed increases as the cross-sectional area decreases
Capillaries have the slowest velocity due to the largest cross-sectional area → more time for nutrient exchange
Flow vs velocity
Flow = how much blood is being moved
Velocity = speed/how fast the blood is traveling
Reynold’s Number
a. Compares inertial forces with viscous forces to predict flow patterns
Inertia = fluid's desire to keep moving
Viscosity = fluids resistance/friction
b. Predicts whether blood flow will be smooth and orderly (Laminar) or chaotic and swirling (Turbulent)
Velocity and diameter are highly influential
in aorta: large diameter and high velocity = high Re - may be turbulent
In capillaries: small diameter, low velocity = low Re - laminar
Reynold’s Number Equation
Re = (p*v*d)/u
p = density of the blood (mass/volume; inertia)
v = velocity of blood flow (how fast)
d = diameter of the blood vessel (resistance)
u = viscosity of blood (how thick/sticky)
Reynold’s Number predictions
i. If Re < 2000 = Laminar
ii. If Re > 4000 = Turbulent
iii. If 2000 < Re < 4000 = Transition flow
Catheter + noncompliant tubing
Carries pressure from the patient to the transducer
Catheter design
Biocompatible, smooth, nonthrombogenic, as short as practical, low-compliance walls, small outer diameter
Pressure transducers
Converts mechanical pressure to an electrical signal when pressure pushes on a pressure-sensitive diaphragm
Transducer senses movement produced by pressure transmitted through the fluid column
Capacitance transducer
Uses two plates → pressure pushes on the diaphragm causes the plates to push against each other → oscillating voltage → increase in capacitance
Inductance Transducer
Uses a coil → pressure causes diaphragm to move and change position of coil → changes inductance of system
Resistance Type Transducer
Uses a Strain gauge bonded to the back of the diaphragm
Pressure pushes on the diaphragm, causing it to bend/move → the strain gauge is stretched or compressed → resistance changes → electrical signal changes
Wheatstone bridge: changes in resistance are easily converted to a change in voltage
Makes small changes easy to detect
Diaphragm moves → strain gauge resistance changes → Wheatstone bridge detects it → voltage changes → pressure displayed
Amplifier
strengthens the electrical signal coming from the transducer
Flush system + pressure bag + stopcocks
Flush: continuously provides a small amount of fluid through the pressure tubing
Prevents clotting; keeps catheter open
Pressure bag: applies pressure on the flush solution so that it is higher than patient pressure (prevents backflow)
Stopcocks: controls flow direction; used to connect the transducer to the patient, collect samples, zero the transducer
Monitor/signal processor
Processes the electrical signal and converts it to pressure measurements
Important functions
Zero: establishes atmospheric pressure as 0 mmHg → balancing the Wheatstone bridge
Scale: changes how the waveform is displayed
Alarms: identify pressure outside selected limits
Natural Frequency
Frequency at which any structure prefers to oscillate/vibrate naturally after it as been disturbed
Longer and more compliant = lower natural frequency
Shorter and stiffer = higher natural frequency
Monitoring system should have much higher natural frequency contained in the patient’s waveform
What can disturb pressure wave forms
Catheter diameter and length
Longer tubing = diminished pressure
High compliance = absorbs changes in pressure
Connection/stockcocks = distortion
Air bubbles
Resonance
Resonance happens when an outside force is applied at or very close to a system’s natural frequency
Can amplify the waveform signal
Damping
The loss of energy from an oscillating system
some is needed

Overdamped
low systolic BP and High diastolic BP
narrow pulse pressure
Causes: air bubbles, kinks/poor connection, small-lumen catheter, blood backed into the pressure tubing
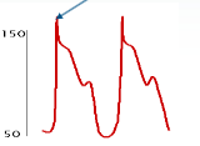
Underdamped
High Systolic BP and Low Diastolic BP
Wide pulse pressure
Causes: resonance, hyperdynamic signals, tachycardia, and tubing vibration

Optimal Transducer Waveform
Square-Wave/Fast Flush Test
Evaluates the dynamic response of the transducer monitoring system
Process
Activate the fast-flush device → release → observe waveform response
diagnose damping from transducer

Square-Wave/Fast flush test
adequate damping

Square-Wave/Fast flush test
Underdamping

Square-Wave/Fast flush test
Overdamping
Patient factors that influence damping
higher-frequency signals occur with tachycardia or sepsis
Aortic regurgitation (blood leaks backward into the LV) or hyperdynamic circulation
Zeroing transducer
calibrate the system to atmospheric pressure to program it as 0 mmHg
Process: close transducer off to the system, open the Wheatstone bridge to air, press zero on the monitor system
Leveling Transducer
location of transducer when zeroing + monitoring pressure to prevent hydrostatic error
If too low, the transducer diaphragm is pushed on by the weight of the fluid
Phlebostatic axis: in line with the patient’s heart/RA
2 mmHg for every 1 unit of vertical difference from the phlebostatic axis
Lag time
longer tubing the longer the lag time, because of inertia, fluid-filled column within system should be transmitted simultaneously and with equal force
Oscillations
numbers of cycles per second
Fidelity
Ability to reproduce the patient’s actual pressure waveform
How faithfully the system reproduces the patient’s pressure waveform
High fidelity = preserves timing, shape, and amplitude
Dynamic response
How accurately the system follows rapidly changing pressure
Response must be quick without exaggerating or blunting the waveform
Ringing
repeated oscillations caused by inadequate damping
Catheter whip
motion artifact from catheter movement
Hydrodynamic pressure
Pressure produced by fluid in motion
Hydrostatic Pressure
Pressure exerted by a stationary fluid column