functional anatomy & lung mechanics
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/79

Earn XP
Description and Tags
These flashcards cover the fundamental anatomy, respiratory muscles, lung volumes, capacities, and ventilation equations as discussed in the Respiratory Physiology lecture.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
80 Terms
respiratory system
system responsible for the exchange of gases in the body that consist of the
gas exchanging organ - alveoli in the lungs & pulmonary capillaries
ventilatory pump - chest wall, diaphragm, areas in the brain that control respiration
chest wall - rib cage + muscles of respiration
respiration
pulmonary ventilation - inflow & outflow of air between the atmosphere & lung alveoli
diffusion of O2 & CO2 between alveoli & blood in pulmonary capillaries
transport of gases - accomplished by circulation
regulation of ventilation
respiratory muscles
muscles involved in the process of breathing which expand and contract the thoracic cavity to facilitate airflow in and out of the lungs
primary (inspiration)
diaphragm
external intercostal
accessory muscles (inspiration)
sternocleidomastoid, scalenes (anterior, middle, posterior), pectoralis major & minor, serratus anterior, serratus posterior superior
muscles of expiration (active/forced)
abdominal muscles (rectus abdominis, external oblique, internal oblique, & transversus abdominis)
internal intercostals (excluding the interchondral portion), innermost intercostals, subcostals
serratus posterior inferior, quadratus lumborum
normal inspiratory muscles
muscles primarily responsible for increasing thoracic volume during inhalation
diaphragm - flatten to push abdominal contents downwards
external intercostals - lift ribs upwards & outward
accessory inspiratory muscles
muscles that assist the diaphragm & external intercostals during deep or labored breathing (ex. exercise or respiratory distress)
sternocleidomastoid
scalenes (anterior, middle, posterior)
quiet expiration
a passive process driven by the relaxation of inspiratory muscles and the elastic recoil of the lungs and chest wall
active expiratory muscles
muscles recruited during forced expiration (exercise, coughing, respiratory distress) to increase intrathoracic pressure and expel air
internal intercostals → pull ribs downward + inward
abdominal muscles (rectus, obliques, transversus) → compress abdominal cavity → push diaphragm upward
pump handle movement
movement where ribs move upwards and forwards increasing the anteroposterior diameter of the rib cage during inhalation
primarily involves the upper ribs (2–6)
bucket handle movement
movement where ribs move upwards and outwards (laterally) increasing the transverse diameter of the rib cage
primarily involves the lower ribs (7–10)
lungs - gross anatomy
structural organization of the lungs, including lobes, airway branching, and relationship to the diaphragm
right lung: 3 lobes (superior, middle, inferior)
left lung: 2 lobes (superior, inferior) → cardiac notch for the heart
trachea divides into right and left main bronchi → further branching into lobar and segmental bronchi
lungs rest on the diaphragm → primary muscle of inspiration
pleura
a thin, double-walled serosa surrounding the lungs
composed of an outer layer lining the thoracic wall (parietal) & an inner layer covering the lung surface (visceral)
the space between the layers = pleural cavity
produces a small amount of lubricating fluid (≈ 10–15 mL) to reduce friction during breathing
pleural effusion
accumulation of excess fluid within the pleural cavity
restricts lung expansion and reduces ventilation
appears as opacity on imaging

phrenic nerve
motor and sensory nerve arising from C3–C5 that innervates the diaphragm and conveys sensation from the central diaphragmatic pleura
provides motor innervation → diaphragm
carries sensory fibers from the central diaphragmatic pleura and pericardium
irritation of these structures (e.g., splenic injury, subdiaphragmatic inflammation) may be perceived as referred pain at the shoulder tip due to shared C3–C5 dermatomes
pneumothorax
collapse of the lung caused by air entering the pleural cavity
air leaks from the lung or chest wall into the space between lung and thoracic wall
accumulated air prevents lung expansion → partial or complete collapse
commonly due to chest trauma or underlying lung disease (COPD, asthma, cystic fibrosis, tuberculosis)

lungs - arterial blood supply
pulmonary deliver deoxygenated blood from the right ventricle → lungs for gas exchange
bronchial provide oxygenated blood to the conducting airways and supporting lung structures
lungs - venous blood supply
pulmonary return oxygenated blood → left atrium
bronchial drain deoxygenated blood from part of the airway circulation (with some drainage entering pulmonary veins)
lungs - parasympathetic innervation
cholinergic input that increases airway smooth muscle tone and reduces airflow
stimulation of M3 muscarinic receptors →bronchoconstriction
increases airway resistance and limits airflow
mediated by vagal efferents to bronchial smooth muscle
lungs - sympathetic innervation
adrenergic input that relaxes airway smooth muscle and increases airflow
activation of bronchial smooth muscleβ2 receptors → bronchodilation
enhances airflow during stress, exercise, or increased metabolic demand
β2 agonists (epinephrine, isoproterenol, albuterol) mimic this effect and are used to treat bronchial asthma
respiratory system organization
upper airways → nose, mouth, pharynx, larynx
conducting zone → extends from the top of the trachea to the beginning of respiratory bronchioles
respiratory zone → extends from the respiratory bronchioles down
upper airways
structures that condition incoming air before it reaches the lower respiratory tract
includes the nose, mouth, pharynx, and larynx
responsible for filtering, warming, and humidifying inspired air
also provides pathways for speech and swallowing
conducting zone
portion of the respiratory tract that moves air but does not participate in gas exchange
extends from the top of the trachea → beginning of the respiratory bronchioles
includes trachea, bronchi, and bronchioles
functions in air transport, humidification, filtration, and regulation of airflow
respiratory zone
region where gas exchange occurs within the distal airways
extends from the respiratory bronchioles → alveolar sacs
includes respiratory bronchioles, alveolar ducts, and alveoli
site of O2–CO2 exchange between air and blood
Weibel’s 23-generation Model
an anatomical framework describing airway branching from trachea to alveolar sacs
23 generations of branching airways
generation 0: trachea
generations 1–16: conducting zone (no gas exchange)
generations 17–23: respiratory zone (gas exchange)
bronchi
cartilaginous airways that conduct air into progressively smaller branches
contain cartilage plates that maintain airway patency
lined with ciliated epithelium and mucus‑producing cells
part of the conducting zone (no gas exchange)
branch repeatedly before transitioning into bronchioles
bronchioles
small, non‑cartilaginous airways that regulate airflow resistance
no cartilage; walls supported by smooth muscle
lined with ciliated epithelium proximally
diameter <1 mm
include terminal (conducting zone) & respiratory (start of respiratory zone)
ciliated mucosal epithelium
airway lining specialized for particle clearance and mucociliary transport
extends from the trachea → proximal respiratory bronchioles
cilia beat upward to remove debris and pathogens
works with mucus to protect lower airways
gradually disappears in distal respiratory bronchioles and alveoli
generation 0
the first division of the airway tree responsible for conducting inspired air
corresponds to the trachea
supported by cartilage and lined with ciliated epithelium
marks the start of the conducting zone
generations 1–16 (conducting zone)
airway generations that conduct air but do not participate in gas exchange
includes bronchi and bronchioles
cartilage present in bronchi; absent in bronchioles
diameter progressively decreases
ciliated epithelium present throughout
functions in air transport, humidification, filtration
generations 17–23 (respiratory zone)
distal airway generations where gas exchange occurs
includes respiratory bronchioles, alveolar ducts, alveolar sacs
no cartilage
thin walls for diffusion
site of O2–CO2 exchange with pulmonary capillaries
central airways
large proximal airways that provide rigid, high‑velocity airflow
include the trachea and larger bronchi
supported by cartilage → semi‑rigid
airflow = fast & turbulent
contribute the highest resistance due to large diameter but intense turbulence
peripheral airways
small, compliant distal airways that regulate airflow distribution
include the bronchioles
no cartilage; walls contain smooth muscle
arranged in parallel → reducing total resistance
airflow = slower and more laminar
airway resistance – peak location
region of the respiratory tract where total airflow resistance is greatest
medium‑sized bronchi generate the highest resistance
branching at this level creates turbulent airflow → increasing resistance
resistance decreases in smaller bronchioles because many parallel pathways lower total resistance
trachea = high turbulence but less total resistance than medium bronchi
type I pneumocytes
large, thin epithelial cells forming the primary gas‑exchange surface of the alveoli
cover ~95% of alveolar surface area
extremely flat → minimize diffusion distance
form part of the air–blood barrier with capillary endothelium
essential for efficient oxygen and carbon dioxide exchange
type II pneumocytes
cuboidal alveolar cells responsible for surfactant production and epithelial repair
synthesize and secrete surfactant → reduces alveolar surface tension
act as progenitor cells → differentiate into type I pneumocytes after injury
proliferate during damage to restore alveolar lining
occupy smaller surface area but are more numerous than type I cells
respiratory membrane
the thin diffusion barrier where gas exchange occurs between alveolar air and pulmonary capillary blood
composed of alveolar epithelium, fused basement membranes, and capillary endothelium
extremely thin (~0.6 μm) → minimize diffusion distance
large total surface area (~70 m2) → maximize gas exchange
site where O2 enters blood and CO2 leaves blood by simple diffusion driven by partial pressure gradients
alveolar surface area
structural arrangement that maximizes diffusion capacity in the lungs
created by millions of small alveoli tightly packed within the thoracic cavity
pulmonary capillaries coil around alveoli to expand total surface area
large surface area (~70 m2) enables efficient gas exchange
respiratory tract particle filtration
size‑dependent mechanisms that trap inhaled particles & protect the lower respiratory tract from harmful debris
> 10 µm: trapped in upper airways (e.g., nasal hair)
2–10 µm: reach trachea/bronchi → reflex bronchoconstriction + coughing & mucociliary escalator
< 2 µm: reach alveoli → cleared by PAMs
mucociliary escalator
a defense mechanism involving coordinated ciliary system that clears trapped particles from conducting airways
cilia beat upward toward the pharynx
removes particles 2–10 µm trapped in trachea / bronchi
works with mucus to protect lower airways
impaired in smoking, chronic bronchitis, and cystic fibrosis
pulmonary alveolar macrophages (PAMs)
immune cells that clear small inhaled particles and pathogens in the alveoli
remove particles < 2 µm
phagocytose microbes and debris
activated in infection, inflammation, and dust exposure
secretory IgA (respiratory tract)
immunoglobulin that protects mucosal surfaces from respiratory infections
produced by airway mucosa
neutralizes pathogens before they invade tissue
key component of mucosal immunity
angiotensin converting enzyme (ACE)
enzyme in produced by pulmonary capillary endothelial cells that activates angiotensin II
converts angiotensin I → angiotensin II
helps regulate blood pressure and vascular tone
prostaglandins (PGE2) – pulmonary epithelium
locally acting lipid mediators that modulate airway physiology
protect epithelial surfaces
regulate inflammation
influence airway tone
histamine (respiratory tract)
inflammatory mediator involved in allergic and immune responses
released by mast cells
contributes to airway inflammation
plays a role in allergic reactions and bronchial hyperreactivity
spirometer
a device that measures the volume of air inspired and expired to track changes in lung volume
floating drum rises and falls with inspiration and expiration
measures TV, IRV, ERV, and capacities derived from them
cannot measure RV, FRC, or TLC because they contain residual volume
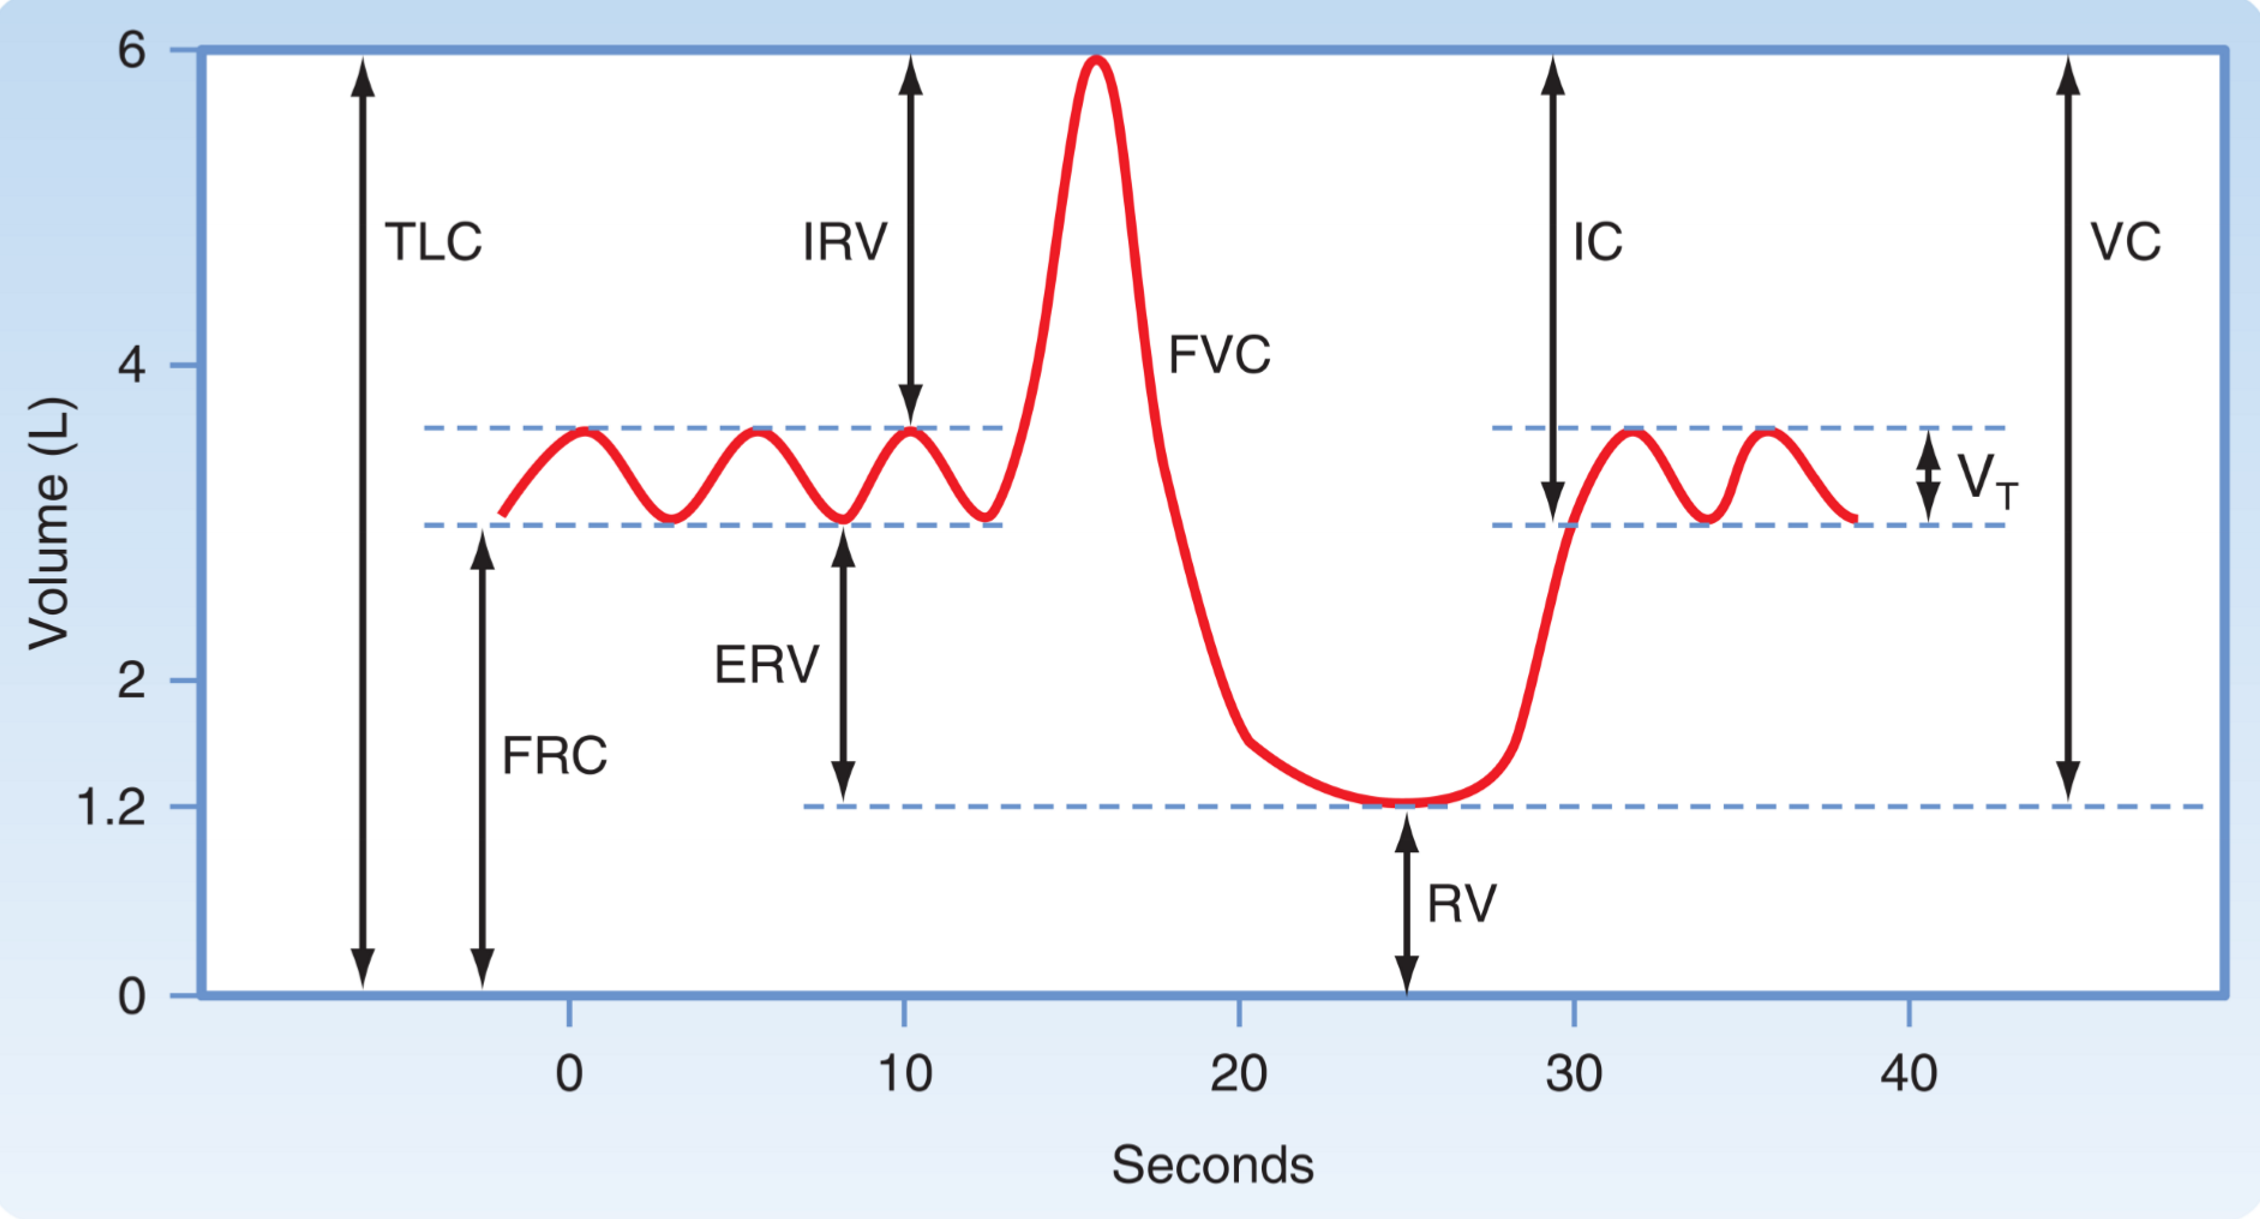
tidal volume (VT)
the volume of air that moves into the lung with each quiet inspiration
typically ~ 500 ml (~ 6–8 mL/kg)

inspiratory reserve volume (IRV)
the volume of air that can still be breathed in after a normal inspiration
forced inhalation → after VT
~ 3,100 mL for ♂ & 1,900–2,500 mL for ♀

expiratory reserve volume (ERV)
the volume of air that can still be breathed out after a normal inspiration
forced exhalation → after VT
~ 1,100–1,200 mL for ♂ & 700–800 mL for ♀

residual volume (RV)
the volume of air remaining in the lung after maximal expiration
cannot be expelled & measured by direct spirometry
prevents alveolar and airway collapse (atelectasis)
reduces the pressure needed for reinflation
minimizes energy expenditure during breathing

inspiratory capacity (IC)
the air that can be breathed in after a normal exhalation
calculated as IRV + VT

functional residual capacity (FRC)
the volume of gas in the lungs after a normal expiration; the equilibrium (resting) point where outward chest wall recoil balances inward lung recoil
calculated as RV + ERV
acts as a buffer for gas exchange between breaths
measured without muscle contraction → usually unaffected by skeletal muscle weakness
lowest pulmonary vascular resistance
increases with height & age → loss of elastic tissue

vital capacity (VC)
the maximum volume of gas that can be expired after a maximal inspiration
calculated as IC + ERV
IRV + VT + ERV

forced vital capacity (FVC)
the total amount of air that can be forcibly exhaled after a maximal inhalation

total lung capacity (TLC)
the total volume of gas present in the lungs after a maximal inspiration
calculated as VC + RV
IRV + VT + ERV + RV

helium dilution technique
an indirect measurement method for lung volumes based on the law of conservation of mass
He = poorly soluble & stays in airways
C1 × V1 = C2 × (V1 + V2)
before equilibration: known C1 and V1
after equilibration: C2 reflects mixing with lung volume V2
valve opened at end of quiet expiration → measures FRC
valve opened after maximal expiration → measures RV
dead space (DS)
regions of the respiratory system where ventilation does not participate in gas exchange
anatomic dead space: conducting airways
alveolar dead space: unperfused alveoli
physiologic dead space: total dead space
measured using capnography (anatomic) and Bohr equation (physiologic)
anatomic dead space
the volume of the conducting airways (ending at terminal bronchioles) where no gas exchange occurs
extends from nose/mouth → terminal bronchioles
proportional to body weight in pounds (≈ weight in mL)
contains air that is ventilated but not perfused
contributes to wasted ventilation
physiological dead space
the total dead space in the lungs
sum of anatomic + alveolar dead space
equals anatomic dead space in healthy individuals
increases when alveoli lose perfusion
alveolar dead space
alveoli that are ventilated but not perfused
contain air but lack capillary blood flow
increases in conditions like pulmonary embolism
normally minimal / absent in healthy lungs
volumetric capnography
method using exhaled CO2 to estimate anatomic dead space
phase I: no CO2 → pure anatomic dead space air
phase II: rising CO2 → mix of dead space + alveolar air
anatomic dead space = volume of exhaled gas at midpoint of phase II transition
phase III: plateau → alveolar air

Bohr’s equation
formula calculating physiologic dead space from arterial CO2 & mixed expired CO2
VD=VT×PACO2PACO2−PECO2
VT = tidal volume (mL)
PACO2 = PA of arterial blood CO2 (mmHg)
PECO2 = PA of mixed expired air CO2 (mmHg)
larger difference = more wasted ventilation
detects ventilation–perfusion mismatch
VT×PACO2PACO2−PECO2
Bohr’s equation - physiologic dead space (VD)
ventilation rate
frequency of breathing cycles per minute
number of breaths taken per minute
normal resting value ≈ 12–20 breaths/min
used to calculate minute ventilation and alveolar ventilation
total (minute) ventilation
total volume of air moving in or out of the respiratory system per minute
tidal volume (VT) × respiratory rate (RR)
VT = mL & RR = breaths/min
example: 500 mL × 12 breaths/min = 6 L/min
includes dead space + alveolar ventilation
tidal volume (VT) × respiratory rate (RR)
total (minute) ventilation
alveolar ventilation (VA)
volume of fresh air delivered to the respiratory zone (alveoli) per minute
(VT − VD) × (RR)
VT = tidal volume (mL)
VD = dead space volume (mL)
RR = respiratory rate (breaths/min)
example: (500 − 150) × 12 = 4.2 L/min
excludes anatomic dead space
determines CO2 elimination
(VT − VD) × (RR)
alveolar ventilation
alveolar ventilation (VA) - PCO2
relationship between alveolar ventilation & partial pressure of CO2 in alveolar air
PACO2VCO2×K⇒PACO2=VAVCO2×K
VCO2 = rate of CO2 production (mL/min)
PACO2 = PA of arterial blood CO2 (mmHg)
K = constant
describes inverse relationship: ↑ ventilation → ↓ PACO2
PACO2VCO2×K
alveolar ventilation - constant CO2
alveolar ventilation – constant CO2
relationship between alveolar ventilation and arterial CO2 when metabolic CO2 production is unchanged
varies inversely
↑ ventilation → ↓ PACO2
↓ ventilation → ↑ PACO2
described mathematically by: VA=PACO2VCO2×K
basis of hyperventilation (low PACO2) and hypoventilation (high PACO2)
alveolar ventilation – exercise
ventilatory adjustments required to maintain normal PACO2 during increased CO2 production
VCO2 increases (often doubles or more) → to keep PaCO₂ ≈ 40 mm Hg → ventilation increase proportionally
↑ CO2 production → ↑ VA
prevents exercise‑induced hypercapnia
same governing equation: PACO2=VAVCO2×K
PACO2=VAVCO2×K
alveolar ventilation – exercise

point A
total lung capacity (TLC) - VC + RV

point B
functional residual capacity (FRC) - RV + ERV

point C
inspiratory reserve volume (IRV)

point D
expiratory reserve volume (ERV)
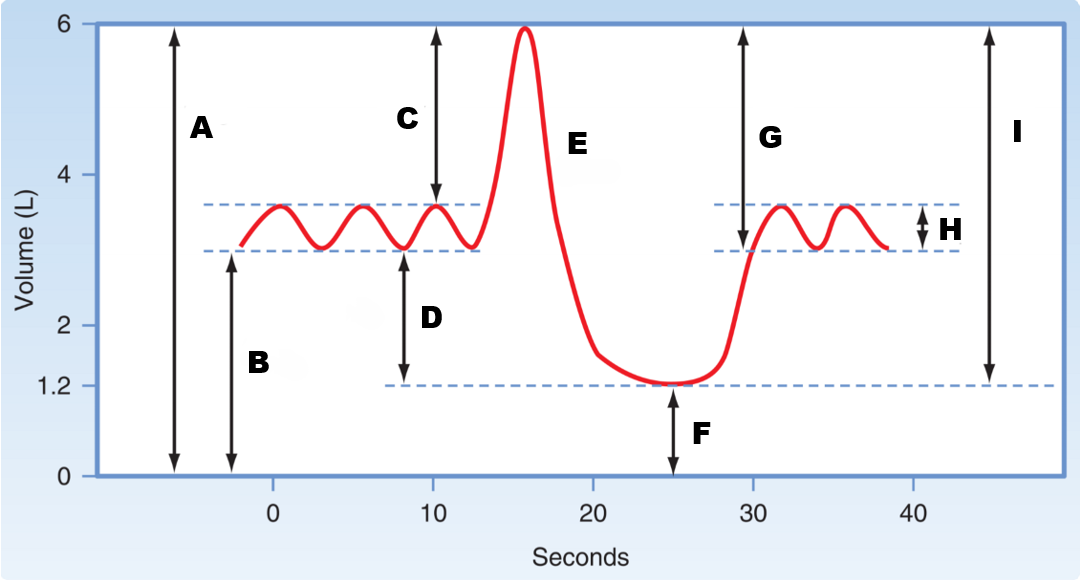
point E
forced vital capacity (FVC)

point F
residual volume (RV)

point G
inspiratory capacity (IC) - IRV + VT

point H
tidal volume (VT)

point I
vital capacity (VC) - IRV +VT +ERV