Diabetes Complications
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/39

There's no tags or description
Looks like no tags are added yet.
40 Terms
What causes DKA? Why is it an emergency?
Absolute or relative insulin deficiency→not enough insulin to suppress fatty acids from being released from fat to be lipolyzed→liver can’t handle all the fatty acids for energy so excess becomes ketones→inc Beta Hydroxybuterate > acetoacetate→ High Anion Gap Metabolic Acidosis causing coma, arrythmias, shock, cardiac arrest


What causes Hyperosmolar Hyperglycemic State (HHS)? Why is it an emergency?
Relative insulin deficiency with enough insulin to prevent ketogenesis, but not enough insulin to drive glucose into cells→glucose gets higher but no ketones(less symptoms because no metabolic acidosis)→High osmolarity of glucose causes shift of fluid out of brain cells→coma, seizures, AMS


Which diabetes type is classically associated with DKA?
Type 1 diabetes

Which diabetes type is classically associated with HHS?
Type 2 diabetes

What is the major metabolic abnormality in DKA?
Ketone production causing anion gap metabolic acidosis

What ketone predominates in DKA?
β-hydroxybutyrate

What causes ketosis in DKA?
Uncontrolled lipolysis from insulin deficiency

Why does HHS not produce significant ketones?
Enough insulin remains to suppress lipolysis and ketogenesis

Compare DKA vs HHS? (Plasma glucose, pH, ketones, osmolarity, mortality)
HHS: higher plasma glucose, no acidosis, no ketones, hyperosmolar, higher mortality
DKA: anion gap metabolic acidosis from ketosis (Beta hydrobutyrate)

What causes dehydration in DKA and HHS?
Osmotic diuresis from hyperglycemia→can lead to hypovolemic shock
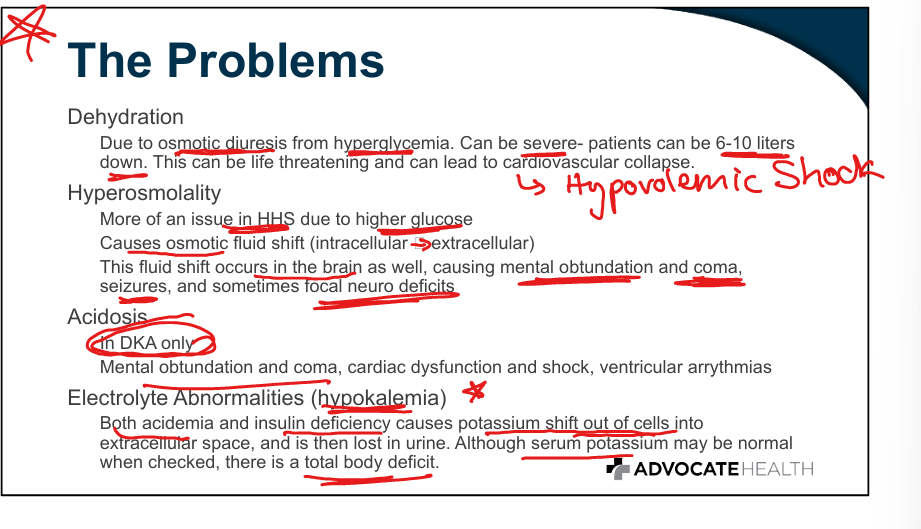
Presenting sx of DKA?
Kussmaul respirations(to compensate for metabolic acidosis), Polyuria/Polydypsia/Polyphagia, Abdominal pain, N/V(due to acidemia), Fruity breath (due to acetone from ketone acetoacetate)
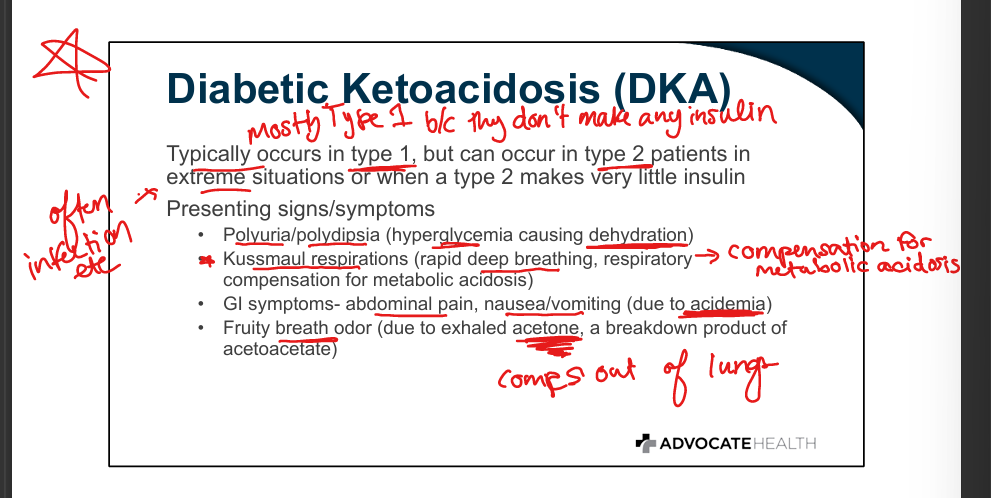
Why do Kussmaul respirations occur?
Compensation for metabolic acidosis
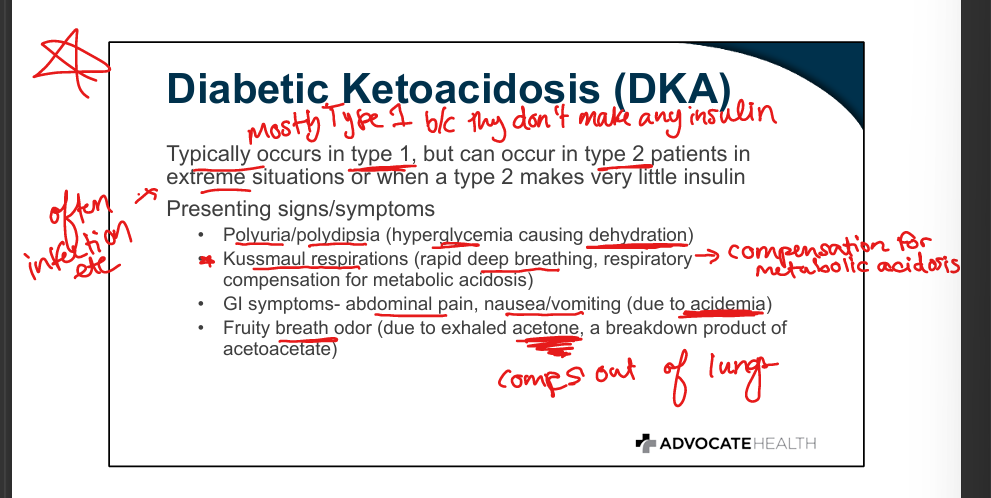
What causes fruity breath in DKA?
Exhaled acetone

Why are neurologic symptoms more severe in HHS?
Severe hyperosmolality causes fluid shift in brain

What electrolyte abnormality is a major concern in DKA/HHS treatment?
Hypokalemia—Need to correct first before adminstering insulin

Why can serum potassium appear normal despite total body potassium depletion?
Potassium shifts out of cells before urinary losses

What is the correct order of DKA and HHS treatment? ***
Fluids → Potassium → Insulin


Why must potassium be corrected before insulin if low?
Insulin drives potassium into cells causing severe hypokalemia

What medication ultimately corrects hyperglycemia and ketosis in DKA/HHS?
Insulin

Why must glucose be lowered gradually in DKA/HHS?
To prevent cerebral edema (too fast could shift fluid into brain cells)

What commonly precipitates DKA or HHS?
Infection or physiologic stress

What normally happens as glucose approaches 70 mg/dL? <70?, Continues to fall?
Insulin secretion from beta cells stops→<70 glucagon gets secreted by alpha cells→if blood sugar continues to drop epinephrine and cortisol are secreted to increase blood sugar

What are the adrenergic symptoms of hypoglycemia (happen first)?
Tremor, diaphoresis, anxiety, hunger

What are the neuroglycopenic symptoms of hypoglycemia (happen second)?
Confusion, seizures, altered mental status→cardiac arrest

What severe complications can occur from hypoglycemia?
CNS injury and cardiac arrest

What happens in Diabetes as glucose approaches 70 mg/dL? <70?
We give insulin→therefore no cease of secretion; only have epinephrine/cortisol to rely upon to increase blood sugar however»the more hypoglycemia you have the less adrenergic response you get (gets toleration) leading to hypoglycemia unawareness

What commonly causes hypoglycemia in diabetic patients?
Us giving Insulin or sulfonylureas

What is the Rule of 15 for hypoglycemia?
15 g glucose, recheck in 15 min
How is severe hypoglycemia treated outside the hospital? In hospital?
Glucagon. Give IV dextrose in hospital

How do AGEs contribute to diabetic complications?
Cause endothelial vessel wall damage leading to macro/microvascular complications (CAD, CVD, PAD)

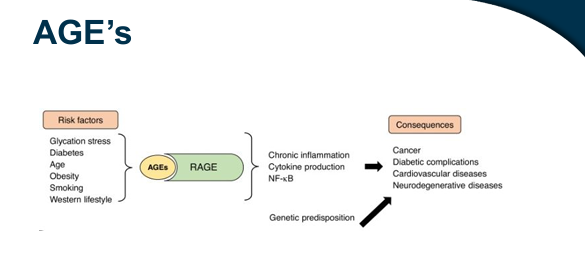
What are the major macrovascular complications of diabetes?
CAD, cerebrovascular disease, peripheral artery disease

What is the major mechanism of diabetic macro/microvascular disease?
AGE-mediated endothelial injury and atherosclerosis

What are the classic microvascular complications of diabetes?
Retinopathy, nephropathy, neuropathy

Diabetic retinopathy types and cause
Caused by endothelial vessel wall destruction→
Non Proliferative DR: Microaneurysms, macular edema, hard exudates
Proliferative DR: vessel damage→hypoxia→neovascularization but weak and fragile blood vessels


What causes proliferative diabetic retinopathy?
Retinal hypoxia leading to neovascularization


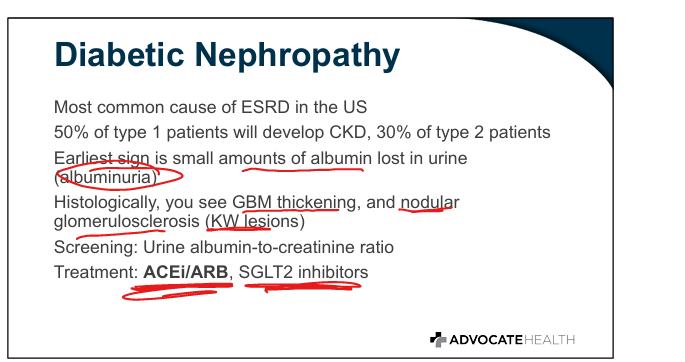
What is the earliest sign of diabetic nephropathy? Tx?
Albuminuria. Tx with ACEi/ARB, SGLT2i

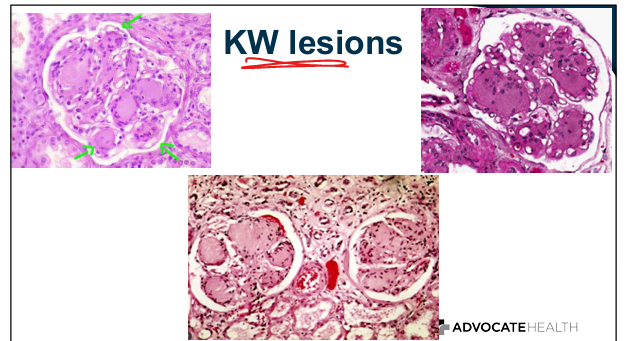
What histologic lesion is classic for diabetic nephropathy?
Kimmelstiel-Wilson nodules
What is the classic distribution of diabetic neuropathy? Tx?
Stocking-glove distribution of longest nerve fibers first (starts in feet), symmetric; Tx with Gabapentin, SNRIS

What diabetic complication commonly leads to foot ulcers and amputation?
Peripheral neuropathy


What is the mechanism of diabetic neuropathy?
Accumulation of Advanced Glycation End-products (AGEs) causing microvascular damage to nerves