Exam 1 Lectures
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/73

There's no tags or description
Looks like no tags are added yet.
74 Terms

Explain this and the 3 components that make it up
communication skills: impairment/activity, the physical impairment and what the client can ACTUALLY DO
Communication environment: physical environment (what structures ramps?) social environment (family, school, their beliefs)
Personal perspectives: preferences/coping, their opinions, feelings beliefs
What are the anti-ableist models of care?
-respect diverse ways of communicating
-not everyone needs to conform to what is historically perceived as normal or typical
-still help clients with any aspect of the biopsychosocial model that would assist them with communicative participation do so in a way that does not convey they have to conform to normal
What is important to the client? What does success mean to them?
What is strengths based care?
-recognizing that our clients have many strengths that they bring into therapy
-draw on their strengths, as opposed to taking deficit only approach
-assess, document and draw on what THEY CAN DO
-clients are experts on their own lives
What is trauma informed care?
-recognizing clients may have experienced various form of trauma in their lives
-medical and education settings (where we work) can be trauma inducing
-welcoming, respectful, and comfortable environment
-work with clients with their consent/assent
What is patient centered/person centered care?
focuses on what is meaningful, relevant and useful to each client in the context of their lives
What does the SEGUE model for shared decision making stand for
-Set the stage
-Elicit information
-Give information
-Understand the patient’s perspective
-End the encounter
What occurs when you set the stage (SEGUE MODEL)
-greet client and others in the room (family, caregivers, etc)
-explain who you are and the role of SLP
-understand the identity/role of others with the client —> who did you bring with you today?
-Make a connection (brief non-medical conversation)—> are they wearing a certain jersey?
-set a professional tone
-jointly set an agenda for the session
Why is agenda setting when setting the stage important?
-helps put clients at ease
-walk through what going to be doing today and how much time
-let them know if they will expect assessment results today or when
What occurs in the elicit information section? (SEGUE MODEL)
-follow disorder specific interview guides
-ask client to share (open ended usually)
-use open ended or neutral question DO NOT LEAD PATIENT TO SPECIFIC TOPICS
-provide communication support as needed
-end with an anything else you would like me to know about you question
What happens during the give information time of SEGUE
-when doing exams/assessments explain why doing and what
-explain diagnoses
-explain all treatment options
-explain pros and cons of different treatment options
-explain resources needed
-explain anticipated outcomes
-use layperson language but dont talk down to client
What is during the understand the client’s perspective? (SEGUE MODEL)
-listen to/watch for client’s responses regarding treatment options
-reflect back (summarize) what you have heard to acknowledge perspective
-ensure questions are answered and understanding is accurate
-keep respectful tone toward client’s wishes (respect autonomy but make sure they know the implication)
What happens during ending the encounter? (SEGUE MODEL)
-save a few minutes at the end of each session to wrap up (about 5-7 minutes)
-arrive at final plan
-review plan and the specific next steps
-clarify who is doing what and when
-ask the patient to “teach back” the plan or key information
-ask if any final questions
-follow through on you end of “next steps”
-make sure client is ready to re-enter real world (wrap up socially, used something learned in session)
What are tips for supportive/reflective listening?
-patient and calm
-use reflective listening by summarizing to reassure client you are listening
ex: I hear you saying… It sounds to me as if you are saying… Tell me more about …
-okay to offer recognition
-reassure it is okay to tell you
-offer to help/help find resources
what to NOT do when responding to clients
-provide empty reassurances you may not be able to deliver
-share your own experiences
-minimize the client’s feelings
What are suggestions for involving family members (for older teen and adults)
-ask client if it is okay to have family member help with communication
-always speak directly to client
-remember that just because family, may not know exactly what client is thinking/feeling
-even when client is a child, interview parents but get child’s opinion too
what is FRAME?
-Familiarize yourself with how the client communicates before starting interview
-Reduce rate
-Assist with message construction
-Multi-modal communication
-Engage client first
Interpreter vs translator
interpreter: spoken language and signed language (another term being used is transliterator)
translator: written language
Who should be an interpreter?
-trained professional from medical/educational interpreter services
(client does not pay for these, but facility is expected to pay)
ONLY IF FIRST IS NOT AVAILABLE
-workplace colleague who is adequately bilingual
-family (not ideal)
What is simultaneous interpreting?
-interpreter converts language while the speaker continues to speak
-used to not disrupt flow particularly in larger meeting
What is consecutive interpreting?
-we will usually us this as SLPs
-speaker pauses to allow time for the interpreter to convert the language then resumes; the message broken down segment by segment
What is prepared translation
translator is given documents in advance and translates ahead of time
What are different modes of interpretation
-in person (best option)
-telephone
-video
-CART
What are tips for working with interpreter
-ALWAYS speak directly to client
-remember ALL stages of the encounter because they will need interpretation too
-try to get same interpreter each time if possible
-meet with interpreter prior to session to orient purpose of session and what to expect
-remember something that is short in one language may not be in another
-expect EVERYTHING to be interpreted
-make sure choose words carefully and accurately convey what you mean, don’t rely on gestures
-speak at normal pace and volume
-avoid sayings/figure of speech
-speak in short segments (1-3 sentences)
-ask only one question at a time
-invite interpreter to stop and interrupt if have questions, need clarification
-maybe sit in a triangle but face the client
-have post session interview with interpreter
-don’t rely on interpreter to raise cultural issues, your responsibility to ask the client
-document presence of interpreter for legal record of services (in S of SOAP)
What are special considerations as SLPs working with interpreters
-we need to know not just what was said but HOW
-need to analyze form, content, and use and clarity
-need to understand extent of errors and difficulty
are they communicating in a typical way for their culture?
What is important when working with interpreters as an SLP
-orient interpreter that purpose is often to evaluate speech/language
-orient interpreter to the nature of session, instruct interpreter what you need to know (speech sounds made correctly, does client choose correct words?
-interpreter needs to understand not to gloss over errors or fill in blank for client (we need to know errors)
-interpreter needs to understand not to help the client, if clinician will be giving cues they need to understand what why how to convey
-debrief with interpreter to summarize their impressions of accuracy of speech/language
What are the different steps of assessment?
-chart review
-interview
-standardized (behavioral) assessment
-non-standardized (behavioral) assessment
-tech based assessment for physiologic function (if relevant)
-patient reported outcomes
intake interview tips for assessment
-explain purpose of interview
-start with open ended questions to allow client to share key concerns
(tell me about what has been happening with xyz)
-ask more specific (closed) questions to get details not shared yet?
history
symptoms
what helps, what doesnt
experiences with prior tx
hopes for tx
social determinants of health
-return to open invitation before wrapping up (what else would you like to share before we begin working together)
-use interview guide
-recognize when client has already answered a question
-respond reflectively
-be efficient (about 15 minutes)
-consider common issues
How to disrupt ableism in clinical interactions?
-help clients consider healthy therapy outcomes that are not solely based on impairment/activity performance
-resist defining goals and outcomes based solely (or at all) on able bodied norms
-focus more on client perspectives and experiences instead of listener focused perceptions
-promote use of inclusive language to replace self-stigmatizing language
-share ideas through education and advocacy
patient provider communication tips for clients with communication disabilities
-allow sufficient time
-multi-modal communication and communication aids
-do NOT talk about people in front of them
-include children/youth at age-appropriate levels
-advocate for autonomy and inclusion
When are common assessments points in care
-diagnosis
-tx planning
-progress assessment
-discharge planning
what are the key questions for diagnosis (if you are first SLP to see them)
-is there a communication disorder/disability/reason for concern?
-what is the severity and characteristics of the disorder?
How will clients enter our clinic/caseload?
-screening (is there sufficient concern to warrant a comprehensive eval)
-comprehensive dx eval (what is the type, nature and severity of any communication disorder/disability)
-updating prior eval (consider time since prior eval in context of likelihood the client has changed since? consider what was included in prior eval and do you want to add anything?)
What screenings CAN do?
provide a binary yes/no indication of if there are sufficient concerns to warrant further assessment
What screenings cannot do?
-provide comprehensive assessment
-provide dx of disorder
-verify function is WNL
-rule out concerns or problems
-rule out need for intervention
-verify that intervention is definitely needed
What is the process of differential diagnosis
-process of triangulation from multiple sources and types of data (history, medial dx/ed records, communication assessment)
-typically a single test will not provide all information needed
-compare data/symptoms/findings that will both rule in and rule out
What are the key questions for assessing for treatment planning purposes?
1 what does the client want/need to do? Where do they want to get with their communication?
2 Where are they now relative to their goals? What can they currently do with their skills and currently available supports?
3 what do they need to cross the gap? skills supports etc
what to assess when assessing for tx planning
-focus specifically on what the client’s goals are-what they need and value for communication
-find the threshold between what the client can already do successfully and where they struggle and need help
-access potential for change with therapy/supports and what type of intervention would likely be most effective (stimulability)—> what is there potential to change with intervention
What are key questions in progress assessments?
-how far has the client come since assessment?
-how far is it still to go to goal?
-is the goal still relevant? Do we need to change anything about therapy?
tx is going on want to be collecting data to compare aka probes
What are progress assessment methods
-start planning for this in baseline stage? (what is an assessment that will be able to reflect long term progress as the client improves?)
-typically use non-standardized assessment that can be repeated across time to show progress (probes)
-typically save standardized assessments —> save for baseline and discharge(if used) to major time points such as discharge planning
What are discharge assessment key questions
-has the client met their goals?
-is there anything else that needs to be addressed in therapy?
-can we demonstrate the progress made in therapy with our data (for the discharge summary report)
basals
-the item on a test at which it is assumed the respondent would get all easier items correct (so those are not administered)
-often a starting point based on age
-some tests may require establishing a basal such as 3 consecutive correct
ceilings
-the item on a test at which the responded would likely get all items that are more difficult incorrect (so not administered)
-usually a stopping rule such as 3 consecutive incorrect responses
raw scores have
limited interpretation
-CANNOT compare to normative references
-CANNOT compare to other tests or other constructs that are tested
Why can’t you report raw scores
if two different aged clients both got 10 correct but are different ages
one client may have gotten a lot further (higher ceiling) but that is not represented in the raw score
it simply looks like they got the same score
percentile ranks
-type of standardized/norm-referenced scoring
-percentage scores or people in the normative reference sample who fall at or below that raw score
-typically higher percentile is better
-ex: client scored at the 76th percentile
Client scored better than 76% of the people in the relevant (same demographics) norm referenced sample
Standard score
used to transform raw scores onto common metric (mean SD)
standard score scales
-helpful to compare across tests or subtests
-common standard scoring we use in our field mean=100, sd=15
do we use age/grade equivalents?
-not best practice
-does not provide comparison to own age/grade peers
testing error and sources of it
how accurate is the score?
sources of testing error (variability)
-clinicians introduce error when not following the directions exactly; administration and scoring variability (U CONTROL)
-clients introduce error: tired, distracted, excited (you can control to some extent)
-the assessment materials have error; not always exact representation of the construct (out of your control)
confidence intervals
95 out of 100 administrations this client’s score will fall in this interval (on any given day, the client would score in this range)
why are confidence intervals important
-is a change from one score to another over time real? likely not if CI overlap
-does a child qualify for services in school district, if child just missed cutoff helps argue for services
in documentation of standardized assessments what must be included?
-name and edition of the instrument
-raw score on each subtest and total test used
-what standard score the test uses
-standard scores and/or percentiles for each subtest, composite and total per the instrument
ex: This instrument uses xyz
-brief layperson interpretation in terms of WNL, how far outside WNL
ex: client scored within ____ SD above/below mean
sufficient sample size
pediatrics
-at least 100 children per relevant age group
adults
-age differences usually not relevant
the following demographic variables should be represented in the sample at a level within __% of the relevant population
5%
-race
-ethnicity
-biological sex
-socioeconomic status (SES)
-geographic representation
-any other relevant variable for population
What are two methods to guard against bias
-does the reference sample include people from the same cultural/linguistic background as your client
-does the test manual provide guidance on any adjustments in scoring on items or sections that are at risk of introducing bias
sensitivity
-the ability of a test to correctly identify someone with the diagnosis
-the proportion of people who have the diagnosis are identified by the test
-expressed as a proportion so higher to 100% is better—> should be above 85-90
specificity
-the ability of a test to correctly rule out someone who does not have the diagnosis
-what proportion of people who do not have the diagnosis are ruled out by the test
-expressed as a proportion so higher to 100% is better —> should be above 85/90%
false positives
identified by the instrument as having the diagnosis but do not have the diagnosis
false negatives
identified as not having the diagnosis but do have the diagnosis
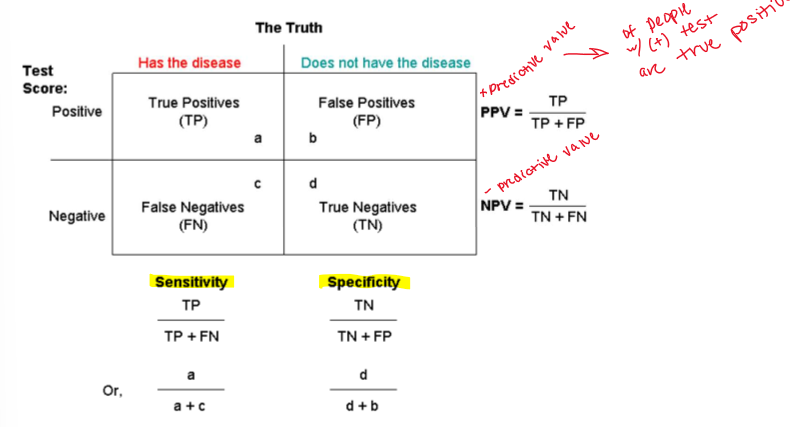
sensitivity and specificity formulas
positive predictive value PPV
-the proportion of people who test positive on the assessment who actually do have the diagnosis
-the probability that a person who tests positive actually has the disease
-a proportion so want closer to 100%
negative predictive value (NPV)
-the proportion of people who test negative on the assessment who actually do NOT have the diagnosis
-the probability that a person who tests negative is actually disease free
-a proportion so want higher to 100%
construct validity
-does the test measure what the construct it is purported to measure?
-do all the items represent the same construct?
yes? use term unidimensional
lower risk of confounding variables
all items can be combined into one score
no? multidimensional
need to separate constructs into subscales to assess different skills
content validity
-does the content of the items do a good job measuring the construct
qualitative judgements:
-do the items reflect the intended content?
-do the items cover the range of topics or content?
-do the items cover the full or intended range of skill level or difficulty level
quantitative evidence:
-item difficulty: does the range of item difficulty match the intended range of assessment
-item discrimination: the items can differentiate between people with different levels of construct ranges from 0-1 with higher values better
criterion validity
comparisons to a criterion
-concurrent validity: high correlation with another instrument that measures the same construct
-divergent validity: low correlation with another instrument that measures a different construct
-predictive validity: accuracy with which the test estimates a future outcome or measure
validity
how sensitive to change is it?
do scores meaningfully differentiate?
-children at differential developmental stages
-different severity levels or characteristics of the diagnosis?
validity: minimally detectable difference
change is real and NOT due to measurement error
validity: minimal clinically important difference
change makes a difference clinically (dx, tx plan, client experience)
reliability
-consistency of measurement over time and across examiner
-scores should not change if the underlying construct did not change
reliability: intra judge reliability
the same examiner should produce the same scores over time due to consistent administration and scoring methods
reliability: interjudge
-different examiners/scorers should get the same results when administering the same assessment to the same client at the same time
-important for kids transferring schools, clinics
test retest reliability
readminister test over an interval that is long enough that participant would have forgotten prior responses but not so long would have changed
internal consistency
how closely related the items are; covariance
split half reliability
split the test into two sets of items and examine correlation of scores across those two sets