Surgical Investigations/interventions regarding vomiting/regurgitation part 2
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/71

There's no tags or description
Looks like no tags are added yet.
72 Terms
indications for gastric surgery
-placement of gastric feeding tubes (PEG)
-gastrotomy for removal of gastric FB
-gastropexy to prevent volvulus
-correction of GDV
-pyroplasty to manage gastric outflow disease
-partial gastrectomy for resection of gastric tumour, ulceration, etc.
Percutaneous endoscopic gastrostomy (PEG) tube
-minimally invasive and highly effective method for providing proper nutrition to dogs and cats

PEG most commonly placed in animals with?
-dysphagia
-oesophageal disorders
-chronic disease that may require long term nutritional assistance
how to place PEG
-insert endoscope into stomach → use light to visualise
-create nick in skin and pass wide bore catheter
-grab loop of suture material with endoscope
-pull endoscope and forceps through mouth
-loop around tube and pull on string which pulls down into stomach
-clamp into skin

what keeps gastrotomy tube within dog
-flange/ plastic cuff

how long should PEG be left
-at least a week so forms adhesion when remove so will not cause a leak
-use endoscope to remove from stomach
describe blood supply of stomach
r and l gastropopleic a→ greature curvature
r and l gastric a→ less curvature
short gastric a from splenic s→ greater curvature

why can stomach heal quickly after surgery
-good anastomotic blood supply
-good for healing
-bacterial low load so unlikely to get infection
how to incise stomach for gastrotomy
-ventral midline celiotomy or laparotomy
-play stay sutures to mainpulate stomach and exteriorise
-pack off with swabs so not contaminating rest of abdo cavity
-place sutures wide enough apart for incision
-incise on ventral wall of gastric body→ full thickness stab incision

layers to enter in gastrotomy
-serosal layer
-muscularis layer
-submucosal layer
-mucosa layer
which layers stick together in gastrotomy
-serosal and submucosal
-muscularis and mucosa
means close in 2 layers as naturally splits in to this

which layer of stomach is the suture holding layer
submucosal layer
-into lumen layer with suture then guarantee all layers needed

gastrotomy closure suture pattern
simple interupted
inverting
simple continuous
how can we close the layers of stomach
all 4 together
2 layers together
gatsrotomy to finish before closing abdo
drape omentum → further drainage and blood supply
indications for SI surgery
-full thickness biopsy e.g. IBD
-enterotomy to remove FB
-enterectomy e.g. FB, intussusception, tumour
-enteroplication
-cholecytoenterostomy (bilary tract bypass)
indications for LI surgery
-colopexy (manage perineal hernia)
-colotomy (e.g. impaction, FB)
-colectomy (e.g. tumour, polyp)
-subtotal colectomy (e.g. megacolon in cat)
why is SI in small animals good for lack of contam
-mesentery large enough to exteriorise out of abdo wall allowing to towel off and drape them
-also no constraints when suturing and tying off
what sites is surgery needed for to get full thickeness biopsies
distal duodenum, jejunum, ileum
when doing surgery on bowels, what is needed
-clamp bowel on each side to stop contents leaking
-get assistant to use fingers to clamp
-atraumatic bowel clamps can be used but a bit too traumatic

where should incisions be made on SI
antimesenteric border

but doent do this on ileum → bc has blood supply on antimesenteric border
to get a small intestine full thickness biopsy, what should be done
-make 2 parallel incisions 2-3 cm apart and 4-5mm in length
-smooth muscle contracts allowing the sample to be exteriorised
-slice this off with blade
-take mutiple from each secton
-close this up after
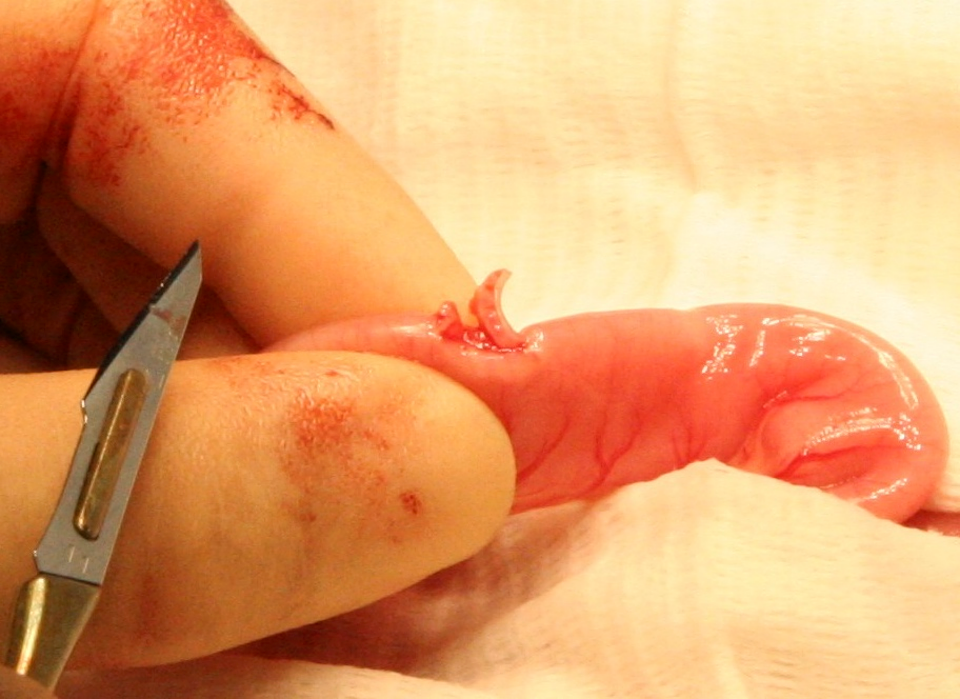

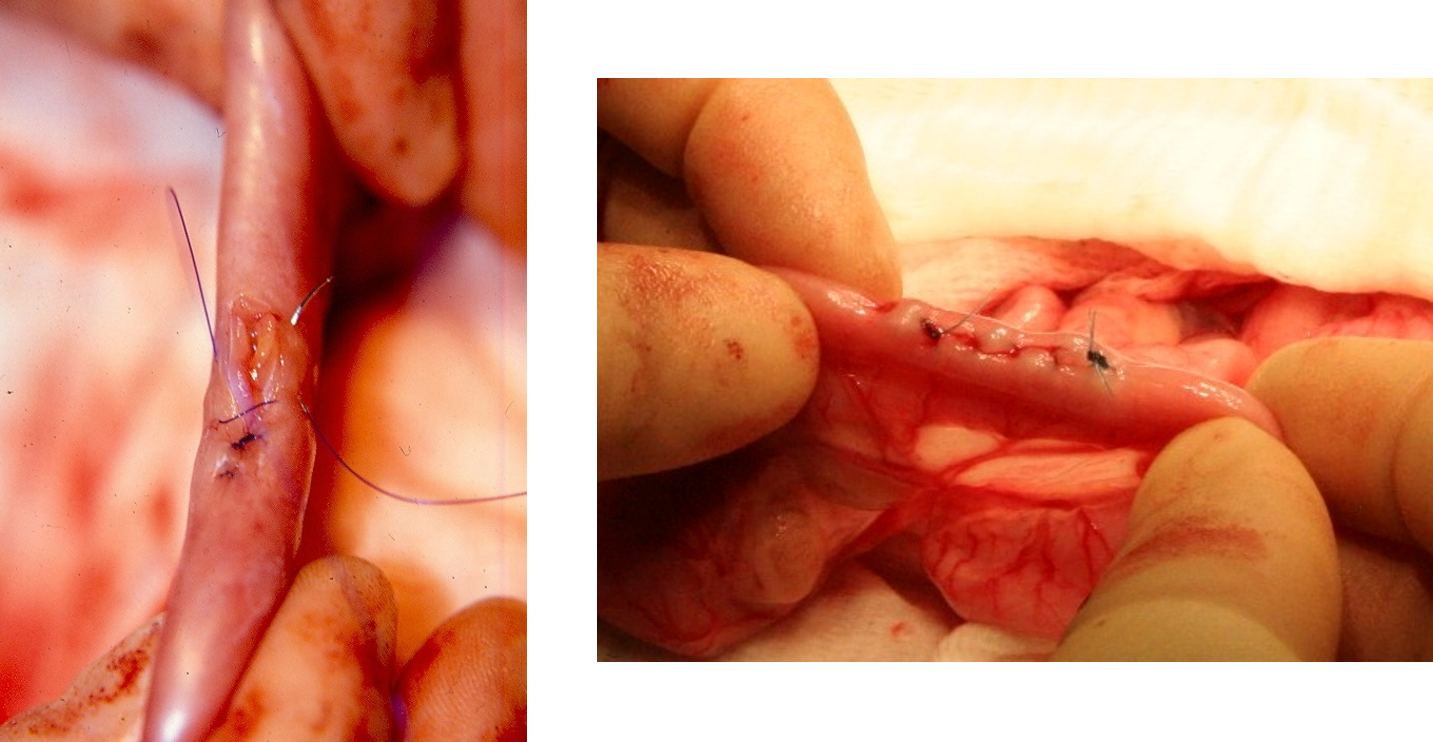
how to close up SI after full thickness biopsy taken
-simple continuous, simple interrupted, inverted
-fully into lumen (full thickness)
-drape omentum→ can suture to keep in place


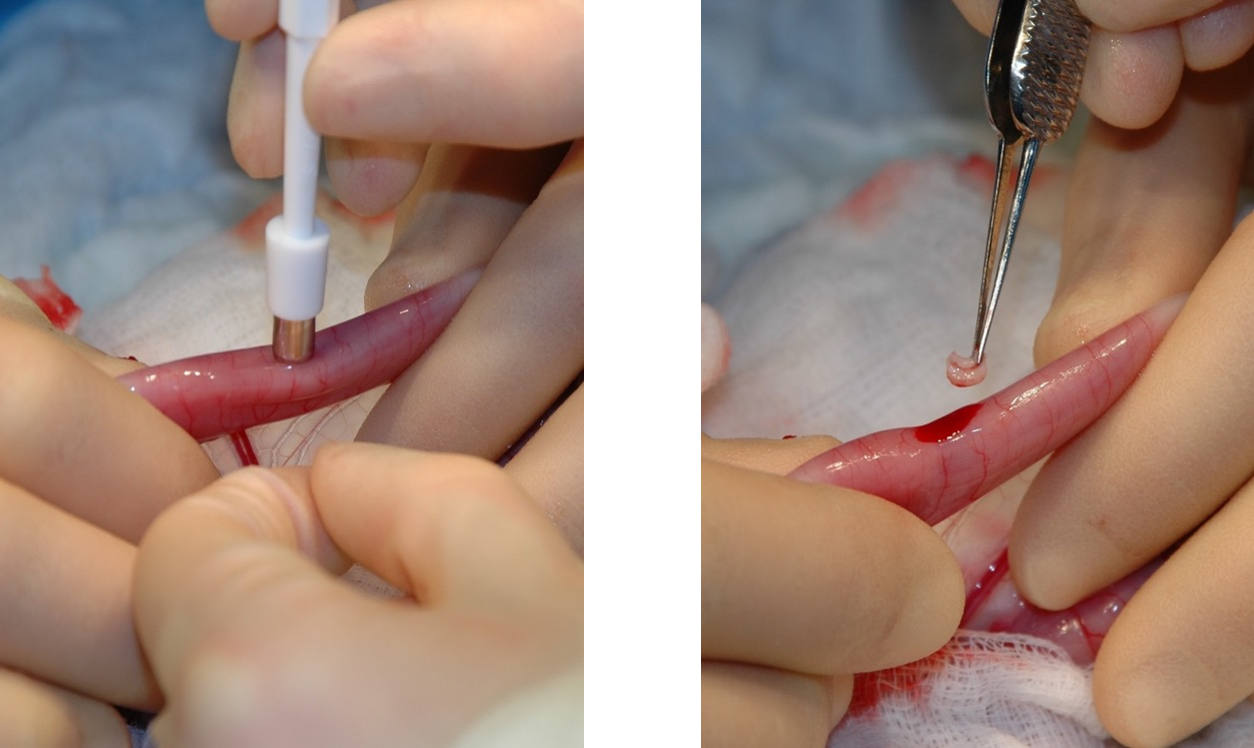
issue with biopsy punch to take small intestinal biopsy
makes a round hole which is hardr to close up
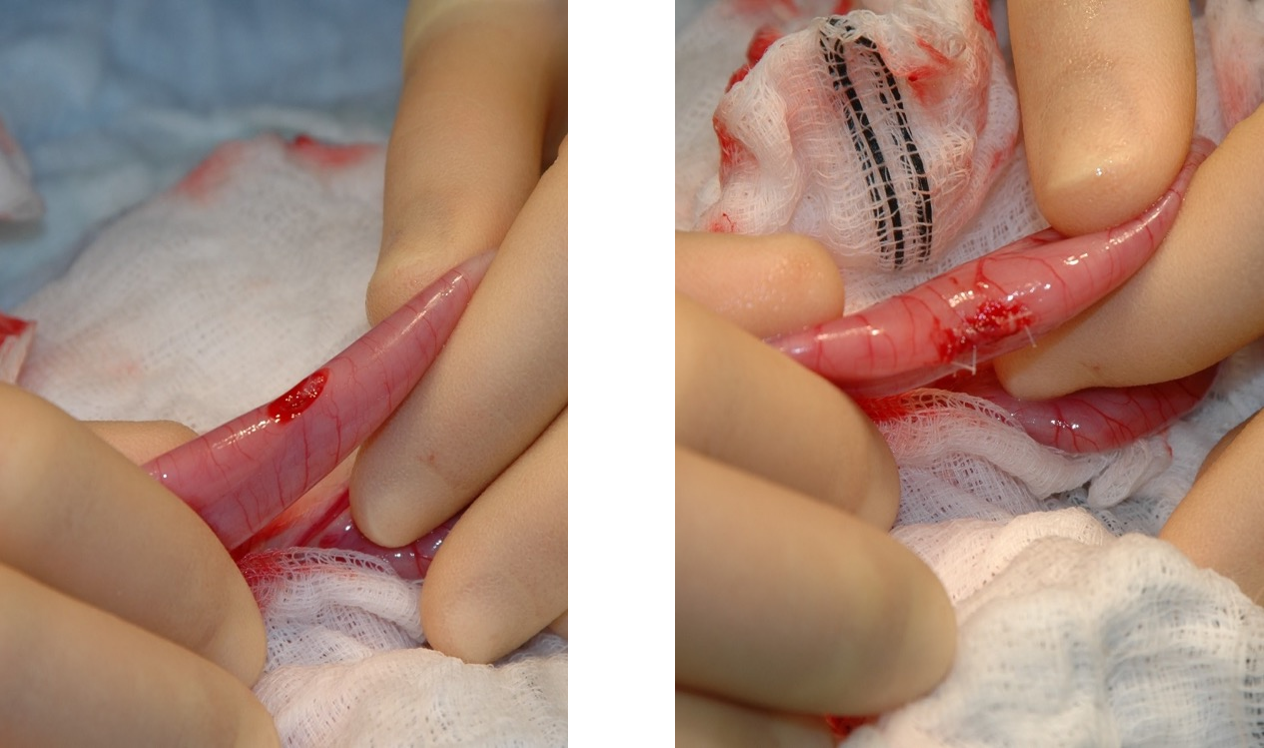

peyers patches when sampling
-avaoid takign so doesnt affect histlogcial diagnosisi
-if taking sample for IBD not good as lymphoid aggregates of lymphocytes not true representation
-this is good to sample if taking lymphoma samples
how would you describe these radiographs

-radiodense, smooth, ovoid, mid ventral abdo object with loops of distended bowel
-bowel distension in proximal/oral (fluid or gas)
-while empty bowel in aboral region

how to know if FB occluding lumen
bowel distension with fluid and gas
how to diagnose FB
if cannot find on x ray then use US
when doing enterotomy, where should incision be done
-on antimesenteric border on healthiest bit of SI poss

what to do with fluid distension when remove FB on enterotomy
-remove it to lower incidence of post op ileus
-want bowels to go back into normal persitaltic function
where to place fluid from eneterotomy
-place separate drape or kidney dish so can be removed as do not want entering abdo due to enterotoxin contents
what will happen if we dont remove the fluid during an fb removal
chance wont get peristalsis
ileus
endotoxamia
how to close SI after enterotomy
-single layer closure, full thickness
simple continuous, simple interrupted, inverted
-fully into lumen with monofilament absorbable
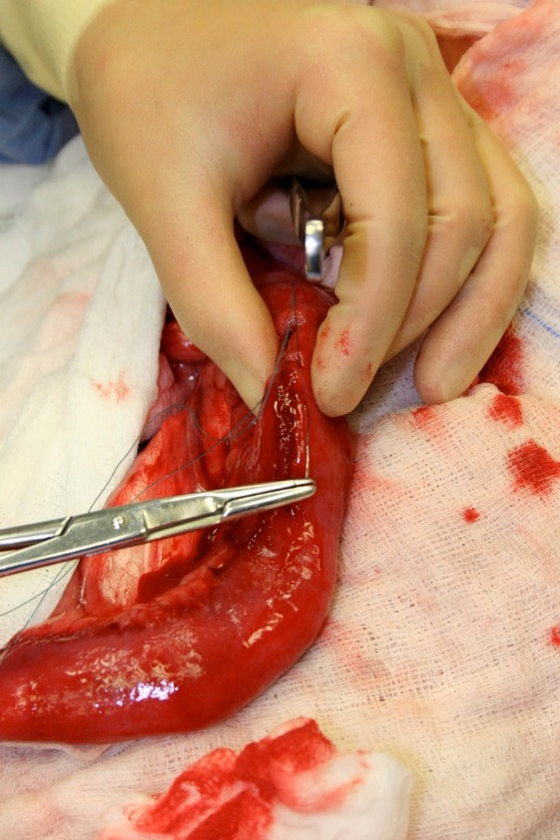
linear fb found in
cats when eat thread and string

how to find linear FB
-have proximal anchor point which is often around tongue or in stomach pylorus

what happens to stomach when linear FB
-persistaltic action makes bowel work up the thread making it concertina

what will be seen on raidography with linear FB
concertina of SI

how does linear FB go unnoticed
bowel not fully occluded
-do not vomit as food still passes through
-thread trying to penetrate through mesenteric border so may need multiple enterectmies
-if too many penetrations through bowel then will need to PTS

enterectomy
-remove portion of bowel
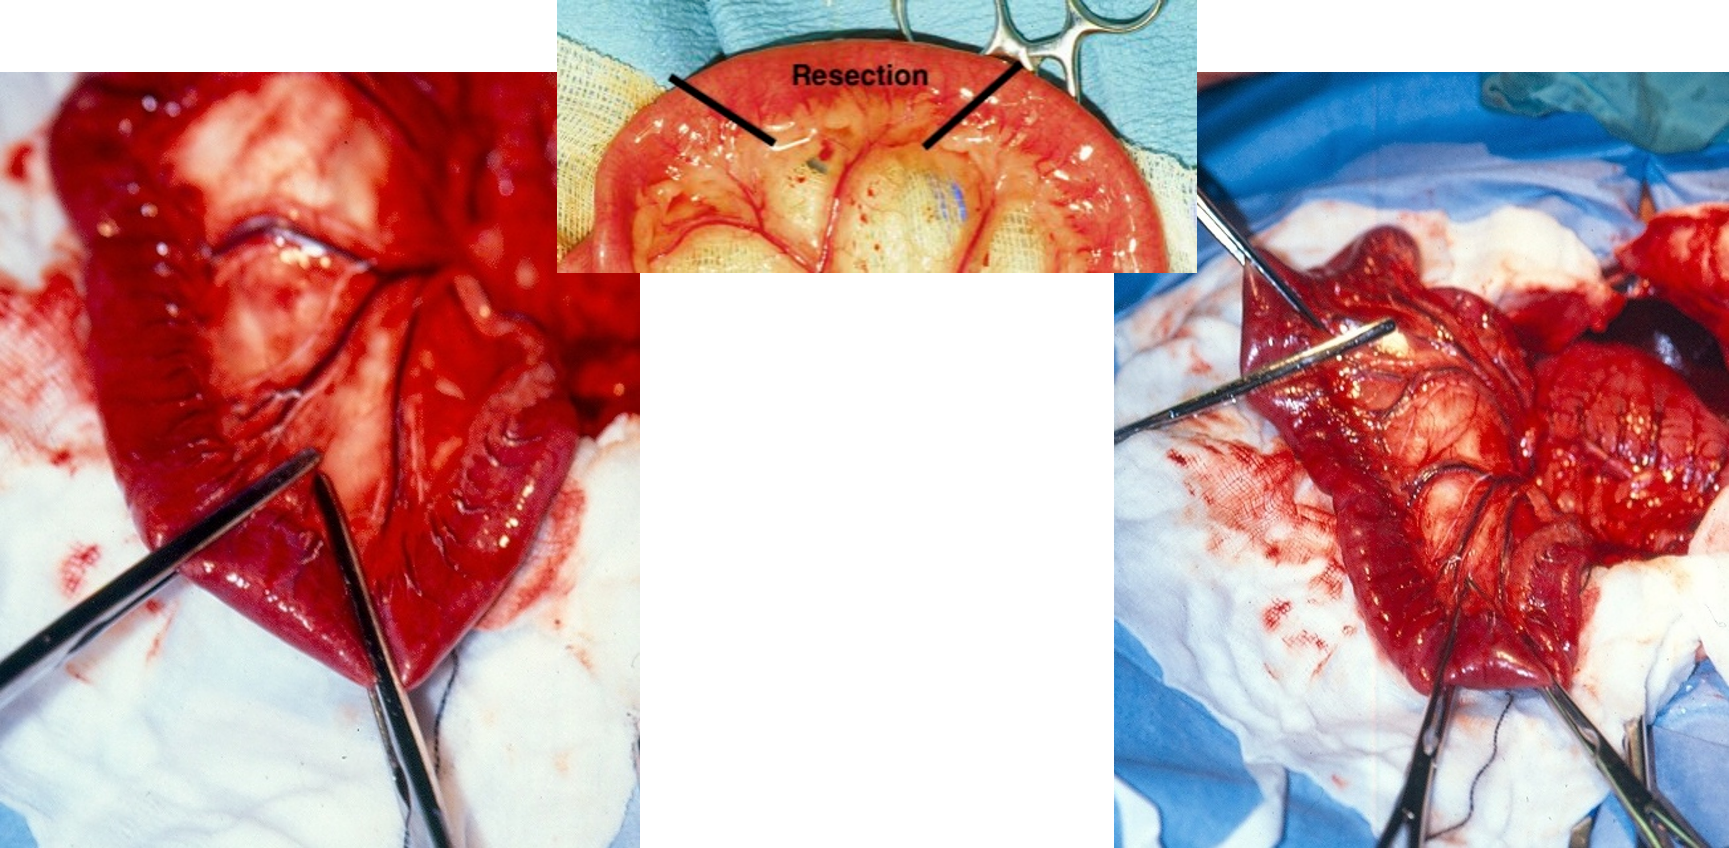
how to stop blood flow for an enterectomy
-remove blood flow to section going to remove with bowel clamps atraumatic on outside and traumatuc on inside
-tie off relevant jejunal arcade arteries and veins


what suture to tie off vessels
mono or poly, whatever preferred
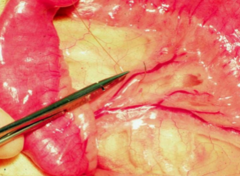
line of transection for enterectomy
place traumatic clamp at angle facing towards the bit staying in so will have good blood supply on tip of antimesenteric border
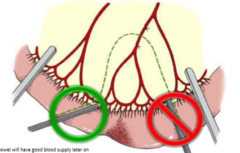
once cut through intestines, what will happen
-mucosa bulges out at you as smooth muscle makes it so trim that→ see submucosal layer
-means when bowel ends together then do not have bulging
-allows end to end anastomosis

end to end anastomosis with what suturing
-simple continuous, simple imterrupted, single layer full thickness
-can use staples
-monofilament absorbable


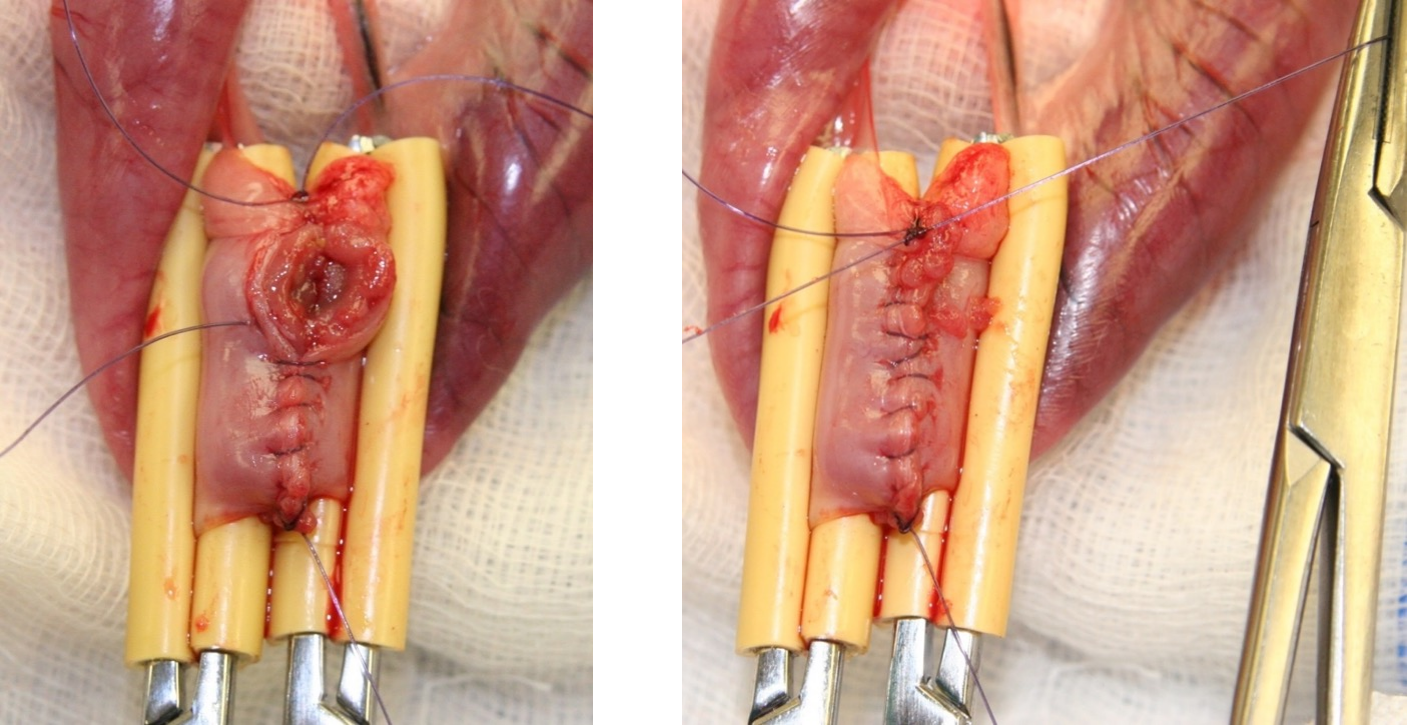

what is leak testing in git surgery
inject fluid into bowels to see if anything leaks out after stitching intestines
what is rent in mesentery
in between intestine where removed bowel leaves hole

why close rent in mesentery
must close as organs can get trapped in the middle of it
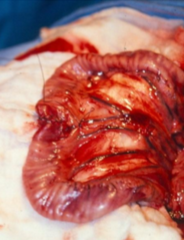
complications of enterectomy
dehiscence of anastomosis and peritonitis
when is most concerning time phase post op
3-5d post op→ dehiscence and peritonitis
in the inflam phase→ indicates issue with surgical technique
this is the time we see them back
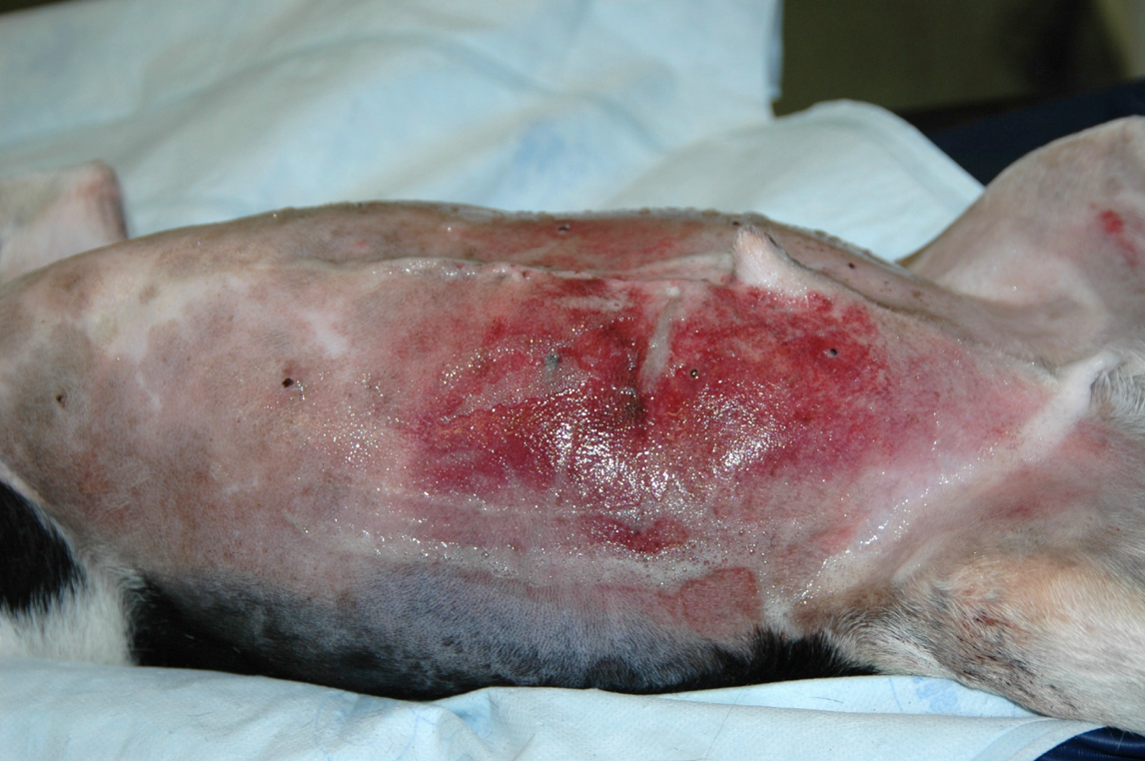
how long until enterectomy surgery heaked
-5-6 days where sutures only holding together
-3-5 days post op is most worrying as still in lag phase
what will happen if dehiscence of anastomosis
-peritonitis where become pyrexic, go off food, diarrhoea and vomiting, bruising on abdo

if suspect peritonitis, what should be done
US abdo for free fluid then tap it
-look at samples and if bad then back to surgery

what can peritonitis develop into
septicaemia

how to deal with dehiscnese post op
back into surgery
flush
another enterectomy
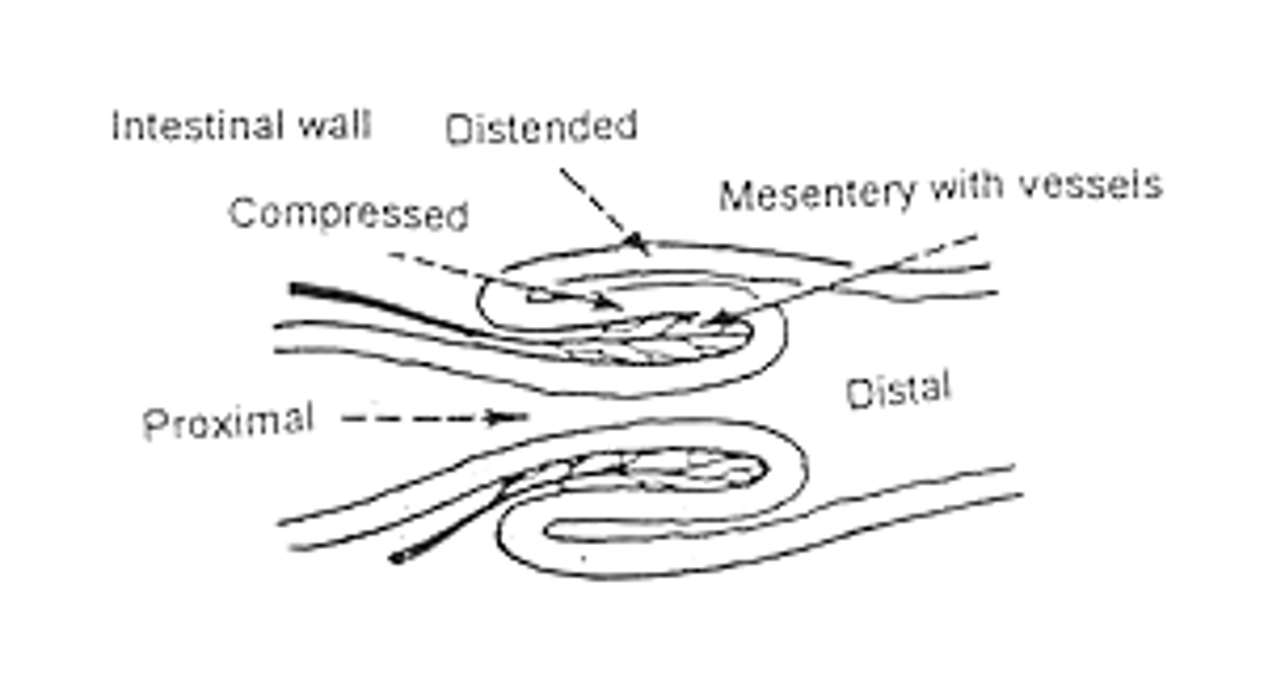
intussusception
-presents like FB
-occludes bowel
-multi layers of intestine
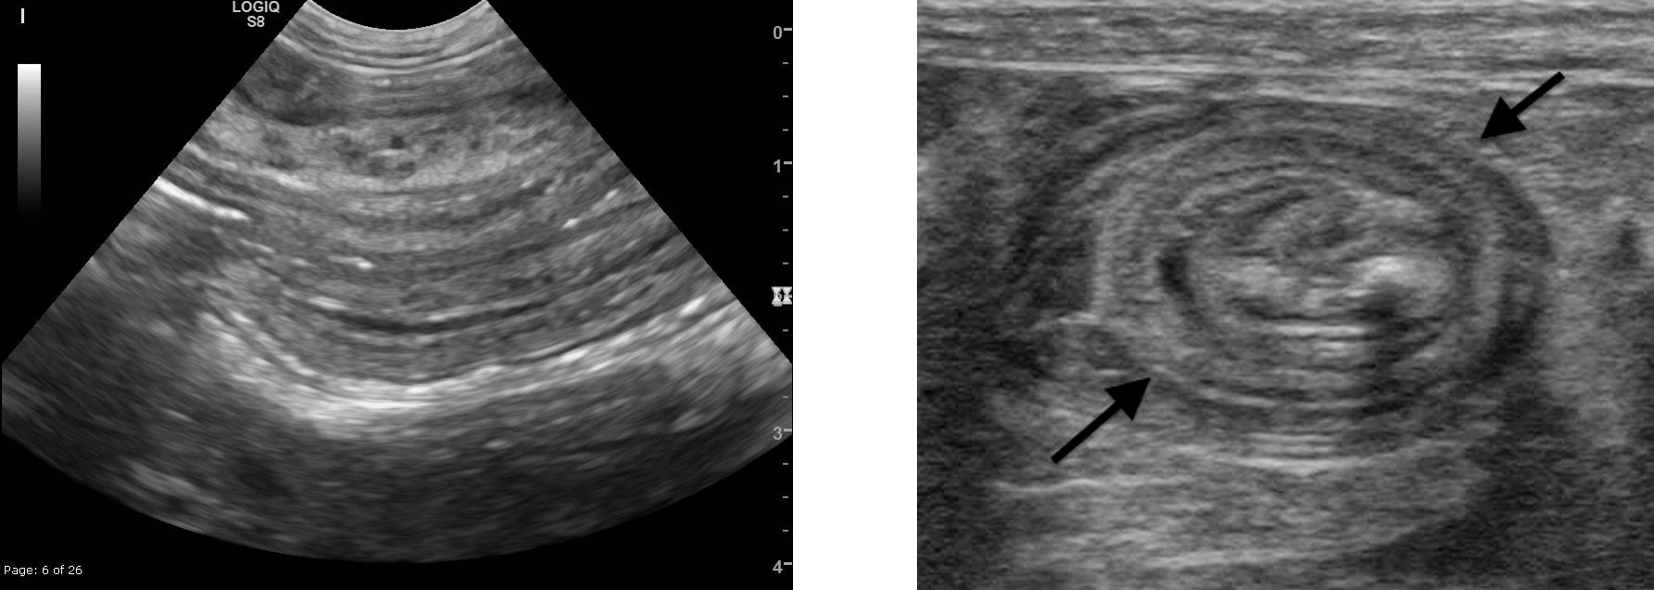
what is intussecepion
proxmial part goes into distal part
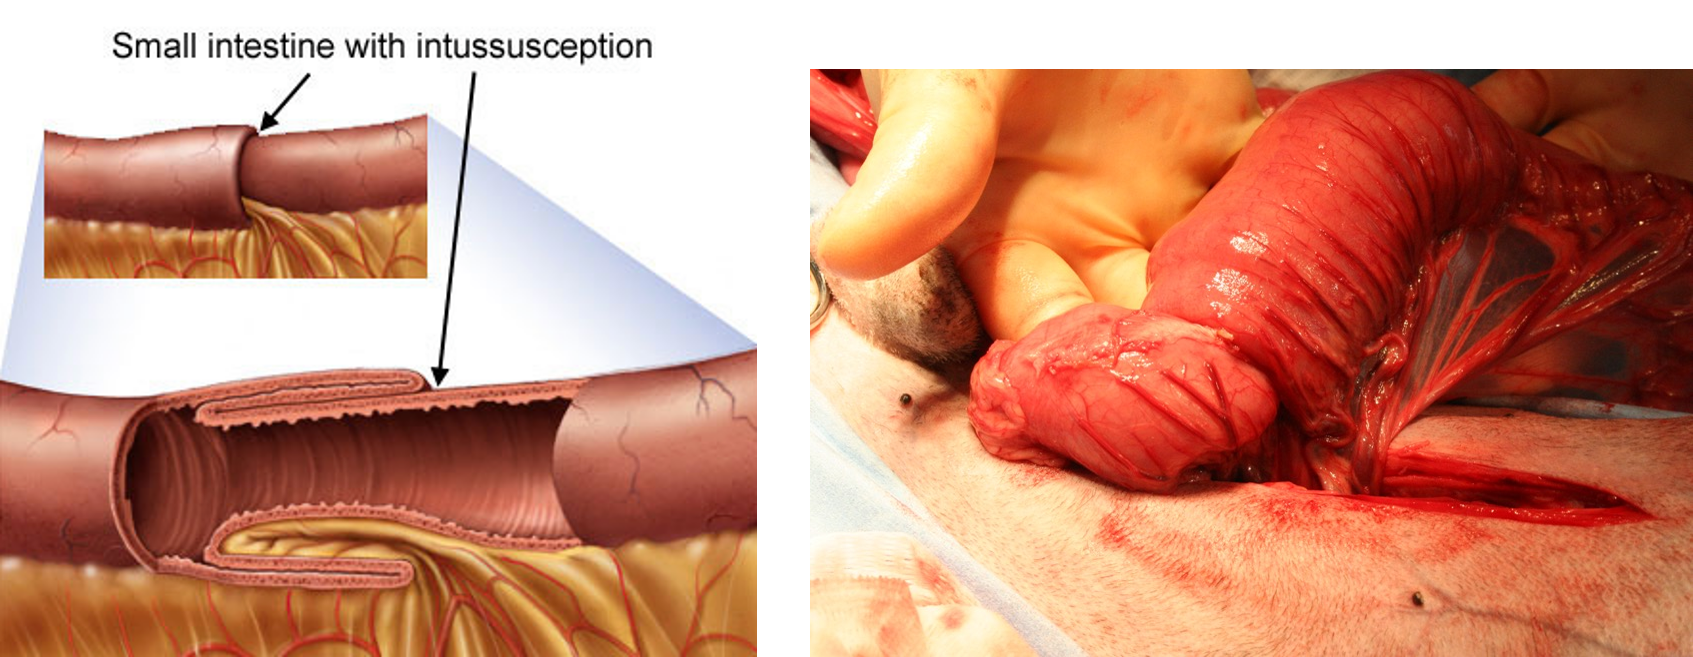
intussusception bowel plication
-attach adjacent pieces of SI together with interrupted sutures which can only pass into muscularis layer
-anchor bowel so does not intussuscept
-only over local area where happebed
issue with bowel plication
-assoc with a lot of discomfort
-can affect bowel motiliy
colonic torsions happen most in
GSDs
issue with colonic torsion presentation
by time present they already have too much dead gut
-blood clots in mesenteric vessel walls so unsalvageable
indications for pancreatic surgery
-biopsy in pancreatitis
-islet cell tumour like insulinoma
-pancreatitis
-pancreatic abscess
-pancreatic pseudocyst
-pancreatic abscess
-pancreatic tumour liek carcinoma
dog pancreas vs cat pancreas
dog has small pancreatic duct but large accessory pancreatic duct which put most of enzume into bowel
cat has pancreatic duct and NO accessory pancreatic duct
pancreas blood supply
-dual blood supply from cranial and caudal
-pancreaticoduodenal blood supply so if accidentally cut off one blood supply then affects both

where is right limb of pancreas
mesentery of duodenum
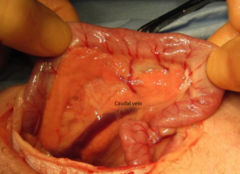
where is left limb of pancreas
in greater omentum

if want to biopsy pancreas, where should you take it from
-cranially on ventral limb on left
=no issue with accidentally hitting blood supply

complications of biopsy of pancreas
-leakage of pancreatic enzumes locally will cause protein breakdown leading to local peritonitis
how to stop leakage of enzymes while biopsying pancreas
-ligate pancreas with monofilament suture material with no breakdown to ensure closed off central duct

issue with handling pancreas too much
can cause acute pancreatitis which is severe and life threatening
insulinoma
islet cell tumour producing excess insulin which makes animal hypoglycaemic
-small tumour with dramatic effects
-make weak and collapse
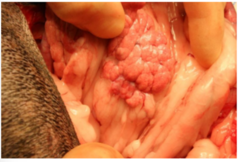
what should be done about insulinoma
remove so remaining islet cells kick back in normally
metastatic properties of insulinoma
-most malignant and often metastasise
-metastatic tissue may be producing insulin