NRN11 - Exam 4 Seminar (Render)
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/51

There's no tags or description
Looks like no tags are added yet.
52 Terms
Fill in the Blank: Veins carry ___ ___ ___ the heart.
Deoxygenated Blood Back to
Fill in the Blank: Arteries carry ___ ___ ___ the heart.
Oxygenated Away From
What is the sac that encases the heart called? What does it contain and what is the purpose?
Sac Name: Pericardium
Contains: Pericardial Fluid
Purpose: Reduce Friction
What is the effect of excess blood of fluid buildup in the pericardium?
An exess of blood or fluid restricts the hearts ability to pump effectively.
Review the flow of blood through the heart.
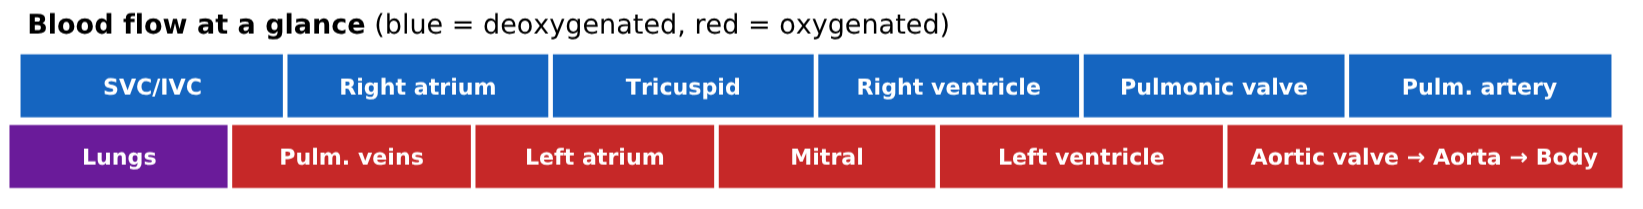
Define: Preload
What cardiac phase does it align with?
Def: The amount of blood in the heart when the ventricles are at rest.
Cardiac Phase: Diastole (End Diastolic Volume)
Metaphor: Filling a balloon with water, it is the pure volume and stretch right before the snap.
What causes preload to decrease?
Blood Bloss
Dehydration
Third Spacing
Burns
What causes preload to increase?
Exercise
Fight-or-Flight
Pregnancy
Fluid Retention
Define: Afterload
Def: The pressure required to open the semilunar valves; the resistance the heart must pump against to eject blood.
Cardiac Phase: Systole
Note: Increased Afterload = Decreased Stroke Volume (SV)
Metaphor: Pinching a straw while blowing through it. It is the resistance against flow.
What causes afterload to decrease?
Low Pressure Impairs Perfusion
What causes afterload to increase?
Chronic High BP (HTN)
High Afterload Lowers SV
Explain the difference between preload and afterload.
Preload is the load before the heart contracts (stretches and fills); afterload is the load the heart pushes against after it starts contracting (resistance to ejection).
If a patient has high blood pressure, how might this affect afterload?
If a patient has high blood pressure, afterload will increase given the left ventricle has to push even harder to compensate for the higher pressure and resistance.
Define: Stroke Volume
Normal Range?
Def: The amount of blood ejected from each ventricle (aortic and pulmonic semilunar valves) with each heartbeat.
Normal Range: 60-130 mL/beat; Average: 70-80 mL/beat
Note: Both ventricles have a stroke volume; however, the stroke volume usually pertains to the LEFT side of the heart, given it perfuses the body with oxygenated blood (systemic circuit).
Note: About 2/3 of the blood is ejected with each beat; 1/3 remains in the ventricle so that pressure can build to open the valves.
Decreased Stroke Volume
Significance
Signs & Symptoms
Significance: Lack of proper blood return.
Causes:
Dehydration
Bleeding/Hemmorphage
Signs & Symptoms:
Cardiac Deficits
N/V/D
Note: If left untreated, decreased SV can lead to hypovolemic shock.
Increased Stroke Volume
Significance
Causes
Significance: The heart recieves more oxygenated blood.
Causes:
Sex
Acute Threats
Exercise
Define: Cardiac Output
Normal Range?
Def: The amount of blood the heart pumps out per minute.
Normal Range: 3.5-8 L/minute; Average: 5.5 L/min
What is the formula to calculate cardiac output?
CO = HR x SV
CO: mL/min
HR: beats/min (bpm)
SV: mL/beat
Define: Contractility
The strength of the squeeze.
Decreases with age; is maintained with exercise.
Define: Compliance
The ability/how easily the ventricle expands when filling.
Decreases: Stiff/Overstretched Ventricles
Limit SV and cause dyspnea or chest discomfort.
Increases: Stretchy Ventricles
Define: Contractility (Frank-Starling Law)
Optimal Stretch? Overstretch?
Def: The idea that the heart can alter its cardiac output according to the incoming volume of blood.
Optimal Stretch (Normal Preload): Stretching a rubber band just the right amount results in a powerful, crisp snap (Optimal Stroke Volume).
Overstretch (Heart Failure): Continuously overstretching the rubber band ruins its elasticity. When released, it provides a weak, floppy snap (Poor Contractility).
Decreased Cardiac Output (CO)
List conditions associated with a decreased CO & interventions.
Signs/Symptoms:
Dehydration
Poor Skin Turgor
Decreased Urine Output
Sunken In Fontanelles
Dry Mouth
Low HR/BP
Sunken Eyes
Blood Loss
Interventions:
Check: WBC, Heart Monitor, Electrocardiogram (ECG)
Increased Cardiac Output (CO) Signs & Symptoms
List signs and symptoms & interventions.
Fever
Anemia
Fluid Overload
Anxiety
Pregnancy
Pain
How does vessel diameter affect resistance?
Small Diameter → Higher Resistance (Vasoconstriction)
Larger Diameter → Lower Resistance (Vasodilation)
What happens to blood flow if resistance increases? Why?
If resistance increases, blood flow decreases.
Why?: Flow is dependnt on the pressure pushing blood and ressistance opposing it. When resistance increases it becomes harder for blood to get through, therfeore less blood moves foward unless pressure rises to compensate.
List noninvasive/indirect ways to monitor hemodynamics.
Capillary Refill (<2 sec)
Skin Color & Temperature
Urine Output (Kidney Perfusion)
Mentation (Brain Perfusion)
NIBP (Cuff Blood Pressure)
List invasive/direct ways to monitor hemodynamics.
Arterial Lines (A-Lines)
Central Venous Pressure (CVP Lines)
Pulmonary Artery Catheters
Note:
Indicated when vital signs are NOT enough to evaluate cardiac status.
Arterial Lines
Are they noninvasive or invasive? Indirect or Direct?
Location?
What do they measure?
Invasive & Direct
Location: Arteries (usually radial artery)
Measure: Continuous beat-to-beat blood pressure monitoring and arterial blood sampling
Central Venous Lines
Are they noninvasive or invasive? Indirect or Direct?
Location?
What do they measure?
Invasive & Direct
Location: Large Veins (tip in the superior vena cava)
Measure: Central Venous Pressure & Fluid Status
Blood may be drawn from it.
Pulmonary Artery Catheter
Are they noninvasive or invasive? Indirect or Direct?
Location?
What do they measure?
Invasive & Direct
Location: Passes into the heart and terminates in the pulmonary artery (lungs).
Measure: Pulomary Pressures
What are critical things to consider in terms of arterial lines, central venous lines, and pulmonary artery catheters?
Vascular Assessment: Continuously check temperature, color, and capillary refill of the extremity distal to the insertion site.
Hemorrhage Risk: Ensure connections are secure; patients can bleed out rapidly if line disconnects.
Insertion Safety: Monitor carefully to ensure surrounding structures are not punctured during placement.
After removal, the patient may lie down for 6-8 hours; keep the site clean and dry, and let it scab.
Mean Arterial Pressure (MAP)
Definition
Calculation
Normal Range
Define: estimates the average pressure in arteries over one cardiac cycle and is used as an indicator of organ and tissue perfusion.
Calculation:

Normal Range: 70-100 mmHg
Mean Arterial Pressure (MAP)—- List critical ranges.
<60 mmHg: Perfusion to vital organs ceases (STARVATION ZONE); indicates insufficient pressure to perfuse tissues and organs.
Elevated MAP: does not mean that tissues and organs are being perfused better; indicates that a higher force is required to maintain perfusion.
CHRONIC ELEVATION: Causes intense stress in the heart muscle…drives up the buildup of fatty deposits (atheroma) on arterial walls, heart muscle compensates by growing thicker (weakens over time), and leads to advanced heart disease, blood clots, MI, stroke, and shortened lifespan.
ACUTE ELEVATION: Medical Emergency—overwhelming blood flow forces its way into end-organs, causing acute organ failure.
Oxygenation: Pulse Oximetry
List the source, measurement, and target.
Source: Non-Invasive Finger Probe
Measurement: Estimates the percentage of oxygen molecules bound to hemoglobin.
Target: 95-100%
Oxygenation: Arterial Blood Gas (PaO2)
List the source, measurement, and target.
Ideal Patient Population
Source: Invasive Arterial Blood Draw
Measurement: The actual amount of oxygen physically dissolved in the blood plasma
Target: 80-100 mmHg
Ideal Patient Population: Respiratory Distress (Shallow, Agitated)
Note: MORE ACCURATE than Pulse Oximetry!!
Provide the O2 Sat and PaO2 (arterial blood gas) levels for: Normal Oxygenation
O2 Sat: >95%
PaO2: 80-100 mmHg
Provide the O2 Sat and PaO2 (arterial blood gas) levels for: Mild Hypoxemia
O2 Sat: 90-94%
PaO2: 60-79 mmHg
Provide the O2 Sat and PaO2 (arterial blood gas) levels for: Moderate Hypoxemia
O2 Sat: 75-89%
PaO2: 40-59 mmHg
Provide the O2 Sat and PaO2 (arterial blood gas) levels for: Severe Hypoxemia
O2 Sat: <75%
PaO2: <40 mmHg
Clinical Takeaway: A patient can be 100% saturated on the monitor but still be profoundly hypoxic if their total Hgb count is low.
List signs and symptoms of impaired perfusion.
Hypotension
Tachycardia (compensation)
Extra Heart Sounds (S3, S4)
Shortness of Breath (SOB)
Dysrythmia
Shock
Reduced Urine Output
Altered Mentation
Cool, Clammy Skin
List signs and symptoms of impaired local tissue and end-organ perfusion starvation.
Brain: Mentation Changes
Kidneys: Decreased Urine Output
Skin/Extremities:
Cool, Pale Skin
Prolonged Capillary Refill
Decreased/Absent Pulses
Peripheral Edema
Labs: Cardiac Biomarkers
Creatinine Kinase (CK)*
Troponin—-specific to heart damage.
Myoglobin*
CRP*
*Rise from other processes.
Labs: Pump/Stretch Failure
BNP (B-type natriuretic peptide)
Think: “BNP” = Big Failing Pump
Labs: Vascular Blockage Risk (Lipids)
Total Cholesterol
LDL
HDL
Triglycerides
Labs: Flow/Clotting Status
Platelets
Fibrinogen
PT/PTT/INR
D-Dimer—-used to evaluate possible clot formation; it does not confirm a clot by itself.
Labs: End-Organ Perfusion (Kidneys)
BUN
Creatinine
K+
GFR
Labs: Chronic Vascular Health
HgbA1C
Orthostatic Hypotension Criteria
A sustained decrease of ≥ 20 mmHG in SBP or ≥ 10 mmHg in DBP upon standing.
Orthostatic Hypotension
Elaborate on compensatory spike and weight drops.
Compensatory Spike: The heart detects the drop and instantly spikes (5-20 bpm increase) in an attempt to maintain CO.
Weight Drops: Standing up redistributes ~500 mL of blood downward. Sudden fluid shift instantly compromises preload, reducing stroke volume and cardiac output.
Orthostatic Hypotension—-List the steps in order of how you would perform the assessment to rule or or confirm the Dx.
Obtain BP and HR lying down.
Obtain BP and HR sitting.
Obtain BP and HR standing.
Compare readings, return client to bed or chair, report positive results.
NGN Clinical Judgment Model Cheat Sheet
