W1L3: Advanced Drug Delivery Introduction
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/43

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
44 Terms
Oral Drug Delivery
Convenient but limited by solubility, permeability, first pass metabolism
Tablets, capsules, solutions, suspensions, chewables
Parenteral Drug Delivery
IV, SC, IM; bypasses absorption barriers; used for biologics
IV infusion bags, pre‑filled syringes, autoinjectors, depot injections
Inhalation Drug Delivery
Rapid systemic uptake, local lung targeting
Metered‑dose inhalers (MDIs), dry‑powder inhalers (DPIs), nebuliser solutions
Transdermal Drug Delivery
Controlled release, limited by skin barrier
Patches, iontophoretic systems
Topical Drug Delivery
Local effect; minimal systemic exposure
Creams, gels, ointments, lotions
Intrathecal/CNS Drug Delivery
Bypass BBB; used for severe CNS disease
Intrathecal injections, implanted pumps
When do we need advanced delivery systems?
To overcome unfavourable physicochemical properties and biological barriers
To make medicines more practical for people
Examples:
Monthly antipsychotic depots
3‑month contraceptive injections
Once‑daily controlled‑release tablets instead of 3× daily
Inhaled insulin for patients who cannot tolerate injections
Biopharmaceutical Classification System

Drug release
Refers to the processes by which drug molecules are transferred from their initial position in a drug delivery system to the outer surface and, in turn, as solutes, into the release medium
Immediate release capsules
Capsules designed to dissolve quickly (20-30 mins)
Capsule dissolves to allow solute access to API
API dissolves in solute (dissolution)
Dissolved API is available for absorption
Extended release
Over an extended period of time
Controlled release
At a controlled rate
Delayed release
After a lag
Why modify release?
Smooth PK profile - constant level of drug in system
Reduce dosing frequency
Reduce toxicity peaks - adverse reactions
Improve adherence
Protect unstable APIs - not stable in some pHs
How are different release profiles achieved?
Using engineering strategies to produce formulation mechanisms
Diffusion controlled
Dissolution controlled
Erosion controlled
Osmotic systems
Ion-exchange systems
Diffusion controlled systems
Drug molecules slowly diffuse out of a polymer matrix or through a membrane
Drug is embedded in a polymer
Water penetrates the tablet
Drug dissolves and diffuses out a controlled rate
The release rate depends on polymer thickness, drug solubility and diffusion distance

Dissolution controlled mechanisms
The formulation dissolves slowly, controlling how fast and for how long the drug is available
Tablet or coating dissolves gradually
Drug release is limited by dissolution rate
The release rate depends on matrix solubility and erosion rate

Erosion controlled systems
Tablet erodes over time, releasing drug as the structure breaks down
Polymer swells, then erodes
Drug is released as matrix disappears
The release rate depends on polymer erosion and not drug diffusion

Osmotic pump systems (OROS)
Water enters and so osmotic pressure builds and the drug is pushed out through a tiny orifice
Semi-permeable membrane allows water in
Osmotic pressure increases
Drug is pumped out a near constant rate
Provides zero-order release (constant rate)

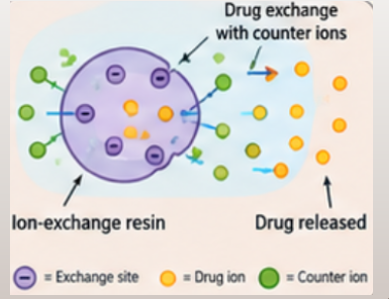
Ion exchange release
Drug is bound to a charged resin and is released when ions in GI fluid swap places
Drug is attached to charged resin beads.
Ions in the stomach displace drug
Release depends on ion concentration
The release rate depends on ion exchange kinetics
Pharmacokinetic benefits of controlled drug delivery
Lower peak concentrations
Higher trough concentrations
More stable plasma levels
Reduced toxicity
Improved efficacy for drugs with short half‑lives
Patient benefits of controlled drug delivery
Less frequent dosing
Better adherence
Less fluctuation in symptoms
Reduced GI irritation (e.g., NSAIDs)
Limitations of controlled drug delivery
Cannot overcome solubility/permeability barriers
Cannot bypass efflux or BBB
Cannot protect fragile APIs
Cannot provide long‑acting exposure (except IM depots - intramuscular drug that creates a temporary storage depot for slow release)
What makes a delivery system advanced?
Ability to control release
Able to protect API
Ability to target tissues
Able to bypass barriers
Ability to improve patient convenience
Physical complexity
Major classes of advanced delivery systems
Liposomes
Polymeric nanoparticles
Micelles
Viral vectors
Lipid nanoparticles (LNP)
Depots and implants
Hydrogels
Liposomes
Tiny spherical vesicles made of phospholipid bilayers.
Mimic cell membranes and can carry both hydrophilic and hydrophobic drugs
Inner aqueous core with hydrophilic drugs encapsulated
Hydrophobic drugs embedded in the bilayer
Protect drug – shielded from chemical breakdown and biological clearance.
Reduce toxicity – API is packaged until it reaches target tissue.
Change biodistribution – liposomes can control tissue uptake.
Good for: Poorly soluble drugs, Highly toxic drugs, Drugs needing targeted delivery

Types of liposomes
Conventional liposomes
PEGylated liposomes
Targeted liposomes
Cationic liposomes
Conventional liposomes
Basic phospholipid vesicles; cleared quickly by immune systems
PEGylated liposomes
Coated with polyethylene glycol (PEG) to evade immune system and extend circulation
Targeted liposomes
The use of surface ligands directs liposomes to specific tissues or receptors
Cationic liposomes
Positively charged; used for gene delivery
How liposomes deliver and release drugs
Liposomes in the bloodstream and may be tagged with targeting ligands to bind to specific receptors on target cells
Liposome ligands bind to receptors on cell membrane and trigger uptake often via receptor mediated endocytosis
Endocytosis - Cell membrane folds around liposome, internalises it into cell - endosome
Endosome in cell matures into lysosome
Lysosome destabilises due to avidity and enzymes and releases drug into cytosol

Polymeric nanoparticles
Tiny polymer made from polymers to carry drugs or other cargo
Encapsulated cargo in a polymer matrix
Polymers degrade slowly = controlled release
Tuneable properties (size, charge and release rates)
Release occurs through diffusion and polymer erosion
Protect API, targeting reduces toxicity, controlled release
Polymeric nanoparticles limitations
Rapidly cleared by macrophages
Limited loading for hydrophobic drugs
Lipid nanoparticles (LNP)
Ionisable lipid structures used to deliver nucleic acid. Delivered to the cells via endocytosis. Genetic material is released via endocytic membrane disruption.
Protect mRNA/siRNA and enable intracellular delivery
e.g. mRNA COVID-19 vaccines
LNPs deliver genetic cargo, liposomes deliver small molecules

LNP Limitations
Trigger inflammatory responses
Rapidly cleared
Depots and injectables
Long-acting injectable or implantable system placed in muscle or subcutaneous tissue
Creates a local drug reservoir (depot) that gradually enters the bloodstream.
Can reduce dosing frequency (weeks to months) and increase adherence and achieve stable plasma levels
Erosion of the formulation, diffusion of the drug from the depot, breakdown of the carrier
e.g. Antipsychotics, contraceptive implants
Limitations of depots and injectables
Invasive, primary care
Cannot be removed easily if adverse effects occur
Doxil
Doxil is a pegylated liposome formulation of doxorubicin
Doxorubicin is a potent chemotherapy drug that treats a wide range of cancers by interfering with DNA replication in cancer cells.
Administered via IV injection
First used 1974 – still used today
Why does doxil need an advanced delivery system
Doxorubicin has a cytotoxic mode of action: intercalates into cancer cell DNA and produces reactive oxygen species that damage DNA, leading to cancer cell death.
Doxorubicin is not selective for cancer cells: cytotoxic mechanism is not tumor specific.
Key toxicities include: cardiotoxicity, myelosuppression, GI toxicity
Cytotoxicity causes pharmacological and toxicological effects
Doxil pharmacokinetic profile
Large tissue distribution underlies toxicity
Rapid clearance from circulation. Very little drug remains in circulation long enough to reach tumours.
How do liposomes help doxil
Liposomes increase size and improve tumour accumulation
Doxil is 100 nm. This size:
Prevents renal clearance
Prevents penetration to healthy tissues
Allows accumulation in tumours via EPR
Doxorubicin molecule: Very small – 543 Da, Can diffuse across tissue. Can enter healthy and tumour cells
PEGylation increases circulation time: Prevents immune clearance, Extends half life (t1/2) from minutes to hours, Allows more drug to reach tumours
Liposome encapsulation reduces cardiotoxicity: Doxorubicin is packaged until it reaches tumour tissue
Controlled release smooths PK: Doxorubicin is released slowly via diffusion, EPR trapping in the tumour allows for a build-up of doxil LNP, Less toxicity and better tumour exposure
Doxil LNP
Much bigger – 100 nm
Too big to enter normal, healthy tissue
Tumour tissues develop with disorganised, leaky vasculature which allows doxil to enter.
The disorganised vasculature has poor lymphatic draining traps doxil LNP
EPR: Enhanced Permeability and Retention
Doxil FDA approved indications
Ovarian cancer after failure of platinum‑based chemotherapy
AIDS‑related Kaposi’s sarcoma after failure of prior systemic therapy
Multiple myeloma, in combination with bortezomib, in patients who have received at least one prior therapy