Pregnancy and Lactation - Philips
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/81

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
82 Terms
What was important about the treating for two initiative?
expand research and build infrastructure for birth defects and ID risk factors
evaluate evidence: expert review process to compare treatment options to ID safe options
educate
What 3 things does the CDC provide technical assistance for?
Antiretrovirals, antiepileptics, vaccines and medications in pregnancy surveillance system
What are the stages of pregnancy?
fertilization: sperm attach to egg → zygote
embryonic period: body forms
fetal period: maturation of structures

What does GxPTPAL mean?
gravidity: numbers of pregnancy
parity: number of fetuses delivered after 20 weeks gestation
term deliveries
premature deliveres
aborted or ectopic pregnancies
living children
GxPTPAL
How do you calculate due date?
add 7 d to first day of last menstrual period then substract 3 months
what is gestational age?
age of embryo beginning w first day of last menstrual period (2 wks prior to fertilization)
When do the 3 trimesters start?
first: 0-13 wks
second: 14-26 wks
third: 27-40 wks
What increases when a pt becomes a mother?
plasma volume, Vd, CO, wt, gastric pH, blood flow (renal, skin, breasts), CYP3A4, 2D6, 2C9
What decreases when a pt becomes a mother?
albumin, BP, GI motility, CYP1A2, 2C19
What is the impact on the fetus? (3 things)
amniotic fluid: provide protection, nutrients, growthfactors and allows for movement and breathing
umbilical cord: exchange blood betw mom and fetus
placenta: barrier betw mom and fetus that allows for gas exchange, waste removal and medication transfer
T/F the placental barrier allows for passive diffusion of medications
true
medications are more likely to cross the placental barrier if they have…
low molecular weight (<600daltons)
lipophilic
non-ionized in maternal blood
low protein binding
medications are less likely to cross the placental barrier if they have…
fetal-maternal conc gradient
maternal blood pH is less acidic
placental blood flow
presence of drug metabolizing enzymes: blocked by immature fetal liver
What is a teratogen and increases risks for it?
substance with potential to alter tissue development or organogenesis (weeks 2-8 post-conception vulnerable)
INC risk: time of exposure, developmental stage during exposure, maternal dose, freq, PK
There are 5 FDA pregnancy categories (ABCDX). Describe them in simple words.
A: adequate and well controlled but fail to demonstrate risk in first trimester
B: animal studies fail to demonstrate risk, no adequate studies in women
C: animal studies show ADE on fetus, potential benefits may warrant use of drug
D: positive evidence of human fetal risk but experience/studies in humans may warrant use of drug
X: positive evidence of human fetal risk and risks clearly outweight benefits (BAD)

What were the limitations of the rules before the pregnancy and lactation labeling rule?
classify teratogenic risk after first exposure BUT it assumes B is safer than C and does not address lactation
What pregnancy category are ACE/ARBs classified as?
C/D:
1st trimester (C): CV and CNS malformations
2nd and 3rd trimesters (D): oligohydraminos, renal failure, patent ductus arteriosus, death
What pregnancy category is methotrexate classified as?
D/X
Category X in psoriasis or rheumatoid arthritis
Fetal malformations (GI, skeletal, craniofacial, cardiopulmonary), developmental delay
What pregnancy category are misoprostol, isotretinoin, thalidomide, warfarin, and statins classified as?

What pregnancy category are paroxetine, valproic acid, carbamazepine, phenytoin, benzodiazepines, and lithium classified as?

pt presents with hoplessness, worry or overall worse mood, poor concentration, lacking energy, potentiall suicidal tendencies, persistent feelings of worthlessness or guilt, INC/DEC appetite, inability to sleep properly, slowing thoughts and actions, diminized interest or pleasure in previously enjoyed activities. What do they have and what should you do next?
MDD; additional screen during comprehensive postpartum visit
psychotherapy: first line in mild-moderate
antidepressants: target neurotransmitter deficiency
What are the official diagnosis criteria for MDD during pregnancy?
DSM-5: MD episode during pregnancy or in first 4 wks after delivery
ACOG: MD episode during pregnancy or in first 12 months after delivery

pt just found out they are pregnant. They have maternal anxiety, life stress, ho depression, lack of social support, unintended pregnancy, low education or socioeconomic status, domestic violence, smoking, single status, and poor relationship quality. what are they at risk for?
MDD
MDD during pregnancy is associated with decreased brain levels of what?
serotonin
NE
ACh
dopamine
What medications are used as second line for mild-moderate depression OR as first line for severe depression w/wo psychotherapy? This medication is not known to affect reproductive capabilities
SSRIs: citalopram, escitalopram, or sertraline
What medications should you not use for MDD in pregnancy?
paroxetine or fluoxetine bc harmful
SSRIs, SNRIs, mirtazepine, bupropin, most TCAs don’t have enough evidence to support increased risks
What are pts taking antidepressants at risk of?
congenital malformations
elevated CV malformation
gestation SSRI use assoc w spontaenous abortion
REVIEW Antidepressant pregnancy risk categories
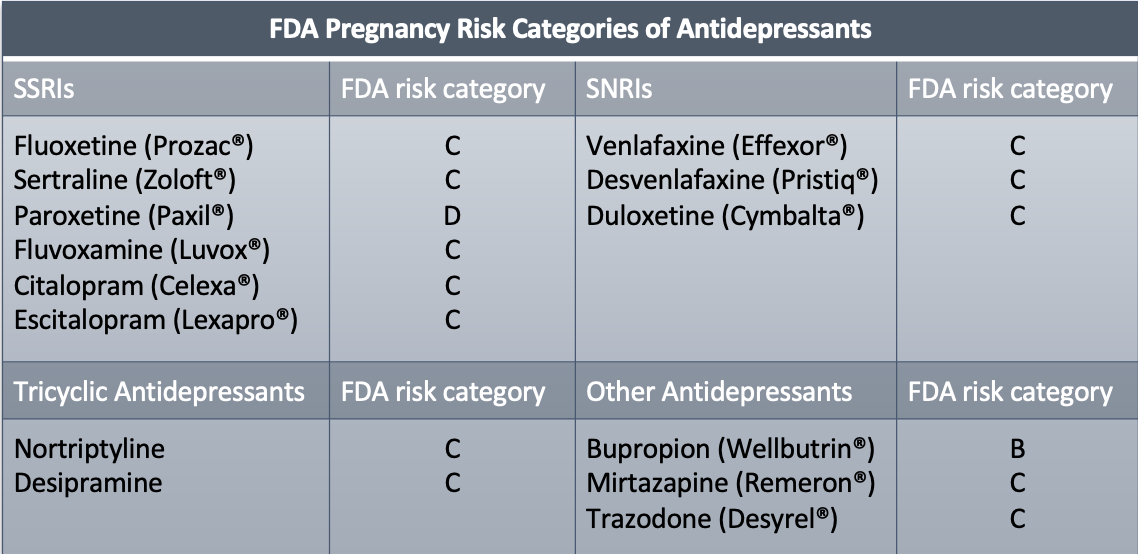
What are somethings to consider when counseling a patient with antidepressant discontinuation syndrome?
results from abrupt discontinuation, caution in antidepressants w shorter duration of action
pts will experience flu like symptoms, anxiety, HT, sweating, n
resolve within 2-14 days by using supportive care
If a fetus is exposed to SSRI depressants in the third triemster, what might happen?
they are at risk of developing poor neonatal adapation marked by jitterness, irritability, tremor, respiratory distress, and excessive crying
Anxiety is chronic, excess perception of real or perceived danger that threatens the security of an individual which produces uncomfortable and potentially debilitating psychological and physiologic arousal. It may impair normal daily functioning. What is anxiety during pregnancy associated with?
spontaenous abortions
preterm delivery
delivery complications
prolonged labor, labor precipitation and fetal distress
At least once during the perinatal period, use a standardized validated tool called GAD-7. If screened during pregnancy, additional screening should then occur during comprehensive postpartum visit. SEQ the test

in mild or less severe cases of anxiety during pregnancy what is the initial preferred treatment?
psychotherapy
What is second line treatment for mild cases of anxiety and first line treatment for moderate-severe cases?
pharmacological therapy: antidepressants (same as depression meds)
What is not recommended for anxiety during pregnancy?
benzodiazepines (-pam) due to being assoc w teratogenic fx, and can cause infant sedation, withdrawal, floppy infant syndrome, hypothermia, lethargy, poor respiratory effort and feeding difficulties in the 3rd trimester
iPledge is a mandatory safety program required by FDA to prevent severe birth defects caused by acne medication isotretinoin. SEQ the therapy regimen
dispense max quantity for 30 days
females of childbearing potential must select and use 2 forms of effective contraception for one month prior, during and one month after therapy
must have 2 negative preg tests prior to first prescription
must be dispensed within 7 days of pregnancy test: 30 days if not potential
What are the non pharmacological therapy for gestational diabetes?
medical nutrition therapy (MNT)
carb controlled meal plan: carbs, fat, protein, micronutrient needs, weight and caloric needs, exercise
What is the first line pharmacological treatment for gestational diabetes when glycemic controlled cannot be achieve with MNT and exercise?
insulin; dose requirement increases the further into the pregnancy (as time passes)
REVIEW INSULIN TABLE

Which types of insulin are safe to use in gestational diabetes considering insulin is excreted into breast milk?
lispro, aspart, regular, NPH (category B)
What is something to consider about insulin regular?
at risk for in between meal hypoglycemia
T/F metformin and glyburide are alternative options for gestational diabetes
true
What are the clinical pearls of metformin?
MOA: inhib gluconeogenesis to INC insulin sens and DEC glucose absorption
ADE: nvd and flatulence
CI: lactic acidosis, hypoxemia predispositions like acute MI, resp fail, CV fail , ACHF, sepsis
PREGNANCY CATEGORY B: long term NO, 2nd and 3rd NO
lactation compatible
What are the clinical pearls of glyburide (diabeta)?
MOA: INC insulin secretion
ADE: hypoglycemia, nd, heartburn, dizzy, blurry vision
PREGNANCY CATEGORY B/C: discontinue at least 2 wks prior to expected delivery date bc infant may have hypoglycemia for 4 days
lactation compatible
What clinical pearl is different in glipizide (glucotrol) compared to glyburide?
PREGNANCY CATEGORY C: discontinue 1 month prior to expected delivery date
What is the nonpharmacologic therapy for HT in pregnancy?
exercise
prevent excessive wt gain
diet: limit sodium intake
pregnant pt is experiencing HT. What is the pharmacologic therapy?
labetalol, nifedipine, methyldopa, thiazide, ACE or ARBs
What is something to consider about using labetalol and nifedipine in HT during pregnancy?
labetalol: fatigue, depression, xerostomia, long term effects on lactation
nifedipine: heart problems, do not use sublingual, lactation compatible
both category C
What is something to consider when using methyldopa or thiazide in pregnant pts with chornic HT and gestational HT?
methyldopa: fatigue, depression, xerostomia
thiazide: HoT and hypokal, 2nd line agent
both category B
What is something to consider with ACE/ARBs in pregnant pts with HT?
category C/D
may cause low amniotic fluid, renal failure, CNS and CV malformations
What is the first line agent for preeclampsia/eclampsia in pregnant pts with HT?
labetalol; BUT CI IN ASTHMA, HEART DISEASE, OR CHF
What are the alternative agents for preeclampsia/eclampsia in pregnant pts with HT?
hydralazine: category C, higher/freq dose assoc w fetal distress
nifedipine: reflex tachycardia
SEQ treatment pathway for pregnant HT pts with BP >140/90mmHg and <20 wks gestation
chronic HT → (plus proteinuria) → superimposed preeclampsia
SEQ treatment pathway for pregnant HT pts with BP >140/90mmHg and >20 wks gestation
no proteinuria → gestational HT
proteinuria → preclampsia → (plus seizures) → eclampsia
What do you treat a pregnant patient with chronic HT and gestational HT?
oral labetalol, nifedipine Xl, methyldopa, thiazide diuretics
What do you give a pregnant pt with severe acute episodes of HT with?
labetalol IV, hydralazine IV, oral nifedipine
Generally you should avoid ACE/ARBs in HT in pregnancy. Only use antihypertensives when
Systolic blood pressure is > 160mmHg and diastolic is > 110mmHg
What is the agent of choice for pain relief in pregnancy?
acetaminophen; category B
Should you give a pregnant woman ibuprofen, naproxen, or aspirin?
ibuprofen and naproxen: avoid in 3rd trimester
C: <30 wks gestation
D: >30wks gestation
aspirin: NO
What is the decongestant of choice for pregnancy?
pseudoephridrine; may cause gastroschisis, not first line for rhinitis
What is the antihistamine of choice in pregnancy?
chlorpheniramine; not diphenhydramine bc of oxytocin like fx
Are guaifenesin and dextromorphan recommeded in pregnant pts?
NO
What are pharmacological agents recommended in pregnant pts experiencing emesis?
Vitamin B6, antihistamines, ondansetron, metoclopramide
Is it recommended to treat diarhea in pregnant pts?
no, risks outweight benefits
What is the agent of choice for diarrhea in pregnancy? try to avoid anyways
kaolin/pectin; does not cross placenta
then loperamide
DO NOT GIVE PEPTO BISMUL (salicylate form) OR ATROPINE
What is the agent of choice for acid reflux in pregnant pts?
antacids: aluminium and magnesium hydroxide (maalox) or calcium carbonate (tums)
What is the alternative treatment for acid reflux?
simethicone
What is the recommendation for breastfeeding?
exclusive breastfeeding for 6 mo
continuoation of breastfeeding for 1 yr or longer is mutually desired for mom and baby
Describe mammary development
Ducts: estrogen
• Lobules: progesterone
• Prolactin levels gradually increase during pregnancy
• Breast enlargement due to these hormones
What is the composition of breast milk?
Proteins: whey and casein
• Growth factors | Immune factors |Cytokines
• pH = 7.2
What are the benefits of breastfeeding for the mother?
DEC post partum bleeding, depression, T2DM, cancer
quicker recovery of pre-pregnancy weight
lactational amenorrhea
What are the benefits of breastfeeding for the infant?
protection against illness/allergies
DEC risk for sudden death infant syndrome
DEC obesity later in life
What are the CI for breastfeeding?
HIV
untreated brucellosis
HSV with breast lesion
metabolic disorder of classic galactosemia
human T-cell lymphotrophic virus I or II
Active TB (resume after 2 wk treatment)
varicella: occurs 5d before through 2d after delivery
drug use
radioactivity, antimetabolite or chemotherapy
amphetamines, ergotamines, statins
What are the properties that promote medication transfer to milk (passive diffusion)
high F, pKA (>7.2)
low molecular weight (<200 daltons), protein binding
lipophilic
long half life
What does the milk to plasma ratio signify?

What is the theoretical infant dose?
Estimates maximum dose an infant may receive through milk
Cmilk * Daily infant milk intake
T/F NSAIDs may transfer in breastfeeding after short term use, small pox and yellow fever are contraindicated in breastfeeding
true
While antidepressants are not contraindicated in breastfeeding what are the possible ADE?
potential for developmental issues
• Somnolence, restlessness, irritability, decreased feeding and weight gain
• Monitor neonates and infants for changes in growth and development
What are the first line interventions of breastfeeding and mild depression?
CBT: Cognitive Behavioral Therapy
IPT: Interpersonal Therapy
What are the second line options for breastfeeding and mild depression?
Citalopram, escitalopram and sertraline
Which immmunizations should pregnant women have?
influenza: annually
tetanus, diptheria, and Tdap: every pregnancy in 3rd trimester
Which immunizations should pregnant women NOT get?
HPV, MMR, varicella