hemodynamic monitoring - Unit 2 AH3
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/21

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
22 Terms
hemodynamic monitoring
early identification of complex medical problems of the critically ill pt (airway breathing circulation)
assess for the presence of shock and cardiac and pulmonary abnormalities
MI complications
the nurse can evaluate the pt’s immediate response to txs
inotropic meds (ex: dopamine)
mechanical support (ex: ventilator)
cardiac output
the volume of blood pumped by the heart each minute
normal: 4-6 L/min
can be measured:
pulmonary artery catheter
echocardiogram (estimate)
indirectly via functional hemodynamics
stroke volume
the volume of blood pumped by the left ventricle w/ each heartbeat
dependent on three important factors: preload, afterload, and contractility
preload
the end diastolic pressure or volume that stretches the right ot left ventricle
reflects a pts fluid volume status
volume of blood filling the ventricle during end diastole
indirectly measured on the right side:
right atrial pressure (RAP)
central venous pressure (CVP)
normal 2-6 mm Hg
indirectly measure on the left side:
pulmonary artery occlusive pressure (PAOP)
“wedge” or "PCWP)
normal 8-12 mm HG
afterload
the force or resistance the ventricles must overcome to eject blood into the pulmonary circuit or aorta
contractility
the inherent ability of the heart muscle to contract independent of preload and afterload
poor contractility directly affects CO and decreases SV
oxygen delivery
the amount of o2 delivered to the tissues
determined through the evaluation of CO and arterial oxygen content (PaO2)
normal CO = 4-6 L/min
SVO2 (mixed venous O2 saturation) **on table
the relationship between oxygen delivery and oxygen extraction at the tissue lvl
tells you how the patient is UTILIZING oxygen
can be drawn from a central venous catheter (central line; measures pressure in right atria) or pulmonary artery catheter (swan-ganz; measures pressure in pulmonary artery)
normal SVO2 = >70%
low: <70% = tissues are extracting more O2 than normal, this may result from a decrease in O2 delivery (due to low hemoglobin or low cardiac output)
high: normal, should be 70-100%
oxygen ** not on table
SpO2 95-100%
DO2 (decreased O2 delivery)
decreased hemoglobin
decreased CO
decreased SpO2/SaO2
we normally extract about 25-30% oxygen to the tissues
SvO2 >70%
VO2 (increased O2 consumption)
increased work of breathing
shivering
fever infection
agitation
nursing care
subtract normal extract of O2 from spo2 and it makes sense that SVO2 is 70%
hemodynamic monitoring systems
arterial catheter (a-line)
measures BP, MAP
can obtain ABGs
central venous catheter
measures pressure in the right atria
CVP (central venous pressure)
can obtain SvO2 through this catheter
pulmonary artery catheter (aka PA or Swan -Ganz catheter
measures pressure in the pulmonary arteries (can indirectly measure left heart function)
can obtain SvO2 through this catheter
pressure bag and transducer set up
pressure bag
mostly radial, but can have femoral (just don’t want it bc infection near groin can be very common, but can be used if issues with arms (ex: arms crushed)
pressurized so blood cant come out, and gives blood pressure
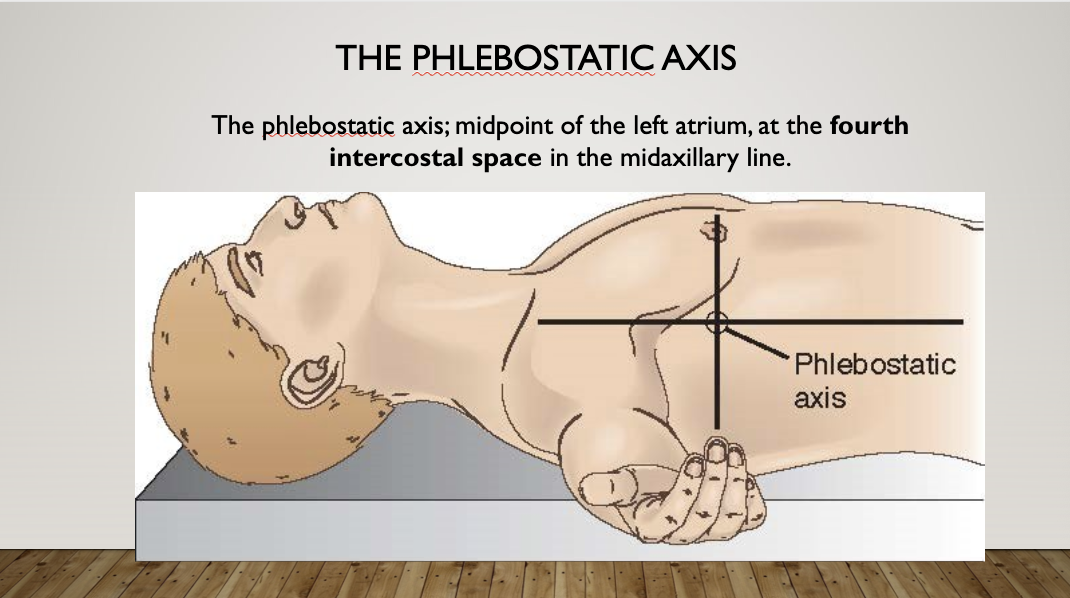
Phlebostatic axis
midpoint of the left atrium, at the fourth intercostal space in the midaxillary line
transducer need to be even with this axis to get a real bp and if not in line with this axis it can give wrong number
if move HOB or body make sure transducer stays in line at all times
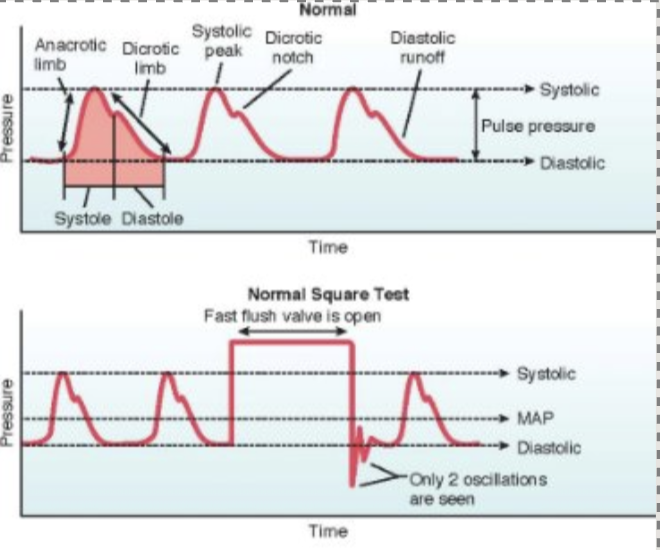
arterial catheter (a-line) ***on table
an arterial line is a small catheter inserted into an artery used to display a constant systemic BP
continuous blood pressure monitoring, MAP
especially useful for pts w/ labile BP on vasoactive meds
normal BP = 120/80 mmHg
normal MAP = >65 mmHg
>60 mmHg for organ perfusion, if low not perfusing organs
low: hypotension, consider causes
high: hypertension, consider causes
Transducer and pressure bag (so blood cant come out {mostly radial, but can be femoral} set up, leveled at phlebostatic axis (transducer needs to be even w/ this axis, midpoint of left atrium at fourth intercostal space mid clavicular) or could give wrong BP #, if you raise HOB need to keep transducer aligned
ABG sample
monitor a pt acid-base and oxygenation status
NURSES DON’T DO THIS, A DOCTOR OR RESPIRATORY MUST DO THIS
NEVER INFUSE ANYTHING THROUGH IT! REMEMBER, IT IS ARTERIAL NOT VENOUS
if comes out need gauze and pressure because it is an artery (high risk for bleeding)
pulses paradoxus: exaggerated blood pressure variation w/ respiratory cycles = blood pressure decreased w/ inspiration
causes: cardiac tamponade, COPD, asthma
IBP vs NIBP vs MAP
IBP: invasive BP (in artery)
NIBP: noninvasive BP (what we as students normally take w/ bp cuff)
MAP - mean arterial pressure needs to be greater than 65 mmHg

Pulses paradox
is the term used to describe an exaggerated blood pressure variation w/ the respiratory cycle
found in cardiac tamponade or during chronic obstructive pulmonary disease or asthma exacerbations
what medications would require an A-line
vasopressers (increased BP)
norepinephrine (Levophed or Levo)
levo is first line vasopresser
effect: it’s a vasopressor - increased bp and increased svr, some increased CO
is titrated - moving it up and down per protocol based on BP
monitor closely for extravastation
IV moves from vein to tissue and will kill the tissue causing necrosis and amputation
med is infused into tissue
watch out for:
bradycardia, dysrhythmias, HTN, renal artery vasoconstriction (low urine output)
digit and gut ischemia at higher doses
alpha (periphery {the rest of blood vessels in body and helps constrict vessels) and beta 1 (the heart {beta 2 would be the lungs})
vasopressin (pitressin)
effect: it’s a vasopressor: increased BP, increased SVR
DO NOT TITRATE
2nd line vasopressor in sepsis and cardiac surgery
also given for gi bleeding and diabetes inspiidus
phenylephrine
effect: vasopressor - increased BP, and increased SVR
TITRATE
watch out
reflex bradycardia - due to selective vasoconstriction and elevation of blood pressure
arrhythmias
HTN
chest pain
all 3 meds need central line and all need to run on it’s own line
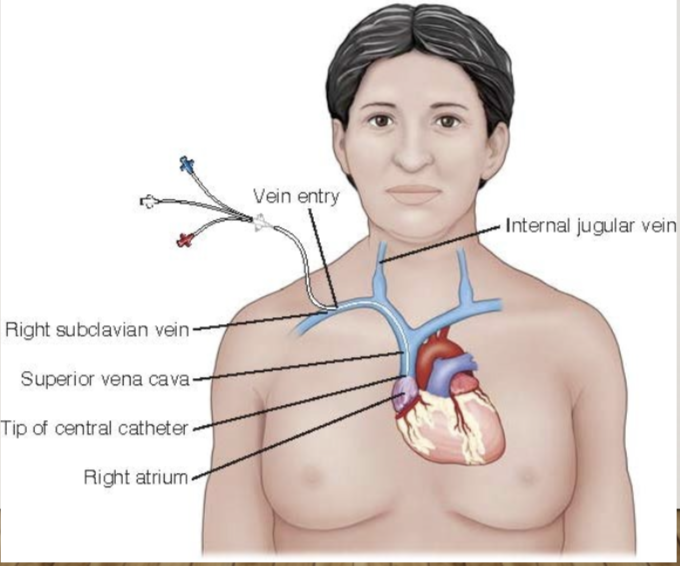
central venous pressure **on table
central venous pressure - provides information about the Right side of the heart, this reading is taken through the distal port of a central line
long catheter placed in the internal jugular (IJ), subclavian (SC), or femoral vein
right atrial pressure
the CVP lvl indicates mean RA pressure (indirect way to measure preload) and is typicaly used as an estimate of right ventricular filling pressures or volume returning to the right heart from the systemic circulation (preload)
normal CVP is 2-6 mmHg
lower number = “dry” fluid volume deficit
high number = fluid volume overload
pulmonary artery catheter
provides information about the right and left side of the heart
right side:
pulmonary artery pressures
reflect the BP in the pulmonary artery
normal parameters are pulmonary artery (PA) systolic 15-30 mmHg and PA diastolic 4-12 mmHG (about 25/10)
if high = pulmonary hypertension
if low = impaired right heart function
left side:
pulmonary artery occlusion pressure/pulmonary artery wedge pressure (PAOP or PAWP) - indirect measurement of left atrial pressure
normal is 8-12 mmHg
10mmHg
if high:
fluid volume overload
mitral stenosis or insufficiency
left ventricular failure
cardiac tamponade
constrictive pericarditis
high lvl of PEEP
a PA (Swan-Ganz) catheter is a flexible, balloon tipped catheter that is guided through the right side of the heart and into the pulmonary artery
the PA catheter is 110 cm long and has four lumens, the distal, proximal, thermistor, and inflation lumens, each of which leads to a specific port. some PA catheters have a second proximal lumen used for IV medication infusion