Medicinal Chemistry and Pharmacology of Erythropoisis-Stimulating Agents, Phosphate Binders, Vitamin D Analogs, Calcimimetics
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/71

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
72 Terms
What is Erythropoisis?
the production of red blood cells (RBCs)
What is Hematopoiesis?
The continuous process of replacing mature blood cells.
What is the ability of hematopoietic stem cells?
They can develop into many different types of blood cells
Hematopoietic stem cells are located in the marrow cavities of:
Skull
Vertebral bodies
Pelvis
Proximal long bones
What stimulates the stem cells?
SCF = stem cell factor
FL
IL-3
GM-CSF
Growth factors that help stem cells develop work with _ to stimulate stem cells to form BFUs and CFUs
cell-cell in the bone marrow
For the erythroid lineage, the important progression includes:
BFU-E → CFU-E → mature RBCs
What is Erythropoietin (EPO)?
the hormone that stimulates red blood cell production
What is EPO produced by?
peritubular interstitial cells of the kidney
a 193 amino acid, ~30-kDa protein
What does EPO bind to?
receptors on committed progenitor cells in the bone marrow
EPO secretion is a
feedback mechanism regulated by oxygen sensing
What is the feedback mechanism of feedback secretion?
Low oxygen/anemia → kidney responds → EPO production → bone marrow RBC production increases
Why can patients with chronic kidney failure develop anemia, and how is epoetin alfa used?
Failing kidneys produce too little endogenous EPO, so epoetin alfa replaces the inadequate EPO production
What is the mechanism of action of epoetin alfa?
It replaces deficient EPO and stimulates committed RBC progenitor cells in bone marrow to increase RBC production
Why must hematocrit/hemoglobin be monitored with epoetin alfa?
To prevent levels from rising too quickly or becoming too high, which increases cardiovascular/thrombotic risk
What hematocrit target is recommended for CKD patients receiving epoetin?
Gradually increase to 33–36%; >36% is not recommended
What is the most common adverse effect of epoetin alfa?
Hypertension
What hemoglobin increase is generally considered safe with darbepoetin?
Less than 1 g/dL every 2 weeks
The goal is not to normalize the hematocrit as quickly as possible, but a gradual rise and monitoring because
rapid increases can cause cardiovascular/thrombotic problems
What are the major functions of calcium?
Muscle contraction, intracellular signaling, blood coagulation, and bone formation/remodeling
Where is most of the body's calcium located?
About 99% is in bone and teeth
What are the major roles of phosphate?
Bone, phospholipids, energy metabolism, enzyme regulation, intracellular functions, and urine buffering
Where is most of the body's phosphorus located?
>80% is in bone
Which hormones regulate calcium and phosphate homeostasis?
PTH, vitamin D, calcitonin, and FGF23
When is PTH primarily secreted?
In response to hypocalcemia (low blood calcium)
How is PTH biosynthesized?
A 115-aa pre-prohormone is processed into an 84-aa hormone and stored in secretory granules
What commercial form of PTH is mentioned in the lecture?
Teriparatide (Forteo), a recombinant 34-aa form of PTH
What is the first step in vitamin D biosynthesis?
UV irradiation of 7-dehydrocholesterol in skin produces cholecalciferol (D3)
What is the major circulating/storage form of vitamin D?
25-hydroxyvitamin D3
[25(OH)D3]
What is the active form of vitamin D?
1,25-dihydroxyvitamin D3
(calcitriol)
What is the mechanism of action of calcitonin?
It inhibits osteoclast-mediated bone resorption, lowering blood calcium
Where is calcitonin produced?
Thyroid parafollicular C cells
What is calcium gluconate used for in hypocalcemia?
IV calcium gluconate treats moderate-severe hypocalcemia and severe hypocalcemic tetany
Why must IV calcium be given slowly?
To avoid cardiac arrhythmias
What is the mechanism of IV bisphosphonates?
They inhibit osteoclast-mediated bone resorption, decreasing calcium release from bone
What is the mechanism of nitrogen-containing bisphosphonates?
They inhibit FPPS, disrupting protein prenylation and osteoclast function
What structural feature identifies a bisphosphonate?
A nonhydrolyzable P–C–P backbone instead of pyrophosphate's P–O–P
What does the R1 hydroxyl group of bisphosphonates do?
Maximizes hydroxyapatite affinity and contributes to antiresorptive activity
What does the R2 group of bisphosphonates affect?
Potency and interactions at the active site
What are the two IV Bisphosphanates drugs?
Pamidronate
Zolexranate
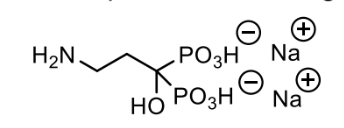
Pamidronate disodium

Alendronate sodium
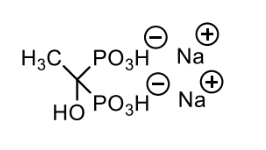
Etidronate disodium

Zoledronic acid (Zolexranate)
What is the mechanism of action of phosphate binders?
They bind dietary phosphate in the GI tract, preventing its absorption and lowering serum phosphate
What is Renagel?
Sevelamer HCl, a nonabsorbable polymeric phosphate binder
What is the mechanism of action of sevelamer HCl?
It acts as a nonselective anion exchanger that binds intestinal phosphate and decreases absorption
Why is sevelamer taken with meals?
To bind dietary phosphate in the intestine before it can be absorbed
What structural feature should you recognize for sevelamer?
A nonabsorbable polymer with amine groups that acts as an anion exchanger.
What are the novel iron-based phosphate binders in the lecture?
Sucroferric oxyhydroxide and ferric citrate
What is the mechanism of sucroferric oxyhydroxide?
Iron(III)-oxyhydroxide binds phosphate through ligand exchange, preventing phosphate absorption
What is important about sucroferric oxyhydroxide compared with sevelamer?
Similar phosphate control with a lower daily pill burden
What is important about ferric citrate?
It binds phosphate and also delivers significant iron, but chronic use can cause iron overload
What adverse effect is common to the iron-based phosphate binders?
Diarrhea

Sucroferric oxyhydroxide

Ferric citrate
What are vitamin D analogs?
Modified forms of vitamin D/calcitriol that can affect calcium/phosphate balance and PTH
What is an important advantage of some calcitriol analogs?
They suppress PTH with less hypercalcemic activity than calcitriol
What is rickets?
A disease involving poor mineralization of developing bone
What is used to treat established rickets?
Vitamin D plus oral calcium
What is calcipotriene?
A synthetic calcitriol derivative with a modified side chain
What is important about calcipotriene's activity in calcium metabolism?
It has less than 1% of calcitriol's activity
What is calcipotriene primarily used for?
Topical treatment/study for psoriasis
What structural feature should you recognize for calcipotriene?
Its cyclopropyl side chain

Calcipotriene
What is a calcimimetic?
A drug that mimics calcium's effect on the calcium-sensing receptor
What is the mechanism of action of cinacalcet?
It increases CaSR sensitivity to extracellular Ca²⁺, decreasing PTH secretion
What type of calcimimetic is cinacalcet?
Type II calcimimetic
What receptor does cinacalcet act on?
The calcium-sensing receptor (CaSR)
How does cinacalcet affect CaSR?
It positively allosterically modulates CaSR, increasing its sensitivity to calcium
What is the ultimate effect of cinacalcet on PTH?
Decreased PTH secretion
Cincalcet →
increase in CaSR sensitivity → decrease PTH