the physiology of carbon dioxide
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/32

There's no tags or description
Looks like no tags are added yet.
33 Terms
CO2
waste product of aerobic respiration
CO2 is produced by the (?) cycle part of respiration
citric acid
oxidation of acetyl-Coa produces ATP and (?)
CO2
mitochondria in cells use glucose and oxygen to produce:
CO2, water and energy
transport of CO2 to the (?) for removal from the body
lungs
CO2 % distribution in the blood
90% diffuses into red blood cells
5% dissolved into blood plasma
5% binds to proteins (haemoglobin)
in red blood cells, CO2 is rapidly converted to H+ and (?) by the enzyme:
converted to H+ and bicarbonate by the enzyme carbonic anhydrase
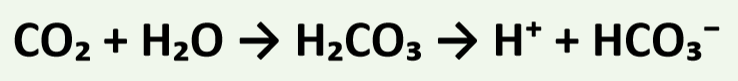
CO2 is quickly converted into HCO3- which allows for the continued uptake of CO2 into the blood down its:
concentration gradient
acidosis
occurs when there are too many H+ ions in the blood
what occurs chemically when HCO3- reaches the lungs? (refer to equation)
HCO3- combines with H+ produced by the oxygenation of deoxyhemoglobin to produce water and CO2
CO2 diffuses into the alveoli and is exhaled as a waste product

what is the normal partial pressure of arterial CO2
35-45mmHg
hypercapnia
too much CO2 in the blood
hypocapnia
too little CO2 in the blood
what can occur to the pH of the blood when there is too much CO2
pH can drop below normal levels
hypoventilation (not breathing enough) can result in (?) levels of CO2 which leads to what type of acidosis?
high → leads to respiratory acidosis
examples of respiratory diseases/impairments that cause abnormally high levels of CO2
Chronic lung diseases (COPD, emphysema)
Respiratory depression
Severe asthma
Hypoventilation
Obstructive sleep apnoea -> problems with breathing when asleep
treatments that restore normal blood gas levels
Improving ventilation
Mechanical ventilation
Intubation
Treat underlying cause of hypoventilation
Use of bronchodilators
Antibiotics (if infection is the cause)
Oxygen therapy
Oxygen tank
CO2 excess can be caused by breathing CO2 rich air (list 3 settings)
In unventilated indoor areas
Classrooms
Submarines
Basements
Occupational setting (workplaces)
Welders
Firefighters
Confined spaces
Natural environments
Volcanic areas
Caves
CO2 levels (see more)
Very high levels of CO2
In submarines and spacecrafts
3000-5000ppm
Typically exposed for days to months
High levels of CO2
In poorly ventilated classrooms/ offices/ public transport
1000-3000pm
People typically exposed for hours
Elevated
Our current atmosphere
Level currently 425ppm
40% higher than pre-industrial levels
People exposed to this throughout life
health effects of increasing levels of CO2 exposure
400ppm → normal air
1000-2000ppm → drowsiness and difficulty concentrating
2000-5000ppm → confusion, headache, and dizziness

physiological response/mechanisms to high CO2 (list 4)
Bicarbonate buffer system
Pulmonary compensation
Renal compensation
Osteological compensation
bicarbonate buffer system
Maintains optimal pH of blood
Neutralises excess acid or base
Too many H+
HCO3- binds with excess H+ to form carbonic acid
Carbonic acid can dissociate into CO2 and water
Too little H+
Carbonic acid releases H+ (and HCO3-)

pulmonary compensation
Central and peripheral chemoreceptors detect changes in the chemical composition of the blood
Communicate to the respiratory centre in the medulla to increase or decrease ventilation
Central chemoreceptors
Located in the brain
Detect pH of cerebrospinal fluid
Peripheral chemoreceptors
Located in the carotid and aortic bodies of the heart
Detect pH of blood as well as O2, CO2, and H+ levels
peripheral vs central chemoreceptor response to elevated CO2 levels
Central chemoreceptors
Blood brain barrier is permeable to CO2
Increase in CO2 will cause more CO2 to diffuse across blood brain barrier
Drives increase in H+ which is sensed by central chemoreceptors
Communicated to respiratory centres
Promotes increase in ventilation
Peripheral chemoreceptors
Increase in blood CO2 and H+ sensed by peripheral chemoreceptors
Communicated to respiratory centres promoting increase in ventilation

renal compensation
Adjusting excretion of H+ and HCO3- via kidneys
Increase in CO2 in blood will increase H+
This increases HCO3- reabsorption
And increases H+ excretion
renal compensation mechanism (explained)
H+ is excreted into the filtrate via Na+/H+ exchangers
Some H+ in filtrate combines with HCO3- to form CO2 and H2O
CO2 diffuses into tubule cell, combines with H2O to produce H+ and HCO3-
H+ produced from 3. is excreted into the filtrate via Na+/H+ exchangers
HCO3- produced from 3. is reabsorbed into the blood via Na+/HCO3- exchangers
NH3 combines with H+ to form NH4+ which is excreted into the filtrate
NH4+ and H+ is excreted via urine overall

osteological compensation
Bones are made up of minerals that can help maintain normal blood pH
Chronic acidosis causes bone reabsorption
Osteoclasts break down and release CO32- and PO43-
These ions act as buffers by binding to excess H+ ions and raising blood pH
Long term this can lead to bone weakening (osteoporosis)
short term exposure to elevated CO2 levels is easily (?)
reversible
long term exposure to elevated CO2 levels can:
lead to renal and osteological impacts
Increasing levels of atmospheric CO2 (can/can’t) be withstood by our ventilatory, renal acid-base compensatory mechanisms and bicarbonate buffering system
can
can we cope with the increasing rise in CO2 exposure?

summary

lecture outcomes