Cardiovascular Disorders
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/33

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
34 Terms
How is the normal flow of adult heart (in terms of stoke volume) differ from newborn?
Adult heart flow output is influenced by heart rate x stroke volume
Neonates no change in stroke volume poorly complient- tachycardia
What are the prenatal screenings for cardiac abnormalities?
Genetics, echo, MRI → cardiac issues can be prenatally diagnosed
Favorable to deliver in a tertiary setting
Prepare parents
APGAR maybe low
Available staff and equipment
Fetal electronic monitoring
What are the risk factors for congenital cardiac disease?
Prenatal History
Family history of cardiac disease
Viral illness: Rubella, 5th disease, Coxsackie\
Chronic medical conditions lupus and diabetes
Advanced maternal age >40 years of age
Intrauterine or perinatal hypoxia; PPH
Teratogenic exposure
Alcohol, recreational drugs, prescription drugs dilantin, lithium, hormones
Fetal Circulation
Umbilical vein, 2 umbilical arteries → the vein brings the oxygenated blood to the fetus and the arteries bring deoxygenated blood and metabolic waste to the placenta to be cleaned by mothers circulation
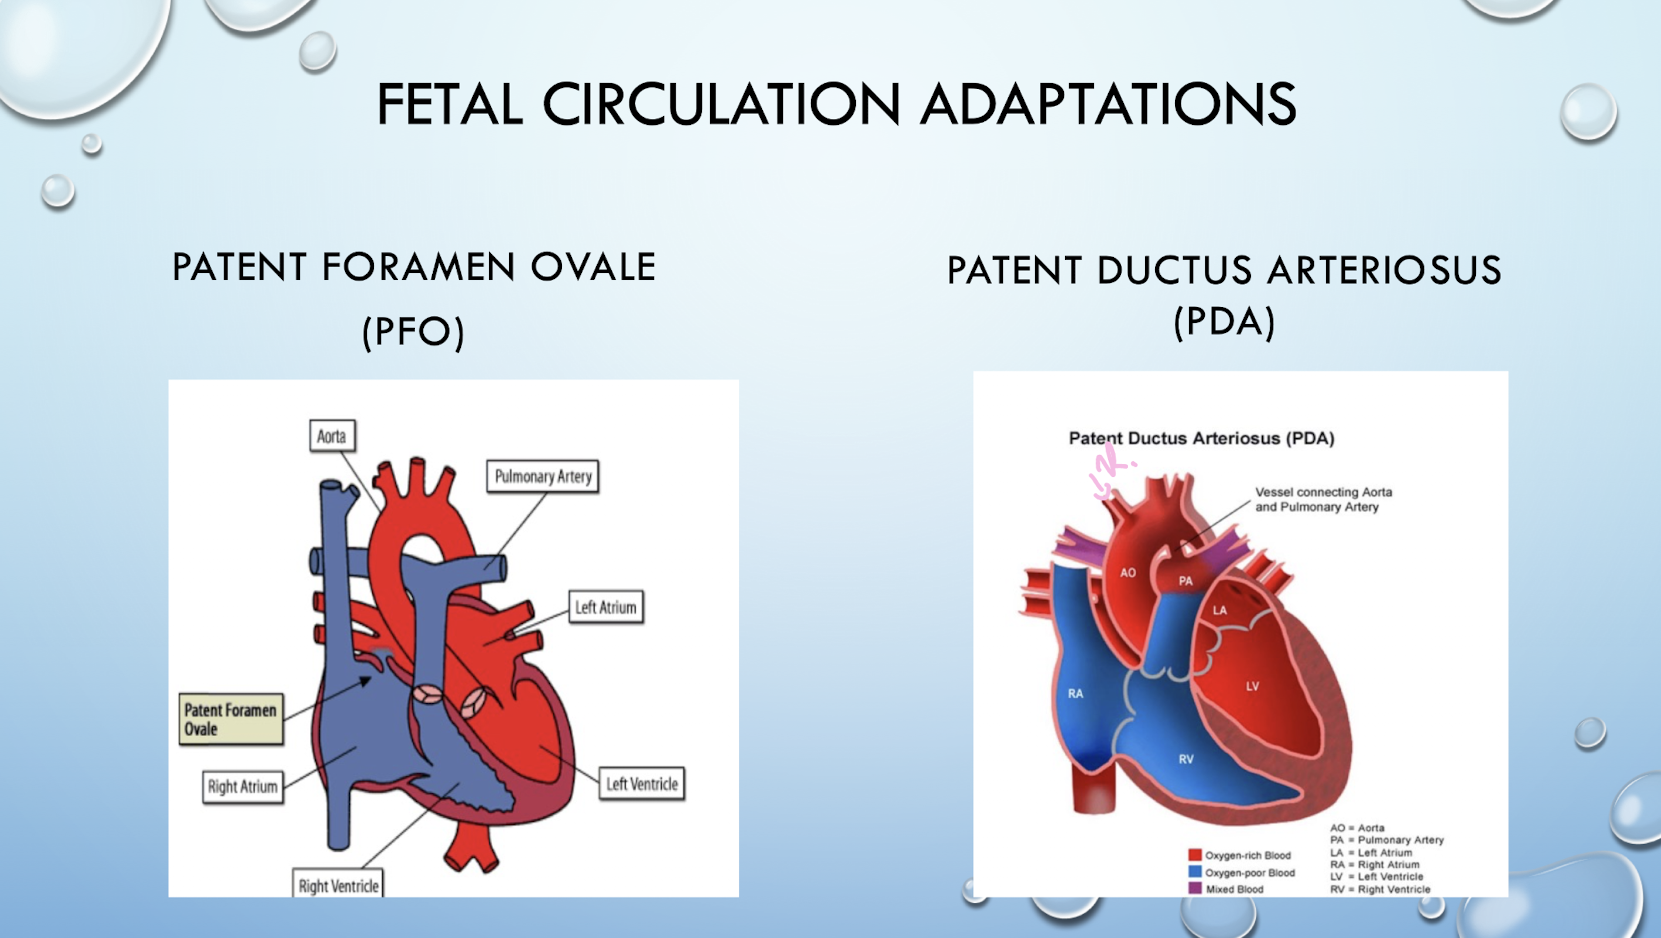
Foramen Ovale: a small, flap-like opening in the wall (atrial septum) between the upper chambers of the heart alowing blood to flow stright from right artium to left atrium bypasing lungs.
Ductus Artriosus: Connects the pulmonary artery to the aorta thus allowing blood to bypass lungs. Prostoglandins keep this open in utero which is why we give them to keep it open in certain situations.
Ductus Venosus: , allowing oxygen- and nutrient-rich blood from the placenta to bypass the liver as placenta does that job in utero.
Shift of gas exchange from placenta to lungs after birth
At first breathe: pulmonary vessels dilate; decrease pulmonary vascular resistance; increase systemic vascular resistance changes blood flow → the left side is higher pressure which is why they right side is considered preductal so the stat prob is put there → thios is why the fetal mecanisms close in addition to decrease of prstaglandins.
What are the S&S of newborn cardiac dysfuction?
Physical exam
Poor purfusion, resp or cardiac failure
VS, BP & pulses; differences between upper & lower extremities; por perfusion → tachy
Ascultation for murmurs
CCHD screening (critical congenital heart disease)
Pulse Ox
Comparison of pre ductul to post ductul >95% at 24 hrs after birth
What is the cardiac asessment?
Health hx
General apperance
Physical examination
Ascultation for murmurs
Pulse strength → would have thready pulse
Cap refil → would be delayed
How are murmurs defined?
Heart sounds that reflect flow of blood within the heart
May occur in systole or diastole, or both
Can occur in a normal heart in periods of stress; anemia, fever, or rapid growth
Can reflect abnormalities in heart or vessels
“Inocent murmurs”= mornal cardiac anatomy and cardiac function
Occur in up to 50% of all children at some time
Cardiac diagnostic tests
CXR→ may see enlargment heart (cardiomegaly); fluid in lungs
ECG
Echocardiogram; echo can check for heart strength & shows HF
CT/MRI
Exercise stress test
Cardiac catherization: Good way of checking pressure in heart & getting idea of what’s actually hapening
What is the management if congenital cardiac heart disease (CCHD) is suspected?
Provide 100% oxygen and other respiratory support as indicated
Evaluate for physical and laboratory signs of shock
Following this evaluation if cardiac disease is suspected
O2 saturation remains less than 75% give Prostaglandin
Carefully evaluate the neonate for any other causes of cyanosis
Pulmonary, sepsis, shock, neurologic issues
What are the two types of heart defects?
Congenital (CHD)
Anatomic → abnormal function
Acquired
Disease process
Infection
Autoimmune response
Environmental factors
Familial tendencies
What are some facts about CHD?
Incidence: 1 in 4 babies
who will need surgery in the first year of life
Major cause of death in the first year of life (after prematurity)
Most common anomaly is VSD (ventricular septum defect)
30% of children with CHD have a genetic syndrome
Examples: Down syndrome, Turner syndrome, 22q11 deletion syndrome, Williams syndrome, and Noonan syndrome
What are the types of cardiac defects (acyanotic; cyanotic)
Acyanotic (O2 not affected)
Increased pulmonary flow
Atrial septal defect (ASD)
Ventricular Septal defect (VSD)
Patent ductus arteriosus (PDA)
Obstructive defects
Coarctation of the aorta
Cyanotic (O2 is affected)
Decreased pulmonary flow
Tetralogy of Fallot
Mixed defects
Transportation of great vessels; two seperate circuits
Oxygen-poor blood returning from the body is pumped right back out to the body without picking up oxygen in the lungs. Oxygen-rich blood from the lungs just goes back to the lungs
What are the things that cause increased pulmonary blood flow defects (PDA, ASD, VSD)? (plus what does this mean in terms of curculation)
Abnormal connection between two sides of heart
Either the septum or the great vessels
Increased blood volume on right side of heart
Increased pulmonary blood flow
Decreased sytemic blood flow
What is Patent Ductus Arteriosus (PDA)?
Fetal shut fails to close
More common among premature infants → bc heart muscle is not strong enough to cause it to shut
Allows blood to flow from the aorta (area of high pressure) through the PDA and into the main pulmonary artery (area of low pressure)
Can lead to pulmonary hemmorhage
Blood floods the lungs and go back into left artium via pulmonary veins
A occusion device may be used to close this opening via cathater
What is Atrial Septal Defect (ASD)?
Occurs when a portion of the atrial septal tissue does not completely form
Blood flows from the higher pressure in the left atrium to the lower pressure in the right atrium → blood flow goes back to RA leading to RA hypertension
Many times, no murmur is noted due to low atrial pressure
Leads to pulmonary overcirculation
Less likely to cause HF
What is Ventricular Septal Defect (VSD)?
Most common congenital defect in newborns
VSD is part of other diagnoses
Happens when a portion of the ventricular septum does not completely close
Blood flows from the left side (high pressure) to the right side (lower pressure)
Most close on their own, but some need surgical closure due to heart failure
Confirmed by echo, treated with diuretics and increased calories to prevent FTT (failure to thrive)
Would have RV hypertrophy; backs into lungs → pulmonary edema
Tetrology of Fallot (4 components, management)
4 Components
RV outflow tract obstruction r/t pulmonary stenosis
VSD
Overriding Aorta (PDA)
RV Hypertrophy
Pulmonary artery gets the extra blood flow → lungs get beat up
Aorta gets least oxygenated blood
Aorta gets the least oxygenated blood
Tet Spells:shuts down ability to get blood to lungs b/c RV tract gets closed when child gets upset
Spasm below the pulmonary valve…
Increases resistance to blood flow
Increased (deoxygenated) blood shunts from right to left across the VSD, causing a cyanotic spell
Treatment of Tet spell
Knees to chest / O₂ / sedation = increased systemic vascular resistance, and O₂ dilates the pulmonary bed'
*Pushes blood back through the pulmonic valve
Heart Failure (presentation in children, clinical manifestations)
The inability of the heart to supply adequate oxygenated blood to meet the metabolic demands of the body
Cardiac output: volume of blood pumped by ventricles each minute
Preload: volume of blood in the ventricle at the point just before contraction → Lasix helps with preload (offloads fluid)
Contractility: the rate and force of fiber shortening → digoxin increases contractility
Afterload: amount of resistance met by the ventricles upon ejection
Volume overload
Pressure overload
Decreased contractility
High cardiac output demands
Pathophysiology
Right-sided failure
Reduced function
Back up to body would see ascites (liver would move down bc of excess fluid back up)
Left-sided failure
Increased pressure; lung congestion
Tachypnea & hypoxia are first
Clinical manifestations
Impaired myocardial function
Tachycardia; fatigue; weakness; restlessness; pale, cool extremities; decreased BP; decreased urine output
Poor feeding, decreased UO meand blood is not getting to kidney → if at RR of like 100 means something is wrong
Pulmonary congestion
Tachypnea, dyspnea, respiratory distress, exercise intolerance, cyanosis
Systemic venous congestion
Peripheral and periorbital edema, weight gain, ascites, hepatomegaly, neck vein distention
What are the goals of management in children?
Improve cardiac function
Decrease preload — how? → diuretics
Decrease cardiac demands
Improve tissue oxygenation → w/ O2
Decrease oxygen consumption
VAD; Ventricular Assist Device- allow for blood flow to be perserved while waiting for heart
Transposition of the Great Arteries (TGA) ( clinical presentation/management)
Cyanotic defect
Second most common congenital defect
”reversal of the great arteries”
Aorta arises from the RV
Pulmonary artery arises from the LV
2 separate circulations
Oxygenated blood returns from the lungs to the LA, goes to the LV and goes back through the PA and to the lungs again
Deoxygenated blood returns from the body to the RA, to the RV and back out the aorta providing deoxygenated blood to the systemic circulation
Infant typically tachypneic
Prostaglandin (PGE) needed to maintain PDA and ”mix” blood→ relaxes muscle to allow for oxygenation to still occur
S/E: It vasodilates as a result facial flushing can occur but the s/e are Apnea and hypotension
Complications of PGE: apnea, hyperthermia
Balloon septostomy will allow mixing through ASD/PFO → Surgical Plan: “Arterial Switch”
Surgically corrected within first 14days of life

Hypoxemia
Hypoxemia
Lower than normal arterial oxygen tension
Hypoxia
Reduction in tissue oxygenation
Cyanosis
Clinical manifestations
Polycythemia
Clubbing
Hyper-cyanotic spells (TET spells)
Coarctation of the Aorta (Diagnosis & Management)
Narrowing anywhere in the aorta
Increased pressure proximal to the defect
Restricts amount of oxygenated blood to lower part
LV has to work harder= LV hypertrophy
Infancy diagnosis most commonly an emergency
Kidney would not get blood flow, lactate acidosis, hypoxia
If you have PDA may be able to get blood flow
Diagnosis & Management
ECHO
4 point BP’s (gradient >10points) → BP in arms would be high & in legs would be low
Bloodwork (lactate)
PGE initiation immediately will open PDA
Balloon/ Stent/ Surgical correction
CCHD screening for prevention

Kawasaki disease (Etiology, management)
Leading cause of acquired heart disease
Acute systemic vasculitis, unknown cause
Duration 6 to 8 weeks, self-limiting
Without treatment of KD, 20%-25% have cardiac complications
Dilation of coronary arteries Coronary artery aneurysms (giant aneurysms >8 mm)
Acute (WEEK 1), subacute (WEEK 2+3)
TREATMENT WITH IVIG
Etiology
Etiology unconfirmed
Peak incidence in toddler ages
Seasonal variations (late winter/early spring)
Widespread inflammation of small and medium- size arteries
Clinical Manifestations
High fever—unresponsive to antipyretics/ antibiotics
“Strawberry” tongue
Edema hands and feet
Extreme irritability (inconsolability) desquamation (SKIN SLOUGH)
Arthritis (JOINT PAIN)
Coronary complications
Rheumatic fever & Rheumatic heart disease manifestations
Inflammatory disease occurs after strep infection
Infrequently seen in United States; big problem in Third World
Self-limiting
Affects joints, skin, brain, serous surfaces, and heart
Most common complication of RF
Damage to valves as result of RF
Clinical manifestations
Carditis—affects muscle layers of heart and most commonly the mitral valve
Polyarthritis—reversible affecting large joints of the body
Erythema; Transitory rash on trunk and proximal extremities

What is the care of the family and child with congenital heart disease?
Help family adjust to the disorder
Educate family
Help family cope with effects of the disorder
Prepare child and family for surgery
Surgical interventions:
Open heart
Closed heart procedures
Staged procedures
Prepare child and family for procedures
Cardiac catherization (pre and post op)
Preprocedural care
Preparation/explanation geared toward developmental level
Perform a nursing history and physical exam
Check for allergies
Locate and mark dorsalis pedis and posterior tibial pulses
Sedation management
NPO
Postprocedural care
Cardiac and pulse oximetry monitoring
Vital signs X 15 min
Assess puncture site for bleeding or
hematoma
Monitor pulses, temperature, color of extremity → ensure cap refill & pedal pulses are intact
I/O
Parent teaching
What is the postop care for child for correction of cardiac issues?
Monitor vital signs and arterial/venous pressures
Intra-arterial monitoring of BP
Intracardiac monitoring
Respiratory needs
Rest, comfort, and pain management
Fluid management
Progression of activity
How should fluid status be monitered post cardiac procedure?
Intake
From all sources
All flushes, other intake
Output
From all sources
Chest tube, urine, NG, surgical drains; also include blood drawn for lab work
Urine output <1 ml/kg/hr = possible renal failure
Concern r/t decreased cardiac output
What are the pharmacological approach with cardic disorders?
IV IgG → support immune
Digoxin (Lanoxin)—improve contractility
ACE inhibitors—reduce afterload
ASA, NSAIDs
Lasix—loop diuretic—causes diuresis—monitor potassium
Spironolactone (Aldactone) —K+ sparing diuretic
How are chest tubes monitored after cardiac surgery?
Monitor chest tube drainage q hour for COLOR
Immediate postoperative may be bright red, but changing to serous
Monitor chest tube drainage for quantity
Notify surgeon if chest tube drainage is frank blood or increases
Be alert for cardiac tamponade (rapid onset; life threatening)
What are the postop complications after cardiac surgery?
CHF
Dysrhythmias
Sinus Bradycardia
Sinus Tachycardia
Supraventricular Tachycardia
Lethal Dysrhythmias
Ventricular tachycardia
Ventricular Fibrillation
Decreased cardiac output syndrome
Decreased peripheral perfusion
Pulmonary changes
Neurologic changes
Cardiac transplant
Most common need for transplant related to CHD and Cardiomyopathy
Not an easy decision
VAD’s and ECMO as bridge
Survival improved
If transplanted before 10yr of age= 83% survival
Immunosuppressants for life
Systemic HTN
Primary = no known cause
Secondary = identifiable cause
Pediatrics: HTN is generally secondary to a structural abnormality or underlying pathology
Renal disease
CV disease
Endocrine or neurologic disorders
Dyslipidemia
Identify children at risk and treat early
Treatment = dietary
Restrict intake of cholesterol and fats
If no response to diet → Rx
Colestipol (Colestid)
Cholestyramine (Questran)