AH III Exam 2 - CAD & ACS
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/31

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
32 Terms
What is CAD? (2)
Atherosclerosis forms & occludes coronary arteries; can l/t an MI
Reduced blood flow through coronary microvasculature; can damage vessel walls
What is stable angina? (2)
Chest pain that is caused by physical activity
Symptoms are alleviated w rest/meds
What is unstable angina? (3)
Chest pain that occurs at rest (can also be caused by phys activity)
Does NOT go away w rest/meds
This is an ***EMERGENCY***
What is Prinzmentals angina? (2)
Vessel wall closes & spasms
Typically occurs at night
Labs for CAD (7)
Cholesterol
Triglycerides
LDL/HDL
CK
CK-MB
Tropnin
How do we dx CAD? (2)
****ECG; 12-lead, tells us what’s going on in the heart****
Stress test - conservative way
Gold standard for CAD dx? (3)
Coronary angiography; INVASIVE
Need to do b4 complete occlusion!!!!!
Determines if we can place a stent
PTCA/PCI notes (2) (what is it)
Stent placement
Done in cardiac cath lab; conscious sedation
Coronary artery bypass grafting
Use saphenous vein to make new path for heart & create blood flow again

What is a STEMI? (2)
Infarction with complete obstruction
ST elevation of 1mm > in 2+ leads in 12-lead ECG
EMERGENCY

What is a NON-STEMI
Ischemia with partial obstruction
Still damage!!!
MI S/S specific/nonspecific (7)
Unstable angina
Epigastric discomfort → common in women
N/V
Diaphoresis
Syncope
SOB
Pain between shoulders/jawline
Troponin lab test for MI dx (3)
Detects cardiac muscle damage
Track & trend if elevated
Series of at least 3
Why is CK lab not the best to use?
It’s nonspecific & detects heart & skeletal muscle
What is the GOLD STANDARD for dx of an MI?
*****ECG******
Determines the next steps
If there is an ST-elevation in the ECG what is next?
Coronary Angiography!!!! (heart cath)
Other diagnostic tests for MI (2)
Echo
Stress test
Enzymes for MI (2)
Troponin I*
Most sensitive indicator bc from myocardium
MI = > 0.04 ng/mL
Norm < 0.04 ng/mL
Troponin T
Skeletal & heart muscle
< 0.01 ng/mL
ASA for STEMI tx (4)
1st LINE!!!
Initial dose 325 mg CHEWED then 81 mg indef
Anti-platelet
DO NOT TAKE WITH NSAIDS!!!
Nitroglycerin for STEMI tx (5)
Potent vaso/veno dilator
Reduces PRELOAD
Need to know pt’s BP
Subling 0.4 mg Q5 min x 3
Monitor for HYPOTEN, HA is common
Who should NOT get nitro (2)
Pts with R ventricular infarction
Use of other PDE-5 inhibitors - Viagra or Cialis
Morphine for MI tx (4)
Use if Nitro doesn’t control CP
1-2 mg IV Q 5-15 min
Reduces preload
AVOID in R Ventricular MI
Oxygen for MI (3)
Use ONLY if O2 falls BELOW 90%
Or if resp distress or hypoxemia (PaO2 less than 85)
Damages myocardium
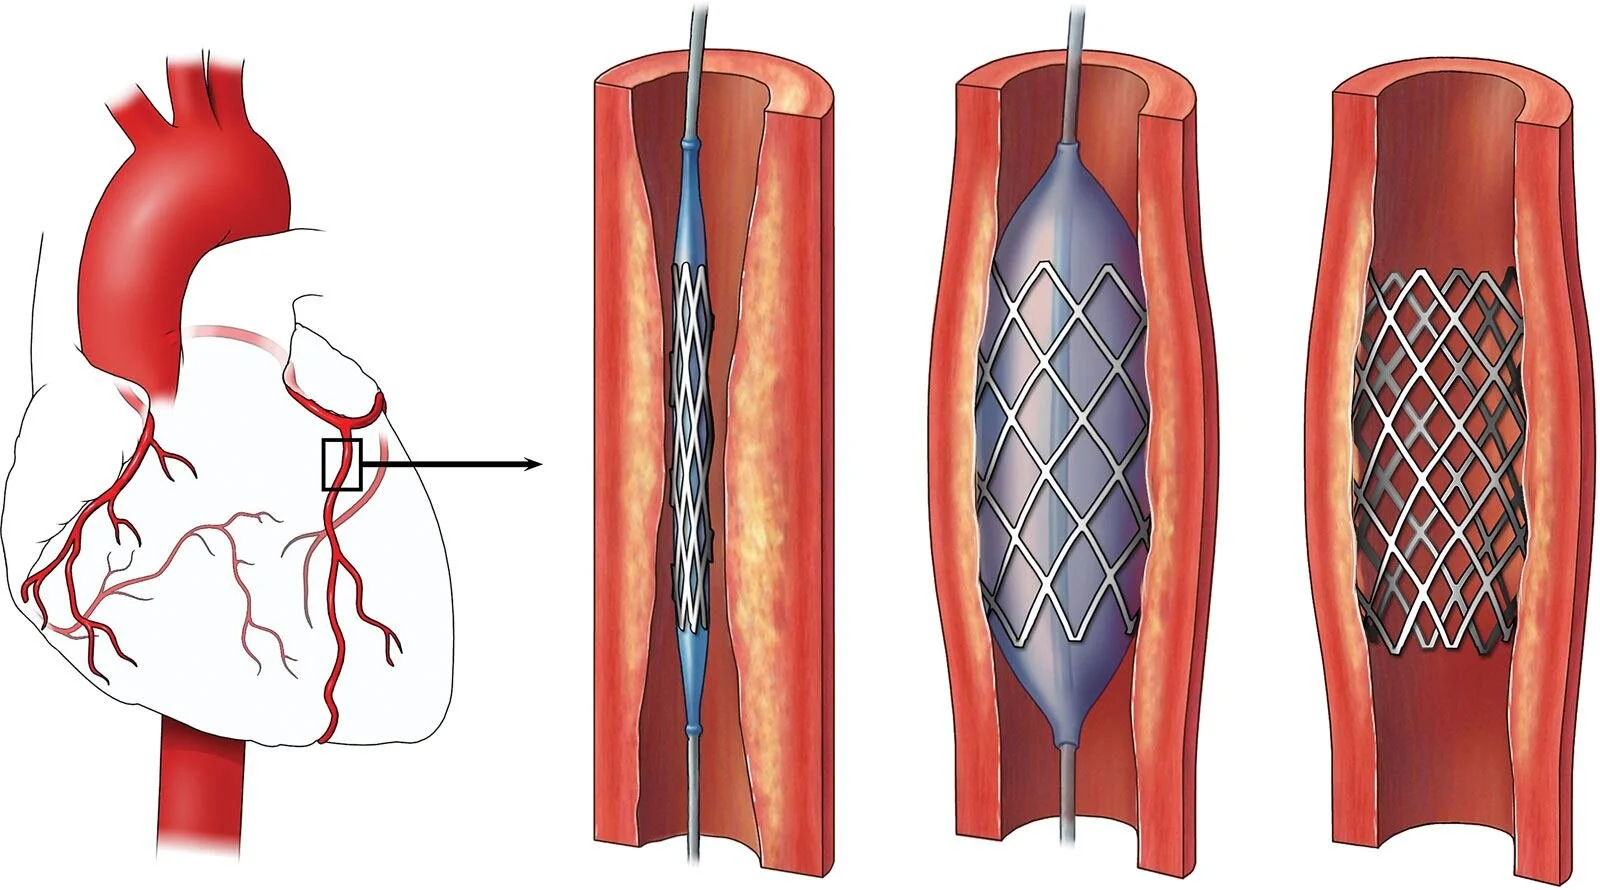
Acute STEMI PCI (3)
Door to balloon time goal: 90 mins
Goes through the radial artery
Monitor kidneys bc hella dye used
Clears through kidneys
Monitor creatine, urinary output, kidney function
What is Retroperitoneal Bleed & Hematoma? (2)
Seen with the femoral approach
Pt bleeds into retroperitoneal (internal bleeding)
S/S of Retroperitoneal Bleed & Hematoma (3)
Tachycardia
**Hypoten**
Back pain, groin pain, flank ecchymosis (late sign)
Retroperitoneal Bleed & Hematoma Tx (4)
STAT H/H
Hold pressure
Balloon tamponade (internal tourniquet)
Prepare for blood transfusion
When would we use fibrinolytic therapy? (3)
If pt can’t get to a chest pain hosp fast - rural areas
Temp care to buy time
RISKYYY
Fibrinolytic drugs & indications (3)
TNKase & rtPA (Activase)
Pain < 6 hrs
ST elevation > 1mm in 2 + leads (active STEMI)
Nursing considerations w fibrinolytics (4)
Bleeding in most common side effect ESP BRAIN BLEED!!!!
Reversal: cryoprecipitate & platelets
Frequent neuro assessments
Avoid punctures/invasive devices/compressive
Monitor renal function
The “Big 5” discharge meds following ACS (MI)
ASA - indef, 81 mg
Plavix at least 1 year
Beta blocker - indef
ACE-I or ARB ; EF <40%, cardioprotective
Statin
What are the dual antiplatelet therapy drugs?
ASA & Plavix
Use for at least 1 year