DENT 267: LO3 LS3 & LS4- Plan Perio Care of Viral Infections of the Gingiva, and Gingival Manifestation of Inflammatory & Immune Conditions and Lesions
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/44

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
45 Terms
viral origin
-Coxsackie virus (hand foot and mouth disease)
-herpes simplex
-varicella-zoster (chicken pox, shingles)
-Molluscum contagiosum virus
-Human papilloma-HPV (squamous cell papilloma condyloma acuminatum, verruca vulgaris, and focal epithelia hyperplasia)
herpes virus
-herpes simplex virus (HSV) type 1 and 2
-Varicella Zoster (chicken pox)
primary herpetic gingivostomatitis
-acute herpetic gingivostomatitis
-herpes simplex virus type I
-small percentage (1%) of individuals on first contact w/ the HSV 1 develop severe signs and symptoms of a primary infection
-contagious
-virus binds to nerve terminals within epithelial tissues of the mouth & skin
-in most ppl, primary infection is asymptomatic, 10-20% may show some signs of initial infection and may go unnoticed)
primary herpetic gingivostomatitis: most contagious when
-vesicular stage
primary herpetic gingivostomatitis: spread how
-by kissing and contact w/ open sores or by contact w/ infected saliva, contaminated surfaces
-from saliva to fingers (herpetic whitlow) to eye
clinical characteristics of primary herpetic gingivostomatitis
-prodrome: tingling, itching, pain at site prior to blisters developing
-acute
-last 7-10 days
-vesicles that rupture to form ulcers (intraoral, skin, lips)
-bleeding
-fever
-malaise
-lymphadenopathy
-headache/irritability
-painful
HSV-1 and HSV-2 stages
1. prodromal stage: early stage with redness, swelling and a burning or tingling sensation at the sight of infection
2. Blister stage: outbreak of tiny blisters filled w/ clear to whitish-yellow fluid
3. eruptive stage: blisters break open and leak fluid, leaving painful open sores that crust over
4. healing stage: crusted sores start to scab and heal
HSV-1
-more commonly associated w/ oral herpes (cold sores)
HSV-2
-more commonly linked to genital herpes

mild reaction to initial HSV infection
-a single herpes vesicle
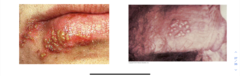
moderate reaction to initial HSV infection
-multiple widespread lesions
severe reaction to initial HSV infection
-severe widespread lesions
histopathology of AHGS (acute herpetic gingivostomatitis)
-vesicles located within the epithelium
-ballooning degeneration
-ulcers
-diagnosis usually based on hx and clinical findings
-virus can become latent in the body and can be reactivated later
etiology of AHGS (acute herpetic gingivostomatitis)
-by mid age, about 70% have been infected w/ HSV-1 without any symptoms during primary infection
-small percentage (1%) of the population will develop the acute signs
-virus ascends through the sensory & autonomic nerves
-most causes of AHGS are caused by HSV 1 but may also result from initial infection by HSV 2
prognosis of acute herpetic gingivostomatitis
-persists as latent HSV in neuronal ganglia that innervate the site
-once infected, most ppl develop immunity
-in some, virus is latent and will hide in trigeminal nerve ganglion and recur as recurrent herpes simplex (only 15%-40% of seropositive patients/clients experience recurrent mucuocutaneous lesions)
-sunlight, trauma, fever, stress may trigger recurrence
-contagious (in vesicular stage)
acute herpetic gingivostomatitis: nutritional implications
-fluid intake to avoid dehydration, nutritional drinks (Boost, Ensure) Gatorade, Pedialyte
-well-balanced diet low in retentive sugars, process foods in blender
-7-10 days resolution
care planning for acute herpetic gingivostomatitis
-diagnosis by clinical symptoms & history
-systemic antiviral meds such was acyclovir
-analgesics and antipyretics (to prevent/reduce fever), fluids, close observation, biofilm control
-rinse/coating agent (Benadryl/Maalox suspension) by prescripton
-topical anesthetic (mouthrinse) w/ caution on children
-usually runs its course in 10-20 days
-dentist/physician may prescribe antivirals if very recurrent
-postpone dental treatment
if someone with acute herpetic gingivostomatitis has a fever of higher than 38.3 degrees celsius, what should be done
-patient is septic w/ oral bacteria that have entered the bloodstream through the open sores on the gingiva or mucosa
-systemic antibiotics to control secondary bacterial infection (Penicillin V or Clindamycin)
recurrent herpes
-no elective dental treatment when client has herpes lesions
-lesions could progress if tissue is manipulated
-virus can spread to clothing through aerosols & then be transmitted
herpetic whitlow
An infection caused by herpes simplex virus infection that involves the finger
varicella-zoster infections
-headache, pharyngitis, maculopapular eruptions, fever, vesicles, ulcers
-in the oral cavity, the vesicles that breakdown form ulcers
-neurotropic virus so can recur as Herpes Zoster causes shingles
-shingles more common in elderly and the immunocompromised
care plan for varicella-zoster infections
-postpone elective dental treatment
-palliative (manage pain, fever, skin lesions, Benadryl, antiviral drugs)
-effective biofilm control
types of hypersensitivity reactions
-contact allergy
-plasma cell gingivitis
-erythema multiforme
types of autoimmune diseases
-pemphigoid
-lichen planus
-lupus erthematosis
types of granulomatous inflammatory conditions
-Crohn's
-sarcoidosis
what is recognized as a clinical manifestation of certain autoimmune/immunopathologic
-desquamative gingitivis
oral features of mucocutaneous disorders
-oral mucosa can be affected by a variety of mucocutaneous diseases (skin and mucosal surfaces- eye, oral cavity, genital mucosal surfaces)
what is desquamative gingivitis
-erosive lesions associated with vesiculobullous diseases such as lichen planus, pemphigoid and pemphigus

oral lichen planus
-intense redness of the gingiva
-ulcerations
-interlacing white lines may be present
-raised white lesions may be present
-normally chronic condition with oral form
-6 types of clinical manifestations
oral lichen planus: what are the 6 types of clinical manifestations (lesions)
-papular
-reticular
-plaque type
-erythematous
-ulcerative
-bulbous

clinical characteristics of MILD and MOD desquamative gingivitis
-mild forms
-mod
-burning sensation irritated by thermal changes, air, spicy foods, and carbonated drinks
-local irritants exaggerate response

clinical characteristics of SEVERE desquamative gingivitis
-lesions may also involve alveolar, buccal and palatal mucosa
-extreme pain that can be aggravated by spicy foods, air, temp, carbonated frinks
etiology of desquamative gingivitis
-related to systemic immunologic (Autoimmune) abnormalities that often show skin lesions as listed in the AAP classification (systemic mucocutaneous conditons)
-allergic reactions, food allergy related, drug induced, potentially vit deficiency, potentially in menopausal women
histopathy/pathogenesis of desquamative gingivitis
-atrophy and thinning of the epithelium
-separation of epithelium from CT
-direct or indirect Immuno-fluorescence testing of tissue may show antibody/antigen involvement
nutritional implications/prognosis
-nutritional: may have problems eating due to soreness
-prognosis: periods of remission/exacerbation is typical for the mucocutaneous disorders
diagnosis of desquamative gingivitis related to a mucocutaneous disorder
-client history
-clinical signs & symptoms
-biopsy of the affected tissue
-biopsy may reveal the antibody/antigen complexes involved
-bloodwork may be involved to detect autoantibodies (such as w/ lupus)
if diagnosis supports the findings of a mucocutaneous disorder, what should be done
-referral to dentist/periodontist/oral surgeon for biopsy
-referral to dermatologist
care plan gingival manifestations of mucocutaneous reactions
-client education: discuss nature of disease and important of biofilm control in eliminating biofilm as a source of irritation
-debridement
-well-balanced diet
-topical corticosteroids may be prescribed by the dentist of physician
-use a splint if needed
-systemic treatment may include systemic corticosteroids
-eval
-frequent CC intervals
-warm water rinses
-avoid spicy, carbonated drinks, and alcohol
-avoid stressful situations
client case: 23 year old female has a history of recurent desquamative gingivitis over last several years in localized areas. A biopsy was done previously with no specific diagnosis made. What should we do?
-refer client to a periodontist for assessment
allergic reactions
-result from contact sens to certain mouthwashes, toothpastes, dental restorative materials (acrylic, nickel)
-carvone- terpenoid found in essential oils of caraway seeds, dill, spearmint
-more common in ppl who have multiple allergies
-flavouring agents/additives in "tartar-control" toothpastes
signs of allergic reaction
-fiery red, edematous with ulcerations
-bleeding
-sloughing
-cheilitis
erythema multiforme
-uncommon acute inflammatory disorder
-causes large, symmetrical erythematous papules resembling target in circular pattern
-unknown cause
plasma cell gingivitis
-rare
-characterized by a massive infiltration of plasma cells into the sub-epithelial gingival tissue
-clinically presents as a diffuse enlargement with edematous swelling of the gingiva in the max and mand anterior segments
-exact mechanism behind this is unknown
-presence of plasma cells suggests an allergic origin
-diagnosis is by biopsy
non-biofilm induced traumatic lesions: physical/mechanical insults
-frictional keratosis
-toothbrushing-induced gingival ulceration
-factitious injury (self harm)
-can be self-inflicted, accidental, or iatrogenic
-commonly appears as abrasions, ulcerations, burns
chemical insults
-etching
-chlorhexidine
-ASA
-hydrogen peroxide
-dentifrice detergents
-paraformaldehyde or calcium hydroxide