Endo/Repro Week 1
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/458

There's no tags or description
Looks like no tags are added yet.
459 Terms
Abdominal obesity waist circumfrence in women? Men?
Women: >35 inch
Men>40 inch

Why is waist circumference useful?
Correlates with insulin resistance, dyslipidemia, and CVD»metabolic disease

What are the metabolic syndrome criteria?
Abdominal obesity, hyperglycemia, HTN, dyslipidemia

What labs should routinely be checked in obesity evaluation?
A1c, glucose, lipids, CMP, CBC, TSH

What is the key metabolic consequence of abdominal obesity?
Insulin resistance


Why must SGLT2 inhibitors be used cautiously with ketogenic diets?
Risk of euglycemic DKA

Why does increased muscle mass improve glycemic control?
Muscle is the largest glycogen storage depot

What is the primary action of insulin? Action in the liver? Muscle? Fat? Cell Membrane?
Stimulates cellular uptake of glucose. Liver: stores glucose as glycogen. In muscles: inc glycogen and protein synthesis. In Fat: inc triglyceride storage. Cell membrane: inc shifting of K into cell

What are the 2 physiologic components of insulin replacement?
Basal and bolus insulin(meal time)

Which insulin types are used for mealtime Bolus coverage?
Rapid-acting and short-acting(regular) insulin: Lispro, Glulisine, Aspart,

Which insulin types are used for basal coverage?
Intermediate/Long acting: NPH, glargine, detemir, degludec

What are examples of rapid-acting insulin?
Lispro, aspart, glulisine

What is the classic short-acting insulin?
Regular insulin

What is the classic intermediate-acting insulin?
NPH

What are examples of long-acting insulin?
Glargine, detemir, degludec(very long acting)

What type of insulin is added for elevated postprandial glucose?
Rapid-acting insulin/short acting
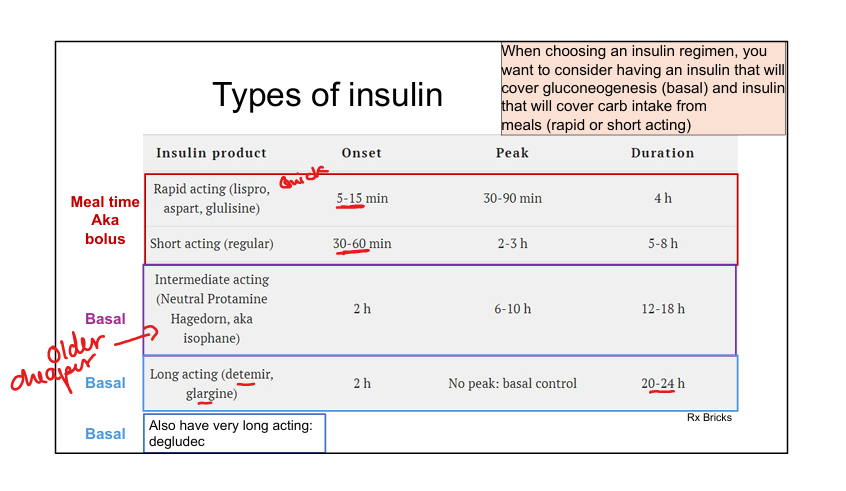
What insulin is commonly given before meals?
Lispro, glulisine, or aspart

What is the most dangerous adverse effect of insulin?
Hypoglycemia.

Adverse effects of insulin
Hypoglycemia (can lead to coma or death), Weight gain(due to inc glucose uptake in muscle+adipose), Lipohypertrophy(repeated insulin injections can form lumps of scar tissue)

How is lipohypertrophy prevented?
Rotate injection sites

What medication should always be prescribed with insulin? Why?
Glucagon. Just in case of hypoglycemia

How does glucagon raise blood glucose?
Stimulates glycogenolysis and gluconeogenesis

What is the first-line medication for T2DM?
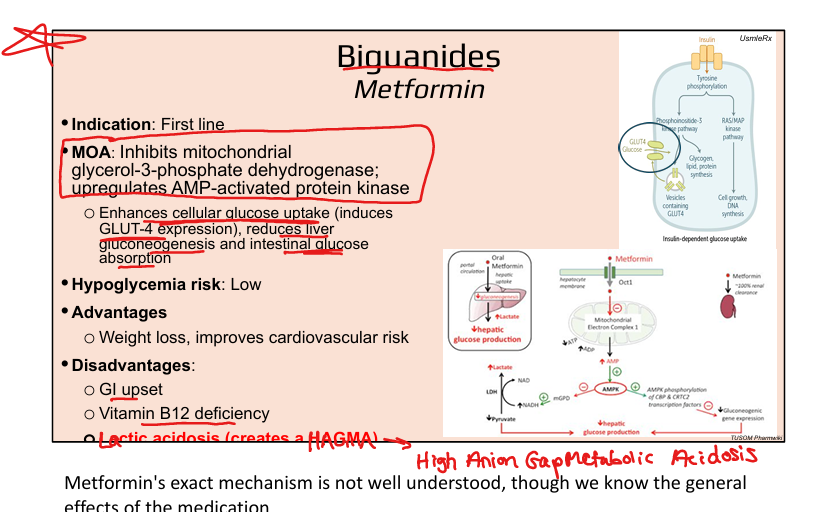
Metformin
What is the MOA of metformin?
Inhibits mitochondrial glycerol-3-phosphate dehydrogenase + upregulates AMP-activated protein kinase→Decreases hepatic gluconeogenesis and increases glucose uptake

What is the risk of hypoglycemia with metformin?
Low
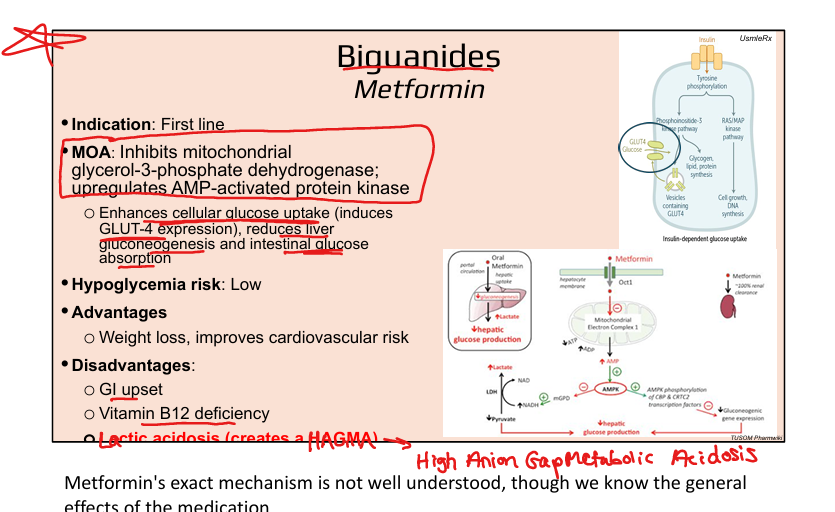
What are major adverse effects of metformin?
GI upset, B12 deficiency, anion gap metabolic acidosis

What metabolic effect is associated with metformin?
Weight loss

What is the MOA of thiazolidinediones? Ex?
Pioglitazone: Increases insulin sensitivity by activating PPAR-gamma nuclear receptors to increase glucose uptake
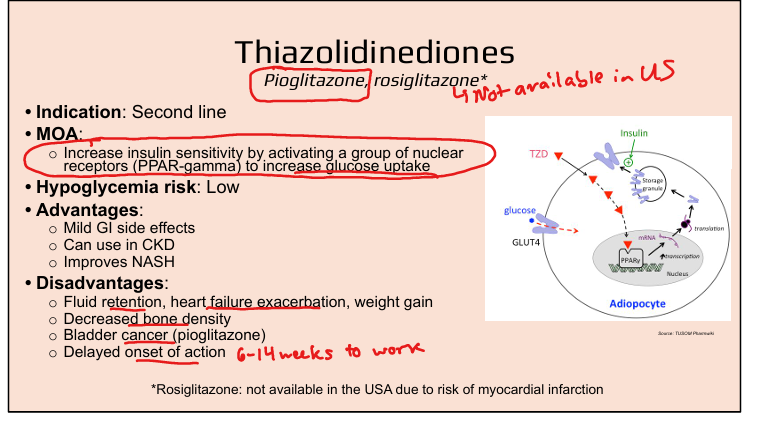
What are major adverse effects of Pioglitazone (Thiazolidinediones)?
Weight gain, edema, HF exacerbation, bladder cancer, delayed onset, decreased bone density
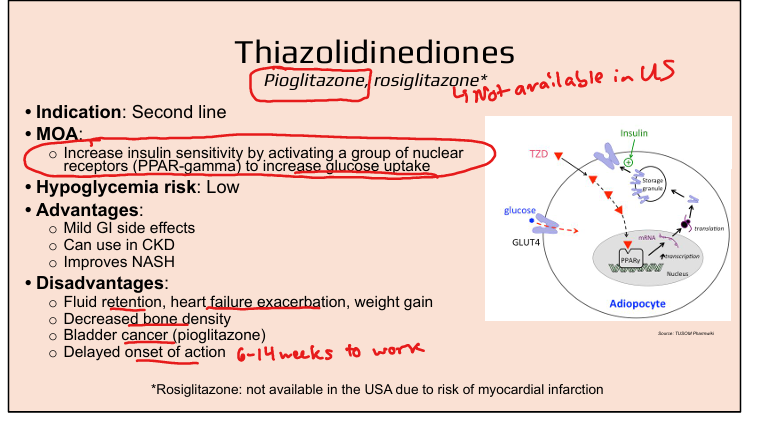
What is the MOA of GLP-1 agonists?
Increase insulin, decrease glucagon, slow gastric emptying

What are examples of GLP-1 agonists?
Semaglutide, tirzepatide, liraglutide, dulaglutide, orforglipron (the tides)

What endocrine cancer is a contraindication to GLP-1 agonists?
Medullary thyroid carcinoma/MEN2

DPP-4 inhibitors MOA + Ex
Inhibit DPP-4 to prevent degradation of GLP-1. Ex: Sitagliptin, saxagliptin, linagliptin (gliptins)

What is the major weight effect of DPP-4 inhibitors?
Weight neutral

What adverse effects are associated with DPP-4 inhibitors?
Pancreatitis and CHF exacerbation

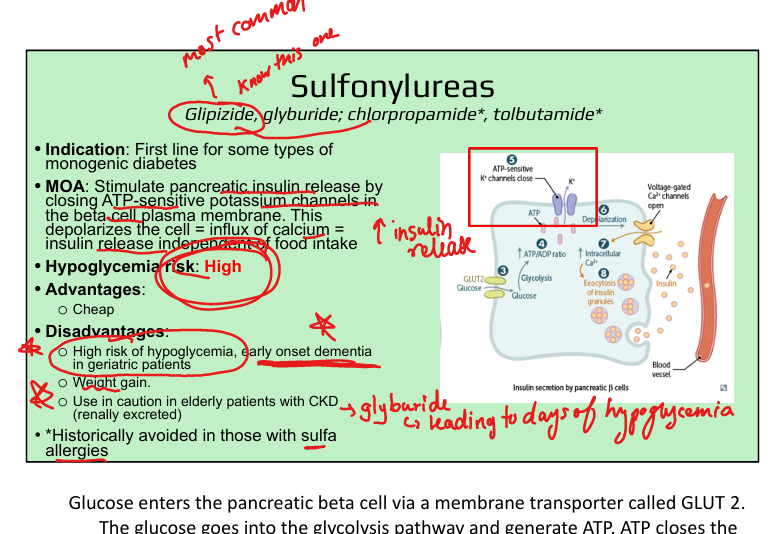
What is the MOA of sulfonylureas? Exs?
Closes ATP-sensitive K+ channels in β-cells which increases insulin release independent of food intake. Ex: Glipizide, glyburide
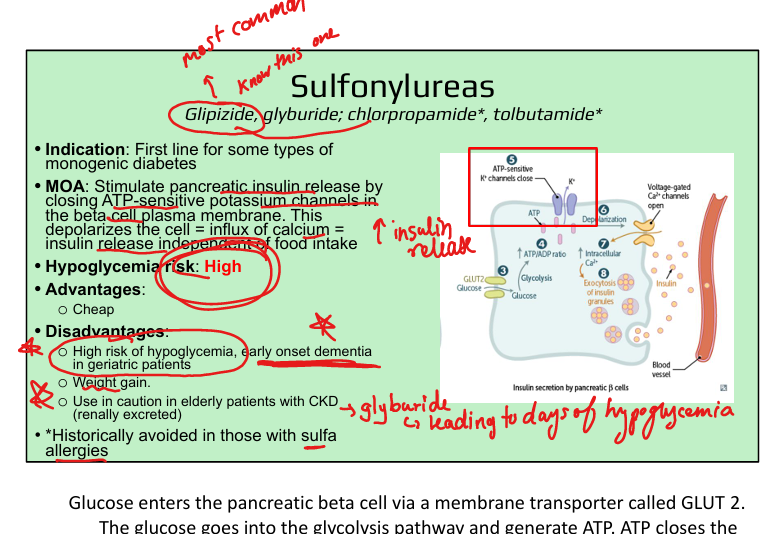
What are examples of sulfonylureas?
Glipizide, glyburide

Which oral diabetes drugs have the highest hypoglycemia risk?
Sulfonylureas

What major side effects are associated with sulfonylureas?
Hypoglycemia, Weight gain, Dementia risk in elderly, allergic rxn
What are examples of SGLT2 inhibitors?
Empagliflozin, dapagliflozin, canagliflozin
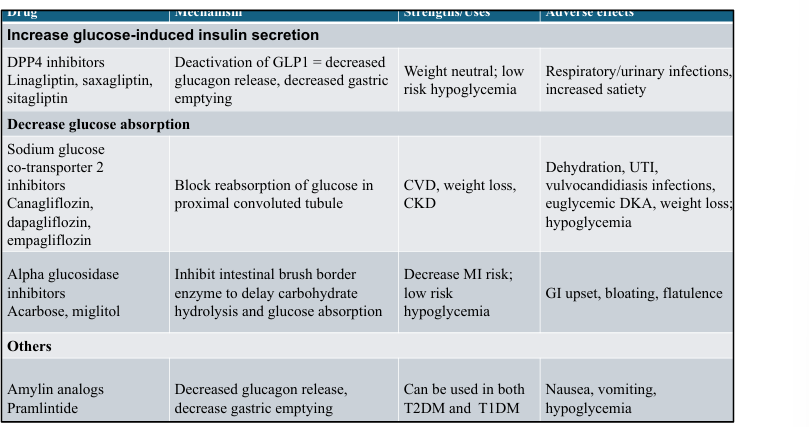
What is the MOA of alpha-glucosidase inhibitors (Acarbose)?
Delay carbohydrate absorption in gut

What is the prototype amylin analog? MOA
Pramlintide→reduces glucagon secretion, slows gastric emptying, inc satiety

What causes DKA? Why is it an emergency?
Absolute or relative insulin deficiency→not enough insulin to suppress fatty acids from being released from fat to be lipolyzed→liver can’t handle all the fatty acids for energy so excess becomes ketones→inc Beta Hydroxybuterate > acetoacetate→ High Anion Gap Metabolic Acidosis causing coma, arrythmias, shock, cardiac arrest


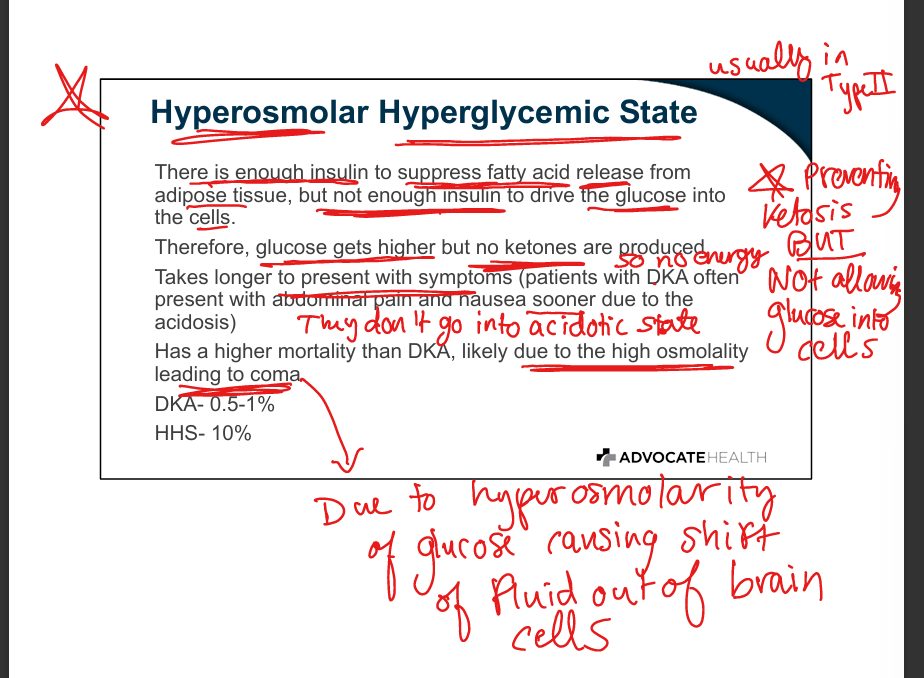
What causes Hyperosmolar Hyperglycemic State (HHS)? Why is it an emergency?
Relative insulin deficiency with enough insulin to prevent ketogenesis, but not enough insulin to drive glucose into cells→glucose gets higher but no ketones(less symptoms because no metabolic acidosis)→High osmolarity of glucose causes shift of fluid out of brain cells→coma, seizures, AMS


Which diabetes type is classically associated with DKA?
Type 1 diabetes

Which diabetes type is classically associated with HHS?
Type 2 diabetes
What is the major metabolic abnormality in DKA?
Ketone production causing anion gap metabolic acidosis

What ketone predominates in DKA?
β-hydroxybutyrate

What causes ketosis in DKA?
Uncontrolled lipolysis from insulin deficiency

Why does HHS not produce significant ketones?
Enough insulin remains to suppress lipolysis and ketogenesis

Compare DKA vs HHS? (Plasma glucose, pH, ketones, osmolarity, mortality)
HHS: higher plasma glucose, no acidosis, no ketones, hyperosmolar, higher mortality
DKA: anion gap metabolic acidosis from ketosis (Beta hydrobutyrate)

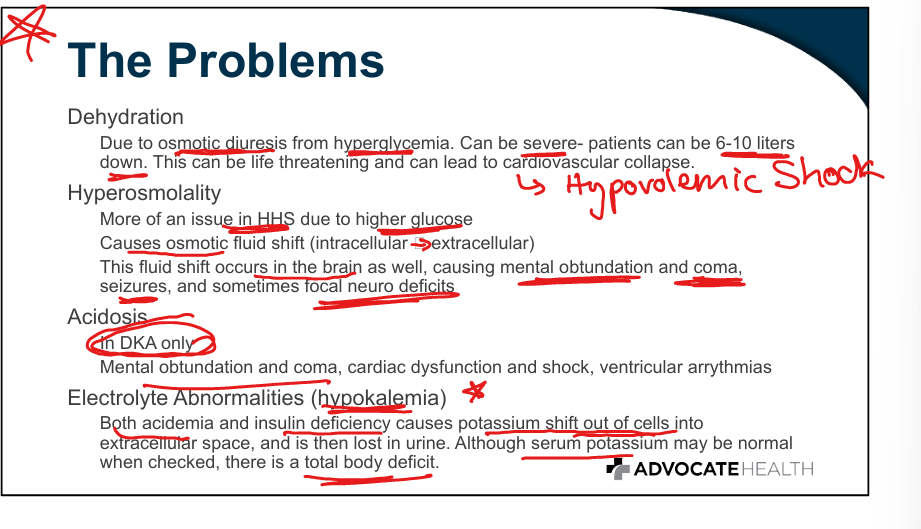
What causes dehydration in DKA and HHS?
Osmotic diuresis from hyperglycemia→can lead to hypovolemic shock
Presenting sx of DKA?
Kussmaul respirations(to compensate for metabolic acidosis), Polyuria/Polydypsia/Polyphagia, Abdominal pain, N/V(due to acidemia), Fruity breath (due to acetone from ketone acetoacetate)
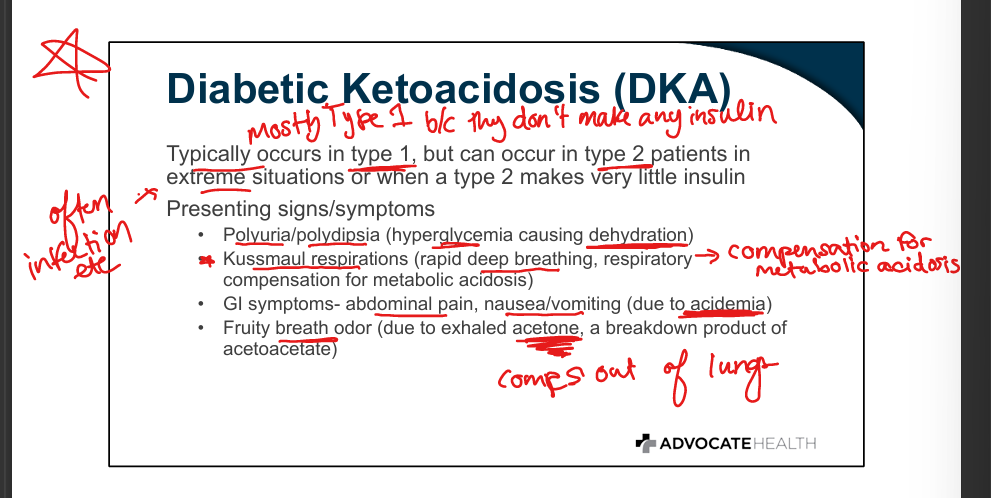
Why do Kussmaul respirations occur?
Compensation for metabolic acidosis
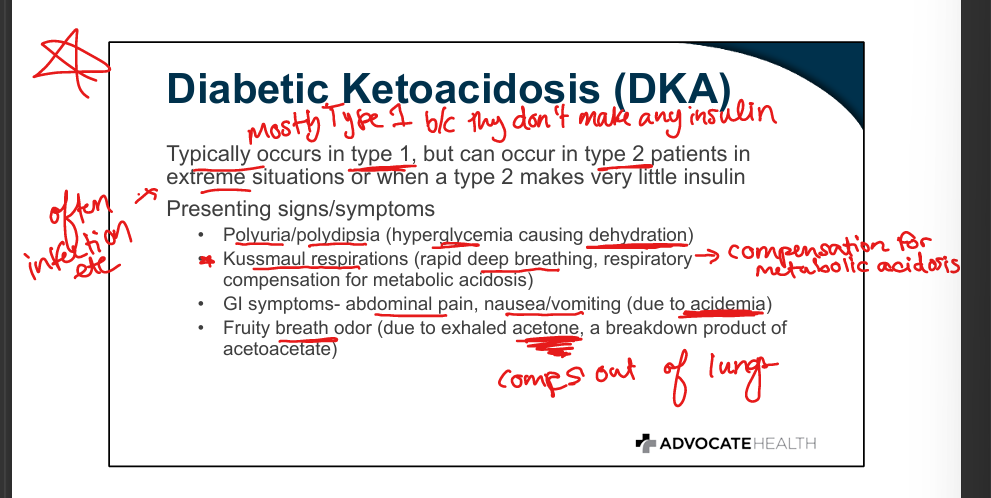
What causes fruity breath in DKA?
Exhaled acetone

Why are neurologic symptoms more severe in HHS?
Severe hyperosmolality causes fluid shift in brain

What electrolyte abnormality is a major concern in DKA/HHS treatment?
Hypokalemia—Need to correct first before adminstering insulin

Why can serum potassium appear normal despite total body potassium depletion?
Potassium shifts out of cells before urinary losses

What is the correct order of DKA and HHS treatment? ***
Fluids → Potassium → Insulin


Why must potassium be corrected before insulin if low?
Insulin drives potassium into cells causing severe hypokalemia

What medication ultimately corrects hyperglycemia and ketosis in DKA/HHS?
Insulin

Why must glucose be lowered gradually in DKA/HHS?
To prevent cerebral edema (too fast could shift fluid into brain cells)

What commonly precipitates DKA or HHS?
Infection or physiologic stress

What normally happens as glucose approaches 70 mg/dL? <70?, Continues to fall?
Insulin secretion from beta cells stops→<70 glucagon gets secreted by alpha cells→if blood sugar continues to drop epinephrine and cortisol are secreted to increase blood sugar

What are the adrenergic symptoms of hypoglycemia (happen first)?
Tremor, diaphoresis, anxiety, hunger

What are the neuroglycopenic symptoms of hypoglycemia (happen second)?
Confusion, seizures, altered mental status→cardiac arrest

What severe complications can occur from hypoglycemia?
CNS injury and cardiac arrest

What happens in Diabetes as glucose approaches 70 mg/dL? <70?
We give insulin→therefore no cease of secretion; only have epinephrine/cortisol to rely upon to increase blood sugar however»the more hypoglycemia you have the less adrenergic response you get (gets toleration) leading to hypoglycemia unawareness

What commonly causes hypoglycemia in diabetic patients?
Us giving Insulin or sulfonylureas

What is the Rule of 15 for hypoglycemia?
15 g glucose, recheck in 15 min
How is severe hypoglycemia treated outside the hospital? In hospital?
Glucagon. Give IV dextrose in hospital

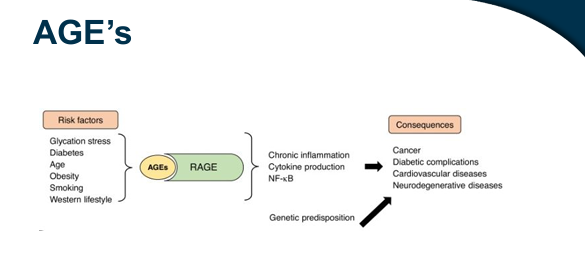
How do AGEs contribute to diabetic complications?
Cause endothelial vessel wall damage leading to macro/microvascular complications (CAD, CVD, PAD)

What are the major macrovascular complications of diabetes?
CAD, cerebrovascular disease, peripheral artery disease

What is the major mechanism of diabetic macro/microvascular disease?
AGE-mediated endothelial injury and atherosclerosis

What are the classic microvascular complications of diabetes?
Retinopathy, nephropathy, neuropathy

Diabetic retinopathy types and cause
Caused by endothelial vessel wall destruction→
Non Proliferative DR: Microaneurysms, macular edema, hard exudates
Proliferative DR: vessel damage→hypoxia→neovascularization but weak and fragile blood vessels


What causes proliferative diabetic retinopathy?
Retinal hypoxia leading to neovascularization


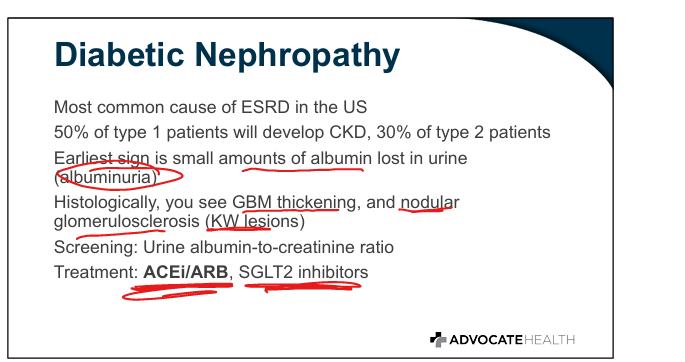
What is the earliest sign of diabetic nephropathy? Tx?
Albuminuria. Tx with ACEi/ARB, SGLT2i

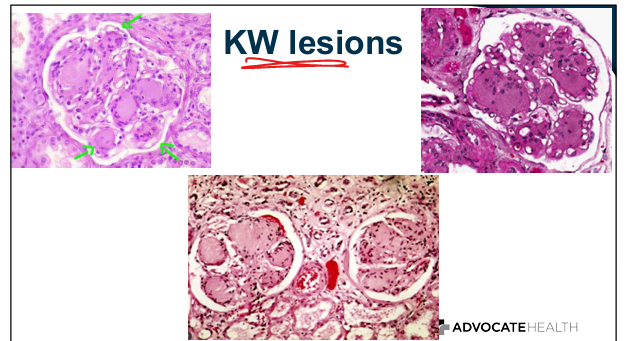
What histologic lesion is classic for diabetic nephropathy?
Kimmelstiel-Wilson nodules
What is the classic distribution of diabetic neuropathy? Tx?
Stocking-glove distribution of longest nerve fibers first (starts in feet), symmetric; Tx with Gabapentin, SNRIS

What diabetic complication commonly leads to foot ulcers and amputation?
Peripheral neuropathy


What is the mechanism of diabetic neuropathy?
Accumulation of Advanced Glycation End-products (AGEs) causing microvascular damage to nerves
What percentage of thyroid nodules are benign and nonfunctioning?
90-95%

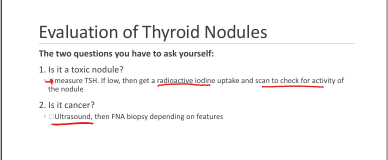
What are the 2 key questions when evaluating a thyroid nodule? Imaging/labs?
Is it toxic(does it alter TSH levels>then get radioactive iodine uptake)? Is it cancer(check ultrasound then maybe biopsy)?

What is the best imaging modality for thyroid nodules?
Ultrasound
When is Fine Needle Aspiration generally performed?
Nodule >1 cm with suspicious features

What is the most common thyroid cancer?
Papillary carcinoma

Papillary thyroid cancer: Cell origin, Path, tumor marker, Genetic Mut
Follicular epithelial cells, papillae formation + orphan Annie nuclei (nuclei with central clearing) + psammoma bodies calcification, Thyroglobulin, BRAF mutation


What nuclei are characteristic of papillary thyroid cancer?
Orphan Annie eye nuclei

What calcification is characteristic of papillary thyroid cancer?
Psammoma bodies

Follicular thyroid cancer: Cell origin, Path, tumor marker, Genetic Mut
Follicular epithelial cells; Path: Microfollicles, Thyroglobulin, RAS mutation

Medullary thyroid cancer: Cell origin, Path, tumor marker, Genetic Mut
Parafollicular (C) cells; Path: Amyloid, Calcitonin, RET mutation (associated with MEN2)


What is the most aggressive thyroid cancer?
Anaplastic carcinoma-Rapidly growing neck mass


What is the most important risk factor for differentiated thyroid cancer?
Prior neck radiation

What is the primary treatment for well-differentiated thyroid cancers?
Surgery ± radioactive iodine ±TSH suppression with levothyroxine

What is are common complications of thyroidectomy (3)?
Hypoparathyroidism due to damage to parathyroids, damage to recurrent laryngeal nerve(hoarseness, dysphagia), damage to external branch of superior laryngeal nerve(singing voice)

What nerve injury causes hoarseness and dysphagia after thyroidectomy?
Recurrent laryngeal nerve

What nerve injury affects the singing voice after thyroidectomy?
External branch of superior laryngeal nerve

What tumor marker is used to monitor recurrence of papillary and follicular thyroid cancer?
Thyroglobulin

Why should thyroglobulin be undetectable after total thyroidectomy? Rise suggests what?
Only thyroid tissue produces thyroglobulin. Rise suggests thyroid cancer recurrence
