chest image interpretation
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/27

There's no tags or description
Looks like no tags are added yet.
28 Terms
Postero-anterior Chest X-ray
Abnormal
Bilateral costophrenic blunting, synonymous with bilateral pleural effusions.
The patient has taken a good inspiration but there is volume loss in both lungs, although lung markings appear normal. Difficult to assess cardiothoracic ratio due to effusions. There appears to be splaying of the carina and this may relate to some cardiac (left ventricular failure) enlargement.
Female. 85 years. Previously well. Now attends her General Practitioner c/o increasing shortness of breath. Temperature normal.

Postero-anterior Chest X-ray
Abnormal
There is a large, irregular, mass obscuring the right cardiac border – leading to a widened mediastinum. The left cardiac border and both diaphragmatic contours can be seen.
There has been a good inspiratory effort, and visible lung markings are normal, as are the remaining bone and soft tissue appearances and there is no volume loss in the left lung. Obliteration of the rt cardiac border suggests an anterior mediastinal mass.
Male. 22 years. Loss of weight and generalised weakness

Posteroanterior chest X-ray
Abnormal
There is a widened mediastinum, both diaphragms appear raised although the lung markings are unremarkable. The mediastinal widening appears to be due to an unfolded aorta (age related) which has resulted in a prominent aortic arch.
Heart size is within normal limits. The costophrenic angles are normal, as is the mediastinum, hila, lungs, bones - all normal.
Female. 65 years. Acute left sided chest pain
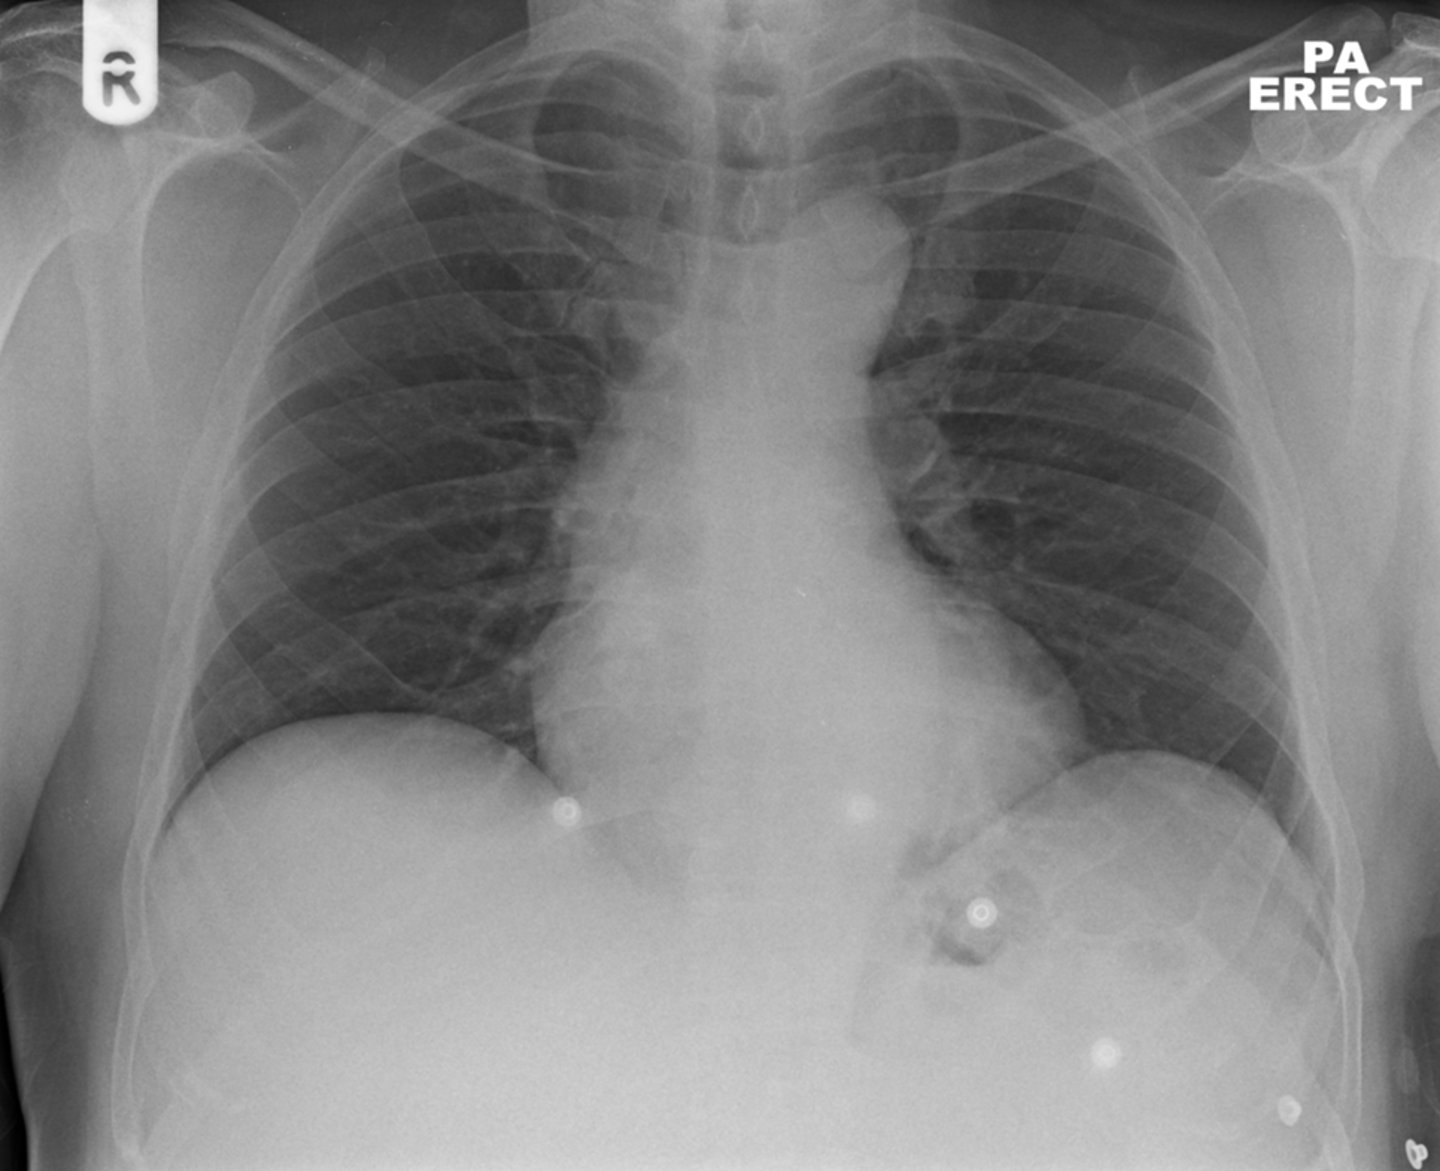
Postero-anterior chest X-ray.
Normal
Both lungs are of normal volume with unremarkable lung markings. No evidence of shadowing in either lung. And the trachea is central.
The Cardiothoracic ratio is within normal limits.
Both hila are symmetrical in appearances, and the diaphragmatic contours are normal, no soft tissue or bony abnormality seen.
Female. 64 Years. Non-smoker. Persistent cough for one month. Otherwise well.

Postero-anterior chest X-ray
Abnormal
Both lungs are on the upper limits of normal lung volume, and the lung markings are normal.
There is, however, asymmetry of the hilar regions, with bilateral hilar enlargement, and increased hilar density seen.
There also appears to be right paratracheal lymph node enlargement contributing to mediastinal widening.
The heart is not enlarged and there is no costophrenic blunting. No other soft tissue or bony abnormality seen.
Female, 30 years. Erythema nodosum and arthralgia. No other symptoms.

Posteroanterior CXR
Abnormal
Normal lung volume and lung markings. No cardiac enlargement.
However, there is a focal increase in density, behind the right cardiac outline.
This is probably a retro-cardiac mass.
There is also juxtaphrenic peaking of the right hemidiaphragm, otherwise the rest of the CXR is normal with no other soft tissue or bony abnormalities.
Male. 42 years. Persistent cough. Otherwise well

Postero anterior chest xray
Abnormal.
Good inspiratory effort, both lungs are of normal volume, and the lung markings are unremarkable.
There is a soft tissue shadow seen in the left middle zone, arising from the chest wall, and is visible in relation to the lateral aspect of the left 7th rib.
There may also be some associated rib destruction.
Otherwise, heart size is normal, and no other soft tissue or bony abnormality seen
Male. 32 years. Complains of severe left sided chest pain.

Posteroanterior chest X-ray
Abnormal
There are sternotomy wires present from a previous median-sternotomy / Coronary Artery Bypass Graft.
There are also some old TB scars at the apex of the right lung.
Otherwise, a good inspiratory effort with normal lung markings evident.
Heart size is within normal limits, but there is moderate superior mediastinal widening present with co-existing tracheal narrowing. This may be suggestive of a mass exerting extrinsic pressure on the trachea.
Male 60 years. Recent onset of shortness of breath and wheezing.

Posteroanterior chest xray
Abnormal
Good inspiratory effort with no volume loss.
However, there is a conspicuous, well-defined shadow in the right middle zone.
There are also diffuse small calcifications apparent within both lungs – but mainly in the left lung, and normal cardiac contours and size.
Both hila are symmetrical in size, shape and density and no effusions can be seen.
Also, note that an azygo-oesophageal line is seen over the anterior surfaces of the thoracic vertebrae. No other soft tissue or bony abnormality seen.
Female. 70 years. Persistent and troublesome cough

Posteroanterior Chest X-ray
Abnormal
There is a subtle area of increased density / shadowing evident in the right lung base located below the dome of the right hemidiaphragm.
Furthermore, the mediastinum appears widened, with increasing density seen behind the left cardiac shadow, this is probably due to aortic unfurling and is therefore unimportant. There is also a prominent azygo-oesophageal line, but this is of no consequence.
The lungs are well inflated, and normal markings are depicted; heart size is within normal limits.
Male. 75 years. Cough and a slight fever - over the last week

AP semi-erect chest.
Abnormal.
There is a large left-side pneumothorax with partial collapse of the lung and a lack of lung markings peripherally.
There is no evidence of midline shift or flattening of the left hemidiaphragm to suggest tensioning.
The right lung is normal.
The heart size cannot be accurately measured due to the projection.
The projection is lordotic.

AP Erect Mobile Chest.
Abnormal.
There is ill-defined increased density involving both lungs, this has the appearance of air-space shadowing. This is densest at the hila and in the mid zones.
There are air bronchograms present.
There is a small left-side pleural effusion.
Appearances are consistent with pulmonary oedema.
The heart size cannot be accurately measured due to the projection.

Postero-anterior chest X-ray
Abnormal
There is widening of the superior mediastinum and volume loss overall in the right lung.
There is increased density behind the medial end of the right clavicle extending to the right lung apex.
There is also ipsilateral blunting of the right costophrenic angle indicating a small, right sided pleural effusion.
The appearances are suspicious of malignancy.
Otherwise, the left hemithorax and lung markings are normal, and the cardiothoracic ratio is within normal limits.

Postero-anterior chest X-ray
Abnormal
Initial inspection suggests widening of the superior mediastinum, however, there is asymmetry of the hilar region, with the left hilum appearing larger, denser and more conspicuous than the right.
The left hilum also appears to be raised in comparison with the right. The left hilar density appears spiculated, and also appears to trach downwards, along the path of the left main bronchus.
Highly suggestive of a bronchial / hilar mass. The left hemidiaphragm is raised, but heart size is within normal limits.

Postero-anterior chest X-ray
Abnormal
A good inspiratory effort revealing normal lung markings. Heart size is normal, but there is an irregular left cardiac border, and the cardiac shadow appears denser on the left side.
There appears to be a large, well-defined, left sided, retro cardiac mass, situated above the left hemidiaphragm, disrupting the medial diaphragmatic silhouette, and urgent referral to the lung cancer MDT is recommended.

Postero-anterior chest X-ray
Abnormal
There is bilateral volume loss, and the lung markings appear more prominent. It is difficult to assess cardiothoracic ratio with poor ventilation.
However, there is a mid shaft fracture of the right clavicle and also what appears to be a healing rib fracture in the left, posterior 4th rib.
The left breast shadow is missing - it is likely that this patient has undergone a previous, left sided mastectomy for breast carcinoma, and in the absence of trauma, the fractures are probably related to metastatic disease.

Postero anterior chest xray
Abnormal
The lungs appear hyperinflated, with flattening of the diaphragms, although this is likely to be down to a large respiratory effort
The lung markings are normal, and the heart size is within normal limits.
However there is a well-defined solitary pulmonary nodule in the right lower zone.
It is difficult to assess the significance of this- does the patient have any previous history of lung disease?
Apices, airways, hilar regions and diaphragms appear normal, and no other soft tissue or bony abnormality seen

Postero-anterior chest X-ray
Abnormal
There is complete opacification of left hemithorax, and traction of the trachea and mediastinal structures to the left side.
The right lung shows signs of compensatory hyperinflation, with mild flattening of the hemidiaphragm and loss of the right cardiac imprint.
The appearances are consistent with atelectasis of the left lung, although there is no apparent cause of the collapse. An urgent MDT referral is recommended.

Postero-anterior chest X-ray
Abnormal
There is volume loss bilaterally , making it difficult to assess heart size.
There are multiple striating lucencies seen in and around the left hemithorax and the soft tissue planes, and these appear to be associated with posterior, left sided rib fractures (ribs 7 - 8).
The appearances are consistent with a traumatic pneumothorax and associated surgical emphysema.

Antero-posterior semi-erect chest X-ray
Abnormal
There is a mis-placed nasogastric tube evident in the right mid/lower zone. The tube initially appears in in the midline of the oesophagus, but fails to cross the carina, instead tracking down the right main bronchus.
The tip resides in the right lower zone instead of passing below the diaphragm and into the stomach.
It must be removed immediately! There is also bilateral, hazy airways shadowing seen.

Postero-anterior chest X-ray
Normal
There is opacification of the left hemithorax and compensatory hyperinflation of the right lung. Normal right lung markings can be seen. The trachea, heart and mediastinal structures appear to be pulled towards the left side.
There are iatrogenic artefacts within the left hemithorax, most likely to be surgical clips, indicating that this patient has undergone a previous, left sided, pneumonectomy.
Normal post-pneumonectomy chest X-ray.

Opacified rt hemithorax – small lucent area right upper zone, pocket of residual air (air bronchogram)
Trachea and mediastinum remain central
This is a case of right-sided consolidation, which is one of the stages of pneumonia.
A 6-year old female with a history of dyspnoea and cough for 1 week.
Query cause?
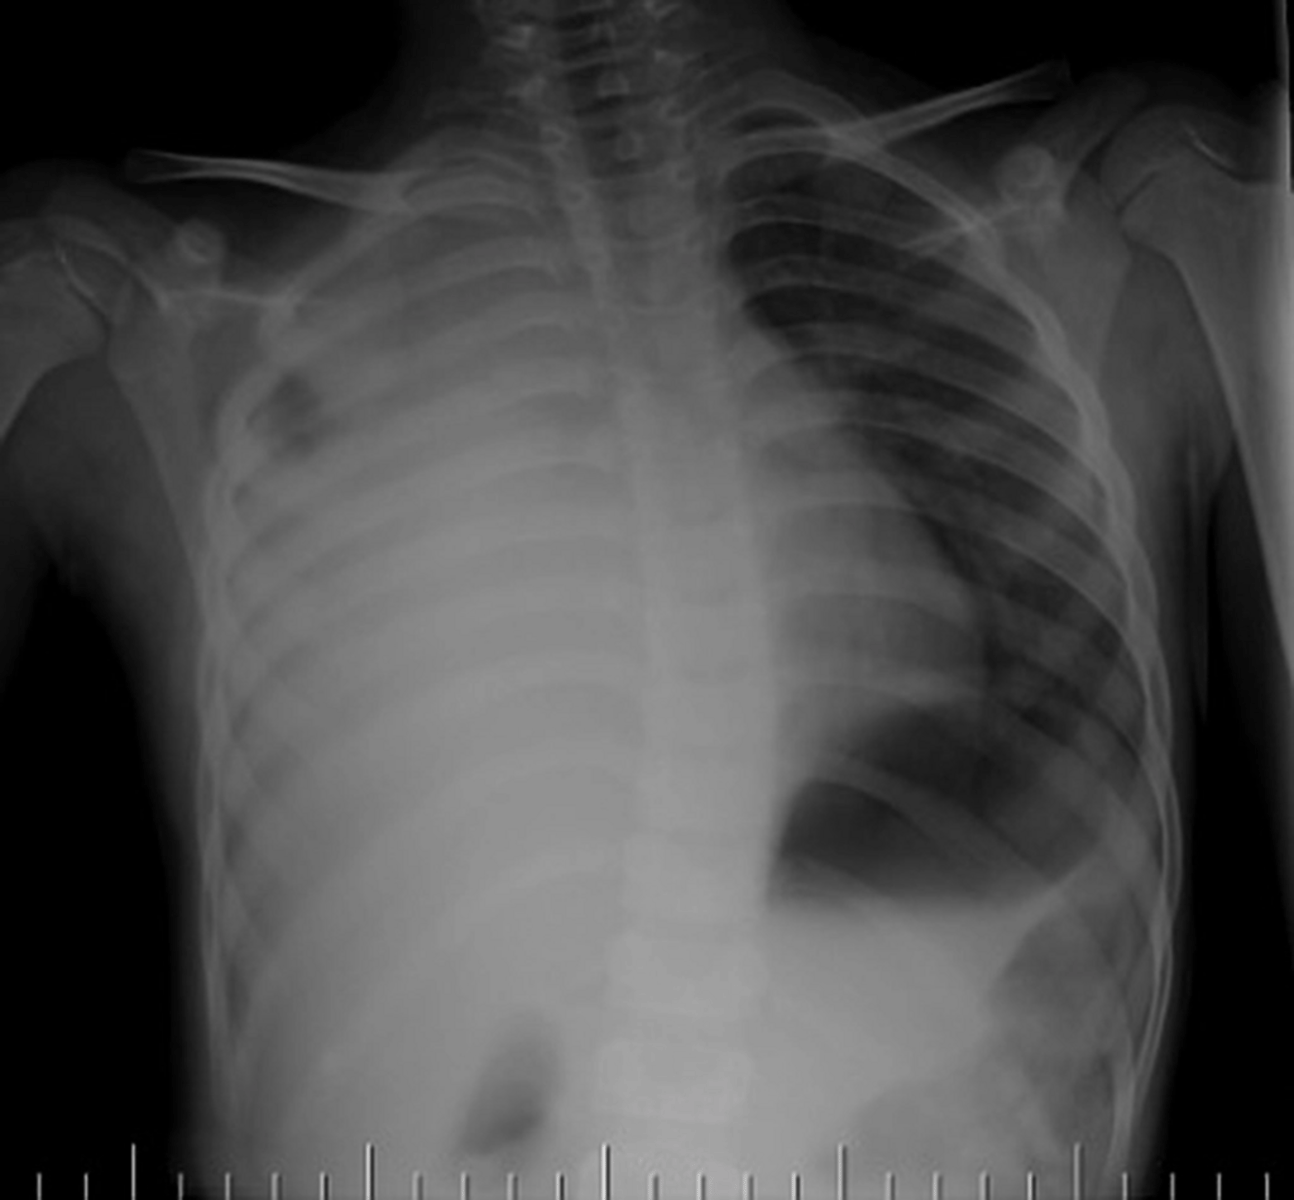
Homogenous opacification of the left hemithorax with an absence of lung markings
Trachea and mediastinal deviation towards the left hemithorax
Surgical clips around the left hilum
Compensatory hyperinflation of the right lung field related to left pneumonectomy.
A 60 year old male, complaining of shortness of breath.. His clinical history also stated that he had undergone previous thoracic surgery.

Diffuse, left sided opacification of the hemithorax, with an absence of lung markings.
Marked mediastinal and tracheal shift to the contralateral side.
The tracheal/mediastinal shift is the clue - huge effusion (relating to possible malignancy), which would be the working hypothesis until a CT examination was undertaken.
A 65-year-old male with severe shortness of breath. Recent weight loss.

Complete opacification of the left hemithorax with absence of lung markings.
Contralateral deviation of trachea and mediastinum, with compression (volume loss) of right lung.
The appearances are consistent with a massive pleural effusion, BUT such a large pleural effusion is atypical in a child.
Patient underwent CT and was discovered to have a large intrathoracic mass - subsequent histology showed this to be a Ewing's Sarcoma.
A 15-year-old female with a TWO month history of dry cough, shortness of breath and weight loss (but no history of fever).

Anteroposterior Chest X-ray
Abnormal
Total opacification of the right hemithorax and an absence of lung markings. There is traction of the trachea and mediastinal structures to the ipsilateral side, while the left lung is inflated and demonstrates normal lung markings. The appearances are consistent with a complete right sided atelectasis.
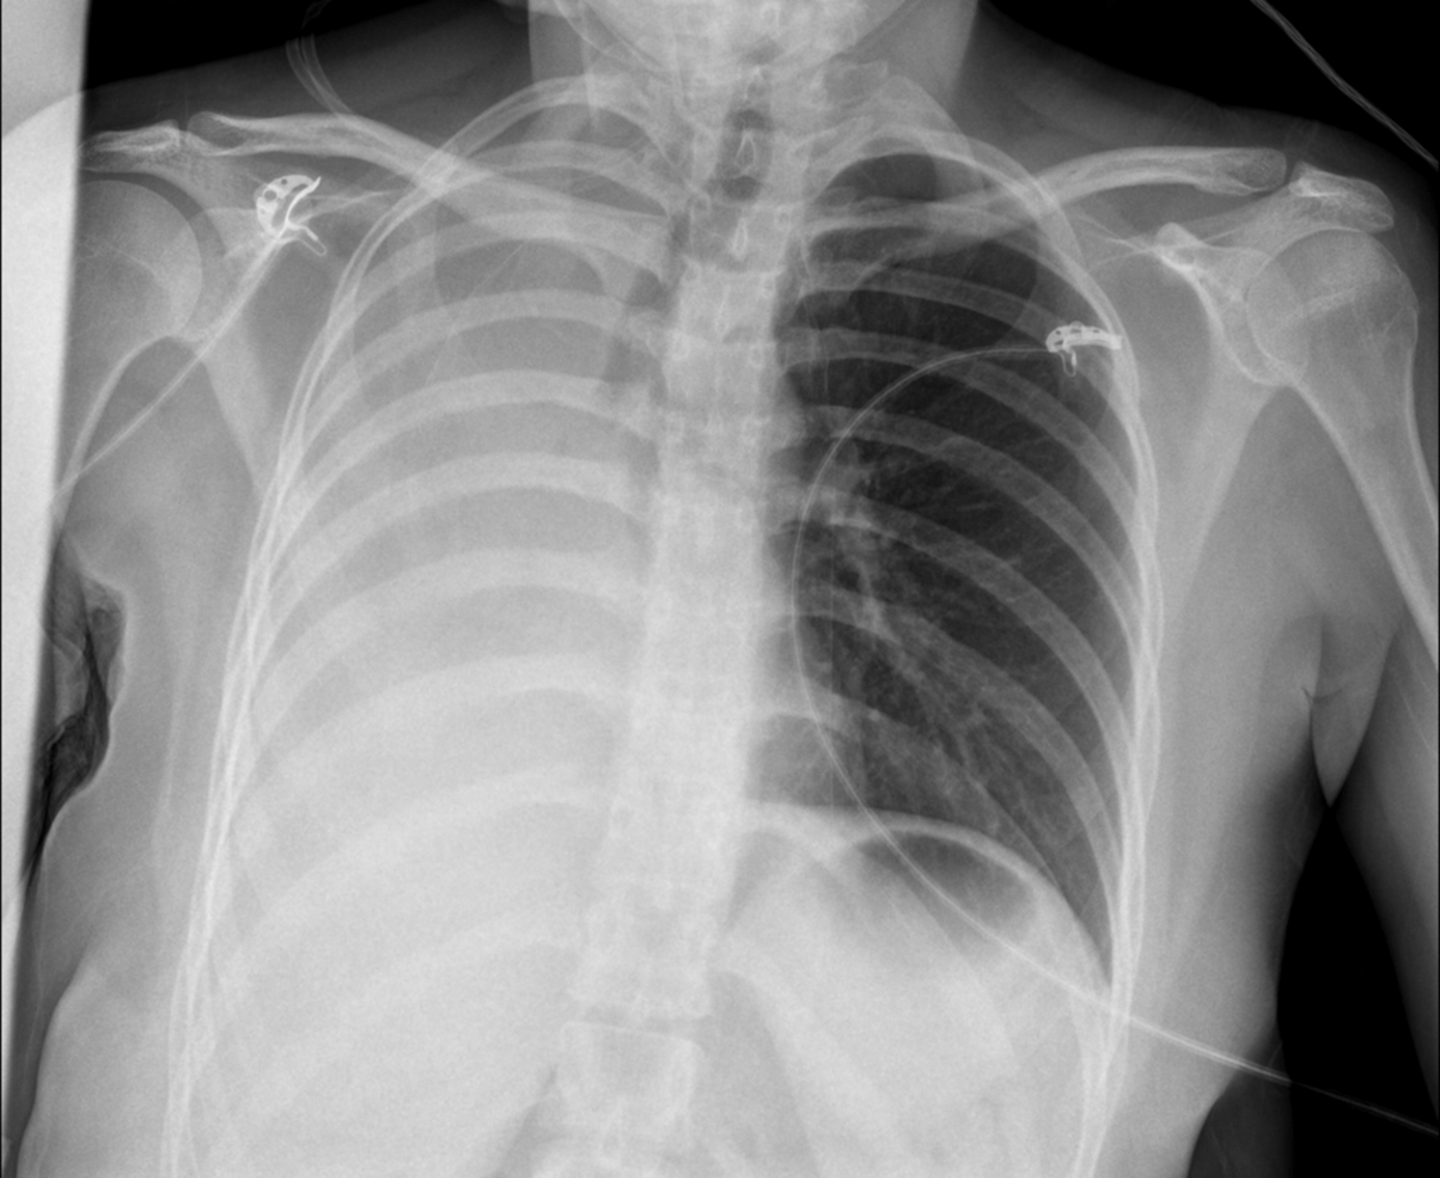
1.Passes vertically, down the oesophagus in the midline, or just to left of midline
2.Crosses the carina in the midline, it must NOT track down either main bronchus
3.Should continue tracking down vertically, in the midline, until it crosses the diaphragm
4.It should pass through the gastro-oesophageal sphincter, extending into the stomach by 10 cm
what is the checklist for NG Tube placement?
Still learning (27)
You've begun learning these terms. Keep up the good work!