HHS CPO Shock Syndromes and Vasoactive Medications
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/50

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
51 Terms
Shock
Acute, widespread process of impaired tissue perfusion, imbalance between oxygen supply and demand → cellular, metabolic, hemodynamic alteration
Stages of Shock
initial
compensatory
progressive
refractory
Initial Stage
Decreased cardiac output
Tissue perfusion threatened
VS can be normal
Compensatory Stage
Mediated by SNS
Neural → stimulate SA, AV, myocardium → Increased HR, contractility → increased CO
Hormonal → RAAS activation → vasoconstriction, vol retention, glucocorticoid release
Chemical → epi and norepi
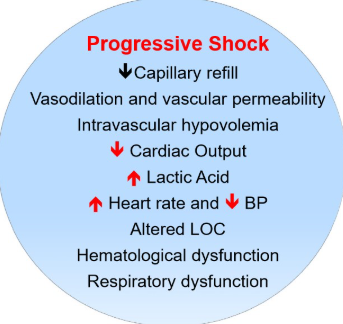
Progressive Stage
Compensation fails to meet tissue demands → ineffective perfusion
Switch to anaerobic metabolism → lactic acid
Vasodilation, increased tissue permeability
Refractory Stage
Irreversible, individual organs can die
MODS → 2+ organs dysfunctional
Categories of Shock
Hypovolemic
Cardiogenic
Obstructive
Distributive (Anaphylaxis, neurogenic, septic)
Signs of Shock
Cold, clammy skin
Hypotension
Oliguria
Rapid, shallow breaths
Drowsiness, confusion
Irritability
Tachycardia
Elevated/reduced CVP
Multi-organ damage
Bloodwork to Send
Serum lactate
Serum bicarbonate
ABG
Mixed venous
Absolute Hypovolemia
Loss of fluid from intravascular space
External loss of fluid or internal shifting of fluid from intravascular → extravascular
Relative Hypovolemia
Vasodilation resulting in inc vascular capacity relative to circulating volume
Hypovolemic Shock Treatment
Correct cause
Fluid, blood to restore volume
Meds to stabilize hemorrhage (TXA, vit K, Calcium Chloride)
Restore tissue perfusion
Prevent complications
Fluid Management
750 ml blood loss → Crystalloid
750-1500 ml blood loss → Crystalloid
1500-2000 ml blood loss → Crystalloid and blood
>2000 ml blood loss → Crystalloid and blood
Cardiogenic Shock
Impaired ability to contract and pump blood (primary pump failure)
Loss of 40% of ability to pump
Cardiogenic Shock Causes
MI
Dysrhythmias
Mitral or aortic stenosis
Cardiogenic Shock Characteristics
Hypotension (SBP<90)
Evidence of poor tissue perfusion
Cardiac → tachy, CP, dysrhythmias
Pulmonary → crackles, SOB, edema
Persistence of shock after correction of non myocardial factors
Cardiogenic Shock Management
ABC
Underlying cause
Administer meds (ino/vaso, diuretics, antiarrhythmics)
Intubation/mech vent
Emergency revascularization
Mechanical circulatory assist devices
Obstructive Shock
Obstruction of blood flow (external to heart) limiting blood from leaving or returning to heart
Obstructive Shock Presentation
Decreased tissue perfusion
Respiratory distress
Tachycardia
Hypotension
Obstructive Shock Management
TREAT THE CAUSE
Tension pneumo → needle decompression, chest tube
Pulmonary embolism → thrombolytic TNK, embolectomy
Cardiac tamponade → pericardiocentesis, thoracotomy
Distributive Shock
Systemic vasodilation resulting in decreased blood flow to vital organs
Anaphylaxis
Neurogenic
Sepsis/Septic shock
Anaphylaxis
Immediate hypersensitivity reaction → severe systemic response
Activation of mast cells, basophils
Anaphylaxis Characteristics
CNS → HA, restlessness, anxiety
CVS → dizziness, hypotension, angina, arrhythmia, tachycardia
Resp → cough, dyspnea, stridor, wheeze
GI → vomiting, diarrhea, abdo pain
Skin → flushing, itching, hives, angioedema
Anaphylaxis Medications
Rapid volume replacement
Epi 0.5mg IM
H1 antihistamine (benadryl) 50 mg IVP
H2 antihistamine (famotidine) 20 mg IVP
Bronchodilators (ventolin) 4-8 puffs
Glucocorticoids (hydrocortisone) 50 mg IVP
Neurogenic Shock
Loss/suppression of sympathetic tone → massive vasodilation, bradycardia, reduced contractility
Caused by anything disrupting SNS
Neurogenic Shock Manifestations
Hypotension → secondary to vasodilation of vascular beds below level of injury
BRADYcardia → suppression of cardiac accelerator reflex
Warm, dry skin
Neurogenic Shock Management
ABC
Symptom management
Promote optimal tissue perfusion
Prevent cardiac instability (fluids, vasopressors, atropine)
Sepsis
Life threatening clinical syndrome caused by an infection and dysrefulated physiological systematic reponse
Perfusion abnormalities → multi organ dysfunction
Septic Shock
Severe sepsis with extreme circulatory, cellular, metabolic effects
Mortality >40%
Septic Shock Manifestations
aLOC
Hypotension
Tachycardia
Tachypnea
Chills and fever
Warm flushed skin
Decreased urine output
Fatigue and weakness
Septic Shock Management
Lactate level
Cultures
Broad spectrum abx
Fluid resuscitation (30 ml/kg crystalloid for hypotension, lactate >4)
Vasopressors to maintain MAP >65
Alpha 1 Receptor Effects
Stimulation → vasoconstriction, smooth muscle contraction
Inhibition → vasodilation, smooth muscle relaxation
Beta 1 Receptor Effects
Stimulation → inc HR, contractility, kidneys release renin
Inhibition → (selective) dec HR, BP
Beta 2 Receptor Effects
Stimulation → smooth muscle relaxation, vasodilation, bronchodilation
Inhibition → (non-selective) dec HR, BP. bronchoconstriction
Medications Used in Shock
Vasoconstrictors
Vasodilators
Inotropes
Antiarrhythmatic
Vasoconstrictors
Epinephrine
Norepinephrine
Alpha-range dopamine
Phenylephrine
Vasopressin
Vasodilators
Nitroprusside
Nitroglycerine
Hydralazine
Labetalol
Inotropes
Beta-range dopamine
Dobutamine
Epinephrine
Norepinephrine
Milrinone
Antiarrhythmics
Amiodarone
Adenosine
Labetalol
Metoprolol
Diltiazem
Lidocaine
Epinephrine
Dose → start at 0.02 mcg/kg/min, maintain at 0.05-0.5 mcg/kg/min
Titration → based on MAP
Reconstitution → 4/8/16 in 250 ml NS or D5W
Norepinephrine (Levophed)
Dose → 0.01-3 mcg/kg/min
Titration → Yes
Reconstitution → Premade in D5W (8mg in 250 ml D5W/NS)
Phenylephrine (Neocynephrine)
Dose → Bolus 100-200 mcg, infusion 0.05-4mcg/kg/min
Titration → Yes (infusion)
Reconstitution → 10 mg/100 ml NS (bolus), 50 mg/250 ml NS (infusion)
Vasopressin
Dose → 2-2.4 unit/hr
Titration → No, set dose ordered
Reconstitution → Nurse makes first dose, 20 u/50 ml NS
Nitroglycerin
Dose → 10-200 mcg/min
Titration → Yes
Reconstitution → 50mg/250ml (200mcg/ml) in glass bottle
Nitroprusside (Nipride)
Dose → start at 0.5 mcg/kg/min (titrate by 0.2 mcg/kg/min q5min, max 8-10)
Titration → Yes
Reconstitution → by RNs, 50mg/250ml D5W (protected from light)
Dopamine
Dose → 0.05-20 mcg/kg/min
Titration → Yes
Reconstitution → Premade, 400mg/250ml D5W
Dobutamine
Dose → Initial 2.5 mcg/kg/min, up to 20 mcg/kg/min
Titration → No, set ordered dose
Reconstitution → Premade, 250mg/250ml or 500mg/250ml
Milrinone
Dose → 0.25-0.75 mcg/kg/min
Titration → No, set ordered dose
Reconstitution → Made by pharmacy, 1st made by nurse. 20mg/100ml NS
Amiodarone
Dose →
Bolus: 150mg/100ml D5W or NS
Infusion:
CVL → 900mg/250ml non PVC bag
PIV → 450mg/250ml non PVC bag
Metoprolol
IVP or bolus 5-15 mg
Labetalol
IVP 10-25 mg, or infusion 100mg/50ml, 200mg/100ml