Week 2: ABO Discrepancies
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/35

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
36 Terms
causes of ABO discrepancies
ABO subgroups
antibody titer diminished
technical error
protein abnormalities
bone marrow transplants
cold reacting antibodies
bacterial enzymes
1st step to resolve an ABO discrepancy
repeat the test on the same sample
technical errors may be resolved
examples of technical errors in ABO typing
adding wrong reagent
missing plasma
switching tubes
contaminated reagents
recording wrong result
heavy cell suspension
2nd step in resolving ABO discrepancies
test a 2nd sample if the current specimen doesn’t match the historical type
what errors do testing a second sample correct?
error in labeling tubes
drawing patinet
documentation
what type of reactions should be investigated in ABO discrepancies?
weak reactions
what discrepancy can these factors cause?
bone marrow or stem cell transplants
antisera with contaminating antibodies
rouleaux
cold reacting antibodies
acquired B phenotype
chimerism
extra reaction in forward type
acquired B phenotype
bacterial enzyme changes the A antigen sugar to resemble B
what should be checked if a patient is suspected to have the acquired B phenotype?
patient diagnosis for GI conditions
chimerism
person with 2 genetically different RBC populations
chimerism can occur in _______
twins
the following reaction denotes what?
anti-A = 0
anti-B = MF+
A1 cells = 4+
B cells = 0
chimerism
O type and B type are present
high _______ concentrations can cause rouleaux
protein
conditions that cause rouleaux
multiple myeloma
waldenstrom macroglobulinemia
liver disease
resolutions for extra reaction in forward type
check patient history
wash RBC suspensions
warm RBC or wash with warm saline
acquired B
how does washing RBC suspensions help resolve discrepancies?
removes excess plasma proteins to fix rouleaux
removes antibodies to reagent component
wash cord cells before testing
wharton’s jelly
mucous-like connective tissue surrounding the blood vessels in a newborn's umbilical cord
how does warming or washing with warm saline resolve discrepancies?
eliminates cold antibodies and thus spontaneous agglutination
the bacterial enzyme that causes acquired B strips an _______ group from the A antigen, turning it into ___________
acetyl, galactosamine
how is an acquired B type confirmed with testing?
prove using auto control that the patient’s rbcs and serum do not react
test with acidified anti-B, which only react with true B antigens
what discrepancy will these factors cause?
massive transfusion of type O blood to non-O patient
chronic diseases (leukemia/lymphoma)
bone marrow or stem cell transplant
ABO subgroups
weak/missing reaction in forward type
some subgroups of A will react weaker or not at all with anti-A, but will react with __________
anti-A,B
what can occur in pancreatic, ovarian, and biliary tract cancers with ABO typing discrepancies?
there is too much soluble ABO antigen, and the antisera binds the soluble antigen rather than the RBC antigens → weak/missing forward rxn
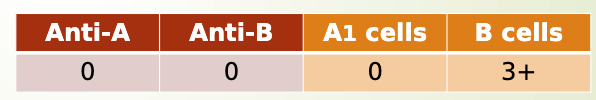
what could this indicate?
patient received O RBC transfusion
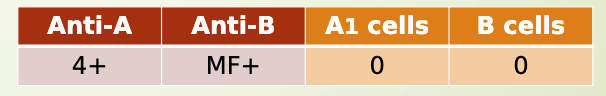
what could this indicate?
patient received A RBC transfusion
resolutions for weak/missing forward reaction?
check patient history
incubate at RT or cold → enhance reactivity
test with anti-A,B → weak subgroups
wash patient RBCs to remove soluble ABO antigen
what type of discrepancy do these factors cause?
elevated globulin (MM, waldenstrom’s macroglobulinemia)
elevated fibrinogen
rouleaux
bone marrow or stem cell transplant
cold reacting antibody
IgM alloantibody
subgroups of a
extra reaction in back type
resolutions for extra reactions in back type
saline replacement
A1 lectin
cold autoadsorption
warming at 37C
saline replacement technique
tells apart true clumping vs rouleaux
centrifuge, remove plasma, add saline
true agglutination = remains +
A1 lectin
Dolichos biflorus
only agglutinates A1 antigen
how are A2 type patients confirmed through testing?
may develop anti-A1 → + reverse
add A1 lectin to patient RBC → - forward
add A2 cells to patient plasma → - back
autoadsorption
remove autoantibodies so that underlying (“masked”) alloantibodies may be identified
patient's RBCs are mixed with their own plasma at 4°C so the cold autoantibodies stick to the RBCs and leave the cleaned plasma behind
what discrepancy do these factors cause?
chronic diseases (leukemia/lymphoma)
bone marrow or stem cell transplant
age of patient (elderly or infant)
acquired or congenital agammaglobulinemia
weak/missing reaction in back type
why do cord blood and heel stick testing for babies not include performing a back type?
newborns do not start developing antibodies until 4 months old
resolutions with a weak/missing reaction in back type
check patient history
add more plasma
incubate at RT or cold
what should also be done when incubating at RT/cold to enhance reactivity in back type?
test against O cells → rule out cold alloantibodies
run auto control → rule out cold autoantibodies