Ch. 13 : The Occipital Lobes & Networks
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/31

There's no tags or description
Looks like no tags are added yet.
32 Terms
Occipital-Lobe Anatomy
main function : vision
posterior within the brain
contains many distinct visual areas & these visual areas extend into the temporal and parietal lobes (occipital lobe is the 1st for vision, but it doens’t do the most)
V1 (primary visual cortex) = surrounds the calcarine sulcus & contains distinct layer & sublayers
contains:
Blobs = process colour info
interblobs (spaces b/w blobs) = process form (shape) & motion
note: the organization of the primate visual system has been studied extensively in Old world monkeys → helps us understand human vision
Topography of the Human Visual Cortex
the primary visual cortex is organized in a topographical:
fMRI’s show abt 25 different visual topographic regions

→ visual cortex is organized into diff areas
cells are in layers in the visual cortex = striate cortex
move from V1 (blobs & interblobs)→ V2 (contains stripe areas)

Organization of Visual Arcs
→ visual processing starts in V1 and projects to all major visual areas (dorsal stream, ventral stream, STS)
V1 (primary visual cortex) = surrounds the calcimine sulcus & contains distinct layer & sublayers
heterogeneous
contains:
Blobs = process colour info
Interblobs (spaces b/w blobs) = process form (shape) & motion
→ processing gets more complex from V1 → V2
→ colour perception ENHANCES our ability to detect form & motion
V2 = the secondary processing location & it projects onwards to major visual areas
heterogenous
contains:
Thin stripes = involved in colour perception (info from V1 blobs)
Thick stripes = process form info (info from V1 interblobs)
Pale stripes = involved in motion perception
projects to major visual areas:
Dorsal stream (how) = visual guidance of movementt
goes into parietal lobe
Ventral stream (what) = object perception & motion perception
goes into temporal lobe
STS stream = object perception & motion perception
goes to higher section of temporal lobe
where the dorsal & ventral stream communicate + also gets info from V1

Theory of Occipital-Lobe Function
→ V1 and V2 seem to be heterogenous areas processing all types of visual info
→ higher visual areas are more specialized, but can still integrate info from multiple aspects of vision:
V3 = processes dynamic form or the shapes of objects in motion - dorsal stream
V4 = predominantly processes colour info - ventral stream
V5 = involved in motion processing (MT) - dorsal stream
note: not all of these are in the occipital lobe
damage to these higher visual areas results in defects SPECIFIC to the fxns of those areas
ppl with V1 damage report being blind, BUT smaller projections from subcortical areas to these higher visual areas provide some limited vision
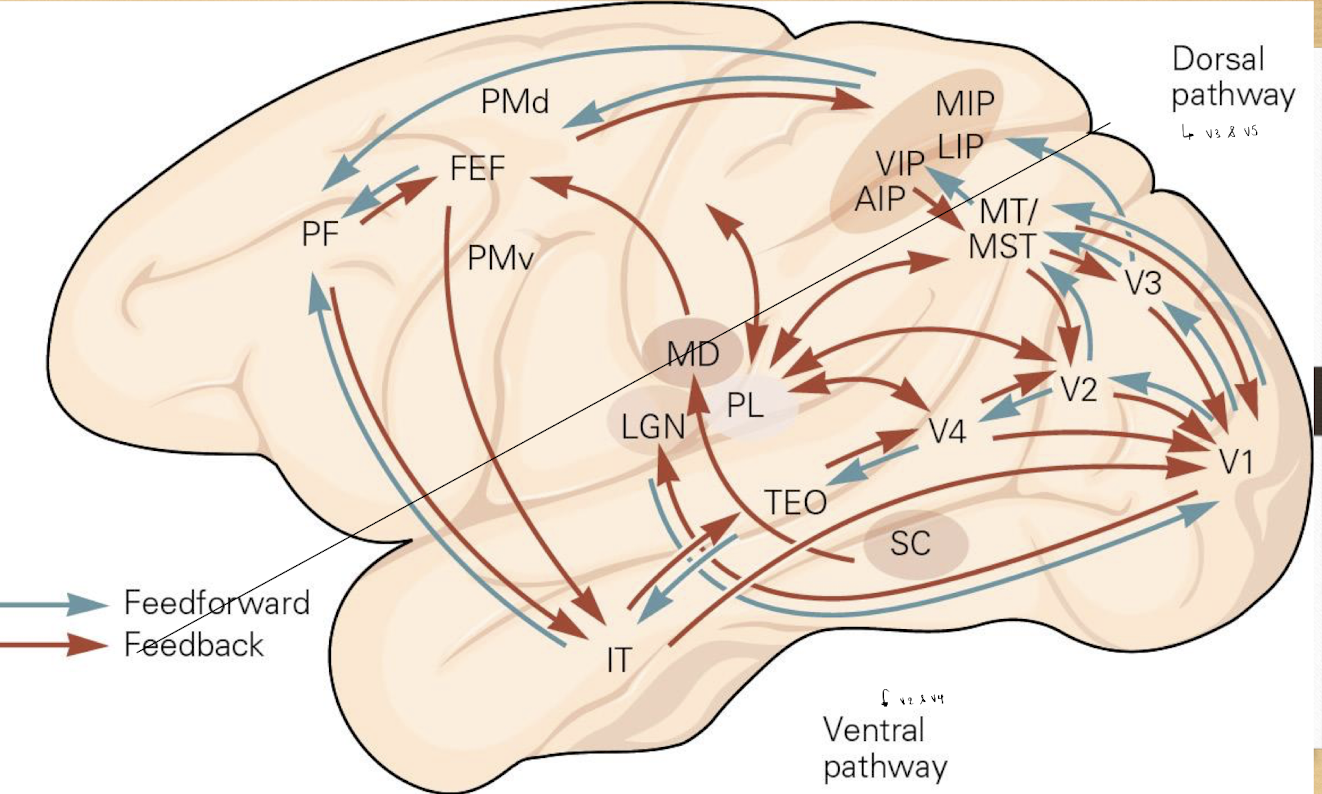
Visual Networks beyond the Occipital Lobe
a dorsal & ventral pathway for the visual system was proposed based on macaque monkey studies
→ using resting-state fMRI, new research suggests the ventral stream contains 2 parts : one on the lateral surface & one on the ventral surface of the temporal lobe
note: ventral pathway seems to be related to language
→ visual streams project to many higher visual areas THROUGHOUT the temporal, parietal & frontal lobes
these visual areas seem to have specific fxns & interact
these sometimes project back to the occipital lobe

Vision for Action: Using vision to aid actions
→ visual processing is necessary to:
1. direct specific movements (can see what’s there)
ex. like reaching for a mug or phone (uses dorsal stream)
to shape the hand to pick up the object (see size/recognize shape using the ventral stream)
→ visual processing can be done with or w/o attention & awareness
→ interaction b/w multiple areas (mainly in the parietal lobe of the dorsal stream) is required to process the visual info abt MOVING targets in order to catch it
Action for Vision
→ when looking at an object, the visual system focuses on ONLY part of the object
ex. when u look at a face, the observer (u) focuses on the eyes & mouth - particularly in the LEFT visual field
possibly in L-visual field, bc its sent to the R-hemis that specializes in emotions
note: bias to the L-visual field seems to be specific for viewing faces
→ when a subject performs a mental rotation task, the task is often accompanied by EYE movements (bc of feedback?)
Visual Space
→ Objects can be described in terms of their relation to the observer (egocentric space) or to e/o (allocentric space)
the visual system likely encodes BOTH perspective (egocentric & allocentric) to guide movements appropriately & to remember a visual scene
allows us to process/interact quicker in the future (ex. first time going to a class vs ease after a month)
note: women tend to be better at allocentric space (connects to women being better at spatial memory)
Visual Pathways Beyond the Occipital Lobe
→ vision’s primary function is to guide movement, NOT to recognize objects (this just helps guide movements)
info for visually guided movement projects from V1 → parietal areas via the dorsal stream
→ the dorsal stream provides real-time visual control of action - allows us to modify movement in real time
thus we dont need to be able to identify the object, just need to know the location & shape to visually control action
pts with damage to visual areas demonstrate the roles of the dorsal & ventral streams:
damage to lateral occipital area : CANT consciously see, but can reach for an object unseen with correct hand shape to grasp
damage to dorsal stream : can see objects, but CANT accurately reach for them
Role of Dorsal-Stream Neurons
location : parietal lobe
Posterior parietal visual neurons = activated ONLY by movement (when the brain is acting on visual info)
just looking at the objects DOESNT cause activity in these cells
provide a connection b/w the visual world thats perceived + the intent to take action in that world + interacts directly with our movements
→ visual info abt shape, movement & location is sent to the parietal lobe over DIFF pathways:
some from occipital : movements & some shape
some from ventral stream : location & shape
→ much of this processing occurs below conscious awareness
→ parietal-cortex lesions that impact visual areas are usually characterized as:
Visuospatial = difficulty with WHERE something is in space
Visuomotor = difficulty MOVING twd something in space
Visual Processing Hierarchy
V1 send info to the dorsal stream’s V5 (motion) & V3A (form) → sent to parietal visual areas for ACTION
V1 also send info to V2
V2 send info to:
V3 (dynamic form) & V4 (colour form) in the ventral stream → sent to temporal visual areas for OBJECT RECOGNITION
ALSO send info to parietal visual areas for ACTION
→ V1 is the most important as it sends to dorsal stream for action, sends to V2 for object recognition, AND sends to V2 to be sent to parietal visual areas for action
→ with a damaged V2 : CANT recognize, BUT we can still act because V1 sends info to the dorsal stream→ this displays why visions is MORE for action instead of object recognition

Imaging Studies of Dorsal & Ventral Streams
when comparing 2 faces:
activity in the temporal lobe (ventral for recognition of facial features) when asked to say which faces were the same
activity in the parietal lobe (dorsal for action) when asked to consider where on the face a dot or box was superimposed
increased activity in V5 (dorsal) when asked to detect motion
activity in V4 (ventral in temporal lobe) when asked to detect colour
→ fMRI studies in primates also show similar results the these lesion studies
What does Imaging Visual Pathways Tell us?
→ shows that diff areas of the brain tend to specialize in different functions of vision
ex. facial recognition in the temporal lobe
ex. spatial location in the parietal lobe

Disorders of Visual Pathways (Part 1)
the L side of each retina projects to L-hemis & R side of each retina projects to R-hemis
L-visual field is sent to R-hemis (using info from both eyes)
R-visual field is sent to L-hemis (suing info from both eyes)
info from both eyes is combined in V1 - combined in one cell to prevent double vision
if a visual disturbance affects BOTH eyes → disturbance must be occurring in V1 (where they’re combined)
if a visual disturbance affects info from ONLY ONE eye → disturbance must occur at the eye, retina or optic nerve (BEFORE V1)
ex. closing one eye and not having the vision from it
visual info is mapped onto a specific location in the retina
this mapping is retained up to the visual cortex
→ clinicians can diagnose the site of damage to visual pathways based on where blindness occurs in the perceived visual field
location of injury results in diff visual patterns
Different Visual Patterns Resulting from Injuries
standard vision
Monocular blindness = no info from one eye
lose info from L&R visual field that would be received in that eye
Bitemporal hemianopia = cut at the optic chasm
L-hemis only gets R-visual field info from L-eye
R-hemis only gets L-visual field info from R-eye
Right nasal Hemianopia = block crossover info from one eye
ex. R-hemis gets L-visual field info from both eyes, but L-hemis only gets R-visual field info from one eye
Homonymous Hemianopia
Quadrant -anopia
macular sparing


Disorders of Visual Pathways (Part 2)
Macular Sparing = damage to the visual cortex usually DOESNT affect info from the central part of the visual field
could be bc the region of the visual cortex related to macular vision receives blood from MULTIPLE cerebral arteries - making a stroke in that area less likely

Scotomas = small blind spots that are often unnoticed bc the eye is constantly moving & the brain fills in the blind spots (w info from previous positions of the eyes)
from small damage to V1 (primary visual cortex)

Consequences of Lesion in area V1 (Primary Visual Cortex)
damage to V1 usually only occurs in one hemisphere
partial damage leads to visual impairment
complete damage leads to blindness
Disorders occurring with damage to the LEFT visual cortex (V1):
Hemianopia = COMPLETE loss of R-visual field

Quadrantanopia = large lesion in one part of LEFT V1 → blindspot at that location in R-visual field
person would be aware of the blindspot

Scotoma = smaller injury to V1 → small blindspots that the brain fills in
person is usually unaware of

Disorders of Cortical Function
→ case studies are often used to understand the fxn of a specific brain region based on the deficits that occur after damage to that region
Know for each case study : what they can & cant do
Case study: B.K.
issue : V1 damage & scotoma
loss of vision in L-visual field → regained lower-left visual field but scotoma remained in the upper left-visual field & form vision was poor in the scotoma region
area of scotoma in L-visual field is rly small
rest of the upper L-vsiual field is unclear (reduced acuity)
cause : MRI showed a stroke in the R occipital lobe
this support the recovery of the lower L-visual field

Perimetry = maps regions of blindness by asking pt to detect s small light moving against a dark background
Result:
Unable to detect the light in the area of the stroke
could say that there had been light after it was moved
→ CAN detect movement, CANT say where it is in the damaged area
Diagnosis:
Blindsight = sensation w/o perception bc of damages
can still detect movement bc dorsal stream is intact
“ it moved, but I didn’t see it”
Case study: D.B.
issue : V1 damage & Blindsight
CANT see anything in the L-visual field (more severe than B.K.) , but sometimes have a “feeling” somethings there
cause : surgery removed part of the R-calcarine fissure (near V1)
result:
see nothing in L-visual field, but have a feeling somethings there
can correctly guess the shape of object in L-visual field
can indicate the location & orientaion of stimuli/lines they DIDNT see in their L-vsiual field
diagnosis:
Cortical Blindness= when a pt has NO conscious awareness of visual stimuli, but can accurately indicate location, directions, forms or colours of the stimuli
note: B.K.’s blindsight is a less severe version of this (B.K. couldn’t indicate location, form or colour, but he could indicate movement)
Case study: B,I.
issue : MOST significant damage to v1
bilateral damage to occipital lobe in first 2 weeks of life
cause : genetic disorder
result at age 6:
NOT blind, but has damage to both sides of V1
can recognize faces and colours & navigate his environment
how:
can see due to significant plasticity to rearrange his visual system so that the thalamus sends info to V5 instead of the damaged V1
note: V5 usually gets a little info from thalamus normally but this plasticity strengthens the pathway from subcortical areas (thalamus) to V5
→ shows that during early life we can recover from significant damage even tho the pt lacks cells in V1, bc others visual areas took over V1

Case study: J.I.
issue: V4 damage & loss of colour vision
note: V4 is the ventral path for visual recognition
lost colour vision after a car accident bc of damage to V4
result:
could only see gray + visual acuity improved (he could notice differences b/w shades of grey)
couldn't remember or imagine colours (colours no longer exist to him)
even dreamed in grey
Case study: P.B.
issue: damage to V1 & V2
damage to posterior cortex bc of loss of O2 → damaged V1 & V2
cause : electrocuted & resucitated
result:
blind, but could detect the presence of light
able to imagine & dream in colour
UNLIKE J.I who had V4 damage
shows:
damage to blobs in V1 and stripes in V2 → Pt is still ABLE to think, imagine or dream in colour
BUT
damage to V4 → NOOOO colour
Case study: L.M.
issue: V5 (MT) damage & movement
unable to detect motion after damage to V5
result:
normal vision, but CANT detect movement
difficulties pouring liquids bc she cant see the level rise (no continuous motion)
interacting w ppl is disturbing bc she cant see them move
→ suggests that the brain’s processing of a form/objects movement is done separately from processing of just the form of an object
thus, processing movement of something is diff than its shape
note: these symptoms can be mimicked by applying TMS to V5
TMS creates temporary lesions to V5 bc its close enough to the skull
Case study: D.F.
issue: occipital damage & visual agnosia
carbon monoxide poisoning causing damage to LO area (in ventral stream)
result:
CANT recognize line drawings of objects
CANT draw pictures of objects when looking at them
CANT reproduce line drawings
Can reach for and grasp objects, even tho they CANT recognize them
CANT tell/judge if lines are horizontal or vertical, but can orient movement to match horizontal or vertical lines
diagnosis:
seem to have an intact dorsal stream (can act), but a damaged ventral stream
visual agnosia = inability to recognize objects or pictures of objects - or the inability to draw a copy of the objects
ex. this pt CANT draw the orientation of a slot in front of them, but they can match their hand/object to the orientation of the slot
this tests visuomotor guidance

Case study: V.K.
issue: parietal damage (damaged dorsal stream) & visual guidance
damage to posterior PARIETAL lobe (damaged V5)
cause : bilateral strokes in occipitoparietal regions
result:
normal form & colour vision
CANT reach for objects or form the correct hand shape to pick up objects
diagnosis:
Optic Ataxia = deficit in visually guided movements, such as reaching
Comparing Grasp Patterns in case studies D.F. & V.K.
D.F. : intact dorsal stream (can act), but a damaged ventral stream
CAN grasp a shape properly
CANT discriminate shapes in a same-different task
V.K. : damaged dorsal stream (cant act)
CAN recognize objects
CANT grasp shape properly (chooses random grasp points)

Case study: D & T
issue: difficulty with higher-level processes
this case study demonstrates a double dissociation
D : lesion to R occipitotemproal region ( R ventral stream damage)
Unable to recognizes faces
some issues reading (can still read tho)
diagnosis : Prosopagnosia
→ Prosopagnosia = inability to recognize similar faces
usually results from R-temporal damage
T : lesion to L occiptotemporal region (left is where lang is)
CANT read
can recognize faces
diagnosis : Alexia
→ Alexia = inability to read
usually results from L-temporal damage
Visual Agnosia
= inability to recognize objects or pictures of objects - or the inability to draw a copy of the objects
Types
→ Apperceptive agnosia = object agnosia in which a pt CANT recognize a basic feature of an object, like colour or motion
typically due to bilateral damage to the lateral occipital lobe (V3, V4, V5 areas)
ex. can recognize an apple but NOT its colour
→ Simultagnosia = ONLY able to perceive ONE object at a time
typically due to bilateral damage to the lateral occipital lobe (V3, V4, V5 areas)
ex. 3 bags on a table → can only perceive one bag at a time
→ Associative agnosia = can perceive an object, but CANT recognize it
typically assoc w damage to the ventral stream
ex. can see somethings there, but cant say what it is
can still pick up the object & react to diff objects bc dorsal stream ISNT damaged
other Visual Agnosia’s
→ Prosopagnosia = CANT recognize familiar faces, including their own
recognize ppl based on the sound of their voice, hair or walk
have normal visual perception (can describe the face)
can differentiate b/w human & non-human faces
assoc w bilateral damage at the occipitotemporal junction
if not bilateral, tends to be on the R-hemis & less severe
→ Alexia = inability to read
can be considered a visual agnosia where the pt is unable to combine parts (letters) into a whole (words)
assoc w damage to the L fusiform gyrus & lingual area
damage near wernicke’s, NOT broca’s
bc the L-hemis is specialized to combine letters to form words
Visual Imagery
→ visualization is important (not as much as we used to think) for problem solving & other thought processes
some pts CANT recognize an object or draw an object in front of them, but can draw it from memory → demonstrates INTACT imagery
bc: damage is to seeing, NOT memory or recall
research suggest that imagery results from top-down activation of visual areas & may be initiated by prefrontal areas
mental rotation of visual images uses R-hemis dorsal stream areas - bc its for an action
