Fluid/Electrolytes
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/41

There's no tags or description
Looks like no tags are added yet.
42 Terms
Sensible loss
measured loss
urine, suction cannister, wounds/drains, stool, gastric contents (via suction)
Insensible loss
cannot be seen or counted
sweat, breathing, etc.
Osmolality
concentration of particles (solute) in 1 L of body fluid (water-solvent)
Hyperosmolar
increased concentration
volume deficit
Hypo-osmolar
decreased concentration
volume excess
Hypertonic
water in but needs out
high volume of solute/very concentrated/lots of salt
cell shrivels up
fluid is pulled out of cell and off of body, moved to blood stream
*used more rarely — severe cerebral edema (get fluid out)
Isotonic
water out = water in
equal concentration to amount in body
no fluid shift
used for fluid replacement in hypovolemic dehydrated patient
dehydrated at all levels & require fluid replacement everywhere
Hypotonic
water out but needs in
diluted, more water than particles
cell swells & bursts
used to prevent dehydration preemptively (ex. NPO, pre-op)
dehydrated at cellular level
5% dextrose in LR
5% dextrose in 0.9% NaCl
Hypertonic IV fluids
0.9% NaCl
LR
Isotonic IV fluids
0.33% NaCl
0.45% NaCl
Hypotonic IV fluids
Dehydration
loss/deprivation of water from cells
DECREASED blood volume
INCREASED blood concentration
CM: dec. LOC, inc. RR and HR, weak pulse, dec. BP
Hypovolemia
low volume in blood
inc HR, weak and thready
dec. BP and urine output (less vol = less pressure)
**inc. serum sodium
dehydration
Hypervolemia
high volume in blood
inc HR, bounding
inc. BP and urine output
fluid overload
3rd spacing
leaking of extra-cellular fluid into a serous cavity
fluid is trapped, not lost
ex. ascites, burns
135-145 mEq/L
Normal sodium level
3.5-5 mEq/L
Normal potassium level
1.3-2.3 mEq/L
Normal magnesium level
8.6-10.2 mg/dL
Normal serum calcium level
97-107 mEq/L
Normal chloride level
25-29 mEq/L
Normal bicarbonate level
2.5-4.5 mg/dL
Normal phosphate level
Sodium
maintains water and acid-based balance
conduction of muscle and nerve tissue
attracts fluid
NEURO!
Hypernatremia
very concentrated in little amount of fluid
causes: fluid loss (diarrhea, insensible loss), fluid deprivation
manifestations: seizures, disorientation, hallucinations, agitation
Hyponatremia
loss of electrolytes; too much fluid, this electrolyte is diluted
causes: fluid loss (vomiting, diarrhea, sweating, diuretics), water gain
manifestations: lethargy, confusion, edema, hypotension
increased intracranial pressure
Potassium
cardiac muscle contraction
electrical conductivity
neuromuscular transmission of nerve impulses
CARDIAC!
NEVER give IV push
IV: 10-20 mEq/hr
Hyperkalemia
causes: renal failure (not being filtered out), meds, diet
manifestations: muscle weakness, cardiac irregularities, paresthesia
SLOW HR — can lead to asystole
Hypokalemia
causes: fluid loss (vomiting, GI suction, diarrhea, diuretics)
manifestations: muscle weakness, cramps, dysrhythmias
FAST HR
Calcium
cell permeability
bone and teeth formation
blood coagulation
nerve impulse transmission
normal muscle contractions
regulated by parathyroid hormone
Hypercalcemia
causes: cancer, hyperparathyroidism
manifestations: lethargy, bone pain, n/v, confusion
Hypocalcemia
causes: inadequate intake/absorption, excess loss
manifestations: numbness/tingling, cramps
Trousseau’s sign
result of hypocalcemia
hand/finger spasm in palmar flexion
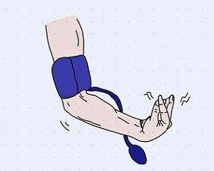
Chvostek’s sign
result of hypocalcemia
facial twitching

Magnesium
enhances neuromuscular communication
Hypermagnesemia
causes: renal failure, use of antacids/laxatives
manifestations: lethargy, diminished DTRs, respiratory depression, n/v, weakness
Hypomagnesemia
causes: fluid loss, enteral/parenteral feedings, alcohol use, sepsis
manifestations: increased DTRs, weakness, tremors, seizures, resp. paralysis
Chloride
acts w/ sodium to maintain osmotic pressure
excreted and conserved w/ sodium by kidneys
regulated by aldosterone
Hyperchloremia
causes: metabolic acidosis, hyperparathyroidism, hypernatremia
manifestations: tachypnea, weakness, decreased cognition, lethargy
Hypochloremia
causes: fluid loss, metabolic alkalosis
manifestations: muscle excitability, tetany, cramps, inc. DTRs
Phosphate
promotes energy storage
carb, protein, fat metabolism
bone & teeth formation
activated by vitamin D
regulates calcium (inverse relationship)
Hyperphosphatemia
causes: renal impairment
manifestations: weakness, dysrhythmias, anorexia
Hypophosphatemia
causes: alcohol withdrawal, DKA, diuretics, absorption issues
manifestations: weakness, slurring, dysphagia, paresthesia, dec. resp. effort, confusion