MICR5836 L14: Nosocomial Infections 9/18/26
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/80

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
81 Terms
What is this?
-Infection acquired while receiving health care [HAI]
-From hospital, aged care or any health facility
-Not present during the time of admission
-Symptoms may not appear until after discharge
Nosocomial Infection
What did Ignaz Semmelweis notice?
-Puerperal Fever: Maternal mortality of 10 – 30%
-Higher in women cared for by doctors than midwife clinics
-Pathologist who cut himself during an autopsy developed similar illness
What Intervention did Ignaz Semmelweis suggest?
-Handwashing was introduced
-Puerperal Fever incidence reduced by hand disinfectant
-Mortality dropped [from 10-30%] to 2%
Describe types of Hospital or Healthcare-related infections
-Central line associated blood stream infection (CLABSI)
-Catheter-related bloodstream infection (CRBSI)
-Catheter associated urinary tract infection (CAUTI)
-Surgical site infection (SSI)
-Ventilator associated pneumonia (VAP)
Name some other types of Hospital or Healthcare-related infections
-Gastroenteritis
-Localised skin/wound infections
-Viral respiratory infections
-Puerperal Infections (1-10 days post partum)

Name some common Bacterial causative agents of Nosocomial Infections
-Acinetobacter
-Burkholderia cepacia
-Clostridium difficile, C. sordellii
-Enterobacteriaceae (carbapenem-resistance)
-Enterococcus faecalis, Escherichia coli
-Klebsiella pneumoniae
-Multi-drug resistant Staphylococcus aureus

Name some other common Bacterial causative agents of Nosocomial Infections
-Mycobacterium abscessus
-Pseudomonas aeruginosa
-Staphylococcus aureus
-Tuberculosis (TB)
-Vancomycin-intermediate/resistant Staphylococcus aureus
-Vancomycin-resistant Enterococci (VRE)
Name some common Viral causative agents of Nosocomial Infections
-HIV (Human Immunodeficiency Virus)
-Hepatitis
-Influenza
-Norovirus
-SARS-cov-2
What is this?
-Staphylococcus aureus (MSSA, MRSA) + epidermis
-Pseudomonas aeruginosa
-Klebsiella pneumoniae
-Enterococcus faecalis
-Acinetobacter baumannii
-Most common bacterial causative agents
-Responsible for 25 - 50% infections
-Caused by patient’s own flora + invasive devices
What are the most common bacterial causative agents that are responsible for 25 - 50% infections [from patient’s own flora + invasive devices] ?
-Staphylococcus aureus (MSSA, MRSA) + epidermis
-Pseudomonas aeruginosa
-Klebsiella pneumoniae
-Enterococcus faecalis
-Acinetobacter baumannii
Are these Risk Factors considered Resource Dependent?
-Prolonged and/or inappropriate use of invasive devices
-Prolonged and/or inappropriate use of antibiotics (Clostridium diff)
-High risk procedures
Resource Independent
Are these Risk Factors considered Resource Dependent?
-Immunosuppression
-Other underlying patient conditions (comorbidities)
-Incorrectly applied standard procedures and isolation protocols (staff are incompetent)
Resource Independent
Are these Risk Factors considered Resource Dependent?
-Inadequate waste disposal facilities/provisions
-Unhygienic environment
-Poor infrastructure
-Insufficient equipment
Resource Dependent
Are these Risk Factors considered Resource Dependent?
-Understaffing
-Over crowding
-Poor staff infection control training/knowledge
-Lack of procedures, guidelines and policies
Resource Dependent
True or False: 50% of Nosocomial Infections caused by Endogenous Transmission from the patient’s own flora
True
Where do ~50% of Nosocomial Infections with Exogenous Transmission come from?
-Direct Contact [Hand hygiene] or Indirect Contact [Fomites]
-Airborne
-Faecal-oral route
-Blood and body fluid exposure
Name some examples of Fomites that spread Exogenous Transmission [50%] through Indirect Contact
Medical Equipment, Clothing, Bedding, Furniture, etc.

Describe how a viral infection can spread in hospitals
-Asymptomatic/presymptomatic patients, super spreaders
-Respiratory virus, not wearing mask, recipients lying in bed
-Poor ventilation increases environmental virus concentration, constant temperature and humidity, spreading contaminated surface
How do hospital staff become a principle source of HAI?
-Endogenous transmission from the patient's own resident microbial flora
-Cross infection from patient to patient, assisted by hospital staff
How does the hospital environment become an important source of HAI?
-Faces soiled by organic material, used/improperly sterilised
-Surgical or anaesthetic equipment
-Protective clothing: Contaminated from outside
-Toilet
What makes HAI difficult to diagnose?
-Often indigenous flora
-Sampling can be invasive (e.g. biopsy, bronchoscopy)
-Interpretation of results can be complicated
What makes HAI difficult to treat?
-Antibiotic resistant strains
-Presence of indwelling medical devices
-Compromised host defences [Steroids for cancer dampen immune response, reduces patient's ability to fight infection]
Is this a developed or developing country?
-7/100 patients
-3 to 12% develop nosocomial infections
-Most infections consist of UTIs
-ICU rates of nosocomial infections are up to 30%
Developed Countries
Is this a developed or developing country?
-10/100 patients
-5-30% develop nosocomial infections
-Surgical site infections are 9x higher than other countries
-ICU rates of nosocomial infections are up to 88%
Developing Countries
Describe the rate of Nosocomial Infections in Developed Countries
-7/100 patients or [3-12%]
-Most common type of nosocomial infections are UTIs
-ICU rates of nosocomial infections are up to 30%
-1.7 million patients per annum in the US
Describe the rate of Nosocomial Infections in Developing Countries
• 10/100 patients or [5-30%]
– Surgical site infection rates are 9x higher
-ICU rates of nosocomial infections are up to 88%
True or False: Longer stay= increased rates and likelihood of more than one nosocomial infection acquired
True
Describe some Consequences of Nosocomial Infections
1) Prolonged Hospitalisation + Increased Cost
2) Additional Morbidity
3) Longterm physical and psychosocial sequelae
4) Death
How do Nosocomial Infections prolong hospitalization?
Average of 11 day longer hospital stays for patients with HAI
How much do nosocomial infections increase the cost of hospitalization?
-$20 billion per year in US, $400 million in AUS
-Each blood stream infection costs $10000 to $50000 AUD
What is the mortality of Staphylococcus aureus BSI?
25%
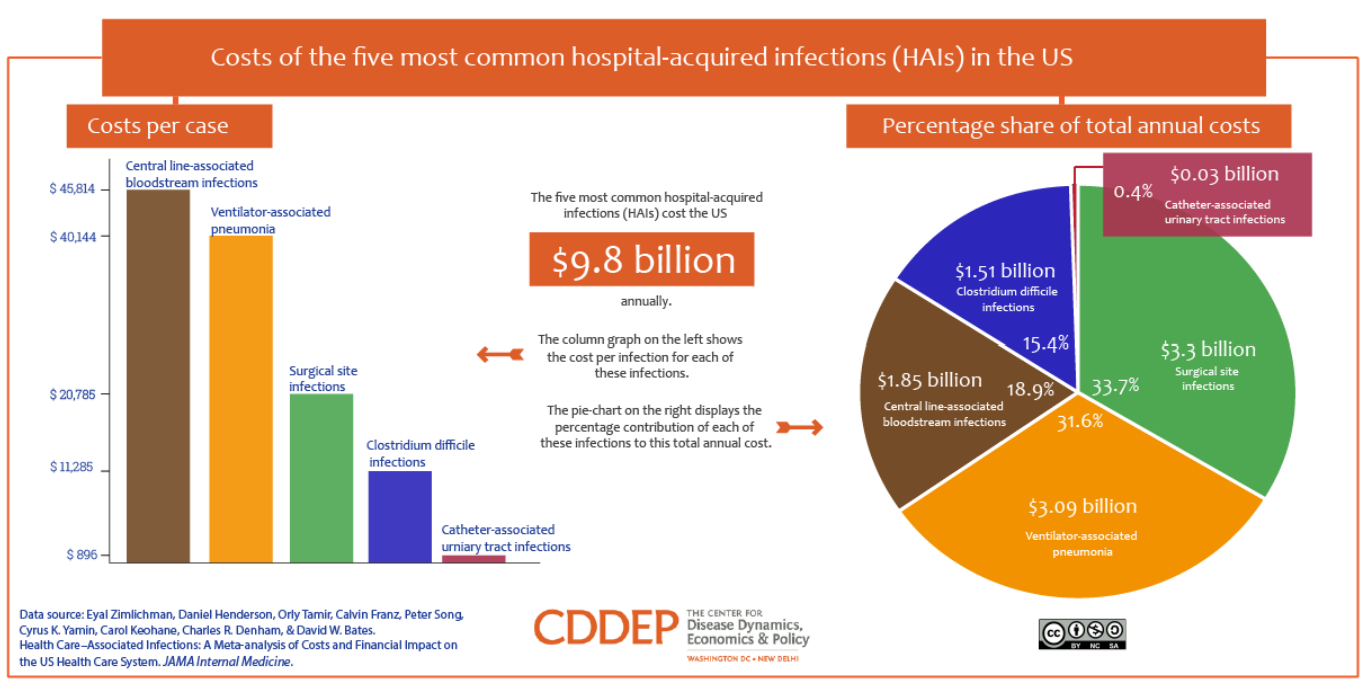
What is this?
1) Central line-associated bloodstream infections
2) Ventilator-associated pneumonia
3) Surgical site infections
4) Clostridium diffcile
5) Catheter UT infection
-Top 5 most common nosocomial infections
-Costs US about 9.8 billion dollars annually
True or False: The Top 5 most common nosocomial infections cost the USA about $9.8 billion annually
True

What are the top 5 most common HAI in the USA?
1) Central line-associated bloodstream infections
2) Ventilator-associated pneumonia
3) Surgical site infections
4) Clostridium diffcile
5) Catheter UT infection
What is this?
-AIR
-Amikacin or Imipenem-Resistant Bacteria
-Species: Enterobacter, Pseudomonas, or Acinetobacter

What is the mean cost per patient episode of hospital acquired infection?
1) MRSA
2) VRE
3) Antibiotic-Resistant E. Coli
1) MRSA: US$60,984 ± 69,254
2) VRE: US$73,481 ± 77,479
3) Antibiotic E.coli: US$39,403 ± 38,091

What is the mean cost per patient episode of hospital acquired infection?
1) Klebsiella
2) AIR
3) Multiple
1) Klebsiella: US$39,403 ± 38,091
2) AIR: US$111,062 ± 45,444
3) Multiple: US$157,835 ± 94,181
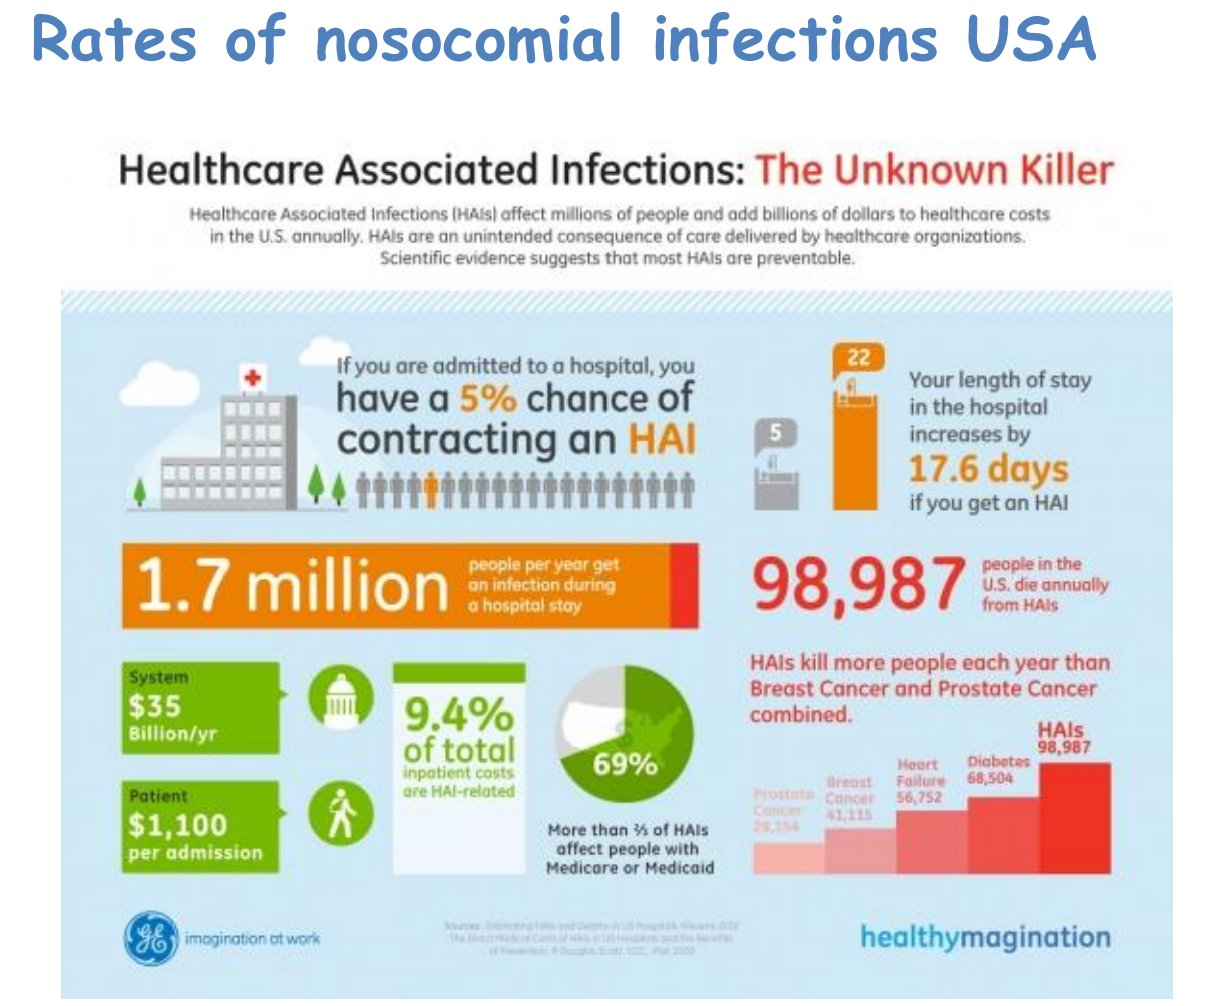
Describe the Rates of nosocomial infections in the USA
-98,987 people die from them in the US
-1.7 million people will acquire an infection
-You have a 5% chance of contracting an HAI
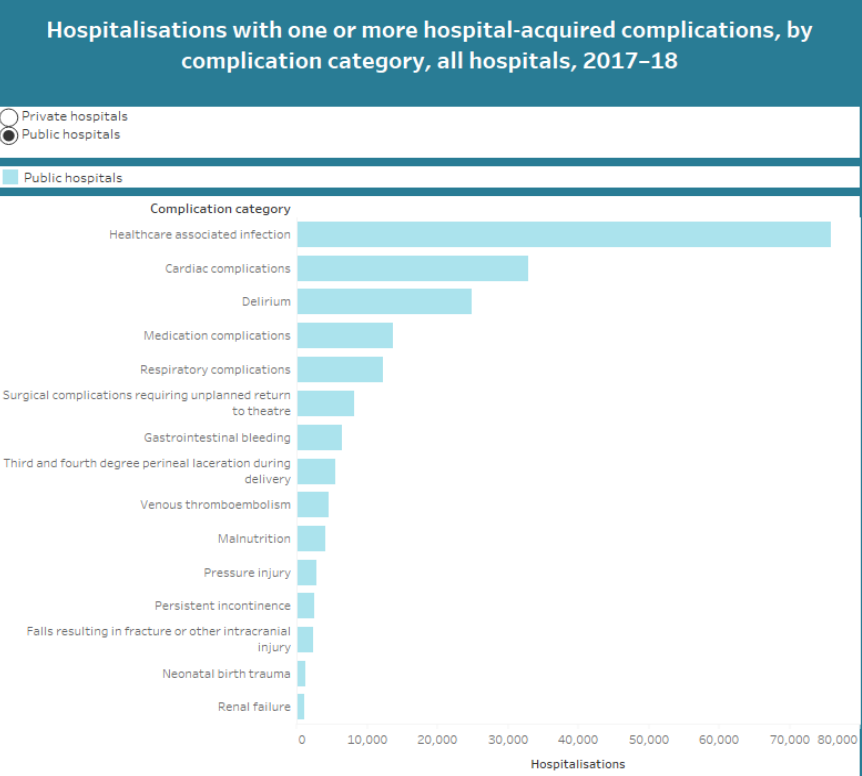
True or False: HAI outweighs all other causes of hospital issues [such as cardiac complications, delirium, medication/respiratory/surgical complications, or GI bleeding]
True

Describe the Risk of Infection to Healthcare Workers
Almost 10x more healthcare workers tested positive than members of the general community in both the UK and USA

Describe the Risk of Infection to healthcare workers in the USA based on geography
Higher concentration of cases in South/East areas of USA

Describe the SARS index case in Hong Kong
-Infected: 15/16 nurses, 6/6 doctors and >16/66 med students
-WHO Data: 8,098 cases, 774 (9.6%) died
-1707 HCW's infected, 21% of cases (150-200 deaths)
What are some targeted areas to break the chain of transmission in Nosocomial Pathogens?
1) Reservoirs
2) Predictable Routes of Infection
3) Susceptible Hosts
What is this?
-SINGLE most effective means of preventing transmission of microorganisms to/between hospital patients
-Adherence: 86% in Nurses, 71% in Doctors
-Inconvenience, time pressures, skin damage
Handwashing
Describe Hand Hygiene recommendations for healthcare works
-Alcohol rubs recommended between all patient contact
-Traditional soap and water handwash if gloves are not worn or if hands are visibly soiled
-Damaged skin is a higher risk, should be even more careful with patients to not transmit pathogens

Describe the 5 moments for Hand Hygiene according to the WHO
1) Before touching patient
2) Before procedure
3) After procedure or body fluid exposure risk
4) After touching patient
5) After touching patient's surrounding
Which type of Prevention/Control for Transmission is this?
-Must prevent transmission from personal contact or fomites
-C. difficile, AMR and infestations like scabies
-Use PPE
Contact Transmission
Which type of Prevention/Control for Transmission is this?
-Large particle droplets >5μms, coughing, sneezing,
-Neisseria meningitidis, RSV, SARS-cov-2
Droplet Transmission
Which type of Prevention/Control for Transmission is this?
-Organisms disseminated through airborne droplet nuclei or small particles in the respiratory range <5μms
-SARS-cov-2, TB, measles
Airborne Transmission
What is required for effective Prevention/Control?
-Total commitment at every level of the organisation
-Appropriate governance and management structures
Describe how this part of Management + Clinical Governance can contribute to Prevention/Control of Nosocomial Infections:
-Managers and Systems
-Managers need to be aware of the healthcare facility’s performance in terms of infection transmission
-Systems to prevent the transmission of infection, reduce risk and address problems when they arise
True or False: Management/Clinical Governance differs depending on the size of the organisation and the types of healthcare services it delivers
True
Describe how this part of Management + Clinical Governance can contribute to Prevention/Control of Nosocomial Infections:
-Person in charge of the organisation (CEO of a hospital, or principal of an office<based practice)
Must have overall responsibility/direct involvement in the organization’s infection control program
Describe how this part of Management + Clinical Governance can contribute to Prevention/Control of Nosocomial Infections:
-Prevention and Infection Control program
-Includes professional development
-Resources are adequate to run program and available to dedicated infection control staff
Describe how this part of Management + Clinical Governance can contribute to Prevention/Control of Nosocomial Infections:
-Organization
-Should define the outcome measures for monitoring infection control policies
-Need active surveillance and reporting [such as S. aureus bacteraemia, prosthetic joint infection]
Describe how this part of Management + Clinical Governance can contribute to Prevention/Control of Nosocomial Infections:
-Staff
-Employees must understand their roles and responsibilities
-Have appropriate training to maintain a safe work environment
What is this?
1) Head/Team Leader
2) Infection Control Officer
3) Infection Control Nurses
4) Member of microbiological lab staff, pharmacists
Infection Control Team
List the members of an Infection Control Team
1) Head/Team Leader
2) Infection Control Officer
3) Infection Control Nurses
4) Member of microbiological lab staff, pharmacists
What is an Infection Control Team responsible for arranging?
1) Regular Surveillance Activities
2) Inspections of Facilities
3) Investigations of Cases + Outbreaks
Whose responsibility is this? Which member of the Infection Control Team?
-Liaises with hospital management
Head/Team Leader
Whose responsibility is this? Which member of the Infection Control Team?
-Executive responsibility for 1) Initiating additional investigations and 2) Preventive Measures
Infection Control Officer
Whose responsibility is this? Which member of the Infection Control Team?
-Arranges for isolation of patients, closure of a ward, etc
Infection Control Officer
What type of job does a typical Infection Control Officer have?
Medical Microbiologist or Infectious Diseases Consultant

Describe how HAI Surveillance works
-Critical: Prevent disease transmission/improve patient safety
-Includes: Monitoring, Analysis, Report, Research
-Data Validation, Process Surveillance, and Monitoring Significant Organisms
Describe the Surveillance of C. diff
-Newer infection, only 30-40 years ago became problem
-Treatment options (antibiotics) leads to increased risk
-Bad: No quarantine for waste disposal

Describe an example of Infection Control Surveillance failing
-Pediatric heart surgery group in Bristol
-30 to 35 children died, massively excessive number
-Poor teamwork, surgeons who did not stop operations while failing
What rules govern Infection Control?
-National Quality Safety and Health Standards
-Should be implemented at every level of healthcare
Describe how Infection Control can be put into practice
-Evidence-based interventions are used to prevent common HAI’s [such as CABSI, VAP, SSI]
-“Bundled interventions”
-Adapted from clinical trials and experimental evidence
-Maintenance requires surveillance and continued education
What are some Problems that make Infection Control challenging?
-Busy staff
-Shortages of trained personnel
-Effective communication
-Lack of consistency in reporting
Describe how Infection Control policies can be applied to Surgical Site Infections when preparing the operation site
-Avoid shaving
-Clipping excessive hair is preferred
-Prepare the site with antiseptic e.g. chlorhexidine, iodine
Compare the chances of infection for surgical sites based on the pre-operation hair removal method
-Clipping: 0.6%
-Shave less than <24h: 7%
-Shave more than >24h: 20%
True or False: During surgery, you should apply antiseptic in then out (not outwards-inwards)
True
Describe how Infection Control policies can be applied to Surgical Site Infections when cleaning the environment
-Surgical scrub handwashing
-All equipment, sutures, drapes should all be sterile
Describe how Infection Control policies can be applied to Surgical Site Infections during and after operating
-Surgical Technique + Dressings
-Less time on table: Haemostasis, debridement, closure
-Hand hygiene precautions whenever wound exposed
-Discard dressings safely
How much can Infection Control reduce HAIs?
Estimated that a 30-80% reduction is possible
What percentage of CABSI and CAUTI are preventable?
Estimated 65-70% are preventable
What percentage of VAP and SSI are preventable?
Estimated 55% are preventable
Describe the estimated outcome for CABSI results if best practices are followed
-5,520 to 20,239 lives saved
-US $960 million - $18 billion per year
Describe the estimated outcome for VAP results if best practices are followed
VAP: 13,667 -19,782 lives saved, US$2.19 - 3.17 billion per year

Which countries had the most deaths from antibiotic-resistant bacteria in 2015?
1) Italy
2) Greece
3) Portugal
4) France

What was the 2015 CDC Target for reducing Nosocomial Infections?
Reduce to 10.83 infections per 100,000