PHARM: ER / CC / SURG / GERIACTRICS INDICATIONS
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/203

Earn XP
Description and Tags
MS
204 Terms
What organization ultimately determines the efficacy and addictive qualities of Rx?
(1973) Drug Enforcement Agency (DEA) was created to regulate the manufacturing and dispensing of controlled substances
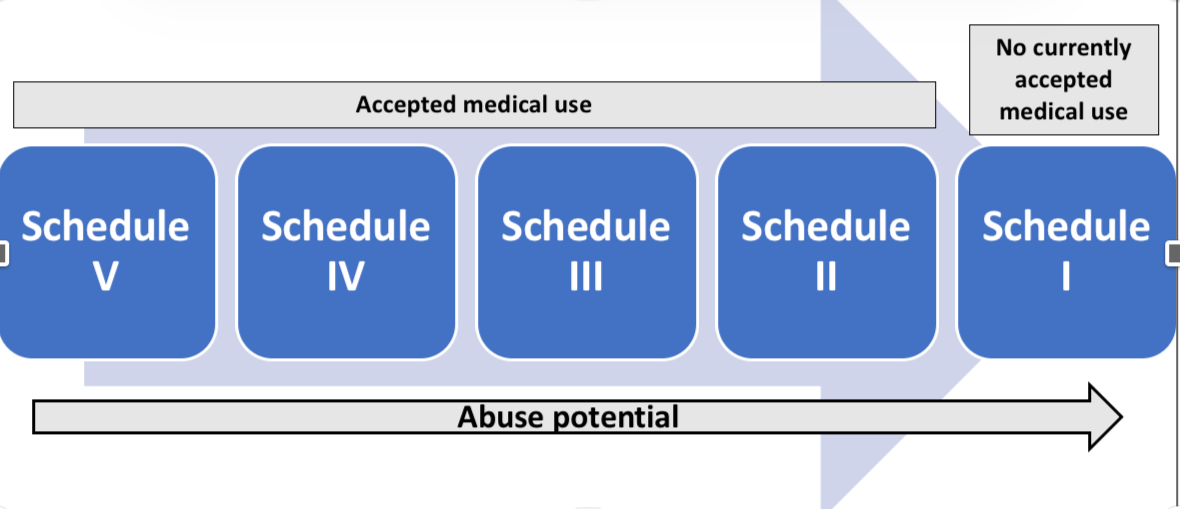
Which schedule for Rx has no acceptable medical use?
Schedule I (heroin, LSD, weed, MDMA, PCP)
What Schedule are the following Rx: hydromorphone, hydrocodone, oxycodone, fentanyl, cocaine, (meth)amphetamines, methylphenidate
Schedule II
PA / NP = only in-facility use; 90 days max + no re-fils
MD = 90 days max; no re-fills
What Schedule are the following Rx: codeine, ketamine, anabolic steroids
How many days supply can mid-levels / MD Rx?
Schedule III
PA / NP = 90 days max (includes refill amts)
MD = 5 refills worth
What Schedule are the following Rx: benzos, Z-drugs, tramadol, carisoprodol
Rx will be valid for 6 mos, how many days of supply can mid-levels / MD Rx?
Schedule IV
PA / NP = 90 days max (includes refill amts)
MD = 5 refills worth
What Schedule are the following Rx: diphenoxylate / atropine, pregablin (lyrica)
How many days supply can mid-levels / MD Rx?
schedule V
PA / NP = 90 days max (includes refill amts)
MD = 5 refills worth
How many days will the Rx be valid for if Rx by mid-levels / MD Rx for NON-controlled Rx?
PA / NP = 6 mos
MD = 12 mos
What are the essential pharmacologic points about Why Does Scheduling Matter??
DEA sets limits on production of higher abuse potential drugs
Strict regulations on how they are Rx
Lesser prescription quantities for higher abuse drugs
What is the acute MOA of EtOH like what NT incr. and inhibits?
Enhances GABA receptors (dose dependent)
Inhibits glutamate receptors (excitatory)
V, coma hypoTN, resp depression
Activation of the reward circuit (dopamine)
Chronic EtOH users can be functional d/t the upregulation of what receptors?
NMDA (glutamate) + slight depression of GABA receptors
What is the physiology of EtOH withdrawals?
upregulated NMDA receptors = unopposed (excitatory → tremors, seizures, etc.) when EtOH no longer agonizes GABA receptors
What are some chronic complications of EtOH use?
Wernicke’s encephalopathy → Korsakoff psychosis
What are 3 Rx that can help tx EtOH withdrawals acutely + Rx that can be used for long-term mgmt of alcoholism?
Benzodiazepines: stabilize vitals, reduce risk for seizures
Scheduled vs PRN (based on CIWA assessment) regimen
Clonidine ± BB: Reduce autonomic component of withdrawals
Thiamine: prevent Wernicke’s encephalopathy
Prevention: naltrexone, acamprosate, disulfiram
What is the best option for EtOH dependence PREVENTION ?
hint: interacts w/ opioids → MUST question pt for any recent consumption of any recreational drugs
What is its MOA, PK, ADE?
Naltrexone
MOA: pure opioid antagonist → Decr craving and blocks reinforcing effects
PK: qd PO or 1 monthly IM
ADE: N
caution: will induce opioid withdrawals! AVOID if opioids!
What is the Rx for EtOH dependence PREVENTION in a mgmt program setting (after detox)?
What is its MOA, PK, ADE?
Acamprosate (Campral)
MOA: possible restoration of GABA and glutamate balance
rec for mgmt programs w/ psychosocial support
PK: PO TID
ADE: D
What option for EtOH dependence PREVENTION causes unpleasant effects if interacts w/ EtOH?
Caution: MAY have to avoid all forms of alcohol (cough syrups, aftershave, cologne, etc.)
hint: similar to metronidazole
What is its MOA, PK, ADE?
Disulfiram (Anatabuse)
MOA: inhibits aldehyde dehydrogenase (acetaldehyde s.) → disrupts EtOH metabolism → Causes unpleasant effects if taken w/ EtOH
PK: PO qd → Effects last 2 weeks after the last dose
ADE: minimal as long as NO EtOH
T/F: its ok to Rx disulfiram for a pt tapering off EtOH
F. ≠ Rx if alcoholics lack the determination to stop drinking
Serotonin Syndrome: ± Mild / life-threatening condition d/t serotonin toxicity; Dx via exclusion
How fast does this develop?
How does it present?
How to tx?
Develops w/n mins to hrs
S/s:
AMS
autonomic instability: tachy, hyperthermia, diaphoresis, V, +
neuromuscular hyperactivity: clonus, hyperreflexia, tremors, +
Treatment: D/C agent(s), supportive care (IV hydration + O2 + cardiac monitoring ± sedation w/ benzos)
Which antimicrobials are serotonergic?
linezolid // ritonavir
what mood stabilizers are serotonergic?
lithium // valproate
List some Serotonergic Medications:
Antidepressants
SSRi / SNRi / MAOi / TCA
addictive drugs
cocaine, MDMA, LSD, Opioids (fentanyl / meperidine / tramadol / methadone), amphetamines, +
Antiemetics
ondansetron / metoclopramide
Migraine (triptans)
mood stabilizers (lithium / valproate)
Antimicrobials (linezolid / ritonavir)
Which opioid reversal agent has a short ½ life?
naloxone — may need multiple doses
What is the reversal agent for acetaminophen / paracetamol ?
NAC to prev hepatic failure
What is the reversal agent for BB / CCB via metabolic shift?
insulin → incr contractibility
What is the reversal agent for digoxin (GI, neuro (visual halos), cardiac (dangerous arrhythmias) s/e)?
digibind
What is the reversal agent for sulfonylureas?
octreotide → suppresses insulin → prev hypoglycemia
What is the reversal agent for benzos?
flumazenil
T/F: flumazenil is used if a chronic benzo user ODs on benzos
F. chronic users ≈ seizure prevention → reversal → ± seizures
What reversal agent converts cyanide into vit. B12?
hydroxocobalamin (renal excretion)
What is the reversal agent for methanol / ethylene glycol?
fomepizole or ethanol → inhibits alcohol dehydrogenase
What recreational schedule II Rx causes
euphoria
C
resp depression
endocarditis
What is the acute tx?
heroin (opioid) → release S / NE / D
acute tx = naloxone
What recreational schedule II Rx causes
HTN + tachycardia + vasoconstriction
hyperthermia
alertness
nasal dmg
What is the acute tx?
cocaine (anesthetic) → dopamine reuptake inhibitor
acute tx = supportive care ± benzos (seizures) ± anti-HTN
What recreational schedule II Rx causes
incr wakefullness
HTN + tachycardia
decr appetite
violent behavior
meth-amphetamine (Stimulant) → crosses BBB → incr NE / D
acute tx = supportive care ± benzos ± anti-psychotics (agitation)
What recreational schedule I Rx causes
loss of coordination
altered sense
relaxation
hyperemesis
What is the acute tx?
marijuana (delta-9-THC) → cannaboids receptor activation → incr D
acute tx = supportive care (IV fluids (hypoTN) ± hot showers (hyperemesis))
What recreational schedule I Rx causes
decr inibition
enhanced sensations
psychedelic effects
a common party drug
± used for PTSD
MDMA / esctasy → blocks reuptake of S → incr S / NE / D
acute tx = supportive care (IV fluids ± rapid cooling (hyperthermia))
What Rx is 50-100x more potent than morphine and can easily become fatal?
fentanyl (≈ contaminant in illicit Rx: cocaine, heroin, weed, benzos, meth, etc.)
What is the PK of fentanyl that makes it so dangerous (harder to reverse → ± multiple does of Naloxone?
very lipophilic → rapid brain penetration → tight bind to mu-opioid → rapid onset → quick resp depression
Indications for medical maurijuana and what are the legalities?
Must have a debilitating medical condition + documentation
Uses: seizures, N (dronabinol), pain, PTSD, insomnia
24 states have legalized recreational use / the 47 states allow for medical use
What program in Texas allows for Rx of marijuana? What are some indications?
Texas’s Compassionate Use Program (CUP) allows certain physicians to Rx low THC (tetrahydrocannabinols) cannabis for medical purposes (PO form)
Limited to:
epilepsy, seizures, MS, spasticity, ALS, autism, terminal cancer, incurable neurodegenerative dx
Activated Charcoal acts like a sponge to absorb toxins before they hit the bloodstream, what is the MOA, PK, and monitoring markers?
finely ground molecules traps chemicals d/t its highly porous surface
aqueous slurry to protect airway
Monitor:
sx improvement
C
electrolytes lvls
black discoloration of stools
When is activated charcoal most effective?
w/n 1hr of consumption of toxin
the usage of vasopressors / inotropes is guided by what measurement?
mean arterial pressure (MAP) = CO x SVR
vasopressor vs inotropes:
which impacts cardiac contractility → incr CO?
inotropes
T/F: vasopressors incr vasc tone / SVR
T
What is the common classification for the following Rx: Norepi, Epi, Dopamine, Phenylephrine, Vasopressin?
vasopressors (constricts blood vessels → incr. BP)
which vasopressor is mainly used for anaphylaxis + cardiac arrest?
epinephrine (acts on a1, b1, & b2 receptors)
which vasopressor is 1st-line for septic shock for resuscitation
norepinephrine (more a1 receptor act)
which vasopressor is dose-dependent?
low dose = dopamine receptors
med dose = beta receptors
high dose = alpha receptors
dopamine
which vasopressor causes reflex bradycardia
phenylephrine (pure a1 receptors) → good for tachycardic hypoTN
which vasopressor is an adjuct to reduce the norepinephrine dose (short ½ life)
vasopressin (V1 receptor)
Which inotrope acts on beta receptors?
dobutamine (cardiogenic shock)
which inotrope inhibits PDE-3 receptors
milrinone (cardiogenic shock, HF, on BB)
What are the typical ADE of vasopressors / inotropes that require monitoring EKG and MAP?
Dysrhythmias (d/t beta-agonist effects)
Myocardial ischemia (d/t increased myocardial O2 consumption)
Hypoperfusion (d/t excessive/prolonged vasoconstriction)
What is common about the following RFs:
infxn
75+ y/o
cancer
hx of VTE
Virchow’s triad
stasis (immobility, bed rest, obesity)
vasc inj. (trauma, surg, catheters, smoking)
hypercoagulability (trauma, cancer, pregnancy, factor V leiden, oral contraceptives)
risk of VTE!
What scoring chart helps determine the usage of thromboprophylaxis?
Padua Score!
What does a Padua score of <4 suggest?
low risk of VTE
What does a Padua score of 4+ suggest?
high risk of VTE → pharmacological thromboprophylaxis
What scoring chart provides suggestions on NON-pharm + thromboprophylactic MEDs?
Caprini Score
What does a Caprini Score of 0 rec for the pt to do?
early ambulation
What does a Caprini Score of 1-2 rec for the pt to do?
low — Sequential Compression Device
What does a Caprini Score of 3 rec for the pt to do?
mod - SCD / heparin / enoxaparin
What does a Caprini Score of 5+ rec for the pt to do?
high - SCD + heparin / enoxaparin
What dose of Enoxaparin (LMWH) = prophylaxis ?
40 mg qd
Why is LMWH preferred vs heparin for acute prophylactic tx?
convenience (1-2/day vs q8-12hrs)
UFH (IV / SQ) inhibits factor 2a and used for VTE prev. & tx // ACS // A-fib.
What labs need to be monitored, what aversion do you need to be aware of, and what capabilities do nurses have w/ this Rx?
What organ-dysfct makes this rx preferred?
monitor: aPTT, Hg / Hct / plt
pork-derivative → avoid pork allergy / religious rzns
nurse-driven dosing to help avoid HIT
used if pt has kidney dx
EnoXaparin (SQ) inhibits factor X and used for VTE prev. & tx // ACS // A-fib.
What labs need to be monitored?
This Rx is ≈ used to bridge pt until what Rx is effective?
monitor: SCr (caution in kidney dx), Hg / Hct / plt, ± anti-Xa if renal dx, extreme habitus, pregnant, prior bleeds / failures
used to bridge for warfarin
FondaparinuX (SQ) inhibits factor X and used for VTE prev. & tx // ACS // HIT
What labs need to be monitored?
monitor: SCr (caution in kidney dx), Hg / Hct / plt
Bivalirudin (IV) is used for ACS (w/ PCI) // HIT
What labs need to be monitored?
monitor: SCr , Hg / Hct / plt
directly inhibits thrombin
What are the time goals for STEMI tx? If PCI-incapable, what rx is given?
cath lab w/n 90 mins since 1st medical contact (EMTs, etc.)
if PCI unable to w/n 120 minutes → fibrinolytic (HIGH risk of bleeding) IF sx w/n last 12 hrs
What does MONA stand for in ACS management? When are each used and what is PK?
Morphine (2nd-line if SL NTG x 3 ≠ effective)
oxygen (if <90%)
nitroglycerin
0.4 mg SL q5mins PRN x 3 max (1st line)
IV (3rd-line)
aspirin (1 tab 325mg chewed)
alt: P2Y12i if allergic
Prior to the PCI, what 2 anti-thrombotic Rx are ≈ given and what can be added on? What are their purposes?
P2Y12i: inhibits plt aggregation → reduce risk of stent thrombosis
anti-coag: inhibits coag cascade → prev procedural thrombosis
± GP2b3ai: more anti-plt coverage for high thrombus burden
For PCI pharmacology, what anti-thrombotic needs a loading dose prior to Sx?
P2Y12i
What class of Rx are these: clopidogrel // prasugrel // ticagrelor
P2Y12i
What class of Rx are these: heparin // LMWH // Bivalirudin
anti-coags
What class of Rx are these: abciximab // eptifibatide // tirofiban
GP2b3ai
How is ischemic stroke treated if sx are w/n 4.5 hours?
Fibrinolytic (C/I in any bleeding risk)
What are absolute C/I to fibrinolytics?
Previous hemorrhagic stroke // stroke w/n the last yr
intracranial neoplasm
recent head trauma // active internal bleeding // aortic dissection
Aspirin prevents secondary ischemic stroke, when can you give it?
after clear CT scan + 24-48 hrs since a fibrinolytic
If it was a minor stroke / TIA, how it aspirin given?
in the form of DAPT x 21 days (wait for clearance 1st)
what Rx is given in addition to aspirin if a fibrin-rich clot was of cardioembolic source (A-Fib, valvular dx, recent MI)?
anticoags (ck CHAD-VASC score 1st)
why are anti-PLTs given for NON-cardioembolic strokes?
clot = PLT-rich d/t PLT aggregation @ plaque rupture / vasc inj
What anti-thrombotics can be reversed w/ andeXanet alfa // 4F-PCC // FFP?
DOACs (apiXaban, RivaroXaban, EdoXaban)
What anti-thrombotics can be reversed w/ idarucizumab // 4-PCC // FFP?
dabigatran
What anti-thrombotics can be reversed w/ vit K // 4F-PCC (preferred for severe bleeding) // FFP?
What coag assay can be monitored?
warfarin → INR / PT decr
What anti-thrombotics can be reversed w/ protamine sulfate?
What coag assay can be monitored?
UFH: aPTT
Enoxaparin IF w/n 12hrs of last dose
aPTT // anti-FXa
What distinguishes hypertensive EMR from urgency?
target organ damage → ADMIT
neuro: stroke, ICH, AMS
cardio: MI, unstable angina, aortic dissection
renal: hematuria, AKI
What is the BP goal in hypertensive emergency management? PO or IV?
Reduce BP by 25% in first hour via IV anti-HTN
then 160/100-110 in next 2-6 hours
normal w/n 24 to 48 hours
What is the ≈ 1st-line anti-HTN for HTN EMR?
CCBs - nicardipine // clevidipine
which anti-HTN can be used in a HTN EMR but is unpredictable and SA?
hydraliazine (direct vasodialator)
Which anti-HTN is good during preg, but C/I in pulm dx (COPD, asthma) and HF?
BB - labetalol // esmolol
Which anti-HTN has a cyanide toxicity risk (renal / hepatic impairment?
nitroprusside
Which anti-HTN should not be used if pregnant, acute MI, or b/l renal a. stenosis?
ACEi enalaprilat
Which antibiotics cover MRSA (list 7)
BCD2-C2L
Very Large Cats Do Take Big Craps?
Vancomycin
daptomycin
linezolid
clindamycin
bactrim
doxycycline
ceftaroline
Which antibiotics cover Pseudomonas?
Pip-tazo
carbapenems (err ertapenem)
cefepime // cetazidime
ciprofloxacin // levofloxacin
aminoglycosides
What is the mainstay of COPD exacerbation treatment?
hint: PDA
Systemic corticosteroids (any)
prednisone 40mg x 5 day
Duoneb (SABA / SAMA)
± Abx if purulent sputum +
dyspnea / more sputum
What empiric antibiotics treat COPD exacerbation?
Amoxi-clav
azithromycin
doxycycline
FQ for severe or freq exacerbations
What is the mainstay of asthma exacerbation management?
Systemic corticosteroids x 5-10 days
Duoneb (SABA / SAMA)
discharge with maintenance therapy
Where do stress ulcers develop and what are the RFs?
ICU
Mechanical ventilation 48+ hours
coagulopathy (low PLT, high INR)
steroid
NSAID
H pylori
What are options to prev stress ulcers?
Proton pump inhibitor (pantoprazole)
H2 receptor antagonist
discontinue when risk factors resolve
when are pre-op abx given, what form, and when to d/c?
give IV abx 30-60min prior → d/c 24hrs after sx