Disorders of Kidney and Urinary Tract Function
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/31

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
32 Terms
Urinary Tract
produces, stores, and eliminates urine
Composed of bladder, 2 kidneys, 2 ureters, and the urethra
Kidneys
Responsible for homeostasis via urine production and elimination
Body functions impacted
BP
Electrolyte and acid-base balance
RBC production (makes EPO erythopoeitn that tells Bone marrow to make RBC)
Bone health (convert vit. D into active form and Ca reabsorption)
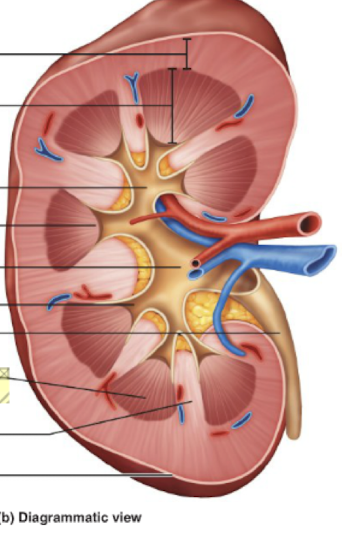
in retroperitoneal space

papillae→ minor calyces → major malyc → renal pelvis → ureter → bladder
Flow of urine
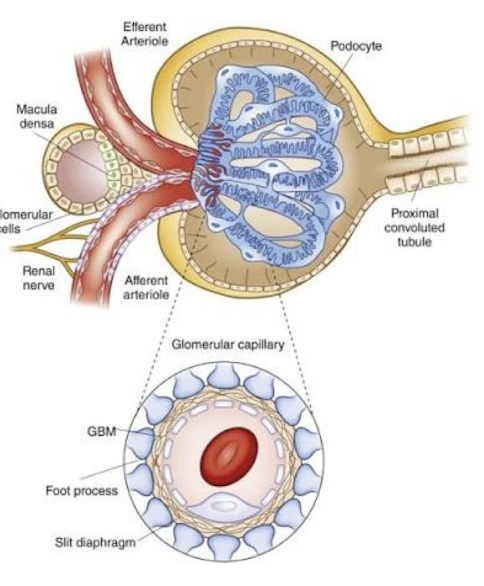
Afferent arteriole
small blood vessels in the kidneys that deliver blood directly into the glomerulus for filtration
They are larger in diameter
feed blood into the glomerulus, creating the high pressure needed to filter waste, water, and solutes
By constricting (narrowing) or dilating (widening), they control how much blood enters the capillary bed
Specialized cells in their walls monitor blood pressure and release renin to help regulate systemic blood pressure

Renal artery
Carries oxygen-rich blood from the heart (via the abdominal aorta) into the kidneys
deliver blood for filtration
Renal Vein
Carries filtered, deoxygenated blood away from the kidneys back toward the heart (via the inferior vena cava
Efferent arteriole
a small blood vessel that carries filtered blood away from the glomerulus in the kidney
It transports blood out and away from the glomerular capillaries after filtration has occurred
has a smaller diameter (lumen) which creates resistance and helps maintain high hydrostatic pressure inside the glomerulus for proper filtration.
By constricting or dilating, the efferent arteriole helps regulate the glomerular filtration rate (GFR) despite normal shifts in systemic blood pressure
After leaving the glomerulus, it splits again into a second capillary network—the peritubular capillaries or vasa recta—to supply blood to the renal tubules and aid in reabsorption before returning to general circulation

Acute Kidney Injury AKI
Rapid decrease in kidney function
Chronic kidney disease CKD
loss of kidney function over time, results from failure of the body to remove waste products
Either kidney damage or GFR <60 ml/min/1.73 m2 for 3mths or more
incidence continues to rise in US and world
25% starting dialysis die within the 1st year of treatment
Etiology
Diabetic nephropahty is MOST FREQUENT CAUSE OF CKD IN ESRD
hypertensive nephrosclerosis
Complication
Cardiovascular disease CVD
metabolic acidosis
chronic kidney disease- mineral and bone disorder CKD-MBD
ANemia
hyperkalemia
hypervolemia
uremia
Dignosis
blood and urine tests
additional lab tests
liver profile
thyroid function tests
electrolyte panel
imaging
KUB (kidneys, ureters, and bladder) x ray
renal ultrasound, arteriogram, CT, MRI
Treatments
anti-hypertensives
ACE/ARB meds
Lipid lowering agents
Statin therapy
Hemodialysis
removal of toxins and excess fluid from the blood
Peritoneal dialysis
removal of toxins and excess fluid by utilizing the peritoneum
Renal transplantation
encouraged in those who have the potential of a good quality of life after transplantation

End stage renal disease ESRD
occurs if CKD is not treated
results from failure of body to remove waste products
urine, acidosis, alkalosis
Urinary tract function
Elimination of waste products: without blood flow to kidneys, ____ output decreases
Acid-Base balance
bicarbonate acts as buffer to maintain acid base balance
In ___, kidneys reabsorb bicarbonate
In ___, kidneys excrete more bicarbonate

muscle detrusor, transitional
Urinary bladder composed of ____ and ___ epithelium
UTI
infection of lower urinary tract of bladder, upper urinary tract, or the kidney
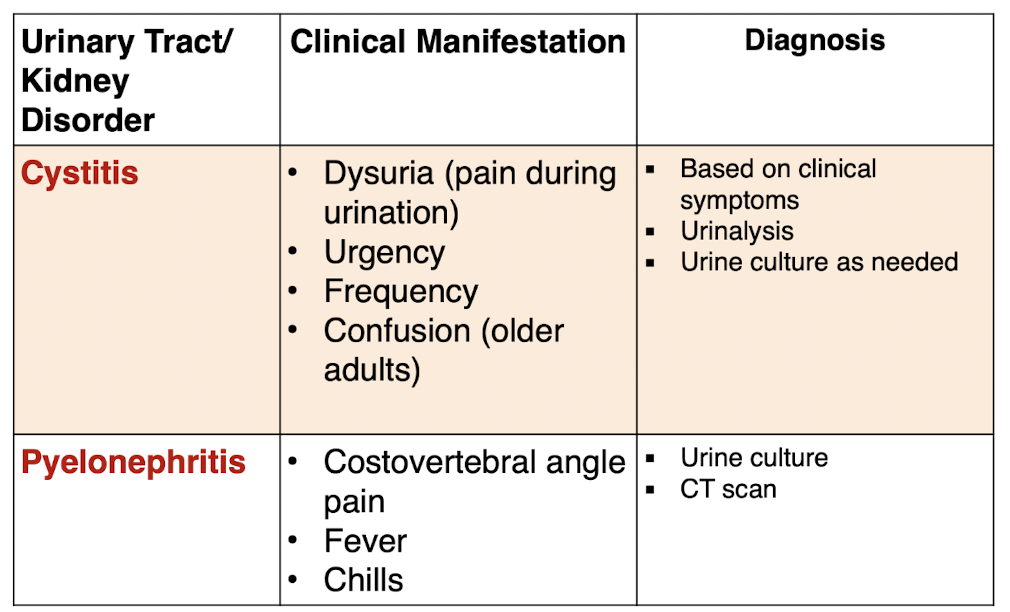
Cystitis
Infection of the bladder
most common bacterial infection
Risk factors
diabetes mellitus
familial predisposition
obstruction
neurogenic bladder
use of spermicides and diaphragms

Pyelonephritis
infection of the renal pelvis (pyelum) and parenchyma (essential functional tissue) of the kidney
Risk factors
female
sexually active
use of spermicides or diaphragm
pregnancy
genitourinary tract abnormalities
neurogenic bladder (loss of bladder control caused by nerve damage that disrupts signals between the brain and the urinary system)
immunosuppression
diabetes
Ascedning bacterial colonization from urethra to bladder
most caused by E coli
classifified as complicated or uncomplicated
Other causes
obstruction in flow of urine
stones
papillary necrosis
residual urine retention
bacteremia (____)
instrumentation
back flow of urine
vesicoureteral reflux (VUR) (a condition where urine flows backward from the bladder up into the ureters and toward the kidneys)

Glomerulonephritis (GN)
inflammation of the glomeruli and capillaries
characterized by mild proteinuria, hematuria, and edema
Etiology and pathogenesis
postinfectious
systemic disease
toxin exposure
thrombosis
genetic
Nephrotic syndrome
defined by heavy protein loss in the urine (>3.5 g/day) resulting in low blood blood protein and severe fluid retention/edema
Ex: post streptococcal glomerulonephrisits (immune complex)
Clinical Manifesations
hyperlipidemia
PROTEINURIA
hypoalbuminemia
edema
urinary fatty casts

Nephritic Syndrome
Involves inflammation of the kidney’s filters (glomeruli) which leads to blood in the urine (hematuria), high BP, and decreased kidney function
Clinical Manifestations
HEMATURIA
mild proteinuria
RBC casts/dysmorphic RBCs

Diabetic Nephropahty
CKD resulting from hyperglycemia
leading cause of end stage renal disease ESRD
proteinuria and hyperfiltration
Risk factors
poor glycemic control
uncontrolled hypertension
obesity
smoking
genetics
Race (More prevalant in African American, hispanci, american indian, and asian people)
Progression of disease
hyperglycemia—> polyuria —> increased renal blood flow —> glomerular hypertrophy —> glomerular hypertension —> hyperfiltration
Clinical Manifestations
Albuminuria
hyperfiltration
hypertension
Dignosis
renal biopsy may not be necessary
diabetes, HTN, and albuinuria leads to dignosis
Treatment
maintain BP <140/90
ACE inhibitors
ARBs
Blood cholestrol control
statins (prescription medications used to lower LDL (“bad”) cholesterol and reduce the risk of heart attacks and strokes)
Maintain A1C <7%
lifestyle modifications
Glucose lowering meds
MOST FREQUENT CAUSE OF CKD IN ESRD
moderate albuminuria= early indicator
Basement membrane thickening, mesangial expansion, increased glomerular permeability, decreased GFR

Renal Calculi Nephrolithiasis KIDNEY STONE
Results from formation or urinary crystals into larger stones
common obstruction (usually affecting white males)
Risk factors
previous stones
dehydration
hypercalcuria
hyperoxaluria (oxalate- nuts, spinach)
high sodium diet
Compostion of Calculi
majority are calcium based
less common: uric acid, struvite (magnesium ammonium phosphate), cysteine stones (amino acid cystine)
Stone Formation
damage to lining of urinary tract
crystal aggregation
slow urine flow to allow crystallization
excretion of large amounts of calcium
Clinical Manifestations
acute, unilateral flank pain
nausea
vomiting
sever pain that comes and goes (renal colic)
Diagnosis based on clinical symptoms, ultrasound, xray

GFR glomerular filtration rate
blood test that measures the level of waste products, primarily creatinine or cystatin C
measures how well your kidneys filter waste from your blood (higher number is better)

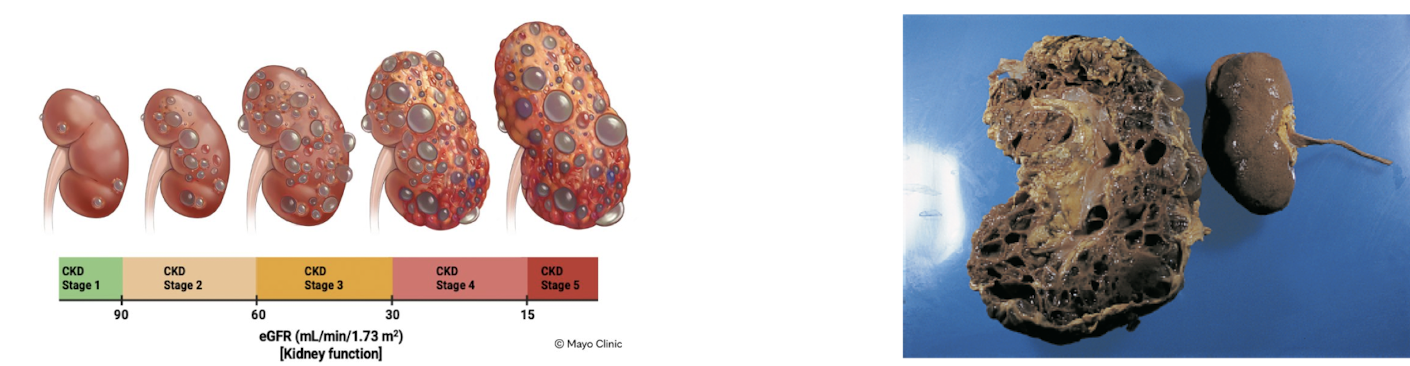
Polycystic Kidney Disease PKD
genetic disorder causing numerous fluid filled cysts to grow in kidneys, manifestation 30-50yrs
Cysts enlarge the kidneys and progressively reduce their function, often leading to kidney failure and high BP
Hypertensive Nephrosclerosis
chronic kidney damage caused by long-term high blood pressure that hardens, thickens, and narrows the small blood vessels inside the kidneys. This process reduces blood flow and oxygen to the kidney tissue, which can gradually lead to a loss of kidney function
increased pressure in glomerulus —> damage of glomerular cells —> glomerulosclerosis
Damage of small vessels in kidney —> inadequate blood supply —> dec BP to glomeruli —> glomerulosclerosis
Hyperfiltration —> thickening of glomerular vessels
Cardiovascular Disease CVD
Most common cause of death in CKD
HTN, dyslipidemia, and chronic inflammatory state
a group of conditions that affect the heart and blood vessels
Metabolic acidosis
In CKD, kidneys retain H+ ions
decreased kidney function leads to increased ammonia and retained H+ ions
Decreased kidney function decreases reabsorption of sodium bicarbonate NaHCO₃
Chronic kidney disease mineral and bone disorder CKD-MBD
systemic condition where failing kidneys disrupt the balance of minerals and hormones like calcium, phosphorus, parathyroid hormone (PTH), and vitamin D
bone disease in CKD resulting from mineral and hormonal changes
causes bone pain, deformities, and fractures
Results from abnormal bone turnover, hypocalcaemia, hyperphosphatemia, and hyperparathyoidism
Phosphorus buildup: Damaged kidneys fail to remove extra phosphorus, causing high blood levels (hyperphosphatemia).
Vitamin D failure: Kidneys stop converting vitamin D into its active form, which lowers calcium absorption from food.
High PTH (Secondary Hyperparathyroidism): Low calcium and high phosphorus trigger parathyroid glands to release excess PTH, pulling calcium out of the bones
Anemia
decreased erythropoietin EPO
worsens with worsening CKD
Leads to increased cardiac preload, decreased afterload, and increased cardiac output
Hyperkalemia
Develops as oliguria develops
results from decreased aldosterone secretion and decreased excretion of potassium
Damaged kidneys cannot effectively filter out extra potassium
Excess potassium stops the heart from resetting its electrical charge properly. This can lead to severe arrhythmias (irregular heartbeats) and, in extreme cases, cardiac arrest
Hypervolemia
once GFR fails, renal secretion of Na and H2O decreases
Exacerbates CVD and LVH (left vent. Hyp. thickening of the wall of the heart's main pumping chamber, called the left ventricle)
medical condition where your body holds too much fluid and sodium in the blood, also known as fluid overload
Uremia
Results from waste product acculmulation
serious, life-threatening medical condition that occurs when damaged or failing kidneys can no longer filter waste products properly, causing toxins like urea and creatinine to build up in the blood
Stages of CKD
Name this

Glomerulonephrosis
damage in the glomeruli
characterized by protein uria (hypoproteinemia) and edema
Etiology and pahtogenesis
diabetic nephropahty
lupus
minimal change diseases (kids)
allergies