GI/GU/Renal - Blueprint
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/160

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
161 Terms
esophagitis cause
#1: reflux
RF: obesity, pregnancy, high estrogen states, hiatal hernia
esophagitis findings
multiple areas of mucosal inflammation, ulcerations, esophageal rings/furrows/fibrosis → biopsy
meds that cause esophagitis
ABX (tetracycline, doxy, bactrim, clindamycin), NSAIDs, bisphosphonates, KCl, Vitamin C, Fe compounds
esophagitis sx
heartburn
retrosternal burning
odynophagia
dysphagia
WARNING SIGNS: positive fecal occult blood, weight loss, anemia
esophagitis dx
clinical
(if warning signs/fam hx → upper endoscopy)
esophagitis tx
depends on underlying cause
GERD: PPI (omeprazole) or H2 blocker
Candida: fluconazole
Eosinophilic: avoidance of food allergens
CMV: ganciclovir
HSV: acyclovir
After 8 weeks therapy a repeat upper endoscopy performed to re-evaluate mucosal response to treatment
esophageal spasm definition
Abnormal peristalsis → Impairment of inhibitory innervation, leading to both premature and rapidly propagated or simultaneous contractions in the distal esophagus during swallowing
esophageal spasm sx
weight loss
regurgitation, heartburn, chest pain
esophageal spasm dx
upper endoscopy w/ or w/o biopsy (if no radiation)
if normal → esophageal manometry (Elevated integrated relaxation pressure of esophogastric junction → achalasia identified)
barium swallow → “nutcracker” or “corkscrew” appearance
esophagitis tx
CCB monotherapy
→ + TCAs → + CCB
achalasia definition
degeneration of myenteric plexus ganglion cells in the esophageal wall (absence of peristalsis in esophagus and lack of lower esophageal sphincter to relax)
achalasia sx
dysphagia to solids AND liquids
dx for achalasia
esophageam manometry
( incomplete LES relaxation and absent peristalsis in the distal esophagus)
achalasia - tx
pneumatic dilation, surgical myotomy, POEM, botulinum injection
mallory weiss syndrome RF
drinking alc and FORCEFUL VOMITING → hematemesis (“coffee ground or blood”
mallory weiss syndrome dx
upper endoscopy
mallory weiss tx
acid suppression (PPI for everyone), endoscopic therapy (band ligation or thermal coagulation)
Hemodynamic instability (d/t significant GI bleeding) → fluid resuscitation + blood transfusion + PPI
Prognosis: generally heal rapidly, majority have spontaneous resolution
Esophageal Neoplasm RF
male sex, age 50-60, chronic GERD, tobacco and alcohol use, HPV infection, Barrett esophagus
(middle-lower esophagus)
Esophageal Neoplasm sx
progressive dysphagia to solid foods, weight loss, anorexia, iron
Esophageal Neoplasm initial + definitive
initial: barium esophagram
definitive: endoscopy with biopsy
Esophageal Neoplasm main type in US
adenocarcinoma - usually related to barett esophagus
(worldwide = SCC)
esophageal stricture most common cause
GERD
esophageal stricture dx
endoscopy UNLESS has sx of proximal esophageal lesion (surger, zenker) → barium esophagram first

Esophageal Varices cause
portal hypertension,
chronic liver disease,
portal vein thrombosis,
Budd-Chiari syndrome (hepatic vein thrombosis),
chronic alcohol use (in adults)
(sx similar to cirrhosis)

esophageal varices dx
upper endoscopy

esophageal varices tx
banding ligation**
ocreotide
prophylactic NON-SELECTIVE BB (and ceftrixone)
fluid resuscitation** (transfusion goal is 7)
definitive = liver transplant or transjugular shunt
esophageal perforation PE
pleuritic pain along esophagus,
worsens with neck flexion or swallowing,
mediastinal air surrounding heart could produce a systolic crunching sound (Hamman crunch)
, subcutaneous emphysema of the neck
Mackler Triad: lower chest pain, vomiting, and subcutaneous emphysema
esophageal perforation dx
CXR - nonspecific, pleural effusion, widened mediastinum
contrast studies - spillage of contrast
esophageal perforation tx*
IV, abx
surgery 9repar/esophagectomy)
asplenia complication*
INC susceptibility to infections (encapsulated bacteria)
→ N. meningitidis, H. influenzae type B, Strep. pneumoniae vaccines
MC of hiatal hernia
sliding
hiatal hernia description
stomach enters through diaphgramatic esophageal hiatus
RF: preg, muscle weakening, low fiber diet, obesity, ascies
sliding hiatal hernia
asymptomatic or gerd
paraesophageal hiatal hernia sx
epigastric pain,heartburn, dysphagia, regurgitation, postprandial pain or fullness, N/V, dysphagia, intermittent chest discomfort
dx for hiatal hernia*
upper endoscopy → retrocardiac air fluid level
hiatal hernia tx
tx of gerd or niseen fundoplication
→ incarceration hernia
GERD gold standard dx*
esophageal pH testing
gastroenteritis cause
viral pathogen (norovirus) or bacteria
gastroenteritis PE
abdominal tenderness w/o rigidity or rebound, fever, dehydration
Dehydration sx: dry mucous membranes, sunken eyes, decreased skin turgor, lethargy, tachycardia, low BP, weak radial pulses
warning stomach signs
bloody stool, weight loss, severe abdominal pain, symptoms lasting longer then 1 week recent hospitalization or abx use, pregnancy, age > 65, presence of comorbidities like DM or HIV, lab abnormalities in electrolyte or renal function, severe volume depletion and dehydration
gastroenteritis tx
self limited, supportive, avoid antidiarrheals
oral (or IV) hydration, probiotic
h pylor gastritis endoscopy finding
loss of normal rugae
→ urea breath testing
→ test 4 weeks again after tx
tx for h pylori
Bismuth subsalicylate, metronidazole, tetracycline, and PPI
charithromycin triple therapy for h pylori
Amoxicillin, clarithromycin, and PPI
gastric carcinoma RF
dietary factors* (e.g., salt-preserved foods, nitrites/nitroso compounds)
abdominal epigastric pain, dysphagia, virchows node, sister mary joseph node → ?
gastric carcinoma
increase the gastric acid secretion and inhibit mucosal prostaglandin production
h pylori and NSAIDs
which ulcer is alleviated by ingesting food?
duodenal ulcer (DUDe, give me food)
Gastrin-secreting tumor (gastrinoma), causes peptic ulcer disease that loves the first part of the duodenum
zollinger-ellison syndrome
elevated fasting serum gastrin level >1000 pg/mL = ?
zollinger-ellison syndrome → secretin stimulation test and upper endoscopy
assoc with MEN1
ecurrent bilious vomiting on 1st or 2nd day of life, double-bubble sign = ?
duodenal atresia
→ u/s or xr → duodenoduodenostomy
pyloric stenosis
2-8 weeks old
RF: macrolide
nonbilious projectile vomiting after feeding “hungry vomiter”
RUQ olvie mass, hypochloremic, hypoK metabolic alkalosis
target sign, string sign, shoulder sign, barium swallow
tx of pyloric stenosis
pyloromyotomy
cholelithiasis tx
NSAIDS
small + cholesterol = ursodiol
surgical = cholecystectomy
cholecystitis
obstruction by gallstone
positive murphy sign, boas sign
RUQ or epigastric pain after eating fatty foods
initial = u/s
gold standard = HIDA
tx = cholecystotomy
acute cholangitis
bdominal pain, jaundice, fever (Charcot triad)
Reynolds pentad (Charcot triad + hypotension and AMS)
RUQ U/S initial, ERCP = gold standard
cholangitis tx
hospital → zosyn (piperacillin-tazobactum)
TOC: endoscopic sphincterectomy with stone extraction
pancreatitis standard
MRCP
Classic triad for chronic pancreatitis
diabetes, steatorrhea, and calcifications on CT
infant colic
persistent crying for no reason
Wessel criteria: ≥ 3 hours/day, ≥ 3 days/week, ≥ 3 weeks duration, ≤ 3 months old
high risk of PPD, shaken baby sydnrome
self limited
tx for intussusception*
air/hydrostatic enema
malrotation complications
volvulus
duodenal obstruction
intestinal malrotation tx
ladd procedre
which vax recommended for celiac disease?
pneumoccocal vaccination
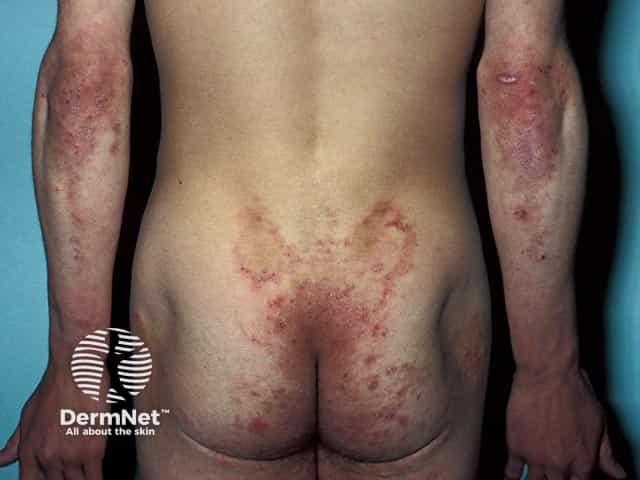
most common extraintestinal manifestation of celiacs?
dermatitis herpetiformis
constipation tx
lubiprostone
miralax/psyllium/osmotic laxatives
diarrhea tx
loperamide
cholestyramine
IBS 2nd aim of tx (relief of abnormal pain)
diet modifications
#1: antispasmodics (hyoscamine, dicyclomine
#2: antidepressants (TCA)
X-ray with dilated bowel, air-fluid levels, a stack of coins or string of pearls sign =
SBO
Hirschsprung Disease
Caused by failure of neural crest cells to migrate to the intestine
Absence of ganglion cells in the distal colon, leading to functional obstruction → no peristalsis so relaxation of anal sphincter
failure to pass meconium within 24-48 hours = ?
hirschsprung disease/CF
hirschspruing disease dx
rectal suction biopsy
empty rectal vault (loops of bowel without gas/stool in rectum) makes you think? + gold standard
hirschsprung disease
(rectal biopsy gold standard)
Meckel Diverticulum
< 5 years old
painless rectal bleeding, abdominal pain, or obstruction
diverticulitis dx*
CT with contrast
upper vs. lower GI bleed
upper: hematemesis, melena, hyperactive bowel sounds, high BUN/creat ratio
lower: hematochezia, normal bowel sounds and bun/cr
best test for upper GI bleed
EGD (esophagogastoduodenoscopy)
best test for lowe rGI bleed
colonoscopy
RLQ pain on extension of right hip, a/w retrocecal position
psoas sign
appendicitis imaging
adults = ct
peds/preg = U/S
preg w/ U/S not working = MRI
Indirect (unconjugated) Bilirubin
from breakdown of Hg
Elevated in hemolysis, Gilbert’s (impaired processing/conjugation)
Direct (conjugated) Bilirubin
Elevated when Liver has Processed the bilirubin but can't excrete it and it backs up into the blood.
Elevated in Cholestasis, obstruction, hepatocellular dysfunction
high AST/ALT is caused by
Acute Hepatitis, Alcoholic Liver Disease, Cirrhosis (AST >ALT)
high alk phos is seen in?
shows problems with the Bile Ducts but can be elevated in Bone disease as well.
Elevated in: Gallstones, Bile Duct Blockages, tumors, Cholangitis.
main cause of hepatic cirrhosis
chronic hepatitis C virus (HCV) infection secondary to IV heroin use
ALT > AST
_ is hallmark of acute infection of hep b
HBsAG (Hep. B surface antigen)
anti-HBs (Hep. B surface antibody)
persists for life, long term immunity
hep B vaccine
all adults aged 19–59 years
Portal hypertension
caput medusae, splenomegaly, ascites
Hepatic encephalopathy
asterixis, confusion, hyperreactive DTRs, insomnia, decerebrate posturing
cirrhosis tx
ascites → diuretics (spironolactone or furosemide)
hyponatremia → stop thiazides/BB/alpha blockers
hepatic encephalopathy → lactulose and rifampin
plt transfusion, stop PPI usage
Hepatocellular Carcinoma screening
abdominal (liver) U/S q6 months
positive AFP makes you think?
hepatocellular carcinoma
HFE gene mutation = ?
hemochromatosis
bronze colord skin
HIGH ferritin and transferrin
hemochromatosis diagnosis
MRI
hemachromatosis tx
phlebotomy
Serum bilirubin level that’s a/w jaundice → ≥ 3 mg/dL
gilbert syndrome (DEC UGT1A1 gene activity)
high indirect bilirubin but normal CBC (def = genetic testing)
hepatic encephalopathy
caused by lots of ammonium and toxic build up
→ confusion, bad sleep, scleral icterus, asterixis
tx for hepatic encephalopathy*
lactulose, rifaximin
campylobactor jejuni
bloody diarrhea and abdominal cramping, often acquired from consuming undercooked poultry or contaminated food and water