Sexual Differentiation
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/64

There's no tags or description
Looks like no tags are added yet.
65 Terms
What gene on the Y chromosome initiates male sexual differentiation?
SRY gene

What does the SRY gene produce?
Testis-determining factor (TDF)

What hormone is secreted by Sertoli cells?
Anti-Müllerian hormone (AMH) which triggers regression of wolffian ducts(paramesonephric)
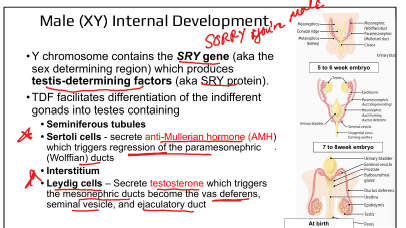
What is the function of anti Mullerian hormone?
Regression of Müllerian (paramesonephric) ducts

What hormone is secreted by Leydig cells?
Testosterone
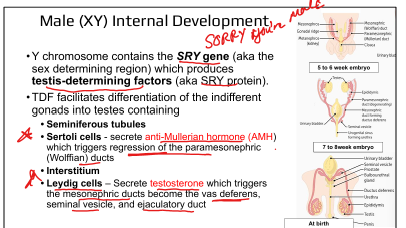
What is the function of fetal testosterone?
Development of Wolffian ducts into male internal genitalia (vas deferens, seminal vesicle, ejaculatory duct)

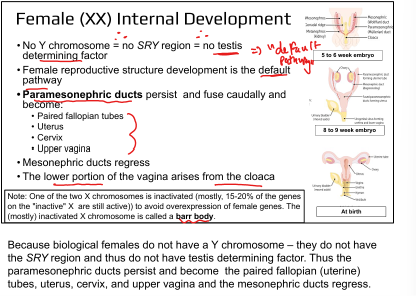
What female structures arise from the Müllerian (paramesonephric) ducts?
Fallopian tubes, uterus, cervix, upper vagina
What drives male external genital development?
Testosterone and DHT


What drives female external genital development?
Absence of testosterone and DHT


What enzyme converts testosterone into DHT?
5-alpha reductase
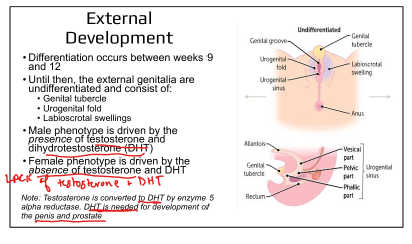
What is DHT required for?
Development of the penis and prostate

What is a Barr body?
An almost inactivated X chromosome (still has 15-20% of genes active)

Why do females have Barr bodies?
To prevent overexpression of X-linked genes
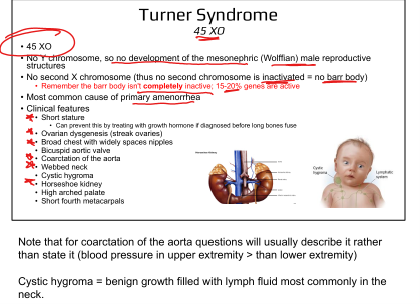
Are all genes on the Barr body inactive?
No, 15-20% remain active

What is the most common cause of primary amenorrhea?
Turner syndrome

What is the karyotype of Turner syndrome?
45,XO

What are the hallmark features of Turner syndrome?
Short stature, streak ovaries, primary amenorrhea, webbed neck

What ovarian abnormality is seen in Turner syndrome?
Ovarian dysgenesis (streak ovaries)

What chest finding is classic for Turner syndrome?
Broad chest with widely spaced nipples

What neck finding is classic for Turner syndrome?
Webbed neck

What renal abnormality is associated with Turner syndrome?
Horseshoe kidney

What cardiac abnormalities are associated with Turner syndrome?
Coarctation of the aorta and bicuspid aortic valve
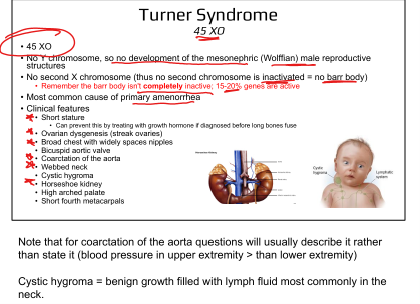
How can short stature in Turner syndrome be treated?
Growth hormone
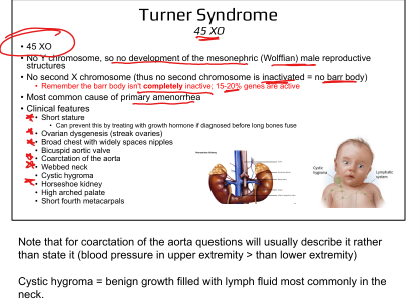
What are the hormonal findings in Turner syndrome?
High LH, high FSH, low estradiol

Why are LH and FSH elevated in Turner syndrome?
Ovarian failure causes loss of negative feedback

What hormone replacement is used in Turner syndrome?
Estrogen and progesterone

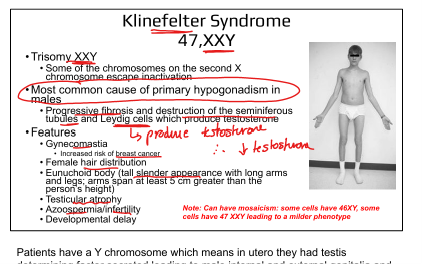
What is the most common cause of primary hypogonadism in males?
Klinefelter syndrome

What is the karyotype of Klinefelter syndrome?
47,XXY (FELT that eXtra chromosome)

What is the underlying pathology in Klinefelter syndrome?
Seminiferous tubule and Leydig cell degeneration causing inabilty to produce testosterone

What are the classic physical findings in Klinefelter syndrome?
NO testosterone: Tall stature, gynecomastia, small testes, infertility

What malignancy risk is increased in Klinefelter syndrome?
Breast cancer

What hair distribution is often seen in Klinefelter syndrome?
Sparse/female-pattern body hair (low testosterone)

What testicular finding occurs in Klinefelter syndrome?
Testicular atrophy (low testosterone)
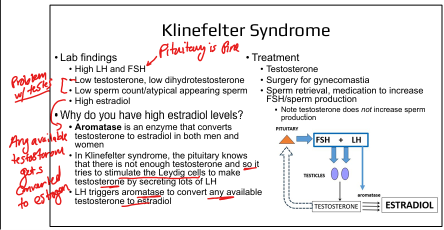
What are the hormonal findings in Klinefelter syndrome? (LH, FSH, testosterone, estradiol)
High LH, high FSH, low testosterone, high estradiol→because any small amount of testosterone gets converted to estradiol by aromatase

Why is estradiol increased in Klinefelter syndrome?
Increased aromatization of testosterone into estradiol

What enzyme converts testosterone to estradiol?
Aromatase

How is Klinefelter syndrome treated?
Testosterone replacement
What is the genotype of androgen insensitivity syndrome (AIS)?
46,XY

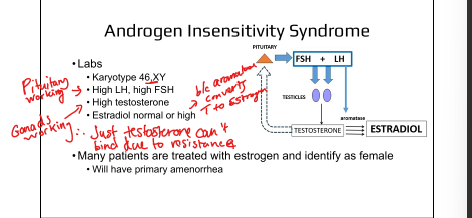
What is the underlying defect in Androgen Insensitivity Syndrome?
Androgen receptor mutation induces testosterone resistance»have testosterone present just can’t use it therefore have more female appearance

What happens to testosterone levels in Androgen Insensitivity Syndrome (AIS)?
Normal to high testosterone with resistance to its effects

Why do patients with Androgen Insensitivity Syndrome (AIS) have no uterus?
They are XY so anti Mullerian Hormone causes Müllerian duct regression

Why do patients with Androgen Insensitivity Syndrome (AIS) have female external genitalia?
Testosterone resistance prevents masculinization

What pubertal finding is classic in Androgen Insensitivity Syndrome (AIS)?
Primary amenorrhea

What genital tract finding is seen in Androgen Insensitivity Syndrome (AIS)?
Blind-ending vagina

What childhood history may suggest Androgen Insensitivity Syndrome (AIS)?
Inguinal hernias containing testes

What are the laboratory findings in Androgen Insensitivity Syndrome (AIS)? (karyotype, LH, FSH, testosterone, estradiol)
46,XY, high LH, high FSH, high testosterone, normal/high estradiol
What is the genotype of Müllerian agenesis?
46,XX

What is the underlying defect in Müllerian agenesis?
Absence/degeneration of Müllerian ducts»responsible for making upper vagina, uterus, cervix, and fallopian tube

Which structures are absent in Müllerian agenesis?
Uterus, cervix, upper vagina, fallopian tubes

Why do patients with Müllerian agenesis have normal breast development?
Normal ovarian estrogen production (because ovaries are derived from mesonephric duct)

Why do patients with Müllerian agenesis have pubic hair?
Normal androgen production because ovaries are intact

What is the typical presentation of Müllerian agenesis?
Primary amenorrhea with normal secondary sexual characteristics(still get sex hormone release because have ovaries) just dont have a uterus or cervix


How can Müllerian agenesis be distinguished from AIS?
Pubic hair is present and karyotype is 46,XX in mullerian agenesis because ovaries intact

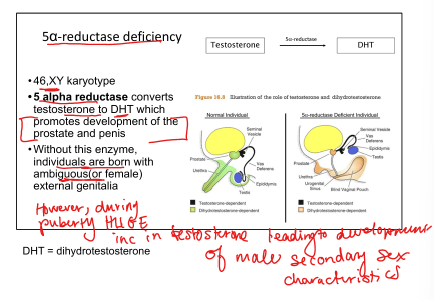
What is the genotype in 5-alpha reductase deficiency?
46,XY

What hormone cannot be produced in 5-alpha reductase deficiency? Leads to?
DHT. Without 5 alpha reductase you can’t convert testosterone to DHT which normally promotes development of the prostate and penis»therefore individuals born with this deficiency ten to have ambigious or female external genitalia BUT during puberty get large surge of testosterone leading to development of male secondary sex characteristics


What structures require DHT for development?
Penis and prostate

How do patients with 5-alpha reductase deficiency appear at birth?
Female or ambiguous external genitalia

What happens at puberty in 5-alpha reductase deficiency?
Masculinization occurs


What pubertal changes occur in 5-alpha reductase deficiency?
Voice deepening, pubic hair, growth spurt, penile enlargement

What finding distinguishes 5-alpha reductase deficiency from AIS?
Masculinization at puberty in 5 alpha reductase. AIS has testosterone resistance and little/no pubic hair

Turner syndrome (mut/cause, presentation, labs(LH,FSH,estradiol), tx)
Cause: 45,XO monosomy with gonadal dysgenesis |
Presentation: short stature, primary amenorrhea, webbed neck, broad chest, streak ovaries, horseshoe kidney, coarctation of aorta |
Labs: ↑LH, ↑FSH, ↓estradiol | Diagnosis: karyotype showing 45,XO |
Treatment: growth hormone, estrogen replacement, progesterone replacement, monitoring for cardiac and metabolic disease


Klinefelter syndrome (mut/cause, presentation, labs(LH,FSH, testosterone, estradiol), tx)
Cause: 47,XXY with seminiferous tubule and Leydig cell degeneration |
Presentation: tall stature, long limbs, gynecomastia, sparse body hair, small testes, infertility |
Labs: ↑LH, ↑FSH, ↓testosterone, ↑estradiol, low sperm count |
Diagnosis: 47,XXY karyotype | Treatment: testosterone replacement and fertility interventions


Androgen Insensitivity Syndrome (AIS) (mut/cause, presentation, labs(LH,FSH, testosterone, estradiol), tx)
Cause: androgen receptor mutation causing testosterone resistance |
Presentation: phenotypic female, primary amenorrhea, absent uterus/cervix, blind-ending vagina, absent pubic/axillary hair, history of inguinal testes |
Labs: 46,XY, ↑LH, ↑FSH, ↑testosterone, normal/↑estradiol |
Diagnosis: karyotype plus clinical findings |
Treatment: often estrogen therapy and management of undescended testes


Müllerian Agenesis (mut/cause, presentation, labs)
Cause: congenital absence of Müllerian ducts |
Presentation: primary amenorrhea, normal breasts, normal pubic hair, absent uterus and cervix
Labs: normal female hormones, 46,XX |
Diagnosis: pelvic imaging showing absent uterus with normal ovaries | Key distinguishing feature: normal pubic hair and normal ovaries


5-Alpha Reductase Deficiency (mut/cause, presentation, labs)
Cause: inability to convert testosterone to DHT
Presentation: 46,XY individual with female/ambiguous genitalia at birth and virilization at puberty |
Labs: 46,XY with impaired DHT production |
Diagnosis: clinical findings plus hormonal evaluation |
Treatment: individualized gender-affirming and reproductive management