Endocrine - Blueprint
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/94

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
95 Terms
diagnosis of DM
Patient is symptomatic and has a random BG ≥ 200
If asymptomatic:
Fasting BG ≥ 126 on more than one occasion
2 hour (75 g) OGTT plasma glucose value ≥ 200
A1c values ≥ 6.5%
type 1 DM tx
exogenous insulin - long acting first and short acting (i.e. regular insulin, NPH, lispro, glulisine, glargine, or detemir)
DM II tx*
metformin (biguanide) = INC peripheral sensitivity to insulin and low risk for hypoglycemia
thiazolidinediones (pioglitazone, rosiglitazone)
alpha-glucosidse inhibitors (acarbose)
lucagon-like peptide 1 (GLP1) receptor agonists (exenatide, liraglutide),
dipeptidyl peptidase 4 inhibitors (DPP4) (saxagliptin, sitagliptin),
and sodium-glucose cotransporter 2 inhibitors (SGLT2) (canagliflozin, empagliflozin).
metformin SE
diarrhea, abd cramp
vit B12 def
lactic acidosis
fruity smeling breath =
diabetes-related ketoacidosis
hyperglycemia, ketonemia, anion gap
diabetic-ketoacidosis tx
Tx precipitating cause
Correct volume depletion with NS, add dextrose to fluids once glucose is < 200 mg/dL
Replete potassium deficit (usually falsely elevated), do not start insulin if potassium < 3.3 mEq/L
IV insulin drip until anion gap closes
DKA is considered resolved when:
pH >7.3, serum bicarbonate is ≥ 18, glucose level is < 200
Hyperosmolar Hyperglycemic State
Glucose > 600
Minimal or NO ketonuria or ketonemia
Arterial pH > 7.3
Serum bicarb > 20
Altered LOC
Serum osmolality > 320
Resolution: normal serum osmolality, vital signs, and baseline mental status
vit A def
night vision loss, xerophthalmia, dry skin (xerosis), growth retardation, Bitot spots on the conjunctivae
bitot spots = collection of keratin in conjunctiva
vit b1 (thiamine) def
beriberi, Wernicke-Korsakoff syndrome, cardiac failure, heavy alcohol use, malnutrition
vit b2 (riboflavin) def
cheilosis, corneal vascularization (the two Cs of B2)
vitamin b3 (niacin) def
dermatitis, dementia, diarrhea, corn-based diet (pellagra)
vit b3 def (pellagra) tx
niacin supplementation
vitamin b6 (pridoxine) def
sideroblastic anemia, convulsions, peripheral neuropathy, INH use
b12 (cobalamin) def
megaloblastic anemia + neurological symptoms, hypersegmented neutrophils
vit c def
scurvy (↑ bleeding, anemia, loose teeth)
hemorrhage, hyperkaratosis, easy bruising
vit d def
rickets (children), osteomalacia, tetanyb12
vit d def dx + tx
dx = serum vit d <12
tx = >12 months vit d 50 mcg/2,000 IU
<12 months = 10 mcg daily vit d
vit e def
anemia, peripheral neuropathy, ataxia
vit k def
↑ bleeding, ↑ PT/INR, ↑ PTT if severe
folate def
megaloblastic anemia, sensory neuropathy
labs for rickets
↓ calcium, ↓ phosphorus, ↓ 25-hydroxyvitamin D, ↑ parathyroid hormone, ↑ alkaline phosphatase
tx for rickets
vitamin d/calcium supplements
if hereditary with LOW SERUM phosphate = calcitriol
wernicke encephalopathy is assoc with a def in _
thiamine
tx for wernicke encephalopathy and korsakoff syndrome
thiamine
korsakoff also gets magnesium
hypomagnesium causes
malnutrition (restricted diet or old)
chronic ppi
assoc with hypocalcemia and hypoK
what cardiac condition is hypomag assoc with
torsades
hypomagnesemia EKG
LONG qt interval
what risk if you correct hyponatremia too fast?
osmotic demyelination syndrome (centrla pontine myelinosis) → dysarthria, dysphagia, paralysis, death
hyperK risks
kidney failure
rhabdo
tumor lysis syndrome
hyperK sx
bradycardia, weakness, paralysis, cardiac dysrhythmia
peaked T waves**, prolonged PR< wide QRS, short QT, no p wave, sine wave
hyperK tx**
calcium gluconate
Causes of Hypercalcemia
VITAMINS TRAP Families
Vitamin A & D intoxication (hypervitaminosis A & D)
Immobilization
Thyrotoxicosis (increases bone resorption)
Addison's disease, Acromegaly
Milk alkali syndrome (too much tums), Medications (Lithium)
Inflammatory disorders
Neoplasm (lytic bone mets, MEN I, MEN IIa, multiple myeloma, Zollinger-Ellison Syndrome (gastronoma))
Sarcoidosis (granulomas/macrophages produce vit D-like substances)
Thiazide diuretics (will increase Ca2+ resorption)
Rhabdomylolysis (muscle break down; Ca released from sarcoplasmic reticulum)
AIDS (increased bone resorption)
Paget's disease, Parathyroid disease, Parental nutrition, Paraproteinemia, Pheochromocytoma, Paraneoplastic syndrome (tumor producing pth-rp [PTH-related peptide, e.g. squamous cell lung carcinoma - sCa++mous cell)
Familial hypocalciuric hypercalcemia – abnormal (low) set-point of calcium sensing receptors (CASR) in the parathyroid for PTH secretion. Benign; accompanied by ↑Mg++
causes of hypocalcemia
hypoparathyroid
vit D def
chvostek sign
facial muscle contraction
(hypocalcemia or hypoPTH)
trousseau sign
carpopedal spasm
(hypocalcemia or hypoPTH)
EKG of hypocalcemia (long)
prolonged QT interval
lab results for primary hyperparathyroidism
increased PTH, increased calcium, decreased phosphorous
→ parathyroidectomy
labs for hypoPTH
low PTH, low calcium, high phosphorus
tx for hypoparathyroidism
calcitriol and calcium
paroxysmal/episodic headaches, diaphoresis, palpitations, tremors, and vision changes with hypertension, tachycardia, orthostasis =
Pheochromocytoma
pheochromocytoma dx
24 hr urinary catecholamines and metanephrines (TOC if low risk), or ↑ plasma metanephrine levels (TOC if high risk)
pheochromocytoma tx*
Alpha-blocker** (phentolamine, phenoxybenzamine) prior to beta-blockade to prevent unopposed alpha-agonism
CCB
Surgical resection
main thyroid carcinoma
papillary
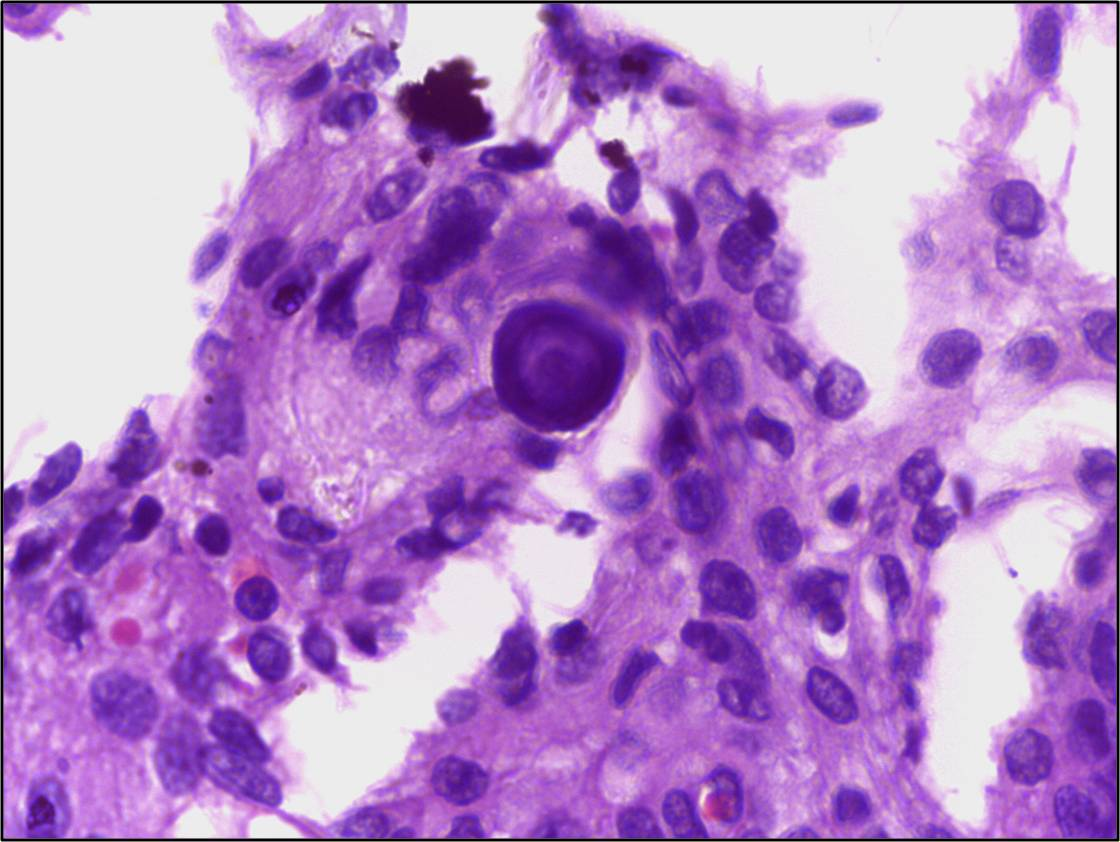
papillary thyroid carcinoma dx
fine needle aspiration → psammoma bodies
neuroendocrine tumor from parafollicular C cells (produces calcitonin), may be associated with MEN2
medullary
→ diarrhea, flushing
give calcitonin
thyroid carcinoma dx
U/S
final needle aspiration biopsy
blood work
if low TSH → thyroid scan
normal/high tsh → fine needle aspiration
Suspicious features on US: microcalcifications, irregular borders, hypOechoic regions, increased vascularity, taller than is wide, extrathyroid extension
tx for thyroid carcinoma
total or partial thyroidectomy and TSH suppression with levothyroxine (T4) replacement, or radioiodine therapy in certain pts
can → hypoCa and recurrent laryngeal nerve injury
hyperthyroidism tx*
methimazole or PTU (propylthiouracil)-preg
methimazole MOA
inhibits synthesis of T3 and T4 by blocking oxidation of iodine in thyroid gland
PTU MOA
nhibit the 5’-monodeiodinase that converts thyroxin (T4 - inactive) to triiodothyronine (T3 - active form) in extrathyroid tissue

graves disease findings
exophthalmos
goiter
tibial myxedema
diffusely INC radioactive iodine uptake
POS thyrotropin receptor stimulating antibodies
thyroid storm occurs in pts with
graves disease
Sx: hyperpyrexia, tachycardia, agitation, altered mental status
Tx: beta-blocker, thioamide, iodine, glucocorticoids
(low TSH and high T4)
primary hypothyroidism labs
elevated TSH and low T4
subclinical hypothyroidism labs
elevated TSH and normal T4
what lab to check with hypothyroidism?
TSH 6 weeks after initiating
if impaired T4→T3, may need liothyronine
congenital hypothyroidism
thyroid gland dysgenesis
head size inc d/t myxedema
large fontanels
hypotonio
prolonged physiologic jaundice
Prader Willi Syndrome
Most common syndromic form of obesity
Caused by absence of expression of the paternally active genes on lang arm of chromosome 15
Infancy → risk of neonatal hypotonia (risk of asphyxia), difficulty feeding, etc.
Late childhood and adolescence → premature pubic and axillary hair (early adrenarche), 2º sex characteristics delayed, menarche delayed, obesity, behavior problems
Adulthood → obesity, short stature, hypogonadism, osteoporosis, etc.
Acromegaly #1 cause
pituitary adenoma
Acromegaly tx
transsphenoidal resection of tumor
MC of pituitary adenoma
prolactinoma
cushing syndrome finding
purple striae
moon face (facial adipose)
buffalo hump (INC adipose tissue in neck and back)
HTN
cushing syndrome dx
HIGH 24 hour free urinary free cortisol
late night salivary cortisol (if cortisol is high)
low dose dexamethasone supp test (elevated cortisol and AM)
high ACTH → pituitary tumor → high dose dexamethasone test
low ACTH → adrenal tumor
cushing syndrome tx
ketoconazole
Most common noniatrogenic cause of cushing syndrome
hypercortisolism from ACTH_secreting pituitary tumor
Primary Adrenal Insufficiency (aka Addison Disease)
deficiency of cortisol and HIGH ACTH
fatigue
SALT CRAVING
hyperpigmentation
hypotension
addisons disease labs
hyponatremia, hyperK and hyperCa
serum ACTH and MSH HIGH
addisons dx
cosyntropin test
addison tx
primary = daily steroids (corticosteroid → hydrocortisone, mineralcorticoid replacement → fludrocortisone)
Zona Glomerulosa (outermost)
produces mineralocorticoids, i.e. aldosterone (salt)
Zona Fasciculata (middle)
produces glucocorticoids, i.e. cortisol,(sugar)
Zona Reticularis (innermost)
produces androgens, i.e. dehydroepiandrosterone and androstenedione (sex hormone)
screening for DM
fasting plasma glucose
glycated hemoglobin (A1C)
2 hour plasma glucose w/ oral glucose test (no common)
when is biguanides/metformin CI?
lactic acidosis
liver impairment
Cr >1.5
SGLT2 CI
GFR <45
TZD CI
III or IV heart failure
what laboratory value is associated with addisons?
DEC cortisol level
INC ACTH
DEC ADH level is assoc with
arginine vasopressin disorder (central DI)
thyroid sterm tx
BB!
can add PTU, steroid, and potassium iodide normally if ENDOGENOUS hyperthyroid, if exogenous only do BB
pt is on metformin and you want to add insulin. how?
continue PO med and add LONG ACTING insulin
prolactinoma suspected, next step?
treat with dopamine agonist (cabergoline, bromocriptine)
if that doesn’t work THEN → transsphenoidal surgical resection
incidental thyroid nodule found - what do you do FIRST?
TSH titer - if high → fine needle aspiratio biopsy, if low → radioactive iodine scan
Subacute thyroiditis
results from URI/viral
enlarged, painful thyroid gland.
sx like hyperthyroidism but eventually → hypothyroidism
tx - NSAID
toxic multinodular goiter
Plummer syndrome, is characterized by an enlarged, nontender, irregularly nodular thyroid gland
hyperthryoidism with NO exophthalmos
ANION GAP metabolic acidosis causes (MUDPILES)
methanol
uremia
DM ketoacidosis
propylene glycol
iron/isoniazid
lactic acidosis
ethylene glycol
salicylates
NON ANION gap metabolic acidosis
addisons
diarrhea
renal tubula necrosis
saline infusion
most common precipitating factor of thyroid storm (extra hyperthyroid)
infection
first step of hyperthyroidism management
block sympathetic activity (think about the HR) → BB for sx control!
A 29-year-old woman presents with dry eyes. Which of the following would indicate the need for testing for a systemic illness?
dry mouth
(sjogrens)
complete androgen insensitivity syndrome (AIS) (testicular feminization)
genetically male individuals appear female
terus absent
ntimüllerian hormone by the testes
At puberty, the diagnosis is suspected by the development of breasts but absent menstruation and sexual hair
gynecomastia, small testicles, infertility, mild delays, and a low upper-to-lower segment ratio
klinefelter syndrome (XXY)
mullerian agenesis
underdevelopment or absence of the uterus and the upper portion of the vagina in female individuals, while the ovaries and external genitalia are typically normal
breast buds, short stature, pedal edema, and widely spaced nipples
turner syndrome
(also have primary amenorrhea from streak ovaries and ovarian failrue)
sjogren syndrome tx
pilocarpine or cevimeline (to stimulate saliva)
Hyperaldosteronism (conn syndrome) labs (aka opposite of addisons)
resistant HTN
hypokalemia
hypernatremia
Metabolic alkalosis,
hypomanesium
dx = CT or MRI to look for adrenal adenoma
Treatment is with high-dose spironolactone or eplerenone (aldosterone antagonist)
you suspect addisons. what’s the FIRST lab you want to look at?
morning free cortisol level
(if low, THEN you can do cosyntropin stimulation test)