Ch. 7 Cholinoceptor-Activating & Cholinesterase-Inhibiting Drugs PART 1
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/56

There's no tags or description
Looks like no tags are added yet.
57 Terms
Cholinergic drugs
medications that increase or mimic the effects of acetylcholine (ACh), an important neurotransmitter
2 types of drug
Cholinergic drugs: Direct-acting agonists
Bind directly to acetylcholine receptors and activate them
Cholinergic drugs: Indirect-acting drugs
Inhibit acetylcholinesterase (AChE), preventing ACh breakdown and increasing available ACh
Acetylcholinesterase
breaks down acetylcholine, helping terminate its effects
Acetylcholine acts on two major receptor families
Muscarinic receptors and Nicotinic receptors
Muscarinic receptors
G protein-coupled receptor (GPCR) that activates intracellular signaling pathway to regulate organ activity
acts indirectly
Muscarinic receptors location
Heart, smooth muscle, glands, endothelium, nervous system
effects are parasympathomimetic
Nicotinic receptors
Ligand-gated ion channel that allows cations (Na) to move across membrane which produces rapid electrical excitation
acts directly
Nicotinic receptors location
Skeletal muscle, autonomic ganglia, CNS
five muscarinic receptor subtypes
Odd (M1, M3, M5) = Gq → increases intracellular Ca²⁺ and PKC
Even (M2, M4) = Gi/o → inhibits adenylyl cyclase, decreasing cAMP and PKA

parasympathetic nervous system
Muscarinic receptors are particularly important in this system
vagus nerve
releases acetylcholine onto M2 receptors in the sinoatrial (SA) node of the heart
M2 Receptors: How Acetylcholine Slows the Heart
3 mechanisms: Decreased sodium entry, Decreased calcium entry, and Increased potassium exit
Decreased sodium entry (mehcanism 1)
ACh binds M2 receptor (Gi/o) → Gαi inhibits adenylyl cyclase → less cAMP → less funny channel (IF) activity → less Na entry and slower SA node firing
decreased heart rate
Decreased calcium entry (mechanism 2)
M2 activation → ↓ cAMP → ↓ PKA → less Ca channel phosphorylation and reduced Ca entry → slower SA node activity
PKA normally phosphorylates Ca channels, increasing their activity
Increased potassium exit (Mechanism 3)
Activation of M2 also releases the Gβγ subunits → Gβγ subunits activate K channels (GIRK channels) → more K leave cell which makes inside more negative (hyperpolarization) → slower SA node to reach threshold for firing
Autoinhibition (negative feedback)
Released ACh binds to presynaptic muscarinic autoreceptors, which decrease further ACh release to prevent overstimulation
Nicotinic Receptors: Skeletal Muscle Contraction
Action potential → Ca²⁺ enters nerve terminal → ACh released → activates nicotinic receptors → Na⁺ enters (depolarization) → muscle action potential → Ca²⁺ released from muscle stores → skeletal muscle contraction
difference b/t nicotinic and muscarinic receptors
nicotinic receptor produce rapid excitation thru direct ion flow, muscarinic receptors produce effects thru G protein signaling pathway
skeletal muscle contractions depends on nicotinic receptors, not muscarinic receptors
Termination of ACh Signaling
Acetylcholinesterase (AChE) is the enzyme responsible for rapidly breaking down acetylcholine
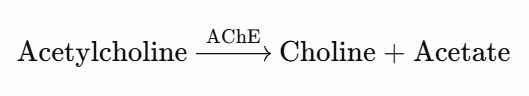
AChE inhibitors (Acetylcholinesterase )
prevent acetylcholine breakdown, allowing ACh to accumulate and prolong its effects
Nicotinic receptors Structure
made of five protein subunits arranged to form an ion channel
subunits are made of different combinations of alpha, beta, gamma, delta, or epsilon subunits
Nicotinic receptors locates
plasma membranes of postganglionic cells in all autonomic ganglia, of muscles innervated by somatic motor fibers, and of some central nervous system neurons
Mechanism of vasodilation
1.ACh binds M3 receptors (Gq) on endothelial cells.
2.Activates PLC → IP3 → ↑ Ca²⁺.
3.Ca²⁺ activates calmodulin, which stimulates nitric oxide (NO) production.
4.NO diffuses into vascular smooth muscle.
5.NO activates guanylyl cyclase → ↑ cGMP → activates PKG.
6.PKG causes smooth muscle relaxation → vasodilation
M3 activation on endothelial cells
causes NO (nitric oxide) release, which relaxes nearby vascular smooth muscle and dilates blood vessels
How Protein Kinase G (PKG) Cause Relaxation
activates myosin light-chain phosphatase (MLCP) → MLCP removes phosphate group from myosin which reduces muscles contraction → PKG decreases intracellular Ca
results in smooth muscle relaxation→vasodilation
Myosin light-chain kinase (MLCK)
Adds phosphate groups → promotes muscle contraction
Myosin light-chain phosphatase (MLCP)
Removes phosphate groups → promotes muscle relaxation
location of the M3 receptor determines its effect
On endothelial cells → indirect smooth muscle relaxation.
On vascular smooth muscle cells → direct smooth muscle contraction
Choline esters
acetylcholine-like compounds that activate cholinergic receptors
Muscarinic Receptor Locations and Signaling

the same M3 receptor can produce
different physiological effects depending on its location
ex Pupil constriction (miosis)

Overall Parasympathetic Effects
M2 receptors in the heart: Decrease cardiac activity and heart rate.
M3 receptors on vascular endothelium: Produce NO-mediated vasodilation
at the neuromuscular junction (NMJ)
acetylcholine (ACh) activates nicotinic receptors on skeletal muscle, producing muscle contraction
two autoimmune disorders that interfere w/ muscle contraction
Lambert-Eaton Myasthenic Syndrome (LEMS) and Myasthenia Gravis (MG)
Lambert-Eaton Myasthenic Syndrome (LEMS)
Autoantibodies attack presynaptic voltage-gated calcium (Ca²⁺) channels → decreases Ca entry into nerve terminal → less ACh released → less muscle contraction → muscle weakness
decreases Ca
Myasthenia Gravis (MG)
Autoantibodies attack postsynaptic nicotinic acetylcholine receptors → reduces receptors available → fewer receptors respond → decreases muscle contraction → muscle weakness
decreases receptor availability
2 ways to improve neuromuscular transmission
Acetylcholinesterase inhibitors and Potassium channel blockers
pyridostigmine
Acetylcholinesterase Inhibitor Drug w/ a duration of 4-6 hours
Glaucoma
involves damage to the optic nerve, often associated with increased intraocular pressure
acetylcholinesterase inhibitors can help improve drainage of fluid from the eye
Methacholine
Primarily activates muscarinic receptors, has minimal nicotinic activity, and addition of a methyl group increases muscarinic selectivity
Bethanechol
Primarily activates muscarinic receptors, has minimal nicotinic activity, and highly resistant to AChE breakdown, allowing longer-lasting effects
Cholinergic activation does not
always cause relaxation
Heart → decreased activity.
Blood vessels → relaxation through nitric oxide.
Lungs → bronchoconstriction.
Eye → muscle contraction.
2 groups of direct-acting cholinomimetic drugs (based on structure)
esters of choline (including acetylcholine)
alkaloids (such as muscarine and nicotine)
Four important choline esters
insoluble in lipids bc they have permanently charged quaternary ammonium group
poorly absorbed and poorly distributed
tertiary cholinomimetic alkaloids
sufficiently lipid-soluble to be absorbed across the skin
In the heart, M2 activation:
Opens K⁺ channels → K⁺ exits → hyperpolarization.
Decreases cAMP → reduces Na⁺ and Ca²⁺ channel activity → slower heart rate
Muscarinic agonists: eye (Pharmacodynamics)
activate M3 receptors → iris sphincter contracts → miosis(pupil constriction) → cilliary muscle contraction → accommodation (near vision)
Improved drainage reduces intraocular pressure
Muscarinic agonists: Cardiovascular system (Pharmacodynamics)
heart: M2 receptors→ decreases heart rate and AV node conduction
blood vessels: M3 receptors → smooth muscle relaxation and vasodilation
Muscarinic agonists: Respiratory system (Pharmacodynamics)
activate M3 receptors in the lungs → Cause bronchoconstriction (airway narrowing)
Muscarinic agonists: Gastrointestinal (GI) tract (Pharmacodynamics)
increase digestive activity, more GI motility and secretions
M3: Directly promotes smooth muscle contraction.
M2: Decreases cAMP and opposes smooth muscle relaxation
Muscarinic agonists: Urinary bladder (Pharmacodynamics)
promote urination by contracting the detrusor muscle (bladder wall) and relaxing the trigone and sphincter muscles
Muscarinic agonists: Secretory glands (Pharmacodynamics)
increases secretion from sweat glands, lacrimal glands (tears), and nasopharyngeal glands
Central Nervous System (CNS) (Pharmacodynamics)
Both muscarinic and nicotinic receptors are present in the CNS
α4β2
Important nicotinic subtype that is most abundant nicotinic receptor subtype in the brain; associated with nicotine addiction
important in autonomic ganglia
α7
Important nicotinic subtype that involved in cognition, pain perception, and potential anti-inflammatory effects
Prolonged nicotinic activation
initially causes muscle depolarization, prevents normal neuromuscular transmission, and eventually produces depolarizing blockade and flaccid paralysis