Ch.16 - Ischemic heart disease and conduction disorders
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/32

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
33 Terms
Heart layers + coronary arteries
epicardium - outer layer
myocardium - muscle layer
endocardium - lines interior layer
Left coronary artery common for MI
Exercise increases coronary collateral vessels AKA hypertrophy
Chambers of the heart
4 chambers
Right atrium: receives blood from superior and inferior vena cava and coronary sinus
Right ventricle: pumps blood into lungs via pulmonary artery
Left atrium: receives blood from pulmonary veins
Left ventricle: pumps blood to body via systemic arteries
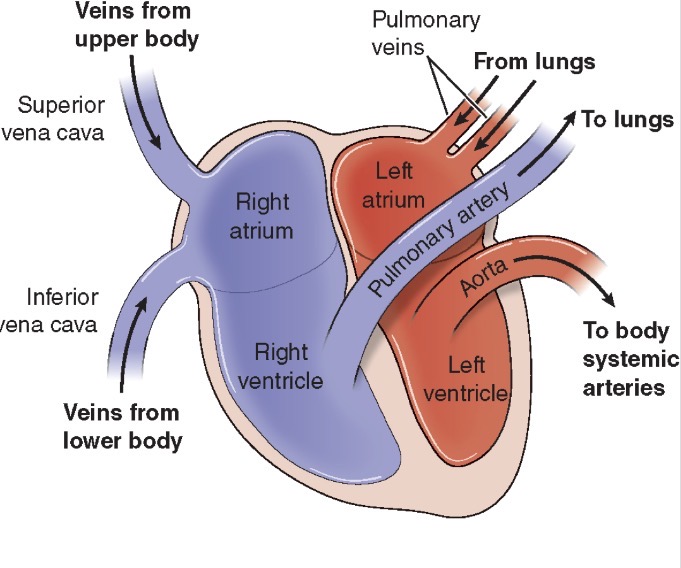
Pulmonary vs. Systemic circuit
Pulmonary circuit
low pressure system because only between heart and lungs
RV pumps deoxygenated blood to lungs, blood picks up oxygen in lungs, returns to LA
Systemic
high pressure system because entire body
LV pumps oxygenated blood to body, deoxygenated blood returns to RA
Conduction system
SA node (pacemaker) → AV node → Bundle of His → Bundle branches → Purkinje fibers
Cardiac cell action potential
Depolarization: sodium enters cell for electrical activation
Plateau: calcium enters the cell to trigger contraction
Repolarization: potassium exits the cell to reset electrically
Refractory period
There should be no contraction during this time so your heart can relax without being reactivated and fill with blood
absolute refractory period: cells cannot be re-stimulated
protects against fatal arrhythmias
Acute coronary syndrome
Sudden reduction of blood flow to heart muscle AKA myocardial ischemia
STEMI, NSTEMI - ischemia + infarction + troponin elevated
unstable angina - ischemia + no infarction + no troponin elevated

Angina pectoris
Chest pain
unstable angina is new, worsening, or unpredictable chest pain not relieved with rest, it IS a medical emergency
chronic stable is consistent, chronic pain relieved with rest/nitroglycerin
Prinzmetal’s: coronary artery spasm
microvascular angina
Unstable angina - risk factors
arteriosclerosis
smoking, diabetes, hypercholesterolemia, metabolic syndrome

Pathophysiology of unstable angina
Oxygen supply cannot meet oxygen demand of cardiac tissue
coronary flow reserve: ability of coronary blood flow to increase when the heart needs more oxygen (with narrowed/dysfunctional coronary arteries, they cannot increase blood flow enough)
can result in ischemia, that leads to lactic acid formation, contributing to angina
Coronary thrombus: blockage from atherosclerotic plaque
Prinzmetal’s angina: Coronary artery vasospasm → temporary narrowing → decreased blood flow → ischemia
Ischemia with no obstructive coronary artery (INOCA): microvascular angina without obstruction
Anemia: less oxygen delivered to myocardium → can result in angina
Signs and symptoms of unstable angina
crushing sensation on left side of chest
Levine’s sign: clenched fist over sternum
pain radiating to shoulder, jaw, down arm
pain initiated by exertion or stress
lasts 1-5 minutes
no change with alterations in position, respiration, or cough
Anginal equivalents - WOMEN
signs of MI for women differ from classic angina, which is why they are often missed AND treated less aggressively for possible MI than men
EX: dyspnea, feeling faint, epigastric pain, extreme fatigue
Diagnosis of unstable angina
blood lipids
blood pressure
ECG: ST elevation - not confirmatory
CRP
cardiac troponin - confirmatory test for MI because heart muscles release troponin when they die
chest X-ray to differentiate between cardiac vs. respiratory abnormality
calcium CT
cardiac angiogram - gold standard BUT risk of rupturing atherosclerotic plaque
noninvasive CT angiography - decreased risk of plaque rupture
graded exercise stress test to determine areas of injury
Treatment of unstable angina
education, modification of lifestyle risk factors
nitrates: vasodilators
aspirin: decrease platelet adherence
beta blockers: decrease myocardial oxygen demand
calcium antagonists: arteriole dilation
ACE inhibitors: decrease BP and resistance
MONA vs. THROMBINS2
Surgical and endovascular options for unstable angina
Percutaneous transluminal coronary angioplasty (PCTA)
angioplasty: inflated balloon pushes plaque against arterial wall
atherectomy: catheter with blade removes plaque
stent: maintains open vessel, antiplatelets (risk for bleeding)
Coronary artery bypass graft (CABG)
creates new routes around occlusions
saphenous vein of leg often used
x3, x4, x5 bypasses
traditionally cardiopulmonary heart pump used, but currently uses off pump procedures where heart still pumps during procedure
Chronic stable angina
Recurring episodes of chest pain
predictable pain relieved by rest and nitroglycerin
“inactive” atherosclerotic plaque
surgical treatment NOT an option
Prinzmetal’s angina - characteristics, diagnosis, treatment
vasospastic angina where coronary artery suddenly spasms, temporarily reducing blood flow
not associated with typical CAD risk, EXCEPT for smoking, inflammatory states (high CRP levels)
associated with migraines, Raynaud’s phenomenon
occurs at rest, think: charley’s horse in your arteries
diagnosis: 24 hour cardiac monitoring, coronary angiography, cardiac enzymes
treatment: nitrates, calcium channel blockers to help dilate and relax
Acute myocardial infarction
Prolonged cardiac tissue ischemia
irreversible damage due to atherosclerotic plaque, thrombus, increased myocardial demand
Factors that determines MI damage
location: determines which part of heart is damaged (EX: LV damage = decreases pumping ability = heart failure)
length of time: greater than 30 minutes of ischemia causes irreversible damage
collateral circulation: alternate blood vessels that provide blood/oxygen to ischemic area (more collateral circulation = less damage)
zone of injury: surrounds zone of ischemia where there are some recoverable cells
necrotic cells: release troponin
Reperfusion injury
Too fast reperfusion can be damaging
AKA myocardial stunning
Reperfusion injury may be due to oxidized free radicals generated by WBCs
MI signs and symptoms
SAME AS UNSTABLE ANGINA
also, sweating, nausea, anxiety, silent MI
anginal equivalents (women)
ECG diagnosis for MIs
ECG cannot confirm MI, can show location
STEMI: ST elevation MI; all the layers of the heart
NSTEMI: non-ST segment elevation MI; subendocardial and NOT completely through heart wall
Blood test diagnosis for MIs
CPK-MB: cardiac enzyme (creatine kinase)
rise within 4 hours of MI, peaks around 12-24 hours, subsides over 3 to 4 days
less specific than troponin
cTnI: cardiac troponin
rises 4-8 hours after myocardial injury, remains elevated for several days
GOLD STANDARD to diagnose because it shows cardiac tissue death
hs-cTnI: high sensitivity cardiac troponin assay
better at detecting early MIs
highly specific for cardiac muscle necrosis
GOLD STANDARD to diagnose acute MI
Treatment for MI
SAME AS UNSTABLE ANGINA
thrombolytic agents: breaks up clots
MI complications
post-MI dysrhythmias
risk greatest after MI
reentry - cause of dysrhythmias
electrically unstable conduction
impulses may reactivate already depolarized areas, causing dysrhythmias
papillary muscle rupture (helps keep AV valves closed during ventricular contraction)
if in LV, mitral valve is affected: mitral regurgitation, backup of blood into LA and pulm. pressure increases, dyspnea + crackles
thromboembolism
poorly contracting heart chambers cause stagnant blood, increasing risk for clot formation
ventricular aneurysm and rupture
pericarditis
occurs 2-3 days post-MI
pericardial friction rub, stabbing pain with inspiration
may occur as component of Dressler’s syndrome: hypersensitive reaction to tissue necrosis in MI
MI complications - heart failure
Left sided HF: LV damaged, fluid backs up into pulmonary circulation (lungs) leading to dyspnea, crackles, pulmonary edema, difficulty breathing, hypotension
Right sided HF: RV damaged, fluid backs up into systemic circulation (body/venous system) leading to jugular vein distention and peripheral edema - fluid accummulation
MI complications - cardiogenic shock
The heart cannot pump enough blood to meet the body’s needs
acute MI accounts for 81% of patients in cardiogenic shock
Ventricles fail to pump sufficient blood so BP drops, cardiac output drops, and poor perfusion of organs cause organ failure
Infectious endocarditis
Growth of bacteria (staphylococcus aureus) that damages heart valves
risk factors:
prosthetic valves, pacemakers, intravascular devices, IV drug usage because they introduce potential for bacteria to come in
pneumonia, polynephritis (infection of kidneys traveling to heart), dental procedures
Vegetation can develop on valve and break off and enter bloodstream (septic emboli)
Native valve endocarditis: Group A beta hemolytic streptococus (GABHS) from strep throat can trigger rheumatic fever which can damage the heart valves and increase risk of rheumatic valve disease
new or worsening heart murmur is important sign
Diagnosis and treatment of infectious endocarditis
Diagnosis: 3 blood cultures drawn 12 hours apart
echocardiographic findings
Treatment
antibiotics: IV 6 weeks or longer, pt at risk for c.diff
high dose oral and depot (slow release) antibiotics may be viable
blood cultures repeated daily until clear
persistent fever may be present despite antibiotic therapy due to paravulvular or extracardiac abscesses
surgical intervention
Myocarditis
AKA inflammatory cardiomyopathy = inflammation of heart muscle
mild to lethal disorder
common cause: viruses (influenza, herpesvirus, hepatitis)
autoimmune diseases, toxin exposure
symptoms: fever, myalgia (muscle pain), arthralgia (joint pain), palpitations
pericardial friction rub and S3 gallop (extra heart sounds) may be present
Myocarditis diagnosis and treatment
Diagnosis: CBC, ESR, CRP
cTnI may be elevated indicating myocardial damage
viral antibody titers should be measures
Treatment: reduce myocardial workload and treat underlying etiology
reduced activity for >6 months
treatments to support the heart: ACE inhibitors, inotropic agents (changes strength of heart’s contraction)
Pericarditis
Inflammation of pericardium and epicardium
pericardial effusion: excess fluid in pericardial tissue
cardiac tamponade: fluid accumulation begins to compress the heart
acute pericarditis: sudden inflemmation of pericardium; can mimic MI
Dressler’s syndrome: specific form of pericarditis after MI (immune-mediated reaction)
Pericarditis - presentation, diagnosis, treatment
Presents with chest pain, fever, pericardial friction rub that worsens with deep breathing
Beck triad: hypotension, visible jugular vein distention, muffled heart sounds
pulsus paradoxus: decrease in SBP by 10 mm Hg or more with inspiration as LV can’t fill normally
Diagnosis: echocardiogram, cardiac MRI
Treatment: depends on etiology