Selected endemic diseases
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/81

Earn XP
Description and Tags
Leptospirosis, salmonellosis and Malignant catarrhal fever
82 Terms
What is the distribution of leptospirosis?
worldwide
Who is affected by leptospirosis?
virtually all mammals
What is the causative agent of leptospirosis?
several pathogenic serovars leptospira
What are some descriptors of leptospira?
aerobic, gram negative spirochete, fastidious, slow growing, corkscrew like motility
What leptospira is cattle host adapted in USA and much of the world?
L. borgpetersenii serovar Hardjo type hardjo-bovis (HB)
What leptospira is cattle host adapted in the UK?
L. interrogans serovar Hardjo type hardjo-prajitno (HP)

What is this?
L. Hardjo
How is leptospirosis transmitted?
shed in bodily fluids - urine, milk, vaginal discharge, semen
chronic carriers
What is the epidemiology of leptospirosis?
penetrates mucous membranes (eye, nose, mouth, genital tract)
persists in the environment in moist conditions
chronic carriers - often asymptomatic, intermittent shedding, often seronegative/low titers
What is twice as likely as to contract leptospirosis than another?
open vs closed herd
What is four times as likely as to contract leptospirosis than another?
bulls vs AI
What is eight times as likely as to contract leptospirosis than another?
Cattle have access to waterways vs not
What is six times as likely as to contract leptospirosis than another?
Sheep cograze with cattle vs not
What is the pathogenesis of leptospirosis?
infection of non immune animals → bacteraemia → antibodies from day 5 → from day 7 limited to immunologically privileged sites
What are immunologically privileged sites when talking about leptospirosis?
brain, joines, kidney tubules from which shed into urine for 18 months, reproductive tract, seminal vesicles in bull, uterus/placenta/fetus in cow, multiples in fetus
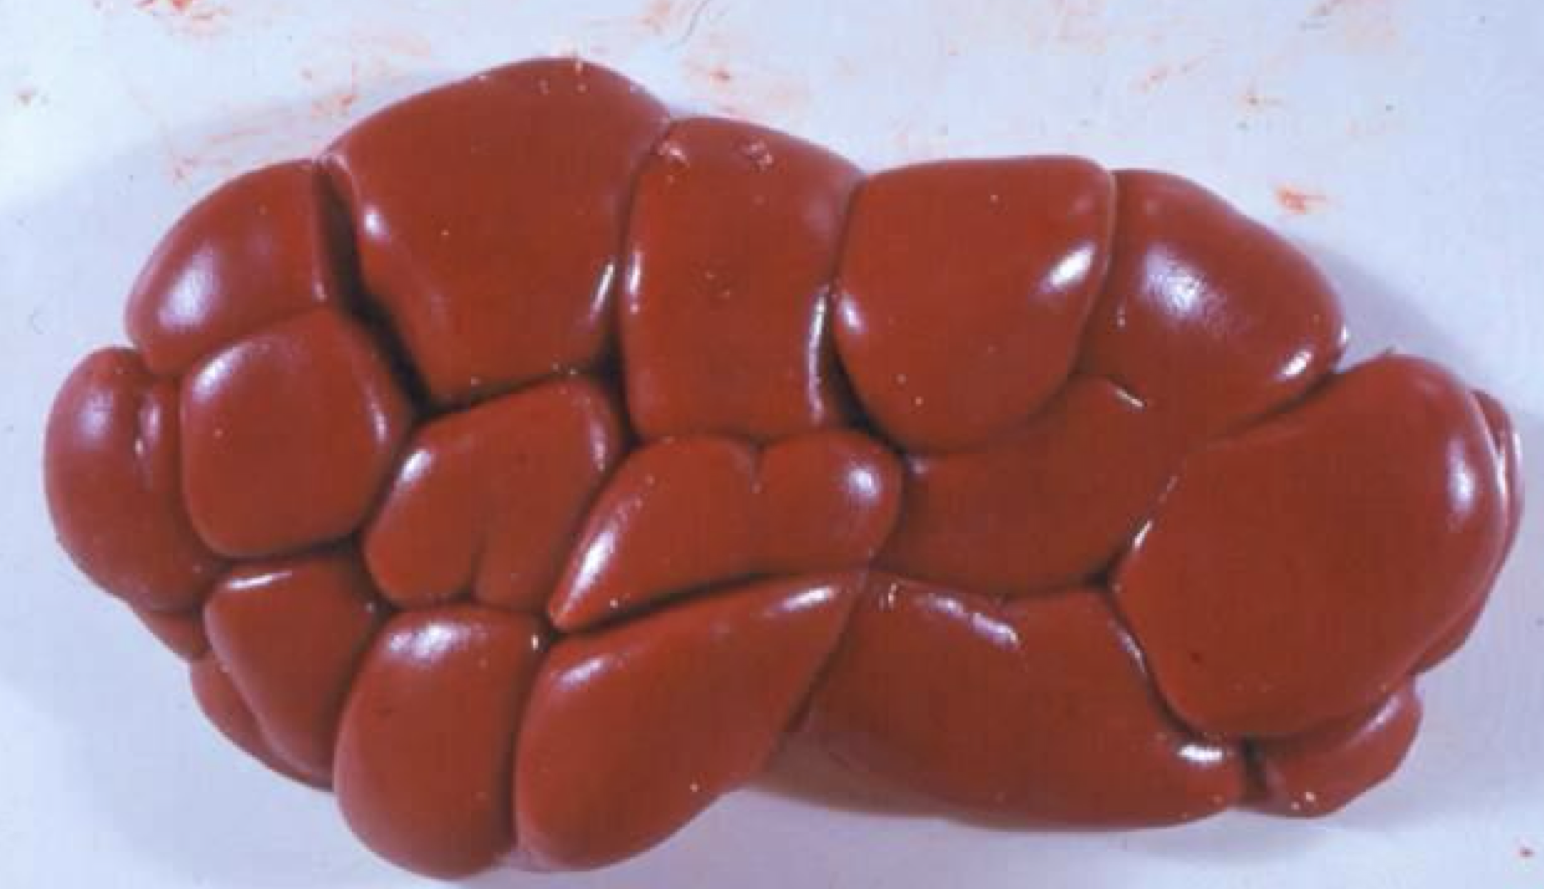
What disease does this kidney have?
kidney - leptospirosis

What disease does this placenta have?
placenta - leptospirosis
What clinical signs are associated with Leptospirosis acute phase?
subclinical (apart from lactating cows)
What clinical signs are associated with Leptospirosis?
reproductive disease- infertility, low conception rates, abortion, stillbirths, weak calves
milk drop
How does leptospirosis cause infertility?
in uterus causes infalmmation and embryo death
How does leptospirosis cause abortion?
6-12 weeks after infection, usually occurs last 3 months of gestation, tends to affect young cattle more frequently, live born calves are weak and unviable
How does leptospirosis cause millk drop syndrome or “flabby bag”?
sudden onset fever and agalactia, all four quarters of udder soft and flabby producing quantities of yellow/orange secretion which may contain small clothes, may affect >50% of cows at one time, milk have high leukocyte count (high SCC)
What are clinical signs of leptospirosis in calves under 2 months of age (rare)?
meningitis, anorexia, severe depression, opisthotonus, trismus, muscle tremors, paddling, pyrexia (40.5-41.5C), ophthalmitis, hypopyon, optic disc edema, congestion of retinal vessels
What are clinical signs of leptospirosis in calves over 2 months of age (rare)?
anorexia and dullness, rarely pallor, petechiation, jaundice, hemoglobinuria
How do you diagnose leptospirosis directly?
dark ground microscopy, culture and identification (difficult), PCR, immunofluorescence/peroxidase in tissue
How do you diagnose leptospirosis indirectly?
serology ELISA - blood or milk
What can make diagnosing leptospirosis difficult?
antibody levels rise at first and may be associated with clinical disease then they fall
abortion can take place with low levels of antibody (up to 12 weeks after infection)
antibody is present in the serum of carriers and vaccinated animals
How do you diagnose leptospirosis on a herd basis?
easily
serology - rising titer in paired sample taken 12 days apart, individual samples with tiers >1:100 indicated chronic or active infection
abortion - fetal serology, culture
bulk milk ELISA regularly used now
What is the aim of treatment for leptospirosis?
to reduce the number of infected animals (prevacc?)
to minimize urinary shedding
to reduce spread of organism to another cattle and other species including man
How do you treat leptospirosis?
Dihydrostreptomycin 25mg/kg (repeat after 7 days) - off data sheet - milk loss
also sensitive to - amoxycillin (15mg/kg), oxytetracycline (20mg/kg IM), tilmicosin (10mg/kg SC, if given to dry or pregnant cows, milk should not be used until 36 days after calving)
How do you control leptospirosis?
identification and removal of carrier animals
vaccination
test/treat/vaccinate replacements
hygiene with special attention to water supply
What dairy cattle do you want to vaccinate against leptospirosis?
close contact with workers, raise replacements separately therefore heifer are naive, complete vaccination course in heifers before breeding, spring booster
vaccine availability - issue with Leptavoid-H, farmers advised to boost with Spirovac
What beef cattle do you want to vaccinate against leptospirosis?
youngstock usually acquire some level of immunity
vaccine availability - issue with Leptavoid-H, farmers advised to boost with Spirovac
Who is affected by Salmonella?
wide range, various animals including humans
What’s an issue with salmonella?
serious economic, health and public health implications
can hide from immune system - carrier status - may or may not shed organism
What are the important causative agents of salmonella?
S. enterica Dublin
S. enterica Mbandaka
S. enterica Typhimurium
What clinical signs do you see with Salmonella Mbandaka in adults>
diarrhea and malaise, also abortion
Who is mostly affected by salmonella typhimurium?
calves
Why is salmonella typhimurium important?
on the increase? various clinical signs, carrier animals, periodic epidemics
Why is salmonella dublin important?
host adapted, latent or persistent carriers, associated with abortion, infrequent in humans but potentially fatal (infected livestock or unpasteruized milk)
Who is mostly affected by salmonella dublin?
both calves and adult cattle
By which route Salmonella transmitted?
feco-oral route
How is transmission of Salmonella important?
cattle to cattle - carrier status important (asymptomatic, may shed in times of stress), carriers can shed millions/day, neighboring herds, marts, shows, bulls
Where can salmonella survive and be transmited from?
slurry - persist in for months, soil for a year
fomites - visitors, animals, birds, vehicles, equipment
feed/water - contamination by other stock and wildlife
What is the prevalence of salmonella?
no one knows - no routine monitoring and need laboratory diagnosis
What are the risk factors for salmonella?
buying in cattle/cograzing, high stocking density, group pens, poor hygeien, concurrent disease (fluke/BVDV), season, age/stage
What age/stage of cattle are affected by salmonella most?
calves under 3 months, cattle in first 2 weeks of lactation
What are the clinical signs associated with salmonella?
acute or chronic enteritis, abortion, septicemia, reduced productivity, poor calf health
What are the issues with the clinical signs associated with salmonella?
range - may be overlooked/underdiagnosed
severity may depend on infective dose and age/stage
What is the presentation of acute enteritis with salmonella?
calves >2 weeks and adults
high fever, severe diarrhea, sometimes bloody, anorexia, colic, abortion
fatalities can be up to 75%
What is the presentation of chronic enteritis salmonella?
may follow acute enteritis
reduced weight gain, intermittent diarrhea, inappetence
stressors can trigger disease - poor nutrition, long transport times, calving, mixing, crowding
What is the presentation of septicemia salmonella?
mainly seen in neonatal calves (<2-3 weeks)
depression, fever, lethargy, labored breathing, nervous signs, rapid death (6-48 hrs)
dry gangrene of extremities after initial phase and joint infections
What is the presentation of abortion salmonella?
usually 5-8 months of pregnancy
± fever and anorexia
retained placenta and reduced lactation
abortion storms: up to 25% of herd
How do you diagnose individual clinical cases of salmonella?
fecal culture, PM, Serology
How do you do an individual fecal culture for salmonella?
fecal sample NOT swab
pooling decreases sensitivity
remember previous use of antibiotic will affect culture
How do you do an individual PM for salmonella?
culture a range of tissues
in abortions, culture fetal stomach contents
How do you do individual serology for salmonella?
best results in calves 3-10 months old
poor seroconversion <12 weeks old
cross reactivity
retrospective due to time take to seroconvert
How do you diagnose herd clinical cases of salmonella?
carrier animals, culture, serology
How do you do herd carrier animals for salmonella?
shedding may be intermittent
2 serology tests over 8 months?
How do you do herd culture for salmonella?
slurry samples or feces of cases
How do you do herd serology for salmonella?
bulk milk tank - good for continued monitoring (daily)
serology of all animals
serology of a subset of animals (calves, those showing clinical signs, 10 youngest calves over 12 weeks)
How do you treat salmonella?
early treatment is essential for septicemic __ - Dublin most sensitive
controversy regarding the use of antimicrobials for intestinal __ - carrier status
intestinal cases may cure clinically but not bacteriologically
How do you control salmonella in a negative herd?
prevent entry - bio-exclusion
How do you control salmonella in a positive herd?
biocontainment & biosecurity
What aspects of biosecurity can you use to control salmonella? (9)
maintain a closed herd or source new stock from high health status farms
quarantine all in-coming stock for at least 4 weeks
avoid shared equipment, bulls and grazing areas
maintain good fences
protect feed and bedding from vermin
use mains water (not natural source)
provide farm clothing for visitors or clean and disinfect boots/clothing before entering/leaving
investigate abortions, scour cases or other illnesses as early as possible
consider herd vaccination with Bovivac S (MSD)
What aspects of biocontainment can you use to control salmonella? (9)
segregate and treat clinical cases
all buildings should have good drainage and waste removal
clean and disinfect calving/maternity pens and buildings between occupancies
remove calf from dam asap
colostrum management
do not feed milk from ill cows to calves
only spread slurry on arable land
strict personal hygiene
**zoonotic risk - older and younger people → do not consume unpasteurized milk)
What are the vaccination options for control of salmonella?
Bovivac S (MSD) - only licensed option in bovine
protects against typhimurium and dublin
inactivated vaccine
What is the alternative name for Malignant Catarrhal fever?
Snotsiekte
What are the natural hosts for Malignant Catarrhal Fever?
Wildebeest and sheep (resulting in subclinical infection)
What are the dead end hosts for malignant catarrhal fever?
Cattle, other bovine species, deer, pigs
What is the causative agent of Malignant Catarrhal Fever in wildebeest?
Alcelaphine HV-1
What is the causative agent of Malignant Catarrhal Fever in sheep?
Ovine herpesvirus 2
What happens when cattle get MCF?
Severe systemic disease, latent forms are likely in those that recover
What is the epidemiology of Malignant Catarrhal Fever?
transmits efficiently between individuals of natural host, inefficiently accross species
Transmission is direct, aerosols, and may use intermediate hosts (flies)
Typically sporadic, multiple cases usually caused by close proximity of lambing ewes to housed cattle
When is Malignant Catarrhal Fever likely to reactivate?
Calving/lambing time
What are the clinical signs of Malignant Catarrhal Fever?
Extreme dullness, anorexia, agalactia, copious mucopurulent oculo-nasal discharge ± blood, drooling of saliva ropes, dyspnea and sterterous breathing, loss of condition
Pyrexia, congestion of scleral vessels, centripetal corneal edema, hypopyon, corneal neovascularization
Diffuse oral ulceration with pain extending onto the rhinarium
General lymphadenopathy +lymphocytsosis
Dermatitis, sweating, crusting lesions, cystitis ± pyuria, altered fecal consistency
Usually fatal (survive ~1 week)

What condition are we suspicious of in this case?
Malignant Catarrhal Fever
What is the typical pathology of Malignant Catarrhal Fever?
Lesions in virtually every system
Hydropic degeneration, vesicle formation and erosion in stratified squamous epithelium, ulcers coalesce and can become very extensive
Vasculitis, paracortical expansion in lymphoid tissues
How can we diagnose Malignant Catarrhal Fever?
Antibodies in serum or from affected tissues
OR
PCR for virus on tissue/whole blood
What are important differentials to exclude when considering mucosal diseases?
FMD, Bluetongue
What is the treatment for Malignant Catarrhal Fever?
Euthanasia
(supportive therapy possible)
How can we control potential infections/contact with Malignant Catarrhal Fever?
Avoid contact with sheep, esp during lambing time