Small animal bronchial dx
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/48

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
49 Terms
What cough receptors are present in larger vs medium airways? Where are they more numerous?
Mechanoreceptors – larger airways
Chemoreceptors – medium airways
More numerous in the URT (larynx, trachea, carina)
What are the Ddxs of coughing?
Compression of mainstem lobar bronchi
Stimulation of cough receptors (laryngeal, tracheal, bronchial disorders)
Foreign bodies
Excessive mucus / fluid / inflam (pneumonia, bronchopneumonia, pulmonary oedema)
usually soft / moist / ineffectual cough
What can cause compression of mainstem lobar bronchi?
Left atrial enlargement
Tracheobronchial / Bronchial LN enlargement
Neoplasia
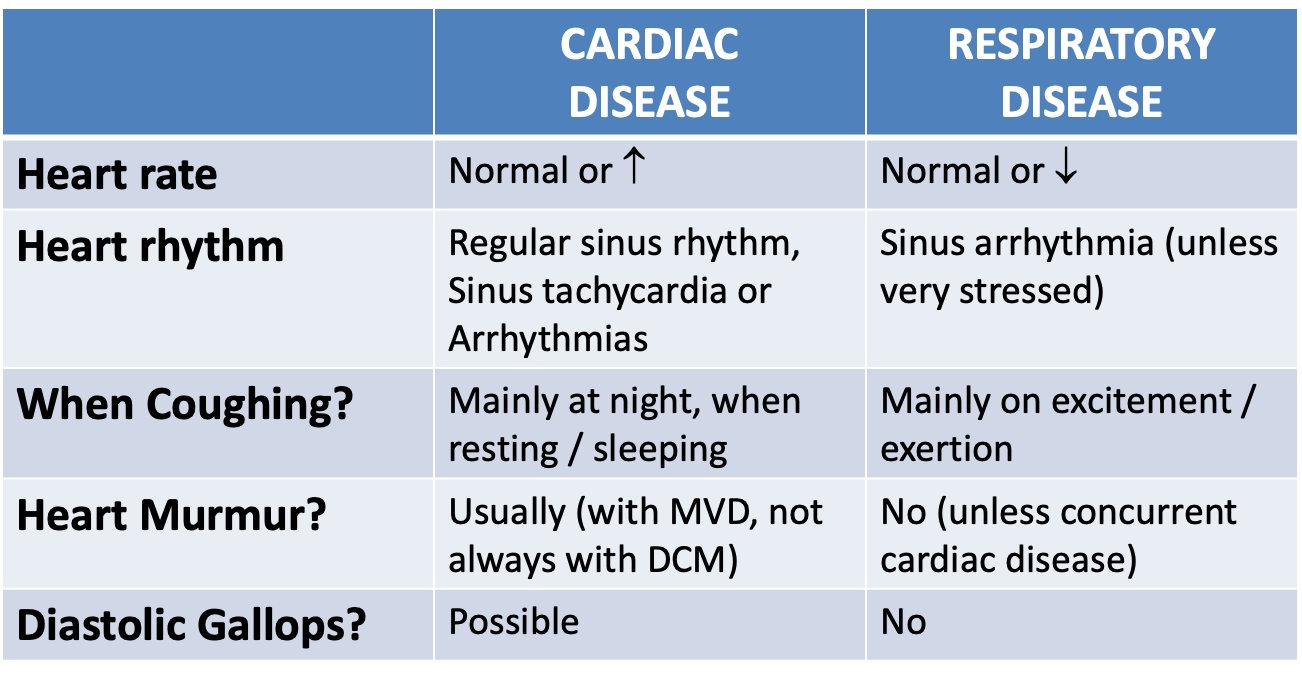
How do you differentiate between cardiac or respiratory disease in dogs?
What are the components of the hx needed to investigate a resp dx?
Environ
Worming history
Travel history
Recent events / illnesses / changes
Any other signs?
How long coughing?
Onset?
Description of the cough. When worse?
Is the cough really a cough?
Any change in voice?
e.g. laryngeal disorders
Does the dog sleep normally?
What are the components of the clin exam for a resp case?
Observe
change in breathing pattern / rate
dyspnoea?
spontaneous coughing?
Auscultate all lung areas during non-panting resp
crackles (normally on insp) caused by fluid/mucus
wheezes caused by bronchial narrowing (e.g. feline asthma / bronchomalacia)
Listen & palpate URT
Percussion of thorax
Thoracic compressibility (cats)
Attempt to induce cough (tracheal pinch)
auscultate following cough
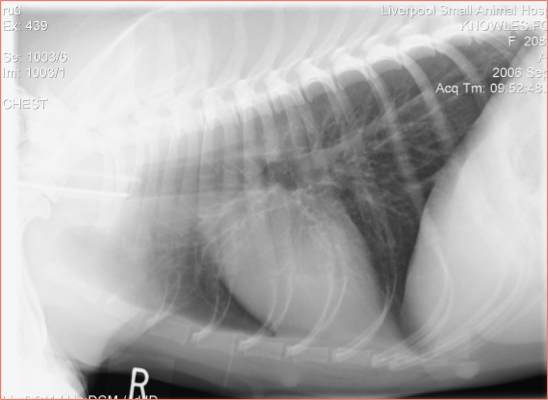
What changes are shown on Rx in chronic bronchitis?
Thickened bronchial walls
Donuts and tramlines

What is chronic bronchitis characterised by?
excessive mucus production
incr goblet cell numbers
hyperplasia of submucosal glands
damage to cilia
loss of ciliated ep
squamous metaplasia of mucosa
2° infections common
What is the aetiology of chronic bronchitis?
Aetiology often not known
Environmental factors
Previous infection
What is the typical presentation of a chronic bronchitis?
Typically small breed / toy breed dogs
Chronic cough with attempts @ production
Worse on excitement
What is the treatment goal of a chronic bronchitis case?
Manage as can't cure
Guarded prognosis bc most changes not reversible
What investigations are indicated in a suspected chronic bronchitis case?
Thoracic rads
Haematology
Bronchoscopy
BAL to obtain samples for cytology / bacteriology / parasitology
eosinophilia?
How is a bronchoscopy carried out and what should be seen on the sample?
Anaesthetised animal
Intubated —> bronchoscope passed down ET tube
Sample should be turbid, cellular & frothy —> alveoli sampled
What changes are seen on bronchoscopy?
Thickened mucosa, inc mucus, can't see vessels
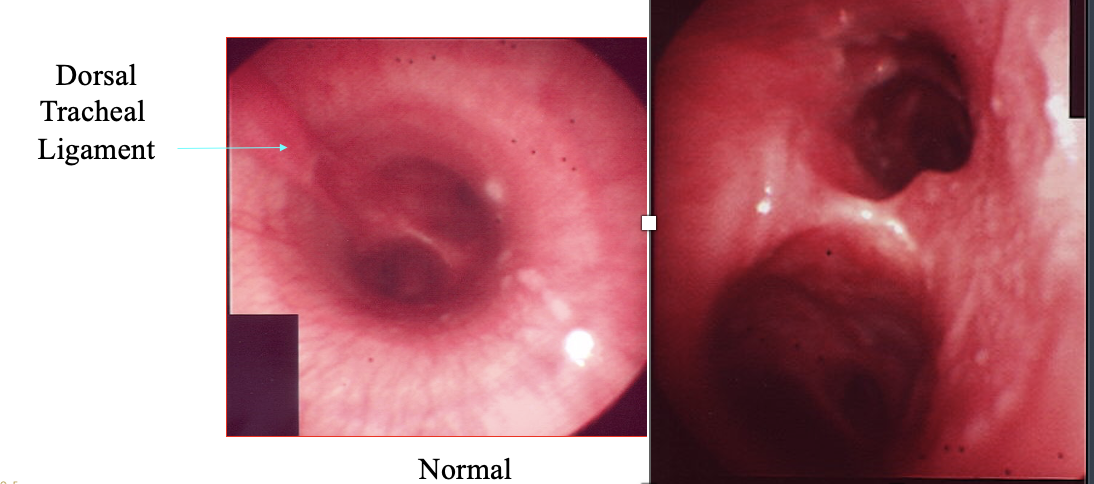
Right bronchus more obvious, left has more of an angle to get down in normal
What is bronchomalacia?
Bronchial collapse (regional to diffuse) w/ associated clinical signs due to airflow limitation
Can cause wheezy cough & may be 2° to other 1° resp conditions

List the respiratory parasites that may be causing a cough?
Oslerus osleri
Crenosoma vulpis (fox lung worm)
Aelurostrongylus abstrusus (cats)
Describe oslerus osleri infestation
No inter host
Direct transmission dog to dog, bitch to pups —> in resp excretions, regurg feeding, faeces (dirty environ)
How does oslerus osleri present on bronchoscopy?
Nodules at bifurcation
Worms 5-15mm long
May have associated airway collapse → cough & resp noise
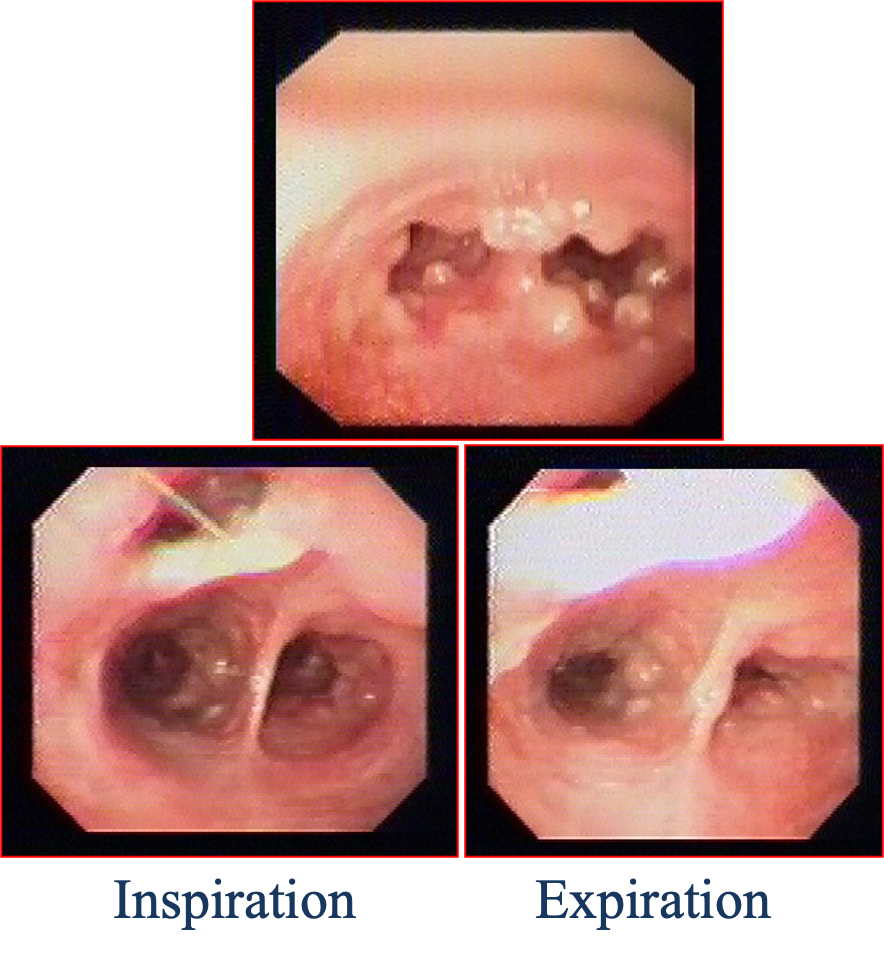

What could this be?
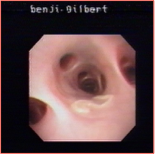
Crenosoma vulpis (fox lung worm)
Worms readily seen on tracheobronchoscopy (4-16mm)
Do not form nodules
What is the inter host of crenosoma vulpis?
Slugs / snails
How do you carry out a BAL?
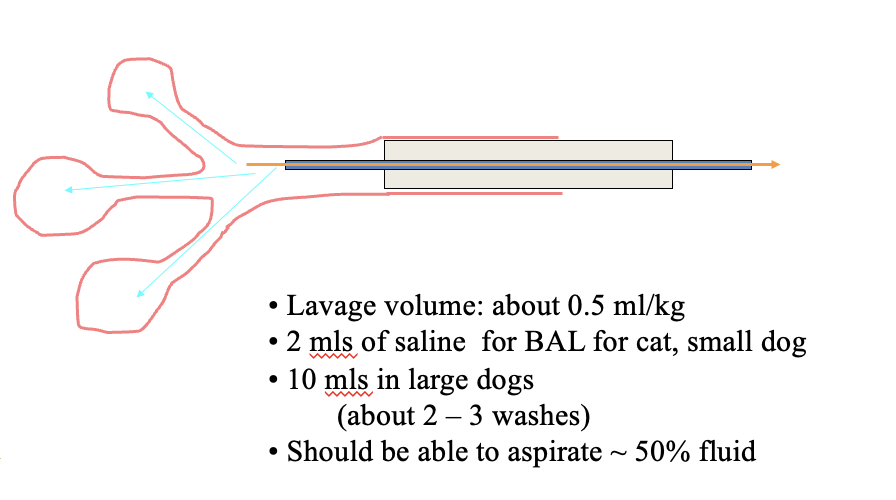
coupage sides of chest before aspirating fluid again
image first before carrying out BAL
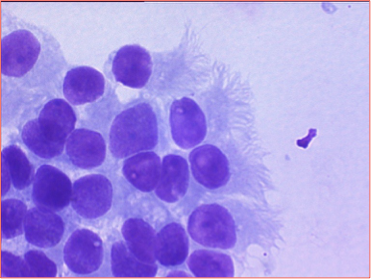
What would you see in normal BAL cytology?
Ciliated columnar epithelial cells (CCECs)
Goblet cells
Look at proportions of cells and if bacteria present esp. if phagocytosed
What are the normal BAL cytology values?
Normal total WBC < 5 x 10⁹/l
Macrophages (~ 70%)
Neutrophils (~20%)
Lymphocytes (~10%)
Eosinophils (<20 – 25%)
What is present on a BAL sample if there is oral contamination?
Simonsiella
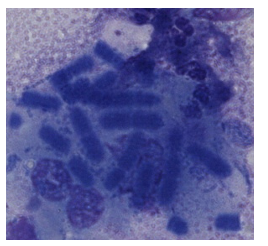
(non-pathogenic)
How does a BAL sample appear on cytology in a chronic bronchitis case?
Incr mucus ++
Incr neutrophils, macrophages
Possibly squamous metaplasia of normal ciliated columnar epithelial cells (CCECs)
Presence of bacteria / particulate matter
Culture normally -ve
What is important when obtaining a bacteriological culture for chronic bronchitis via BAL?
Culture normally -ve
Ensure sample obtained aseptically, avoiding contam from mouth / pharynx
How do you manage chronic bronchitis?
Weight control
Harness rather than collar / lead
Avoid irritants / smoking
Hydrate so excess mucus is easier to shift
Avoid very dry environs
Nebuliser (dogs only)
Spend time in bathroom during owners shower/ bath
How is chronic bronchitis treated?
Bronchodilators
Anti-inflam glucocorticoids (steroids)
+/- Anti-tussives
What do bronchodilators do?
Reduce spasm of lower airways
Reduce intra-thoracic pressures
Reduce tendency of larger airways to collapse
Improve diaphragmatic function
Improves muco-ciliary clearance
Inhibit mast cell degranulation (reduced release of mediators of bronchoconstriction)
Prevent microvascular leakage
Give an example of bronchodilators you can use for chronic bronchitis
Theophylline (dogs)
Terbutaline (not licensed for dogs or cats)
What are the effects of glucocorticoids?
Broncho-dilatory
Anti-inflam
Inhibit both prostaglandin & leukotriene synthesis
Potentiate beta-2 adrenergic activity
Reduce leukocyte accumulation
Induce lymphopenia & eosinopenia
Reverse increased vascular permeability
Alter macrophage function
Inhibit fibroblast growth
Modulate the immune system
When are ABs indicated for resp dx?
If C&S results +ve or if intracellular bacteria seen on BAL cytology
Can consider tx trial (e.g. doxy in case of mycoplasma)
If sterile NO ABs
What can you add to your tx plan for chronic bronchitis if mucociliary clearance is compromised?
Mucolytic —> e.g. Bromhexine
What can be used as an anti tussive?
Codeine phosphate
Diphenoxylate (has atropine so not used if additional heart dx)
Better to treat cause rather than suppress but consider for airway collapse if impacting on quality of life
What is being shown here?
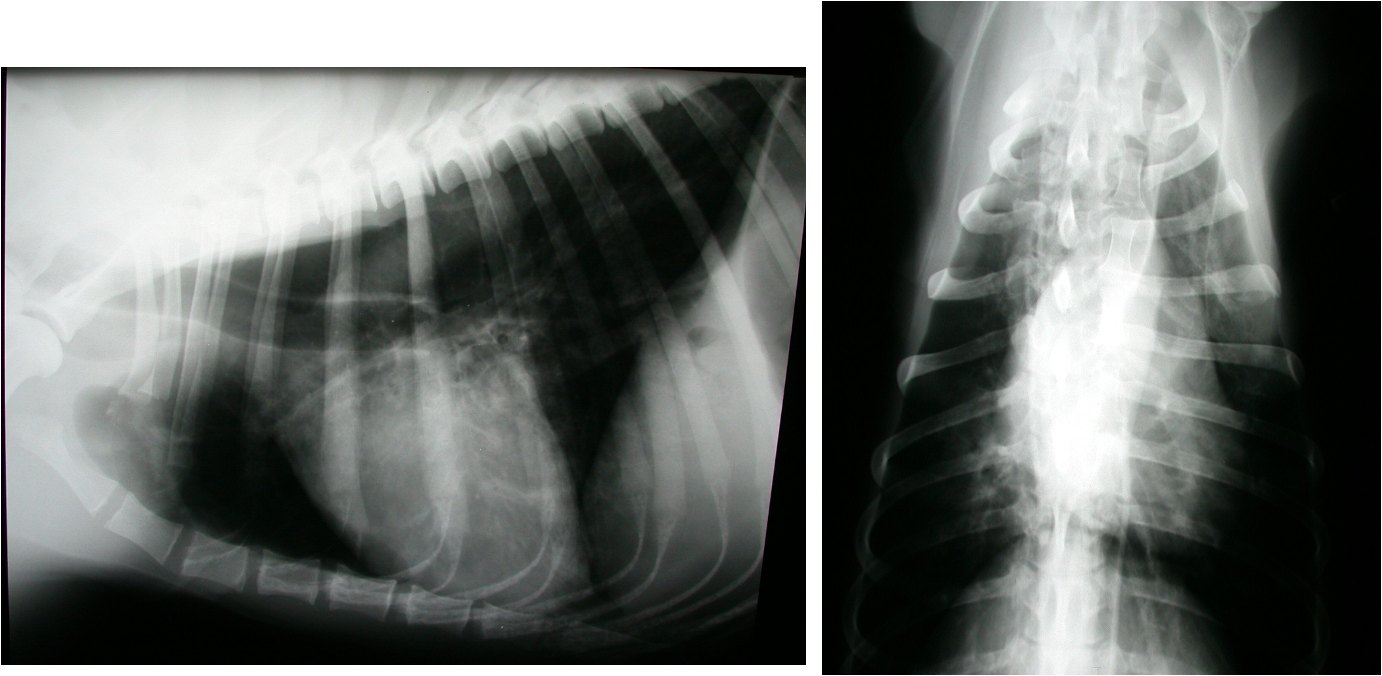
Bronchopneumonia caused by aspiration pneumonia w/ Mega-oesophagus
(Myasthenia gravis —> neuromuscular)
What is being shown here?
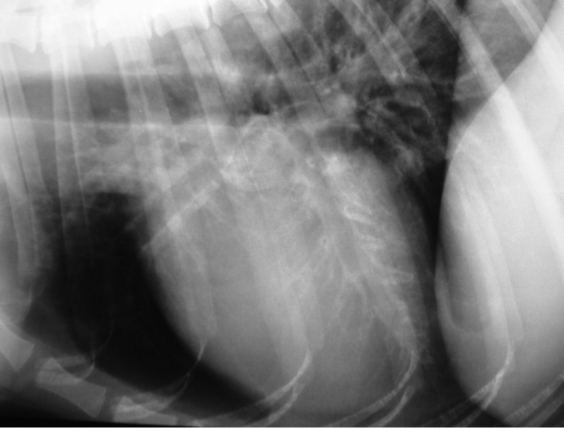
Bronchiectasis (thickened bronchi) —> can be end stage of any of the bronchial diseases
compromised mucocillary clearance → risk of 2° infection
What needs to be considered when choosing an AB for resp dx?
Should be bacteriocidal & needs to be effective against resp pathogens
Need to treat for long enough (2 wks min)
Give examples of an AB you would use for resp infections
Doxycyline —> if confirmed or suspected Mycoplasma or Bordetella
Clavulonate —> potentiated amoxycillin (broad spec)
Cephalexin —> gram -ve
Fluroquinolones —> broad spc
Clindamycin —> gram +ve & anaerobes
Metronidazole —> anaerobic
Use a combination if life threatening pneumonia/ bronchopneumonia
What is eosinophilic lung disease (ELD)?
Spectrum of dx from “chronic bronchitis” to pulmonary granulomatous disease
Usually mixture of bronchial & interstitial pulmonary involvement
Usually young dogs, large breeds
Presumed hypersensitivity to inhaled allergens (or parasites e.g. migrating Toxocara canis)
How does ELD usually present on bronchoscopy?
Typically copious amounts of yellow-green mucus

What value is diagnostic for cytology of ELD?
over 25% eosinophils
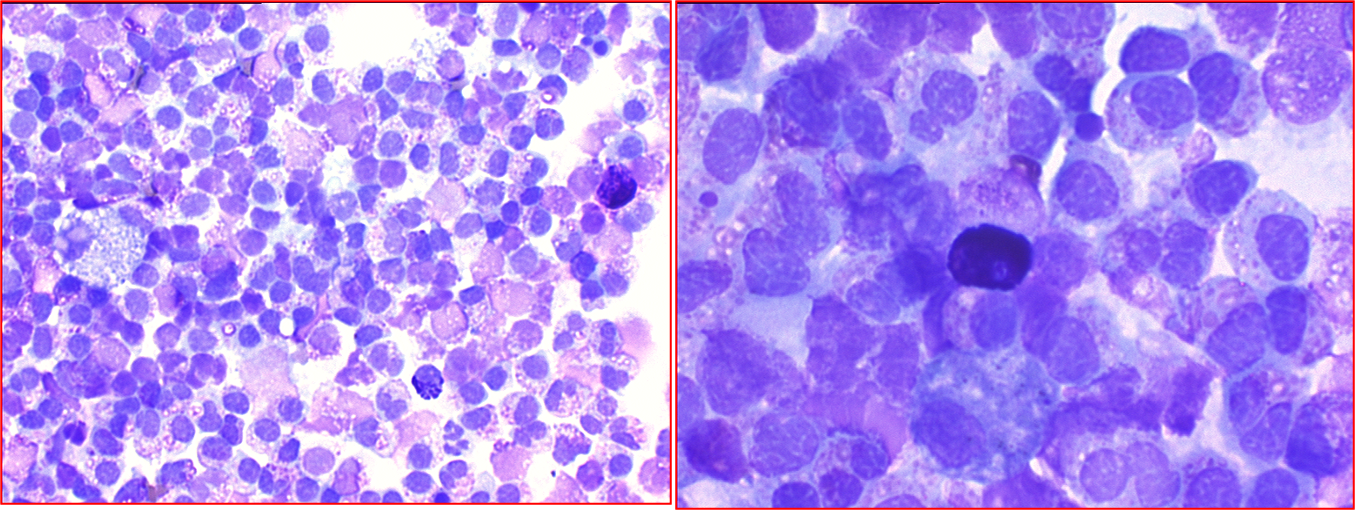
How is ELD treated?
Prednisolone (2mg/kg/day then slowly tapered once clinical signs controlled)
(remember to rule out parasites first)
can consider addition of other immuno-supp agents e.g. azothioprine
What is the most common cause of a cough in cats?
Inflammatory airway disease (IAD)
(also called Allergic Airway Disease or Allergic Bronchitis)
How does feline asthma present?
Cough
Can also have bronchoconstriction
→ air trapping & dyspnoea
→ expiratory dyspnoea
Can have exp. wheezes on ausc.
How does feline asthma present on rads?
Inc bronchial marking (donuts, tramlines)
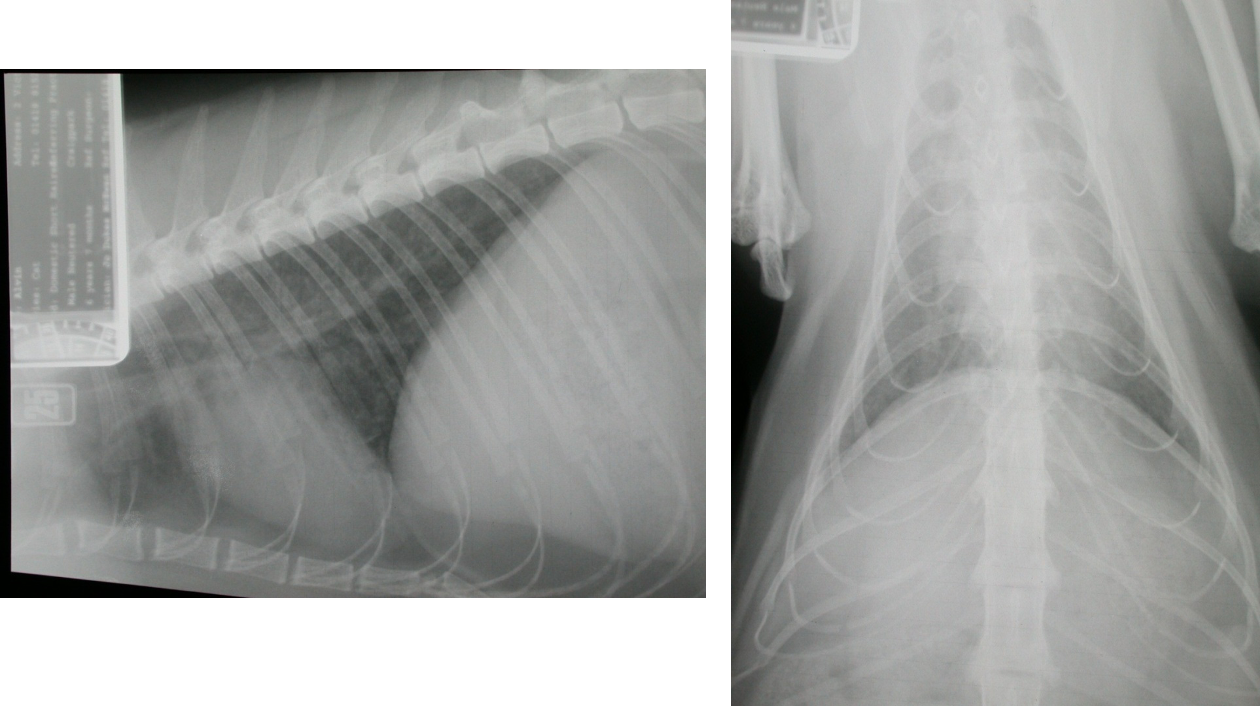
If air trapping —> diaphragm flattened, barrel chest on DV view
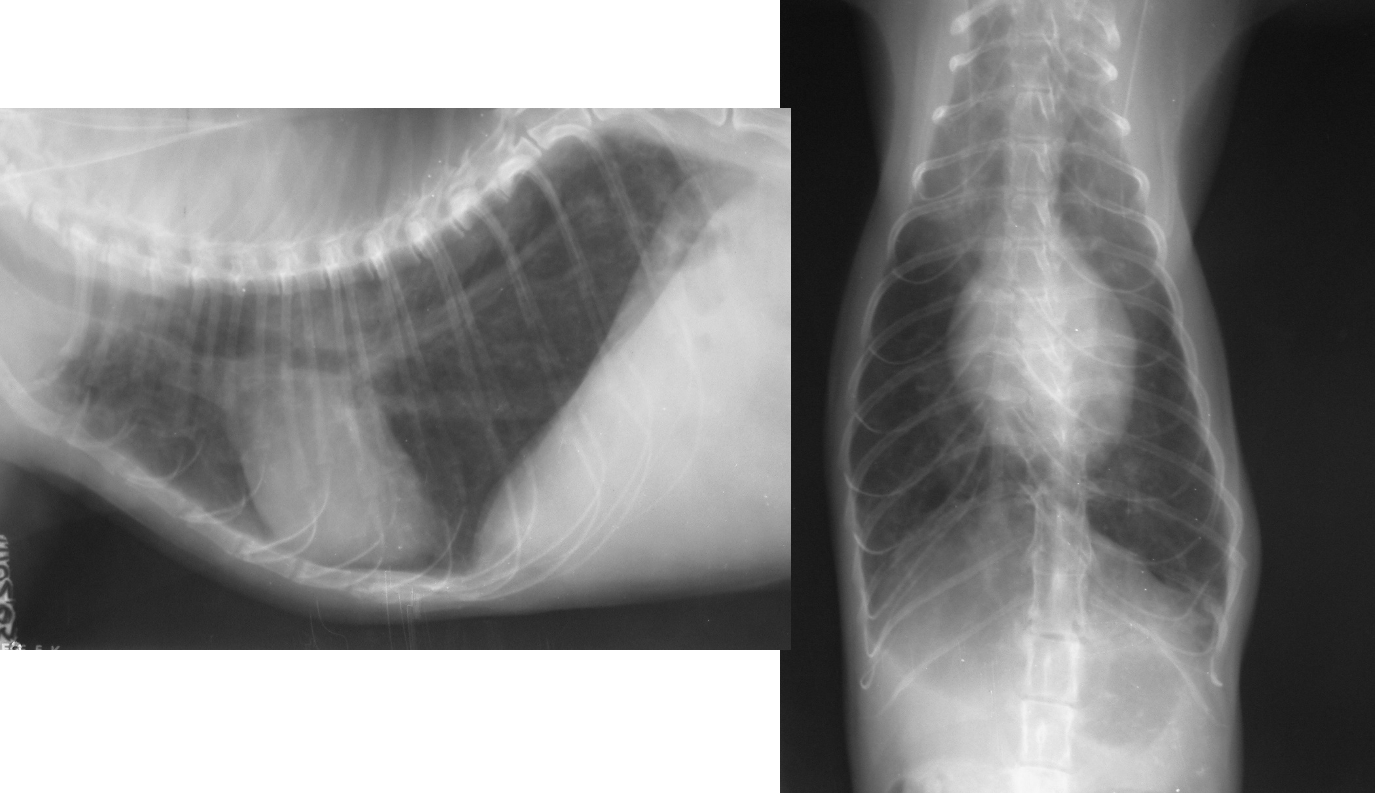
How do you treat a dyspnoeic cat with feline asthma?
Minimise stress
Provide humdified O2
Give IV steroids (e.g. dexamethasone 1mg/kg)
Bronchodilators (terbutaline)
Consider MDI (meter dose inhaler) admin of salbutamol
Severe, life threatening —> adrenaline
How can you use the metered dose inhaler (MDI) to manage feline asthma chronically?
Salbutamol (effective within 5 mins, lasts 4 hrs, give as required)
Fluticasone (long term control, takes 10-14 days for peak effect)
What general management and oral treatment can be used for feline asthma?
Keep away from allergens (e.g. soft furnishings, carpet etc.)
Allow outdoor access to avoid warm, dry environments
Bronchodilators —> terbutaline / inhaled salbutamol
Prednis —> consider inhaled fluticasone
ABs not indicated
How do bronchial FBs present?
Sudden onset coughing
Usually gun dog breeds (scenting / sniffing)
Hx of exercise through fields / crops / woodland
If long standing, halitosis often marked
Partial response to ABs
