Dermatology Skin Conditions
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/87

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
88 Terms
Acne Vulgaris
RF: m/c dx in America
teenagers (puberty)
severe→male
more common→female
E: propionibacterium acnes
inflammation
androgen+receptors
excess sebum
plugging of follicle
CM:
sebaceous gland activity areas:
face
chest
back
shoulders
comedonal:
whiteheads (closed comedones)
blackheads (open comedones)
inflammatory:
papules
pustules
nodulocystic:
comedones/inflammatory lesions+large nodules with/without scarring
TX:
topical
comedonal+inflammatory→retinoids:
andapalene (weak)
tretinoin
tazarotene (weak)
inflammatory acne+p. acnes→abx:
clindamycin
erythromycin
dapsone
p. acnes:
benzoyl peroxide
oral
inflammatory+p. acnes→abx:
doxycycline
minocycline
androgen-receptors→hormonal tx:
contraceptive pills
spironolactone
excess sebum:
isotretinoin
-teratogenic
-monthly pregnancy tests
-Ipledge registration
-monthly bloodwork
-not for hormonal acne
-15+ y/o (fully developed skin glands)
P: POC→post-inflammatory hyperpigmentation→tx aggressively
Hiradentitis Suppurativa
E: chronic
puberty
apocrine gland sites
-axillae
-groin
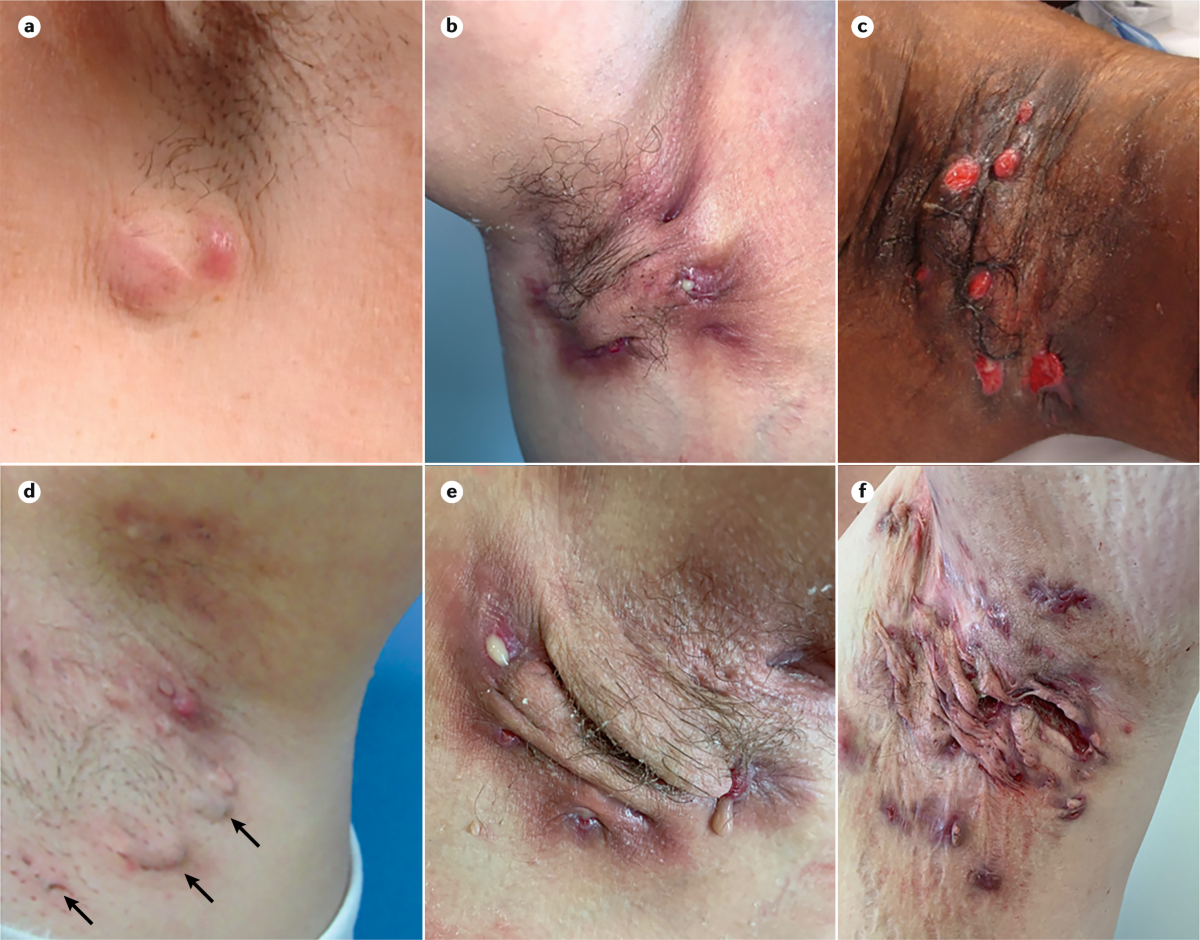
CM: tender+recurrent inflammatory nodules/abscesses
open comedomes
sinus tracts
purulent drainage
DX: bx culture
TX:
NP:
decrease weight
stop smoking
incision+drainage
excision+laser surgery
MX:
1st line: topical tetracycline
chlorhexidine
IL triamcinolone
prednisone
humira
cosentyx
Folliculitis
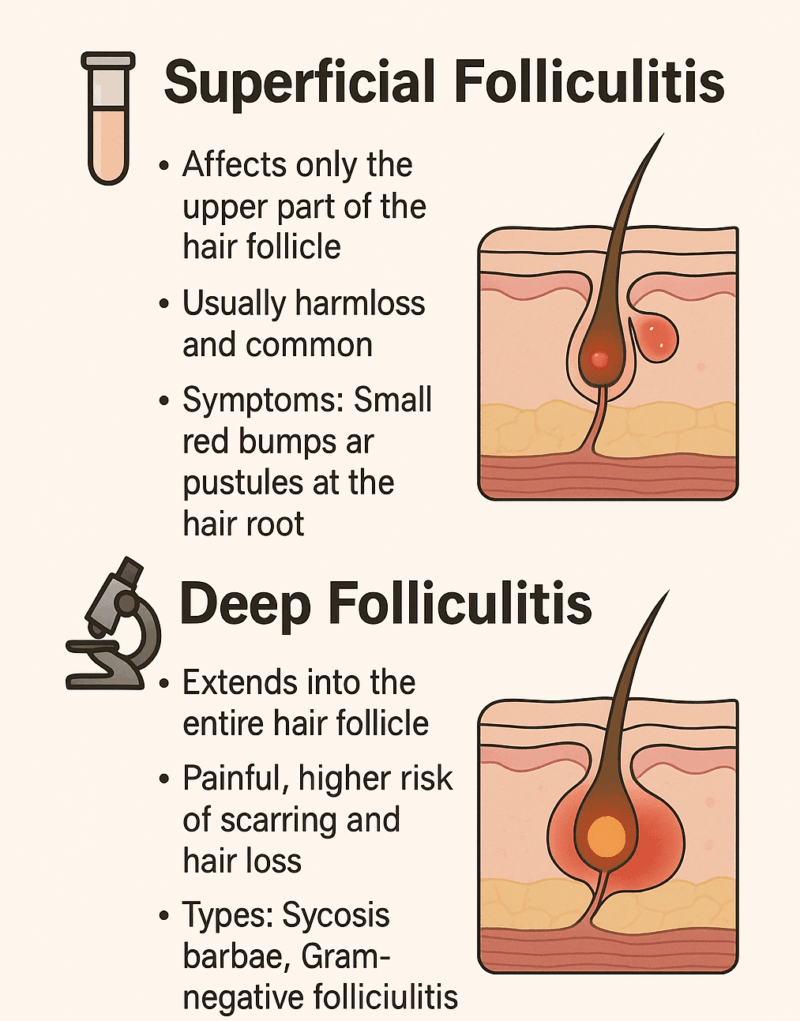
PP: inflamed hair follicles
-superficial
-deep
anywhere there are hairs
E: infection
occlusion
irritation
s. aureus
malassezia
CM: tender red perifollicular papule
with surface pustule
TX:
s. aureus:
PO cephalexin
PO cefadroxin
topical mupirocin
malassezia:
econazole
ketoconazole
selenium sulfide
systemic: fluconazole
Hot Tub Folliculitis
RF: hot tub use
E: p. aeruginosa
CM: red papules on lower body/lower regions
TX: PO ciprofloxacin
topical gentamicin
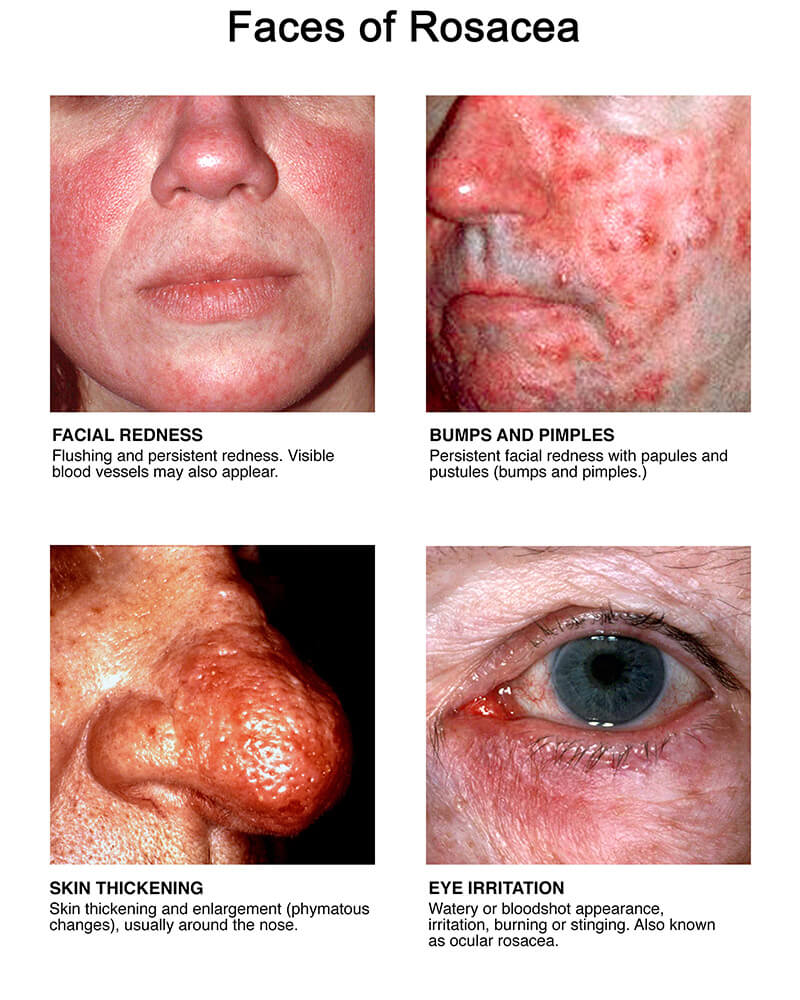
Rosacea
PP: persistent erythema of convex surfaces of face
includes nasolabial fold
E: unknown
steroids (too long/strong on face)
CM:
phymatous (nose)
ocular (eye)
papulopustular (papules/pustules)
erythematotelangioetic (flushing)
DX: biopsy
ANA
TX:
NP:
avoid spicy foods
avoid alcohol
gentle skin care regimen
blood vessels→laser surgery
rhinophyma→surgery+CO2 laser
MX:
topical:
1st line: metronidazole
azelaic acid
sulfacetamide
ivermectin
systemic:
doxycycline 20mg BID
doxycycline 40 mg QD
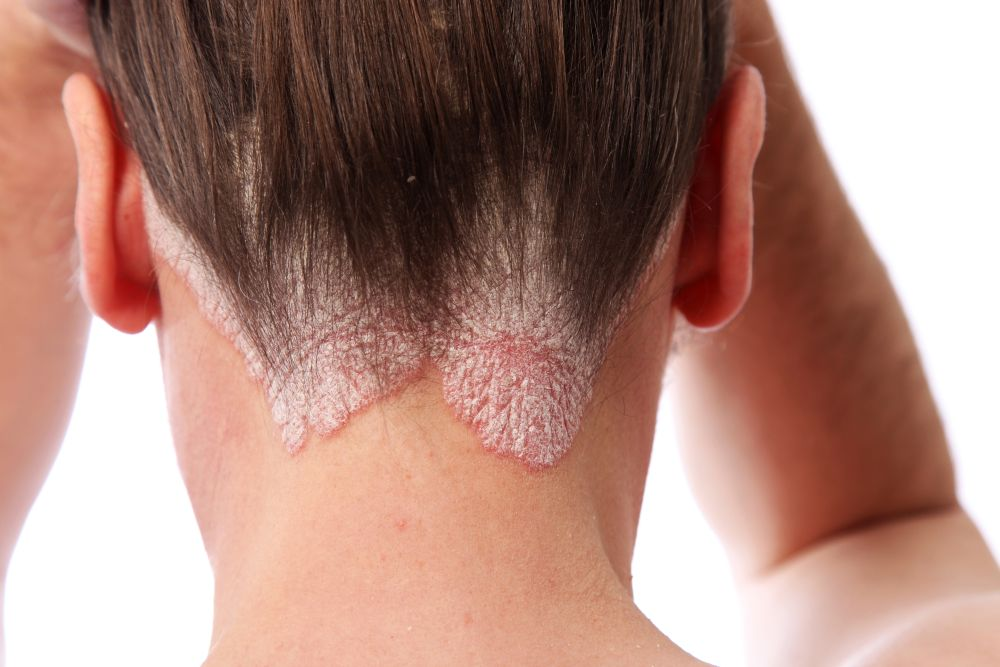
Seborrheic Dermatitis
PP: abnormal inflammatory reaction to malassezia in sebum-rich areas
E: malassezia
sebum rich areas
-scalp
-central face
CM: greasy scale on erythematous base
dandruff
peds: “cradle cap”
POC: lighter in color+no redness
TX:
peds:
NP: reassurance
outgrow by 6 months
MX: aquaphor
coconut oil
adults:
short term: hydrocortisone cream
long term: ketoconazole cream
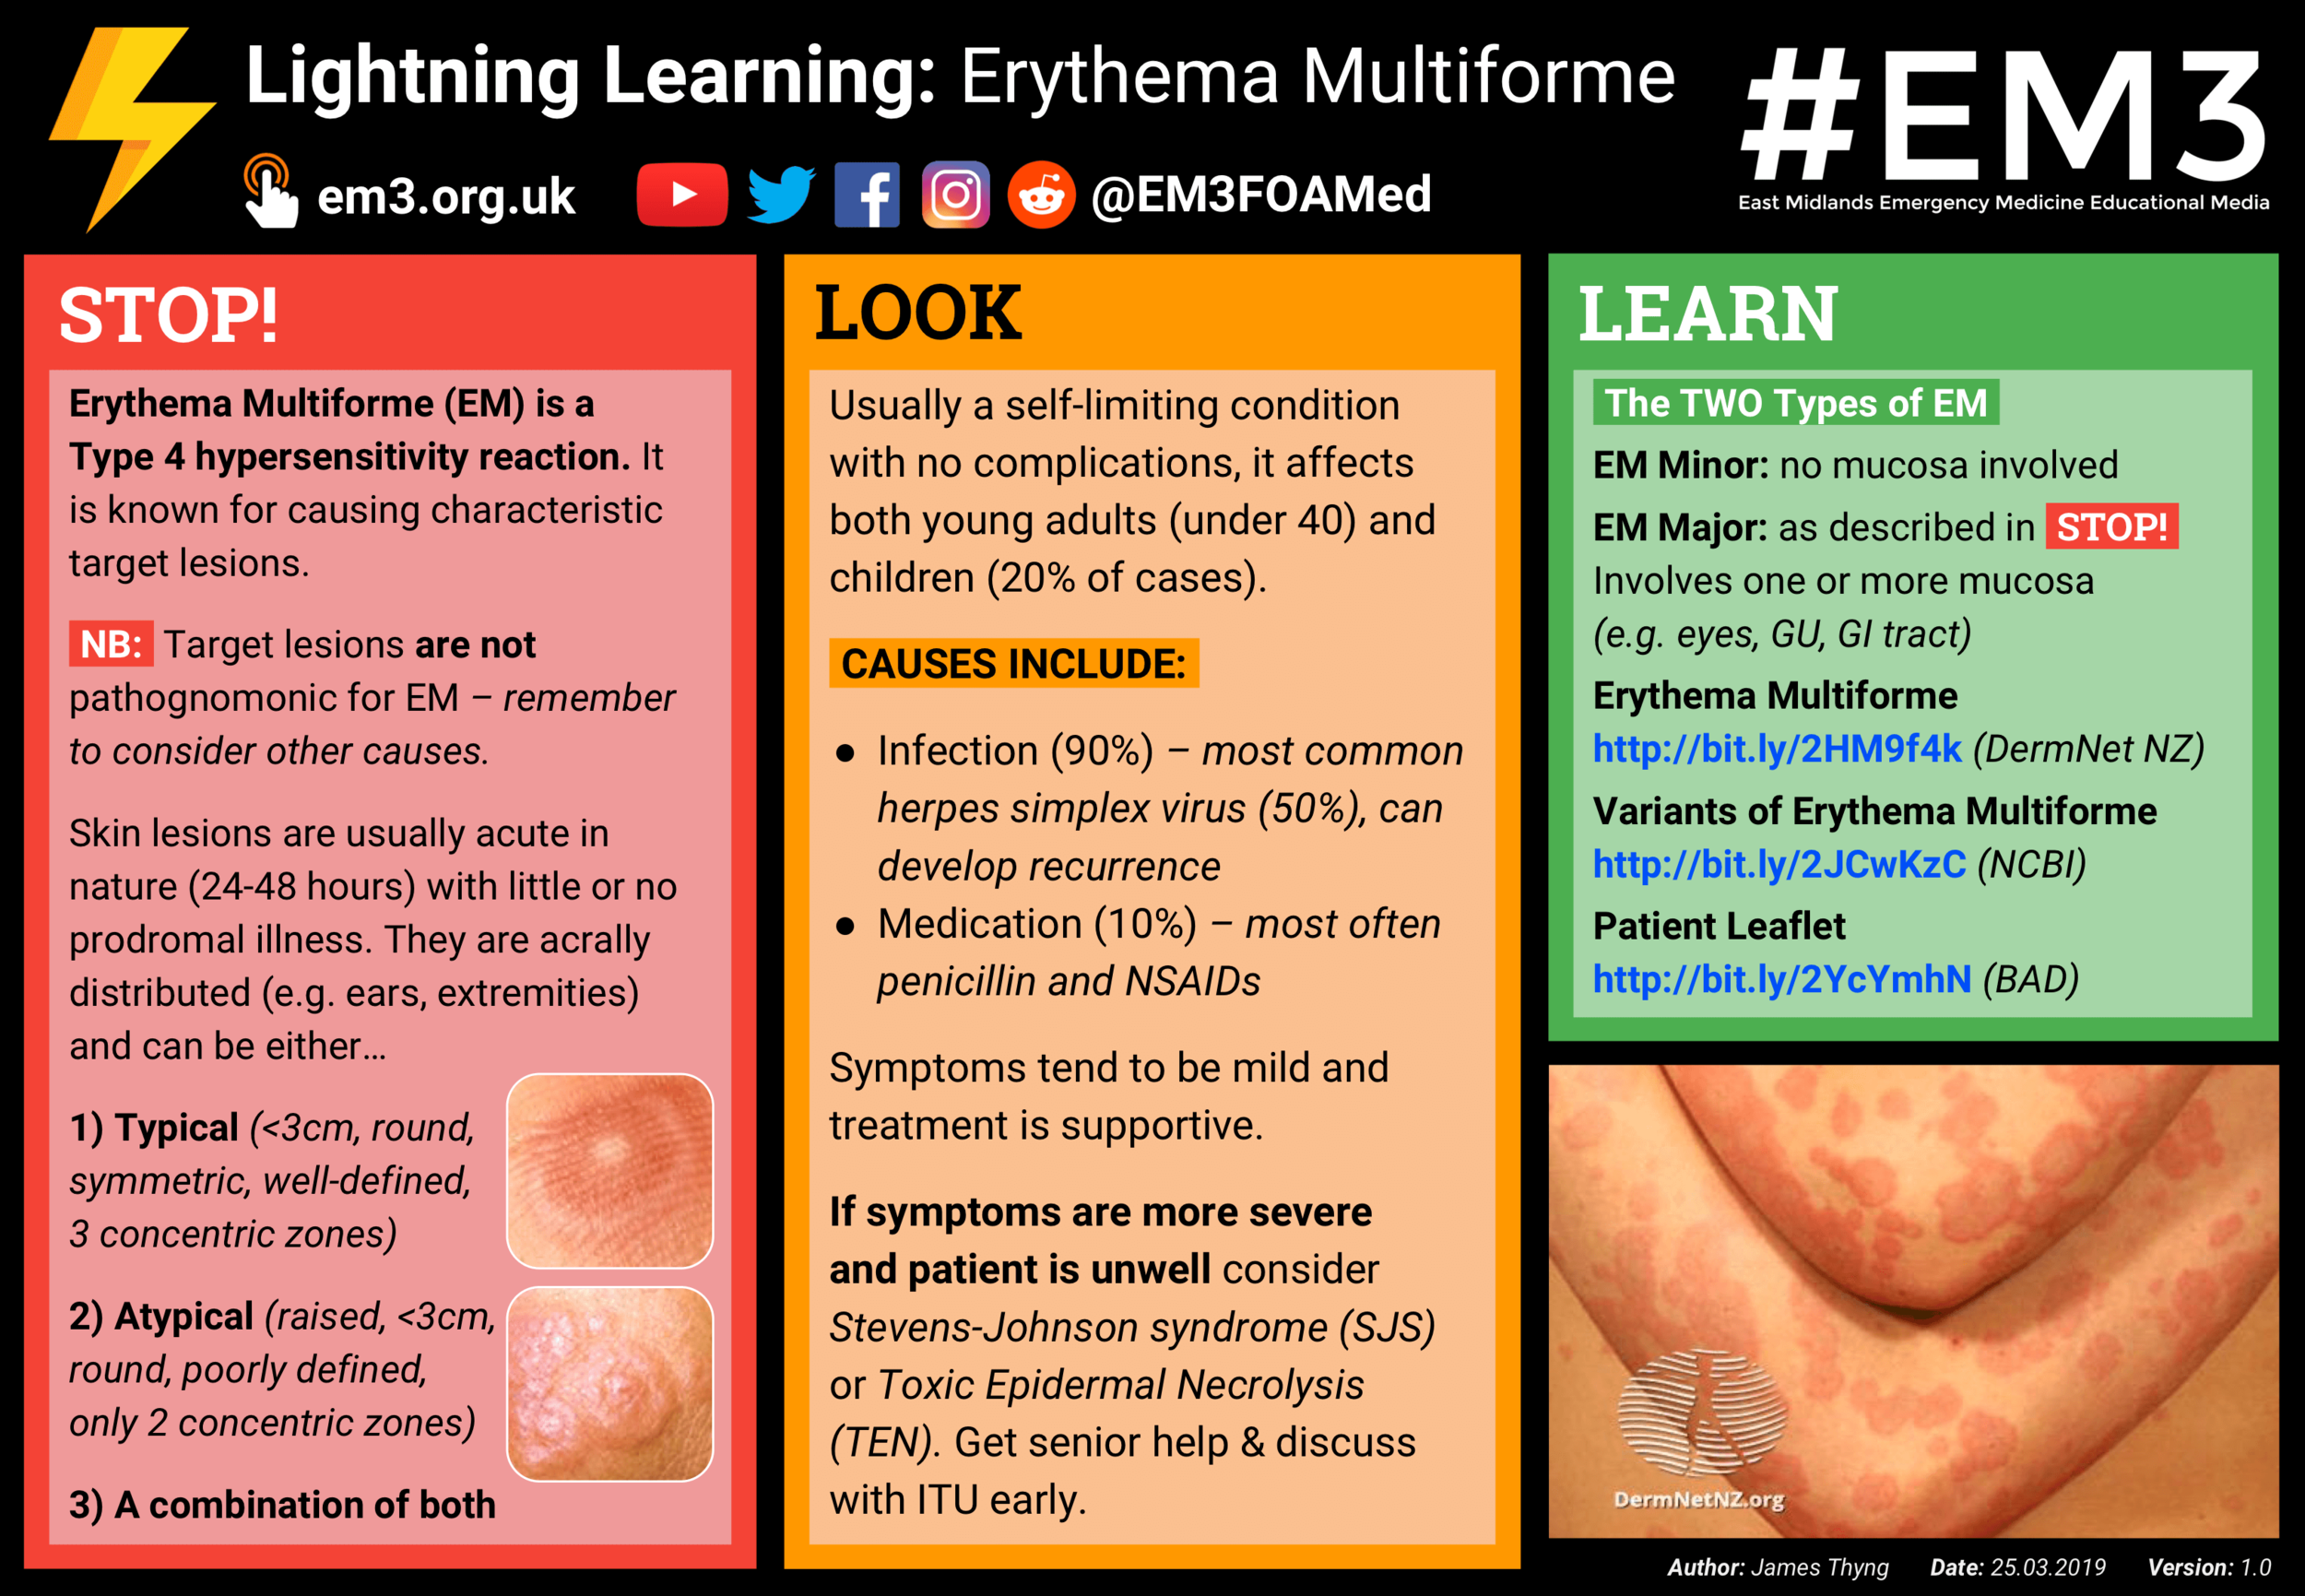
Erythema Multiforme/SJS/TEN
EM minor:
PP: sharply marginated erythematous macules→raised+edematous over 1-2 days
ring of erythema forms→target shape
E: m. pneumonia
CM: orolabial herpetic outbreak 3-14 days before rash
no prodromal/flu-like sx
P: self-limited
1-2 weeks
common recurrence
EM major:
PP: sharply marginated erythematous macules→raised+edematous over 1-2 days
ring of erythema forms→target shape
E: m. pneumonia
CM: influenza-like sx 1-2 weeks before cutaneous lesions
P: 5% mortality rate
uncommon recurrence
SJS:
PP: EM like skin lesions
cover 10% BSA or less
mucosal involvement
-oral
-occular
-genital
E: adverse reaction to mx
-sulfonamides
-anticonvulsants
TEN:
PP: cover 30% or greater BSA
skin sloughs off body
E: adverse reaction to mx
-sulfonamides
-anticonvulsants
DX: clinical assessment
biopsy→does not distinguish
neutropenia
BUN (high→bad prognosis)
TX:
EM:
NP:
stop mx
tx underlying cause
MX:
antihistamines
mild topical steroids
SJS/TEN:
admit to hospital
TEN→burn unit
Alopecia Etiology
good hx needed
non-scarring:
hormonal
tight hair buns
immune system (alopecia areata)
telogen effluvium (systemic cause)
-pregnancy
-COVID
-mx
-nutrition deficiency
scarring:
follicles destroyed by inflammation
-ex: discoid lupus

Alopecia Areata
E: autoimmune dx
-totalis (scalp)
-universalis (whole body)
CM: non-scarring
1+ round/oval patches (1-5 cm)
exclamation point hairs
TX:
localized:
intralesional/topical triamcinolone
extensive:
topical immunotherapy
PO JAK inhibitors
off-label tx
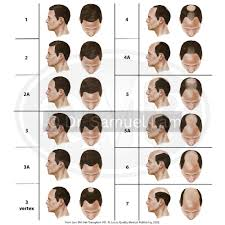
Androgenic Alopecia
E: genetics
sensitivity to DHT (dihydrotestosterone)
CM:
male:
front temporal areas+vertex of scalp
female:
crown of head
retaining frontal hairline
TX:
male:
topical/PO minoxidil
PO spironolactone
female:
topical minoxidil
PO finasteride
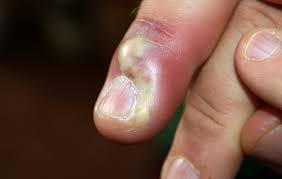
Paronychia
PP: inflammation of the nail fold
E: bx
secondary candida colonization
CM: erythema
swelling
throbbing pain
pustular drainage
TX: topical+systemic abx
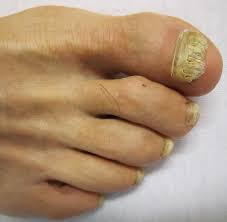
Tinea Unguim/Onchymycosis
PP: fungal infection of nails
E: dermatophytes
CM: subungual hyperkeratosis
scaling
yellow discoloration
onycholysis (end of nail lifts up)
DX: clinical
KOH
culture
nail plate biopsy
TX:
topical ciclopirox QD x 1 year
terbinafine QD x 3 months
-mx interactions
-mtr liver enzymes
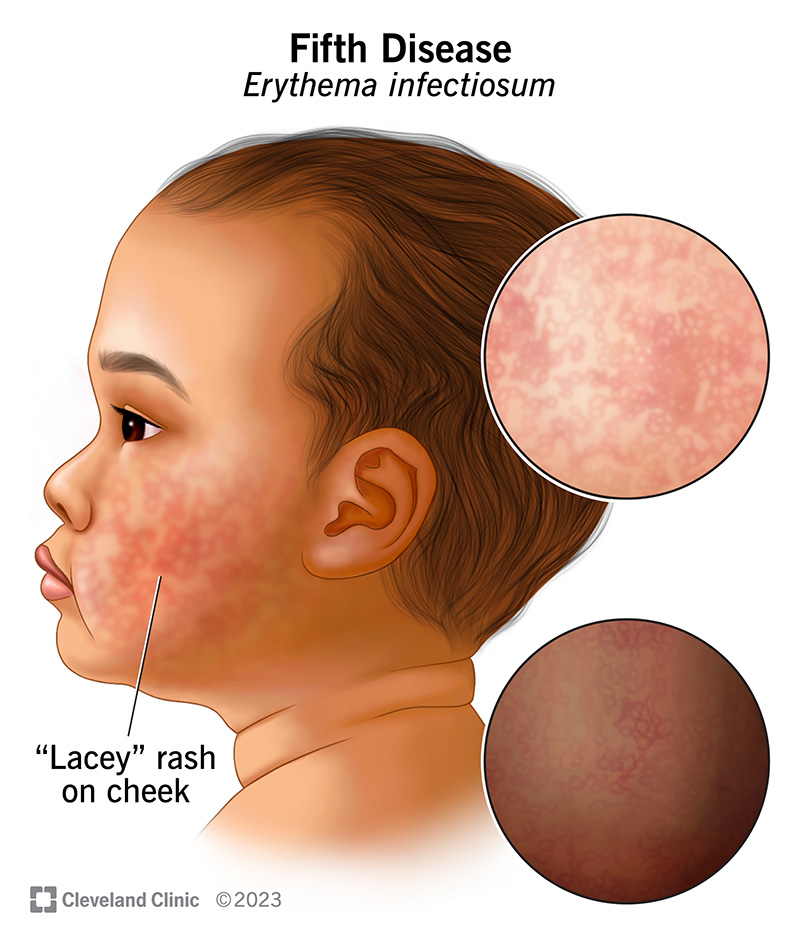
Erythema Infectiosum (5th Disease)
E: parvovirus B19
CM: mild fever+headache→red slapped cheeks x 2-4 days→reticulated/lacy patch on limbs/trunk
TX: none
C: spontaneous abortion
polyarhtorpathy
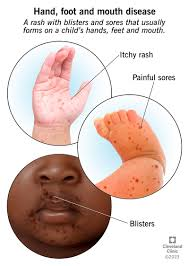
Hand Foot and Mouth Disease
E: coxsackie virus
common
mild
short-lasting
contagious:
direct contact
nasal
oral secretions
fecal contamination
CM: flat pink patches→blisters on hands+feet
peel off in a week
small+painful vesicles in mouth
red macules+papules on butt/arms/genitals
TX:
don’t pop blisters
antiseptic mouthwash
maintain fluid intake
poor PO→IV fluids
painful oral ulcer→topical/PO analgesics
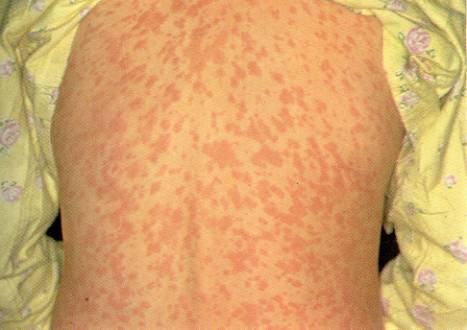
Rubeola/Measles
E: measles virus/morbillivirus
highly contagious:
airborne
respiratory droplets
CM: cough
coryza
conjunctivitis
gray-white papules
buccal mucosa (koplik’s spots)
high fever:
nonpruitic morbilliform rash on face→24-36 hrs→entire trunk+extremities (no palms+soles)
TX: none
prophx: measles vaccine
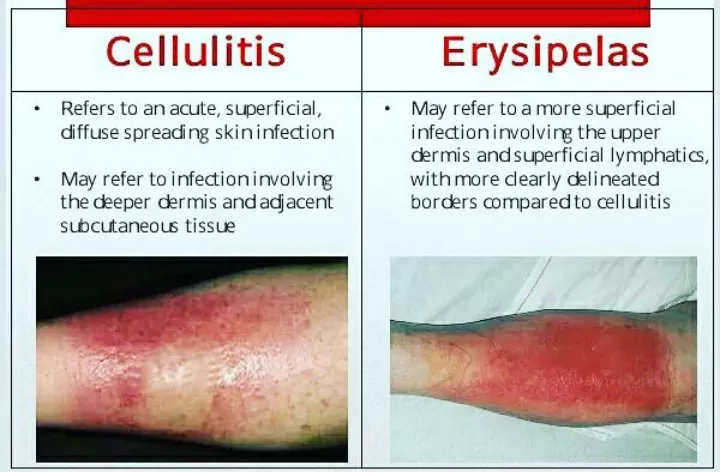
Cellulitis
PP: acute spreading inflammation of dermis+subcutaneous tissue
E: h. influenzae
streptococcus
staphylococcus
DX: drainage bx culture
TX:
PO dicloxacillin
PO cephalosporins
severe→IV 1st gen cephalosporin
surgery
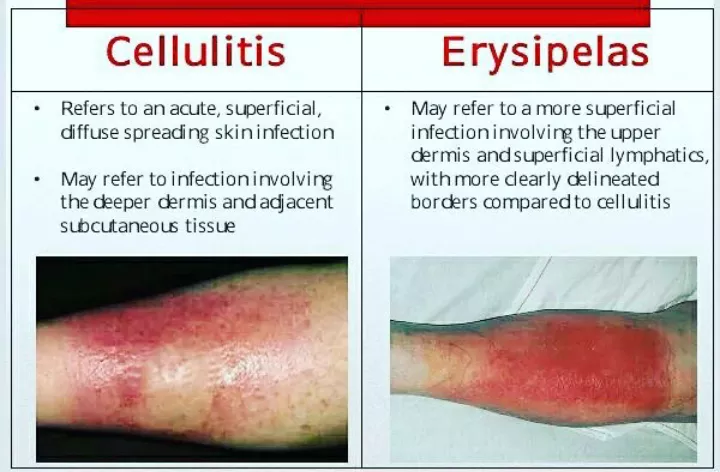
Erysipelas
PP: superficial cellulitis of the upper dermis that extends to superficial cutaneous lymphatics
E: abrupt onset
rapid progression
CM: painful macular rash
well-defined margins
fiery red rash
face→progression to extremities
TX:
PO penicillin x 10-14 days
IV penicillin x 10-14 days
desquamates x 5-10 days
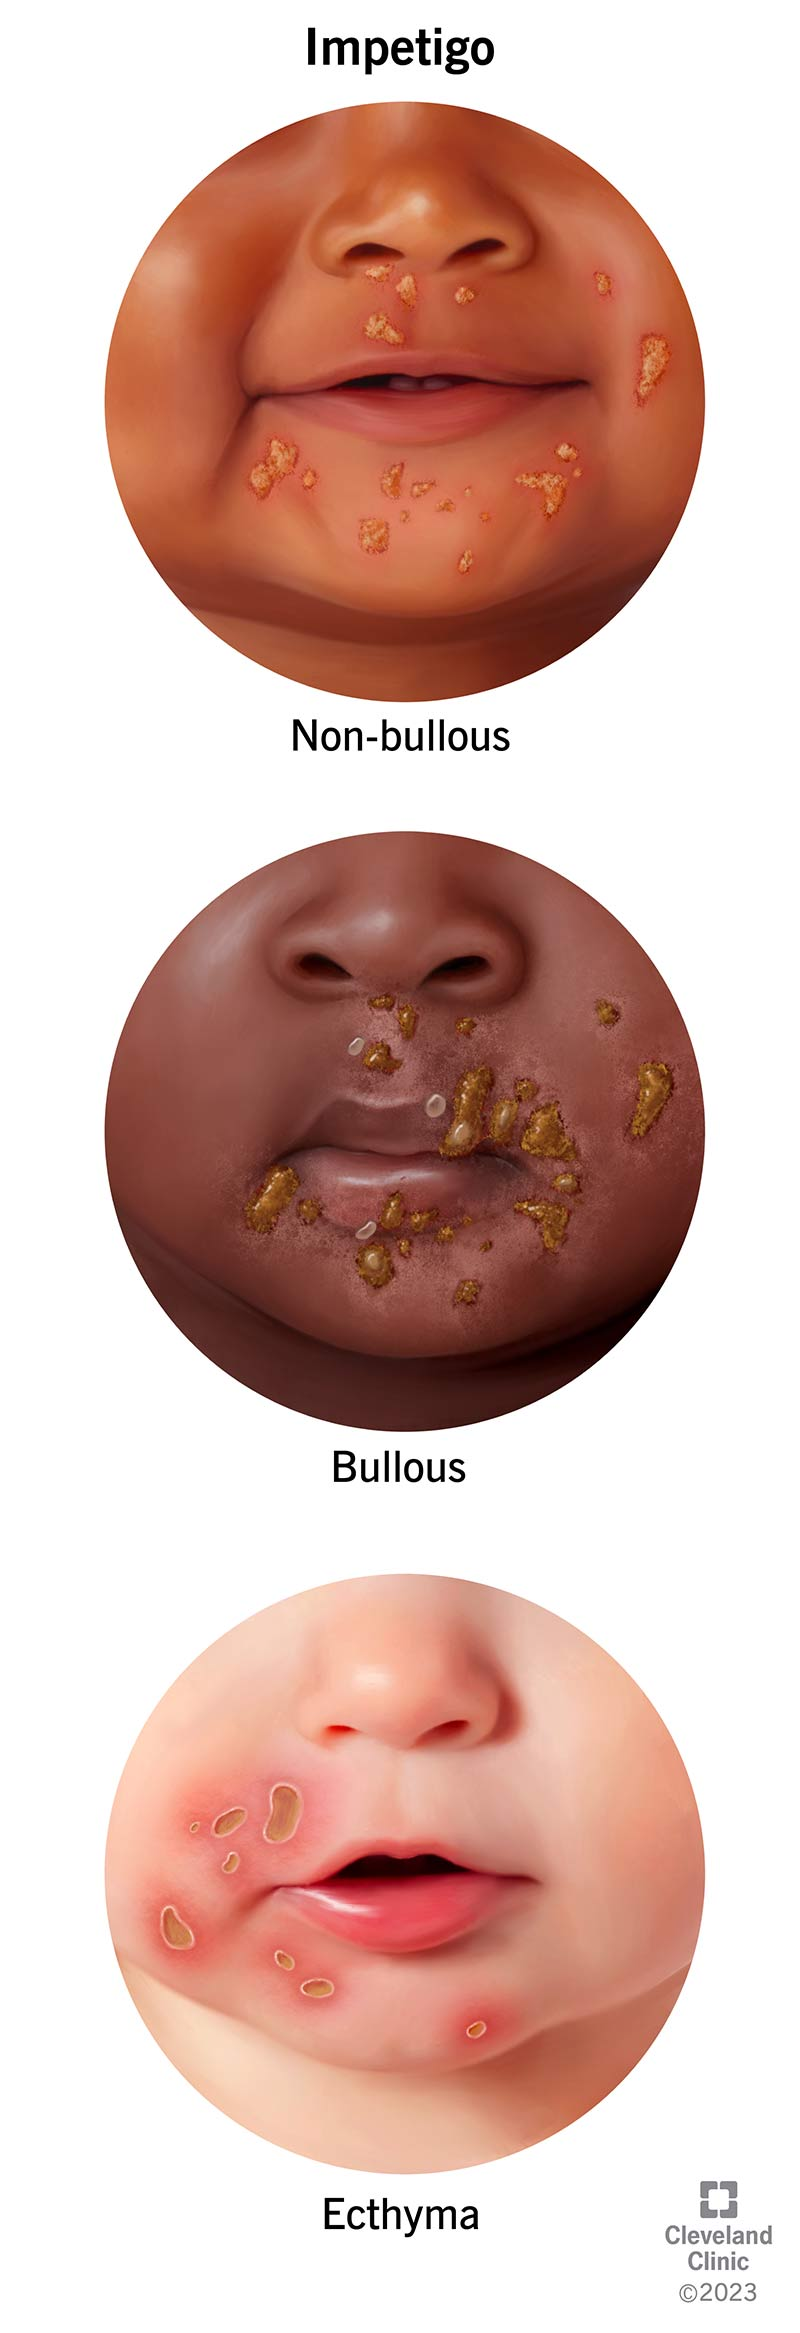
Impetigo
PP: gram-positive bx infxn
E: s. aureus
10% of peds derm
warm/humid environment
highly contagious
face
extremities
spreads:
cutaneously
systematically (rare)
CM:
bullous:
-m/c peds
-blisters (enlarge+rupture)
nonbullous:
small+easily ruptured vesicles→honey-covered crusts
DX: bx culture
TX:
NP: proper hand washing
MX: cephalexin
cefadroxil
topical mupirocin
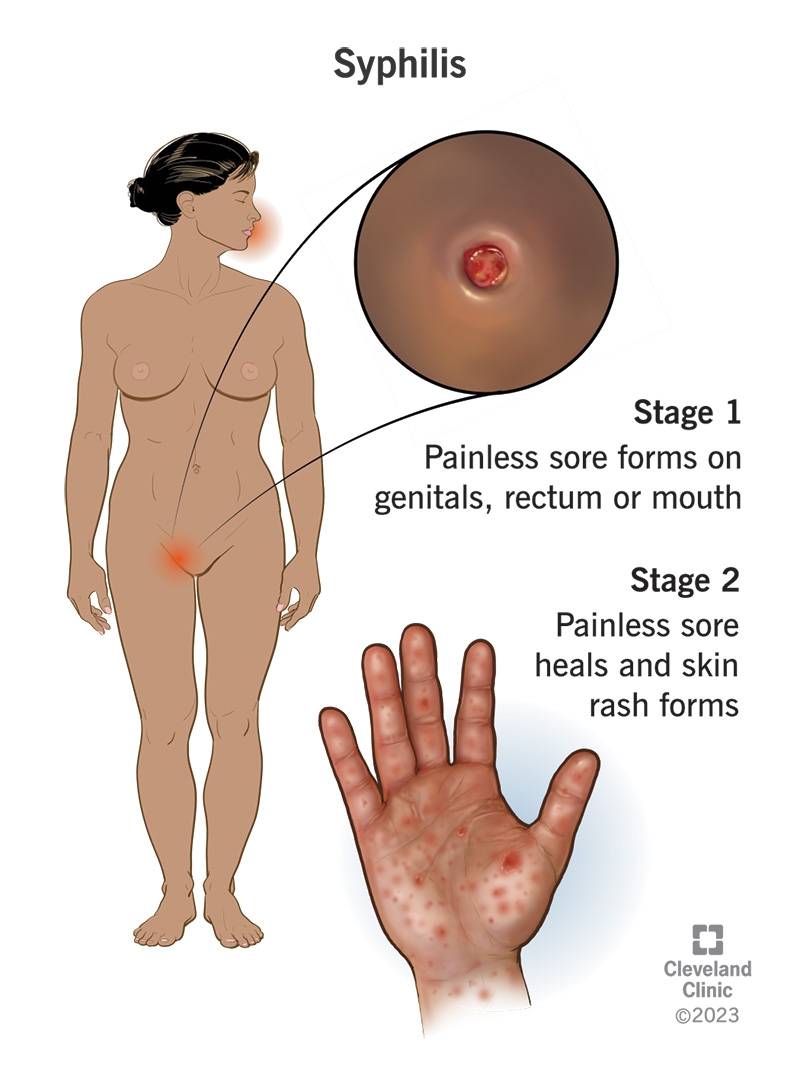
Syphillis
PP: skin/mucous membranes→circulatory system (tertiary/late)→CNS (neurosyphillis)
E: trepodema pallidium
sexual contact
congenital
CM:
primary:
painless/indurated macule/papule
highly infectious
heals in 3-6 weeks
secondary:
several weeks after primary syphillis
persists for weeks-months
highly infectious
rough/red/non-itching papules/patches on trunk+palms+soles
latent:
asx
only shows with positive serologic test
tertiary/late:
widespread abx→rare
gummatous lesions
CV sx
neurosyphillis:
asx
or
acute syphilit meningitis
ocular involvement
congenital:
deafness
deformities
neuro impairment
DX: treponemal qualitative+nontreponemal qualitative
HIV testing
report to state department
TX: IM penicillin
doxycycline
tetracycline
C:
congenital:
stillbirth
neonatal death
infant disorders
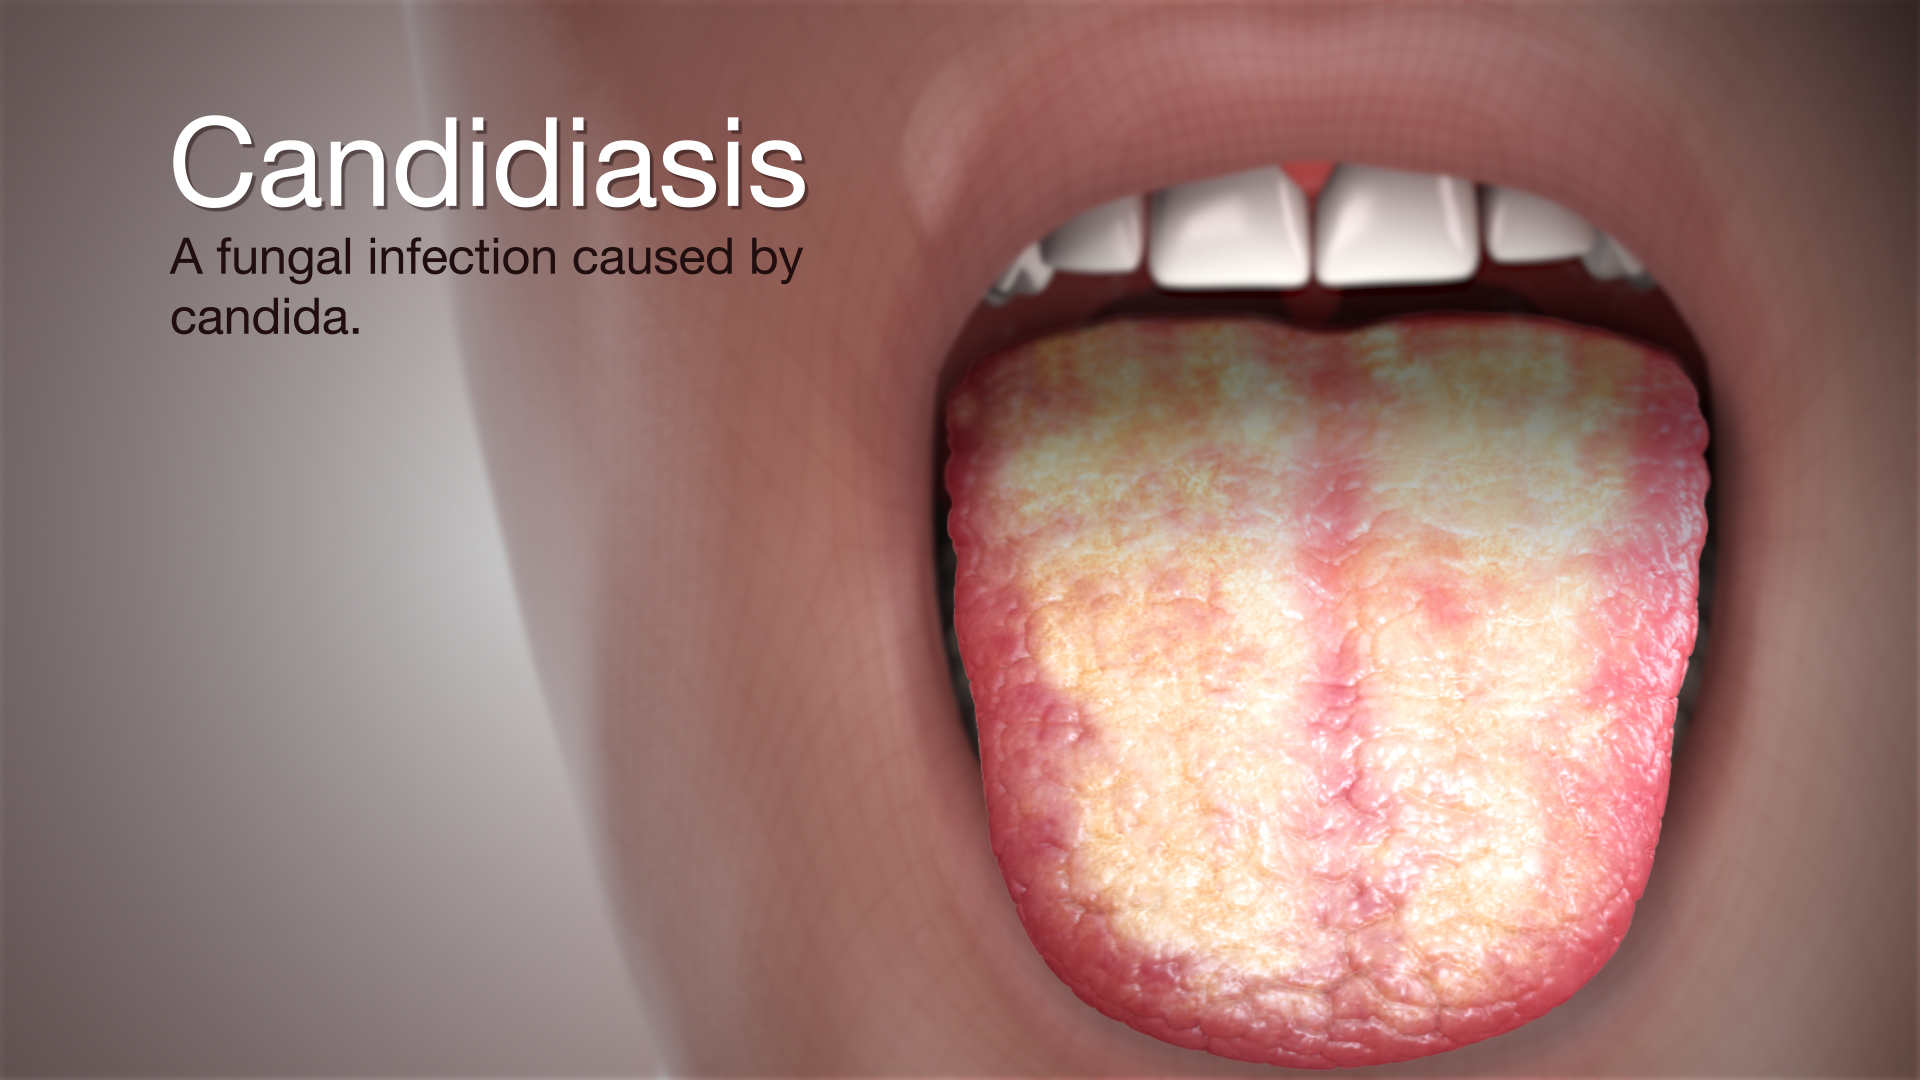
Candidiasis
E: yeast
abx
diabetes
obesity
poor hygiene
oral infxn (1st sx of HIV)
warm/moist areas
CM:
oral: whitish plaques on erythematous base of buccal mucosa (thrush)
body:
beefy/red papules/plaques in skin folds (interigo)
satellite lesions
thick “cheesy” discharge
TX:
oral:
nystatin suspension
fluconazole
breastfeeding→tx mother’s nipples
body:
keep area dry+clean
stop mx
topical/PO antifungals
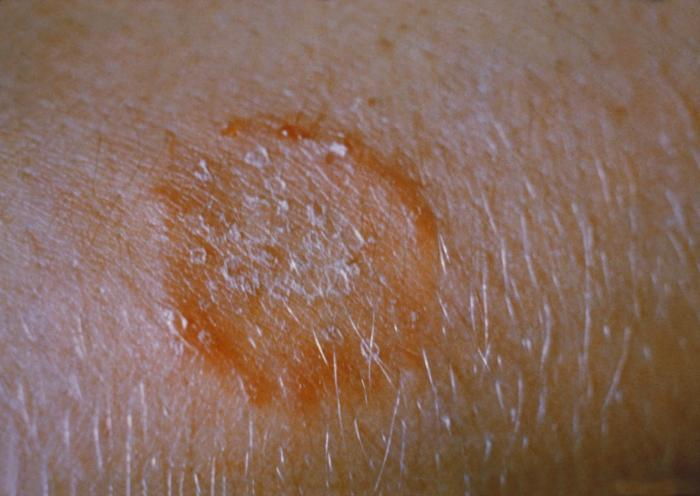
Tinea Capitis
PP: fungal infection of scalp
E: dermatophytes
CM: dry scaling
moth-eaten hair loss
inflamed mass/abscess (kerion)→untx→permanent scarring/baldness
DX: bx culture
TX:
NP: throw out hairbrush
adjunctive therapy
MX: ketoconazole shampoo
selenium sulfide shampoo
PO griseofulvin x 6 weeks-6 months
P: swollen lymph glands at sides/back of neck

Tinea Corporis/Ringworm
PP: fungal infection of body
E: dermatophytes
CM: well-demarcated annular plaque
central clearing+peripheral scale
contagious
DX: KOH prep
TX: topical econazole
topical ketoconazole
P: swollen lymph glands at sides/back of neck
Tinea Incognito
PP: potent topical/non-antifungal steroid→drives fungus deep into skin→affects hair follicles
E: dermatophytes
CM: irregular/red/scaly plaque
follicular papules
pustules→more severe→majocchi’s granuloma
TX: PO griseofulvin x 4-6 weeks
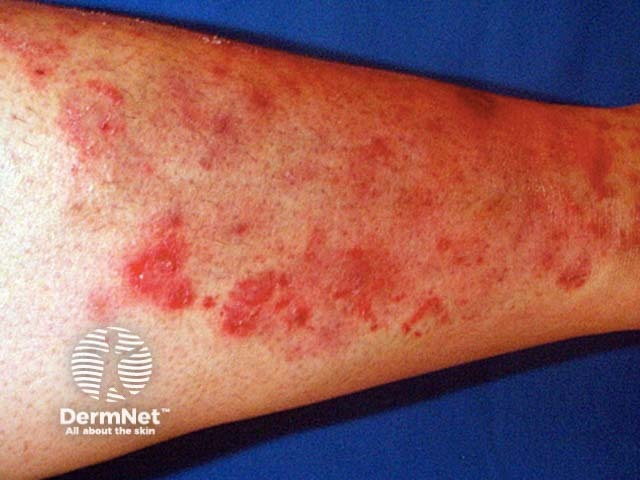
Tinea Cruris/Jock Itch
PP: fungal infection of groin+gluteal cleft
E: dermatophytes
contaminated towels/sheets
autoinnoculation
CM: scaly plaque with widespread erythema
intensely pruritic
TX:
NP: keep groin dry
weight loss
MX: topical azoles x 2-4 weeks
Tinea Manuum
PP: fungal infection of palms on hands
E: dermatophytes
primary infection→rare
CM: blisters on palms/fingers→single scale patch→infected nails
TX: topical antifungals
PO antifungals
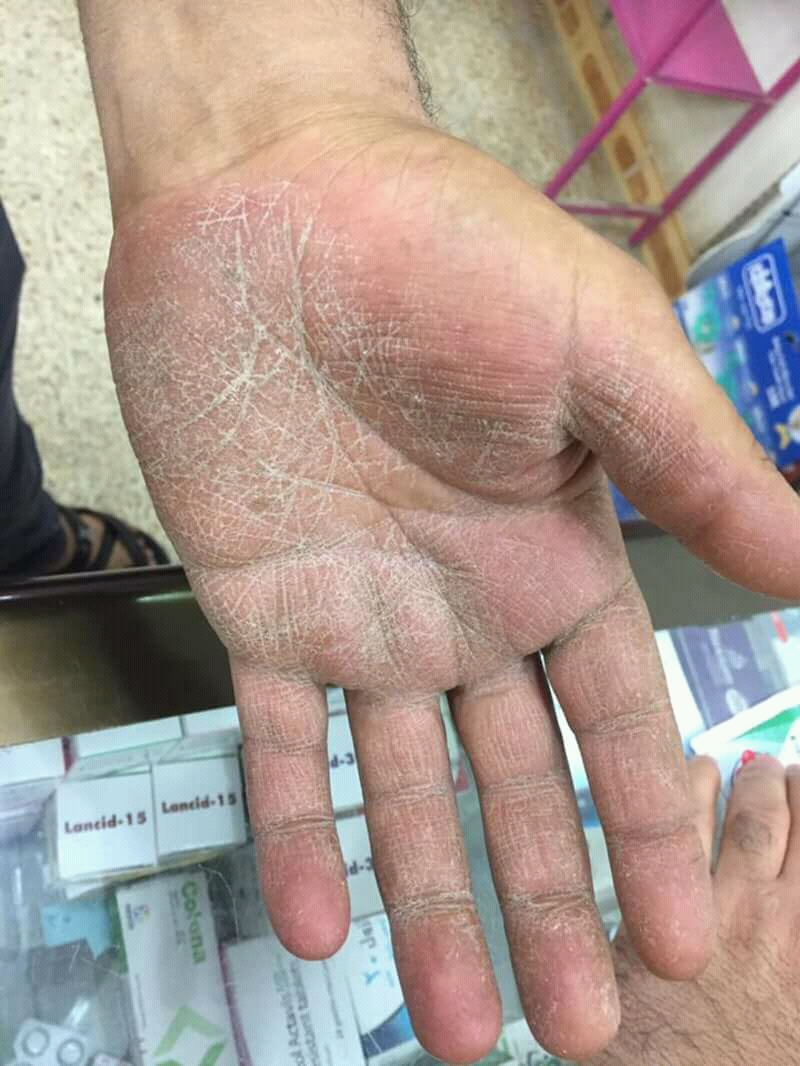
Tinea Pedis/Athlete’s Foot
PP: fungal infection of feet
E: dermatophytes
CM: macerated scale on feet
DX: KOH
bx culture
biopsy (rare)
TX:
NP: wear protective footwear in communal areas
minimize foot moisture
MX: topical antifungals
mocacsin-type/chronic→PO antifungals

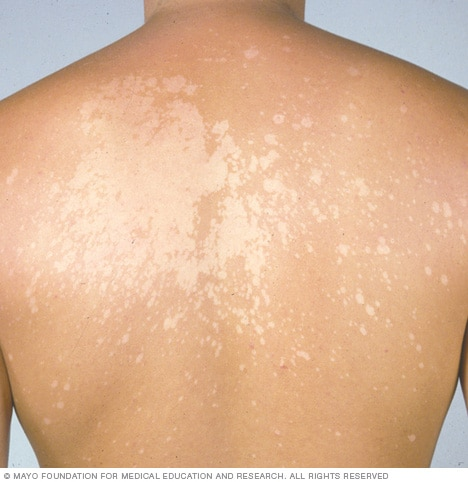
Tinea Versicolor
PP: superficial malassezia infection
not contagious
E: malassezia furfur
CM: hyper/hypopigmented oval macules
fine scale on chest+back
TX: topical ketoconazole
topical selenium sulfide
P: 1-2 months for pigment to return to normal
Pediculosis Capitis/Head Lice
PP: scalp infestation
E: head lice
CM: intense itching
posterior cervical lymphadenopathy
excoriations on scalp
nits/ova on hair
TX:
NP: remove lice+ova
nit combing (not on topical spinosad 0.9% suspension)
MX: permethrin
malathion 0.5% lotion

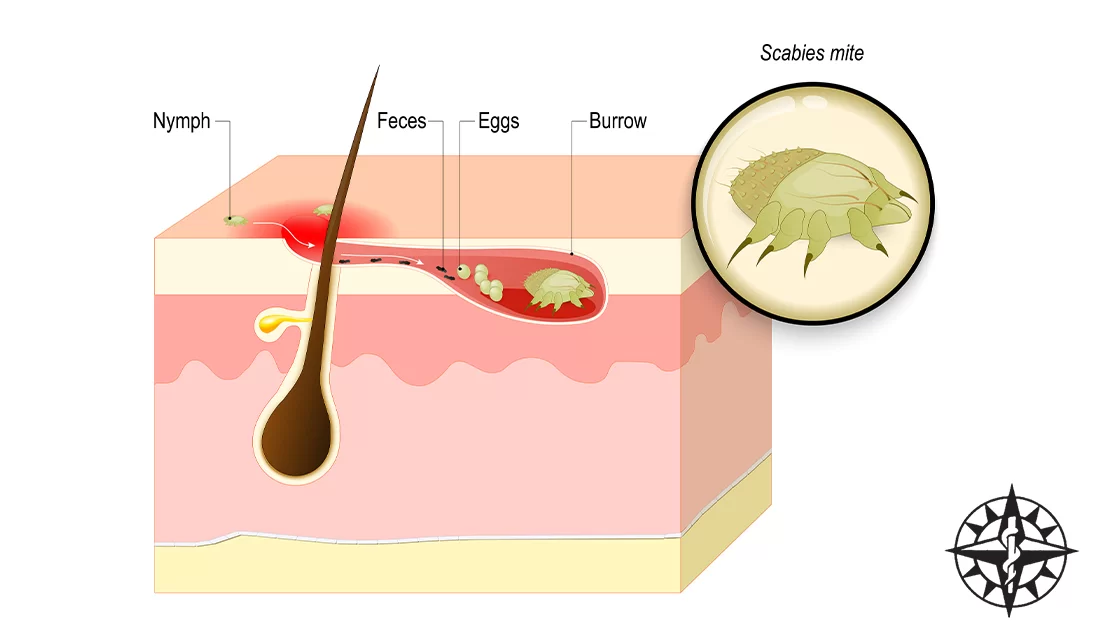
Scabies
PP: female mites burrow into skin+lay eggs
eruption conditions:
length of infestation
climate
host’s immune status
E: sarcoptes scabiei mites
personal contact
contaminated linens+clothing
CM: pruruitic papular lesions
excoriations
s-shaped burrows
common sites:
finger webs
wrists
axillae
lower abdomen
genitals
buttocks
adults: scalp
face
infants: entire body
DX: surgical blade→scrape burrow→place on slide+mineral oil→examine under microscope
TX:
NP: clothing+bed lines changed+laundered thoroughly
MX:
topical permethrin 5% cream
neck to feet
wash over 8-10 hours later
repeat x 1 week
PO ivermectin
take on day 1
repeat x 1 week
Bed Bugs
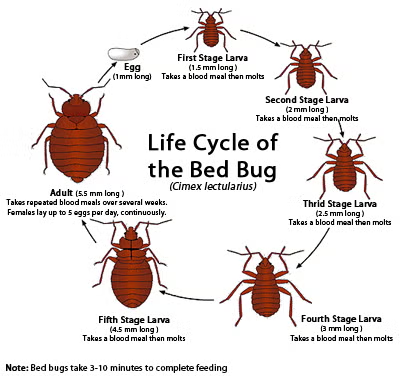
PP/E: blood-sucking human parasite
cimex lectularius
survive without eating for 1 year
RF: warmth
night
mattresses
furniture
luggage
clothing
CM:
papular urticaria:
upon awakening
bites in groups of 2-3
TX:
NP: extermination
MX: topical steroids
antihistamines
secondary infections→abx
Verucca Infections/Warts
PP: benign viral tumor
wart
E: HPV 16
HPV 18
CM:
common wart (verrucous vulgaris):
solitary papule
irregular
scaly surface
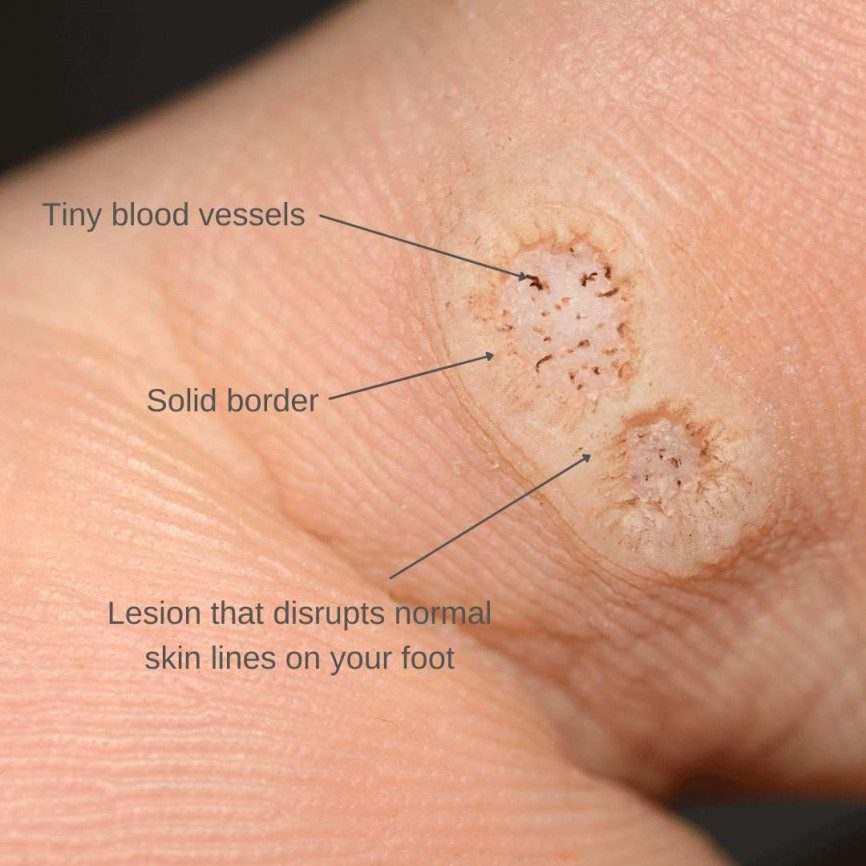
plantar wart (verrucous plantaris):
weight-bearing areas on feet
flat wart (verruca plana):
multiple papules
flat-topped
broad-skin
colored
veneral wart (candyloma acuminata):
multiple/confluent papules
irregular surface
on genital mucosa
TX:
NP:
1st line: cryotherapy
laser surgery
MX:
1st line: topical salicylic acid
intralesional bleomycin
topical fluorouracil
topical immunotherapy
Candyloma Acuminatum/Veneral Warts
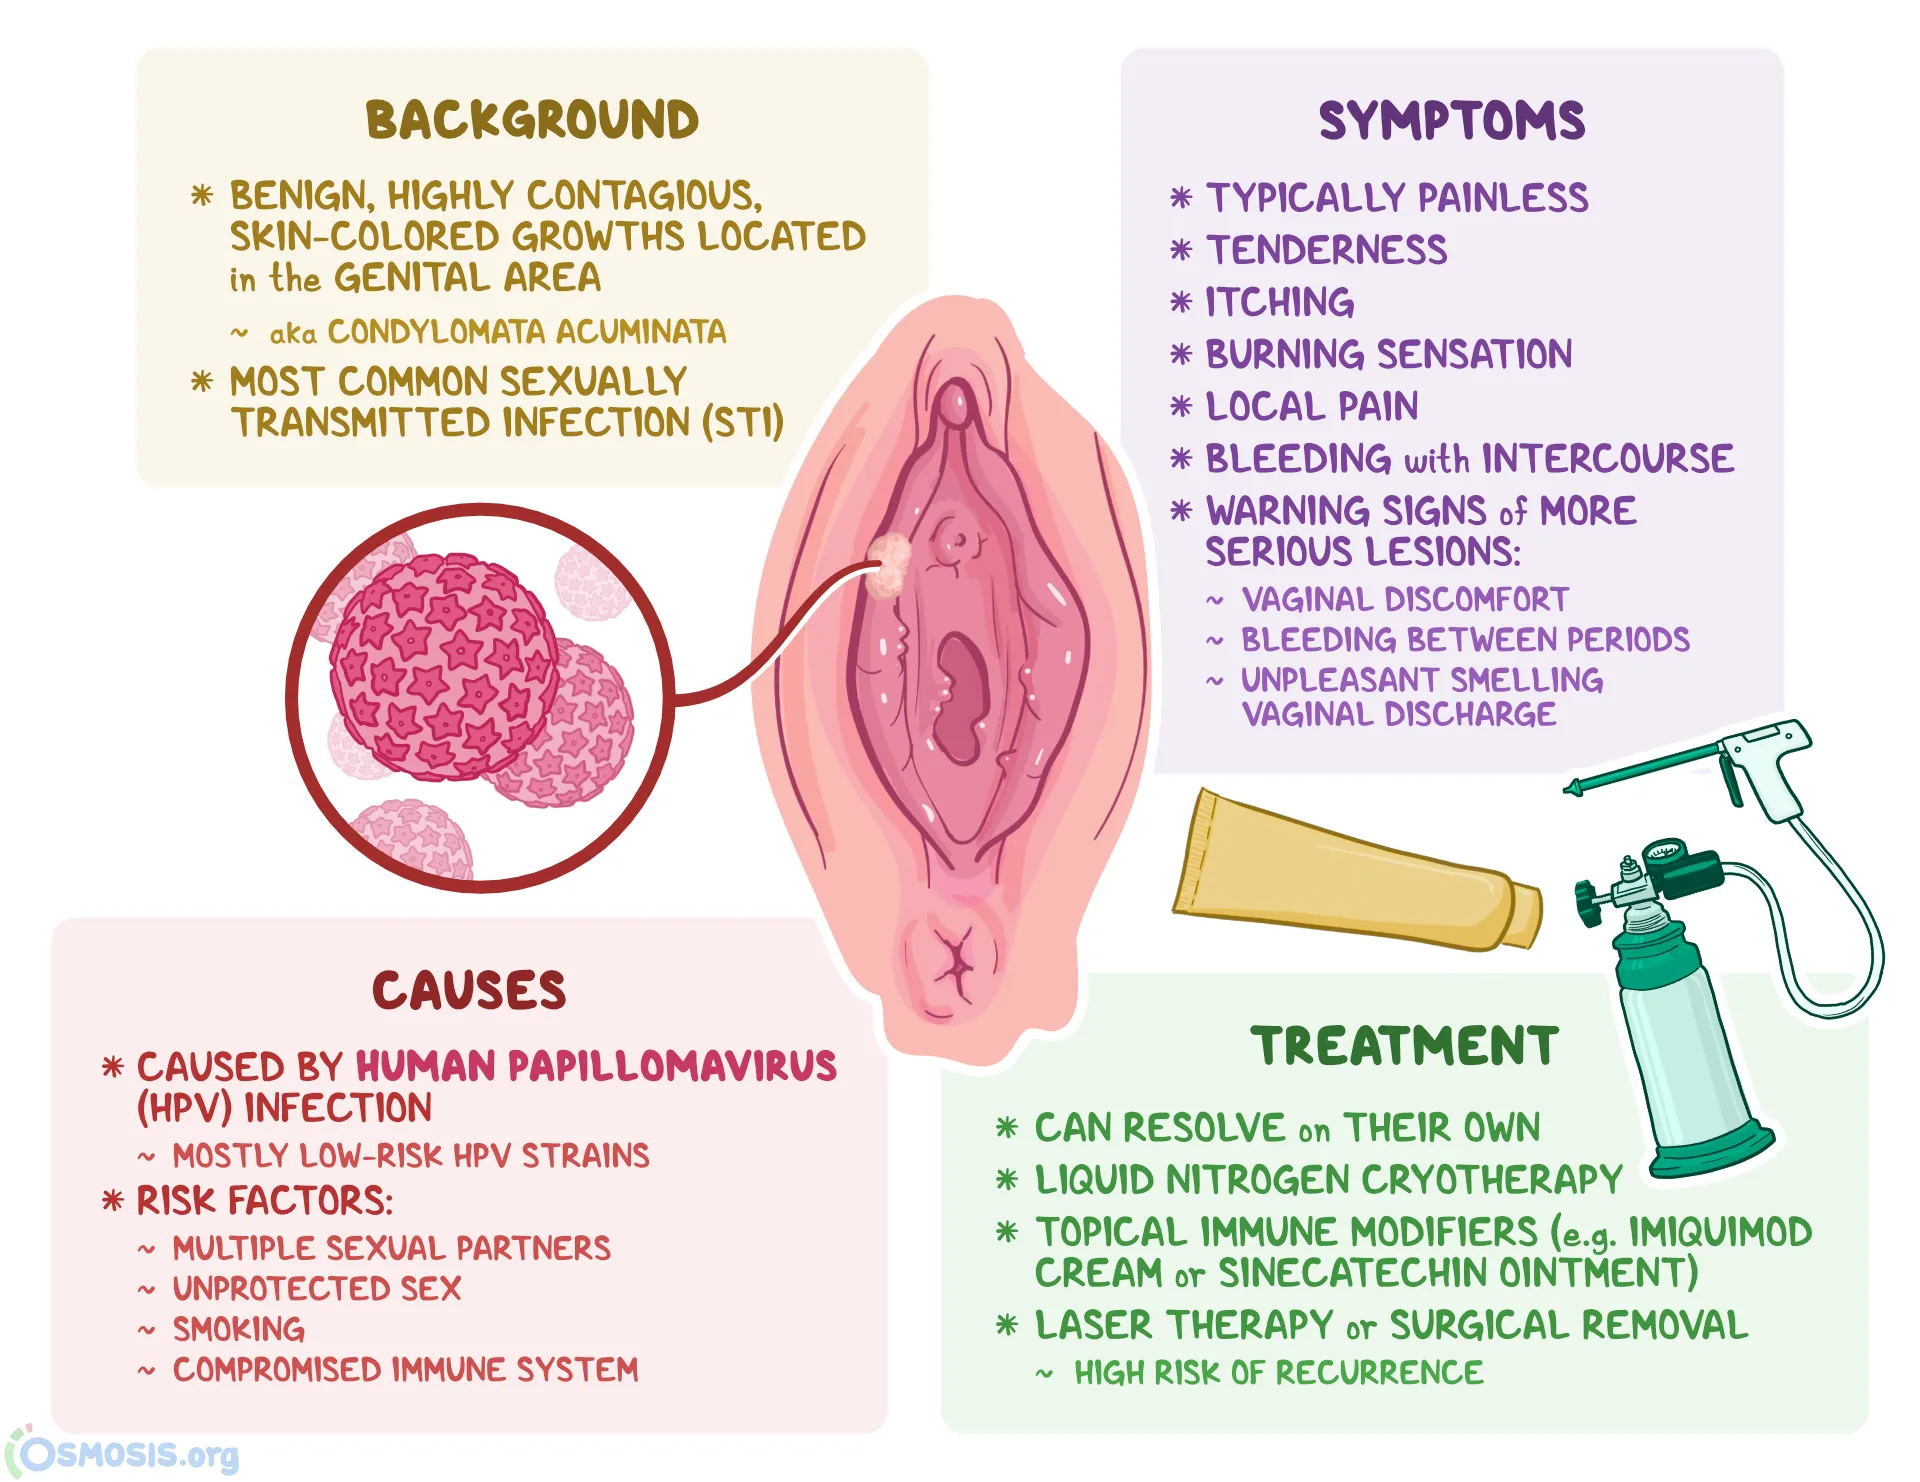
PP: benign viral tumor
genital wart
E:
cervical:
HPV 16
HPV 18
RF for dysplasia→cervical cancer
genital:
sexual contact
CM: multiple/confluent papules
irregular surface
on genital mucosa
TX:
NP:
1st line: cryotherapy
HPV vaccine
laser surgery
MX:
1st line: topical salicylic acid
topical imiquimod
intralesional bleomycin
topical fluorouracil
topical immunotherapy
Herpes Simplex
E:
HSV-1:
oral herpes
more common
HSV-2:
genital herpes
multiple sexual partners
monogamy→5-10% risk of transmission
CM:
grouped vesicles on erythematous base
recurrent cases→tingling or pain
triggers:
UV light exposure
dental procedures
HSV-1:
cold sore
high fever
leukocyte adhesion deficiency (LAD)
malaise
duration: 1-2 weeks untxd
-oral mucosa
-tongue
-tonsils
-lips
HSV-2:
asx shedding→no clinical lesions/sx→still infectious with sexual contact
painful
dysuria
fever
flu-like sx
leukocyte adhesion deficiency (LAD)
duration: 3+ weeks untxd
-vagina
-rectum
-penis
-buttock
DX: viral culture
specific for acute lesions
not in older/crusted lesions
TX:
HSV-1:
NP:
daily sunblock on lips
MX:
prodrome→valacyclovir BID x 1 day
dental/laser procedures prophx→ valacyclovir BID x 14 days (start 24 hours before surgery)
topical acyclovir crm
topical pencyclovir
topical tetracaine
inflammatory rxn prophx→fluocinonide gel 0.05% TID+systemic tx
HSV-2:
NP:
condom use
active lesions→avoid sexual exposure
MX:
PO valacyclovir BID x 7-10 days
6-12 outbreaks/year→PO valacyclovir QD (reduces shedding by 95%)
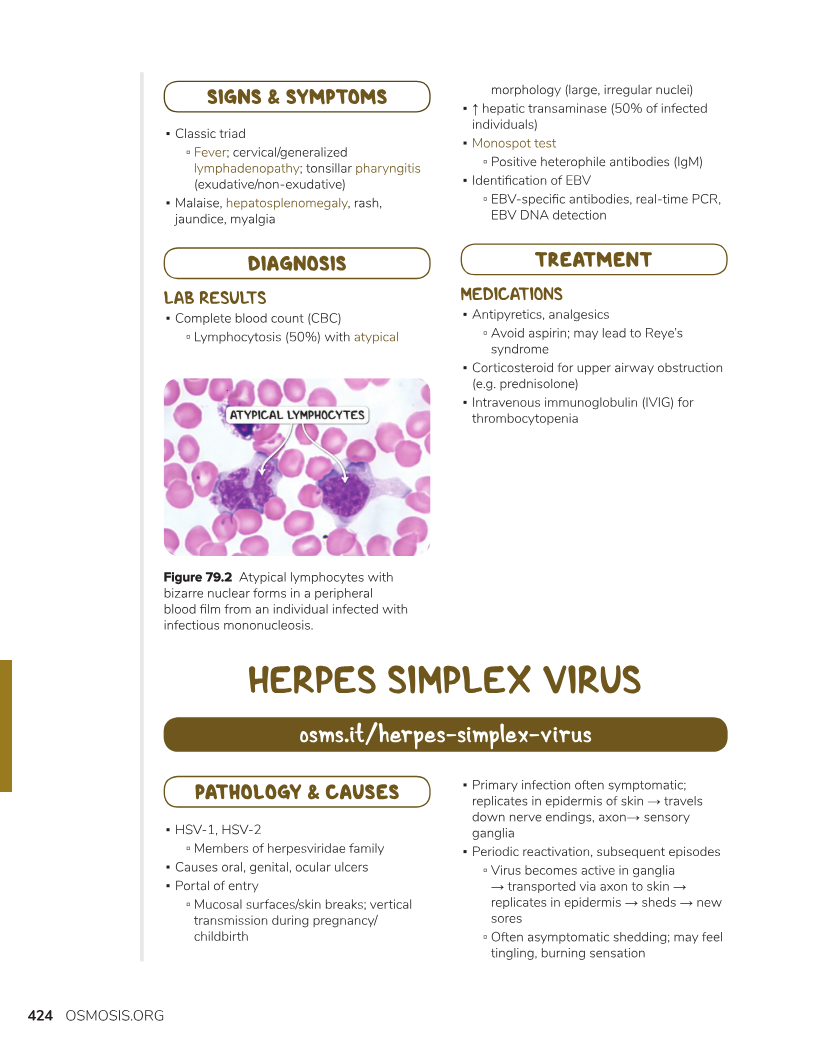
Herpes Zoster/Shingles
PP: reactivation of varicella-zoster virus
E: varicella-zoster virus (VZV)/chicken pox
CM: pain→red papules+plaques→blisters
UL on a dermatome
leukocyte adhesion deficiency (LAD)
elderly→scar
immunocompromised→scar
TX:
NP:
immunocompromised→inpatient tx
varicella-zoster vaccine (recommended for 60+ y/o)
MX:
acyclovir
post-herpetic neuralgia:
PO gabapentin
topical capsaicin
P: eye→temporary/permanent blindness (hutchinson’s sign)
ear→hearing loss (ramsay-hunt syndrome)
20+ lesions outside dermatome→disseminated
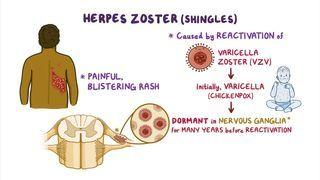
Molluscum Contagiosum
PP: benign contagious viral infection
incubation→2-7 weeks
E: pox virus
CM: white/flesh-colored papules
central umbilication
TX: nothing→goes away on its own
cryotherapy
topical cantharadin
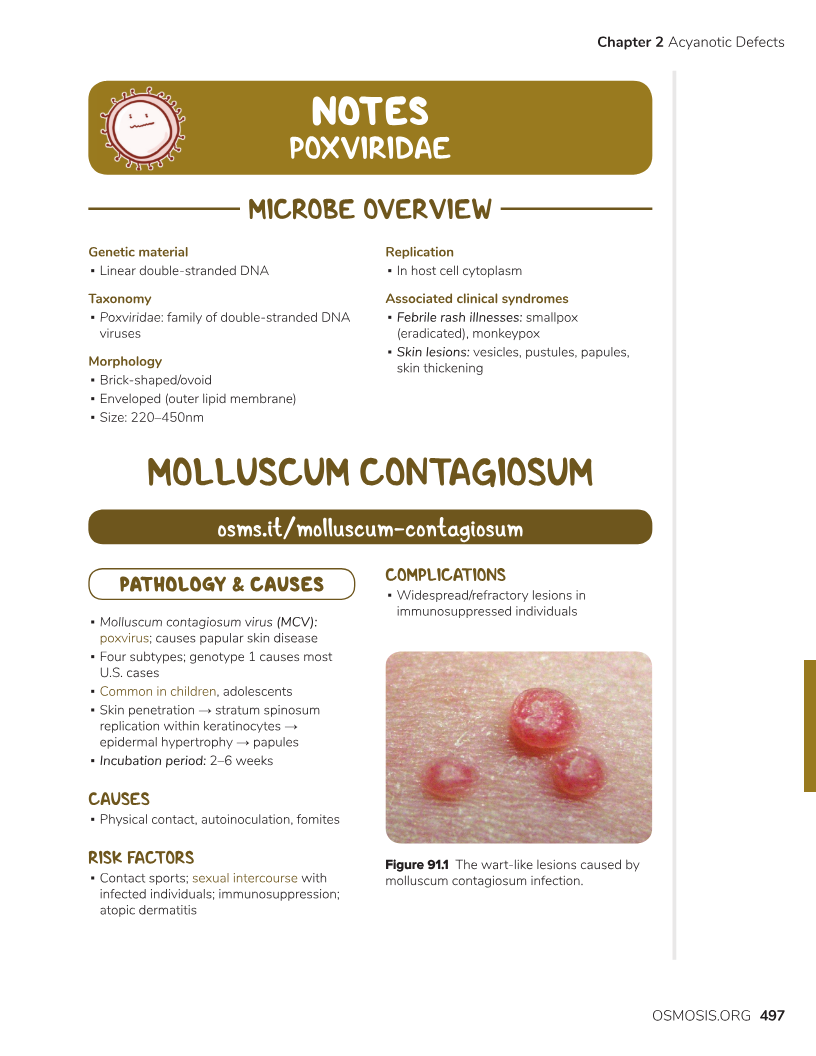
Actinic Keratosis
E: 2nd most common derm dx
sun exposed areas
leukoplakia:
sun
smoking
chronic irritation
CM: firm+rough keratotic papule
erythematous base
leukoplakia:
white patch on mucous membranes (mouth)
more aggressive
DX: unsure+r/o SCC→biopsy
TX:
NP: cryotherapy
photodynamic therapy (PDT)
laser
chemical peel
electrodessication+curettage (ED&C)
MX: topical 5-fluorouracil
imiquimod
P: precursor to squamous cell carcinoma/SCC
normal→30%
leukoplakia→20-40%
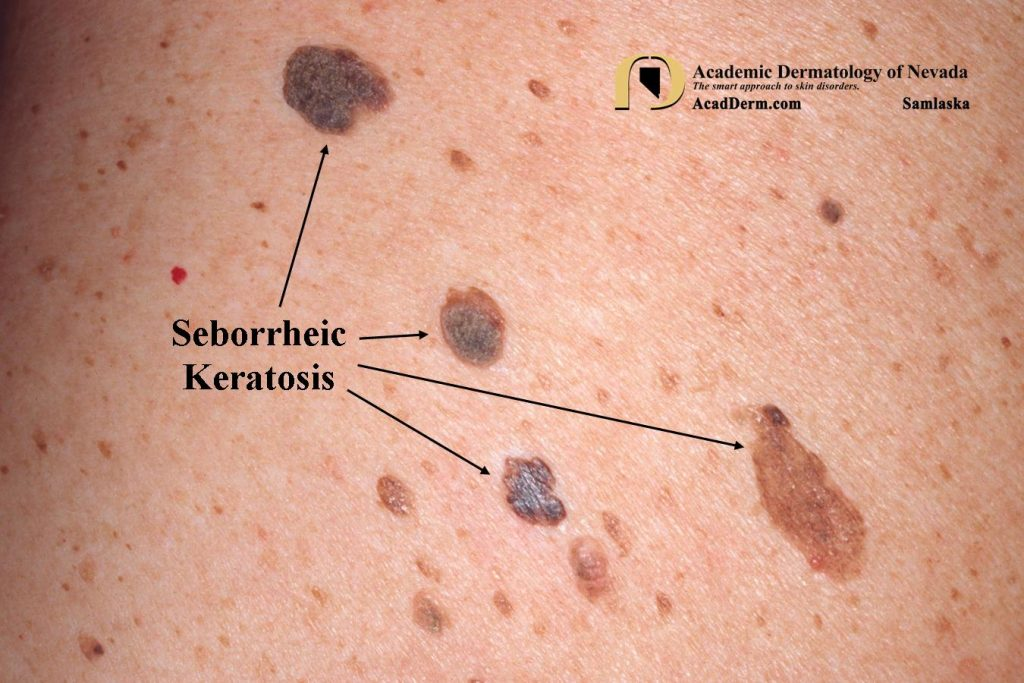
Seborrheic Keratosis
E: very common
CM: papule
-dry
-raised
-“stuck on”
-tan/brown/black
-sharply demarcated
Lesar Trelat sign: sudder appearance of multiple SKs→internal malignancy
TX: cryotherapy
curettage
Benign Nevus
mole/freckle
benign
symmetric/evenly-pigmented macule/papule
new nevi after 30 minutes in sun→suspicious
blue nevus: melanocytes in dermis
becker’s nevus:
present at birth
appear with puberty
males
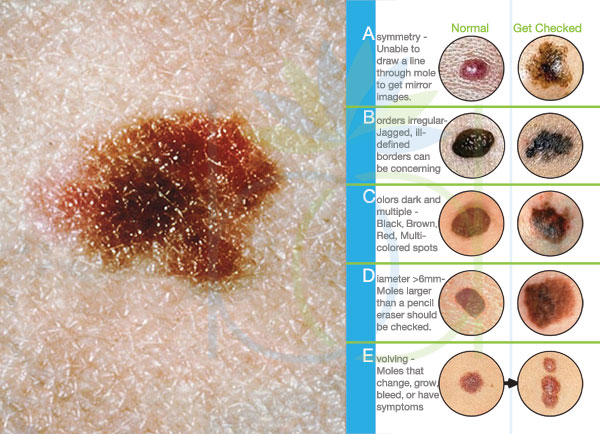
Atypical/Dysplastic Nevi DX
5-10% has at least 1 atypical nevus
increased number→increased melanoma risk
ABCDE rule:
Asymmetry
Border irregularity
Color variation
Diameter (greater than 6mm+)
Evolution
history:
especially past bleeding/ulceration hx
single most historical reason for close eval/referral
biopsy:
shave biopsy
punch biopsy
moderately atypical→normal removal/monitoring
severely atypical→remove with 5mm margins
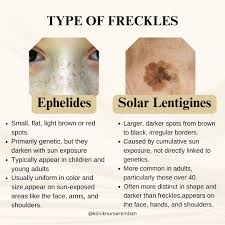
Ephelides/Freckles
E: sun-exposed areas
young children
genetics
CM: flat brown macules
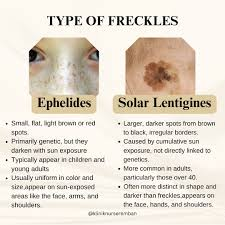
Lentigines/Sun Spots
E: sun-exposed areas
adults
photoaging
CM: flat brown macules
don’t fade with no sun exposure
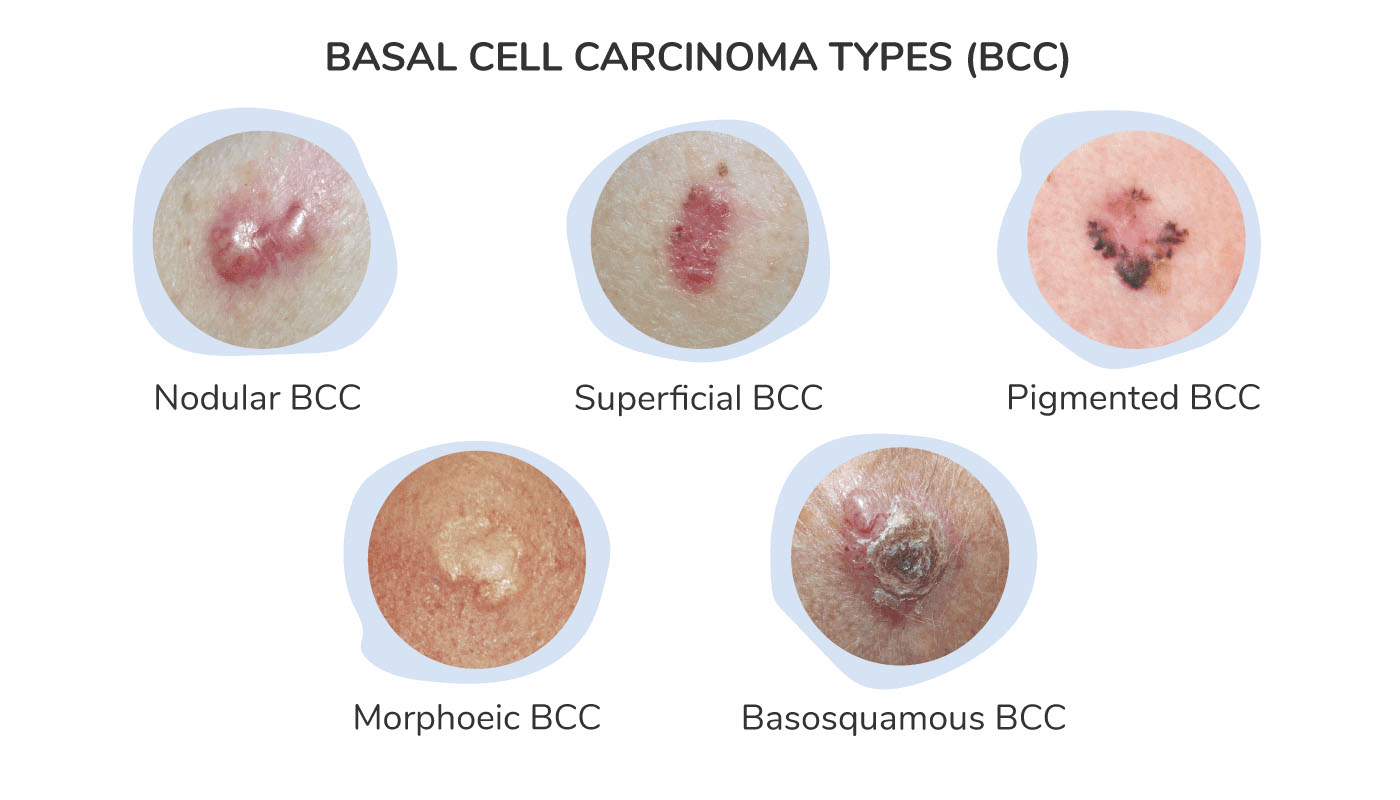
Basal Cell Cancer
PP: locally invasive
rarely metastasizes
RF: sun-exposed/damaged areas
elderly
males
fair skin
previous skin injury
thermal burn
CM: “lesion that won’t heal+keeps bleeding”
nodular (most common)
superficial (least aggressive)
sclerosing (most aggressive)
pigmented (confused with melanoma)
TX:
NP:
surgical excision
electrodessication+curettage (ED&C)
moh’s surgery
radiation
MX:
imiquimod cream
PO vismodegib x lifelong
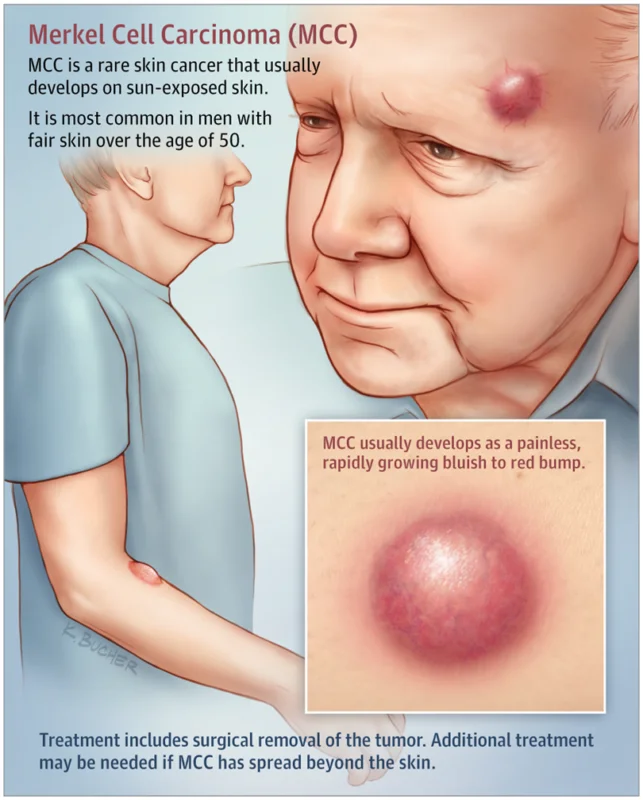
Merkel Cell Carcinoma
PP: pink nodule
solitary
rapidly growing
E: extensive actinic damage
older
head
neck
DX: sentinel lymph node biopsy (SLNB)
TX: wide excision
radiation
P:
40%→distant metastases→18% survival
under 2 cm+no metastases→70% 5+ years survival
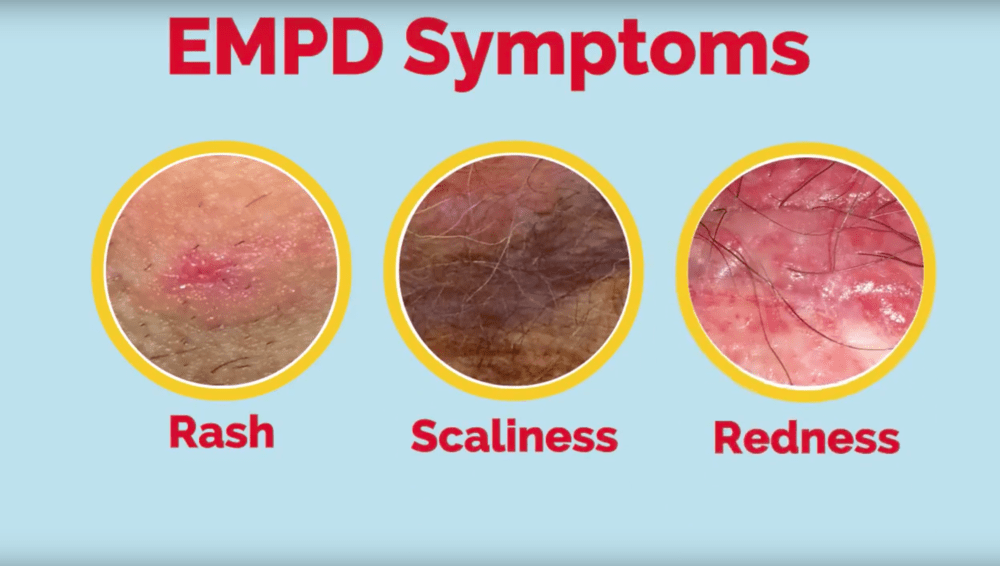
Mammary vs Extramammary Paget Disease
mammary:
unilateral
hyperpigmented in beginning→nipple eczema-like
extramammary:
genitalia
starts from intraepidermal carcinoma/GI cancer
eczema-like
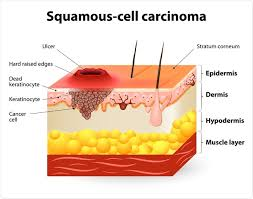
Squamous Cell Cancer
RF: sun exposure
fair skin
HPV infection
radiation exposure
sunburns
E: 2nd most common skin cancer
actinic keratosis
sun-exposed areas
chronic trauma
inflammation
genitalia
oral mucosa
CM:
bowen’s disease: SCC in situ
keratoacanthoma (KA):
appears suddenly
grows rapidly
TX:
mohs surgery
surgical excision
in-situ→electrodessication and curretage (ED&C)
no surgery→radiation therapy
P: 45%→metastasis
early intervention→high cure rate
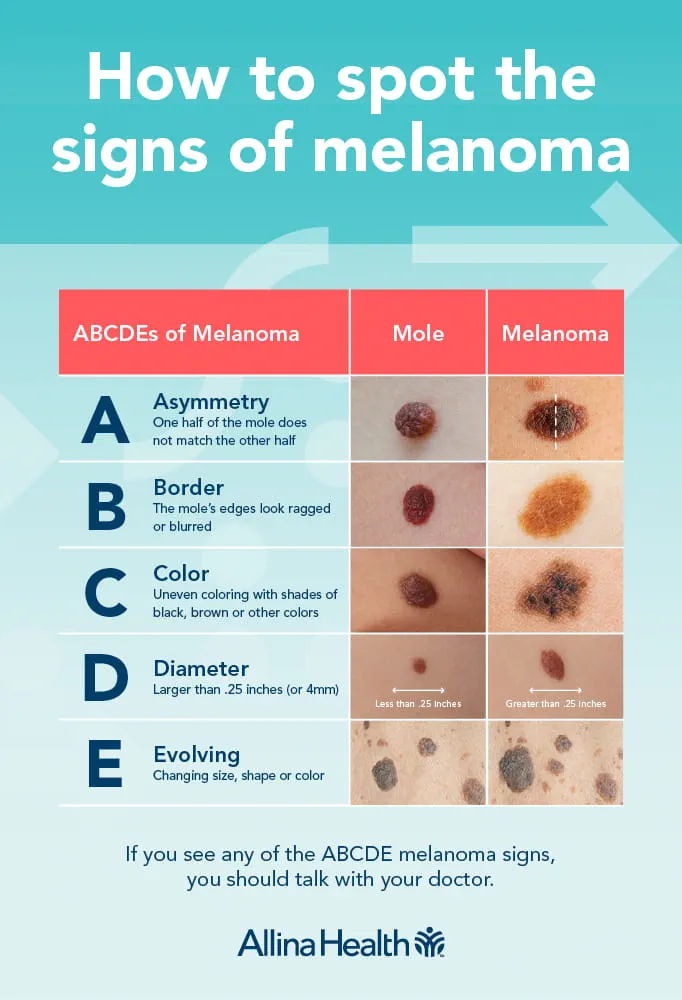
Melanoma
PP: malignancy of melanocytes in skin
half-develop from pre-existing nevi in normal-appearing skin
RF: atypical nevi
fair skin
family hx
sunburns (5+/1 blistering→2x risk)
E: women
25-29 y/o
CM:
lentigo maligna
older patients
heavily sun-damaged skin
tan macule→spreads+darkens
5+ years→invasive
superficial spreading
most common
any form of skin
upper back
multicolored
acral-lentiginous
dark skin+asian
periungual hyperpigmentation (dark pigment under nails)
hutchinson’s sign (pigmented streak+black color on proximal nail fold)
nodular
smooth+dome shaped tumors
sun-exposed areas
bleeding→late sign
amelanotic:
non-pigmented
pink/erythematous/flesh-colored
DX:
ABCDE
asymmetry
border irregularity
color variation
diameter over 6mm
evolution (metastasis)
1mm+ thickness→sentinel lymph biopsy
TX:
early (5-20mm)→surgical excision
metastatic
NP: radiation
chemotherapy
MX: ipilimunab+nivolumab
P: deadliest skin cancer
deeper→worse prognosis
metastatic→6-9 months
metastatic 5 year survival rate→under 20%
Melanoma Histopathology
breslow depth+ulceration→tumor stage
ulceration
top layer breaks/pulls apart→poor prognosis
mitosis
increased mitosis rate→decreased survival rate
margin status
surgeon gets/doesn’t get clear margins
Melanoma Prophylaxis+Patient Education
lab work not effective
many dysplastic nevi→full body photography
skin checks:
1st year→every 3 months
after 1st year→every 6 months
all 1st degree relatives
melanoma risk→ +0.5% every year
pt education:
risk+prevention (spf protection)
monthly skin exam
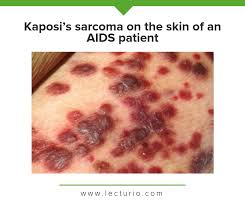
Kaposi Sarcoma
PP: malignancy of vascular endothelial cells
E: AIDS-associated
skin
mucosa
lymph nodes
GI tract
CM: reddish/blue-black macules/patches→spread+coalesce→nodules/plaques+edema
TX: surgical excision
radiation therapy
laser ablation
injected chemotherapy
P: slow progression
deaths due to other causes
AIDS→intercurrent/secondary infection→death
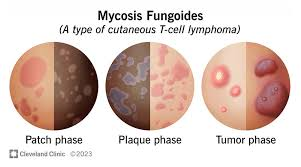
Mycosis Fungoides
PP/E: cutaneous T-cell lymphoma
skin→dormant for years (or)→progresses to systemic disease
CM: scaly patches/plaques on trunk
itchy
localized/systemic
erythematous
DX: multiple punch biopsies
TX: topical chemotherapy
UV light phototherapy
systemic chemotherapy
immunotherapy
topical steroids
commonly mistaken for eczema/tinea/psoriasis
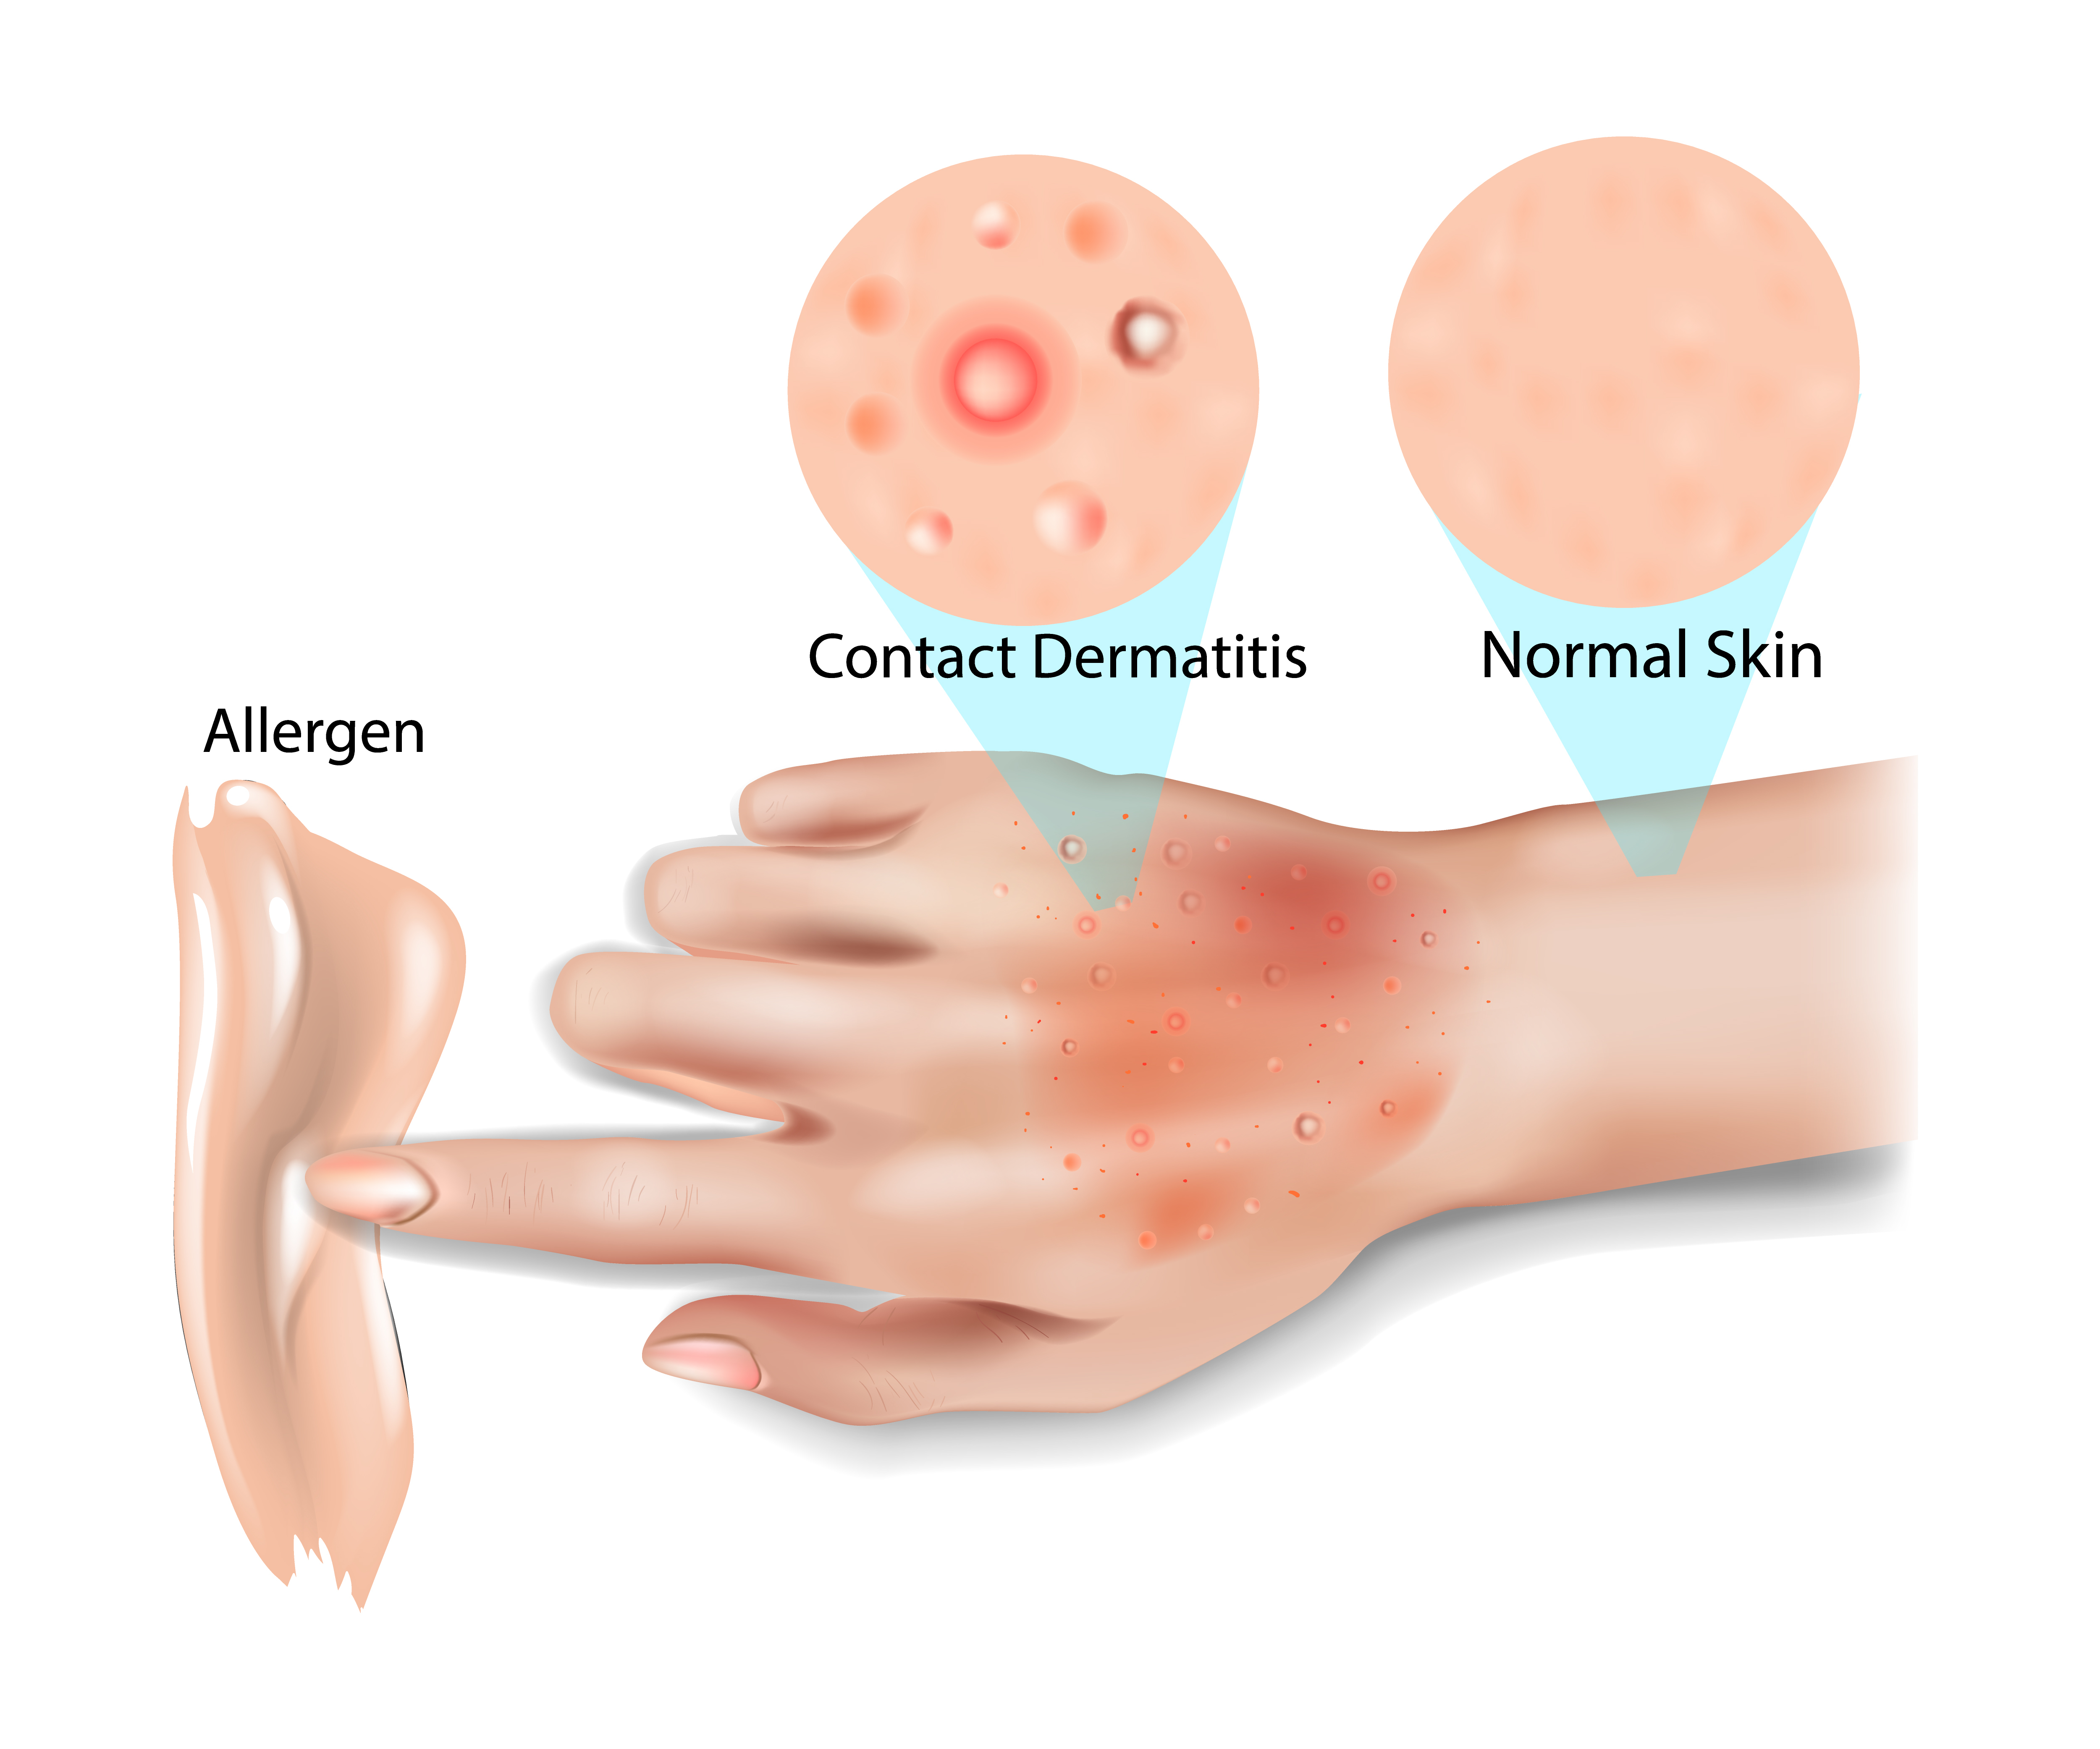
Contact Dermatitis
PP/E: direct skin contact with irritant/allergen
irritant
nonspecific inflammatory skin reaction
bleach
allergic
hypersensitivity to allergy
poison ivy
TX: discontinue contact with offending agent+topical steroids
Dermatitis Medicamentosa
PP: adverse skin reaction to medication
E: NSAIDS
antimicrobials
cytokines
anticonvulsants
psychotropic agents
chemotherapeutic agents
CM: symmetric drug rash
morbiliform
pustules
urticaria
pruritus
dysethesia (pain to light touch)
arthralgia
fever
headache
malaise
DX: histology
skin biopsy
P: discontinue mx→resolves on own
mild+self-limiting
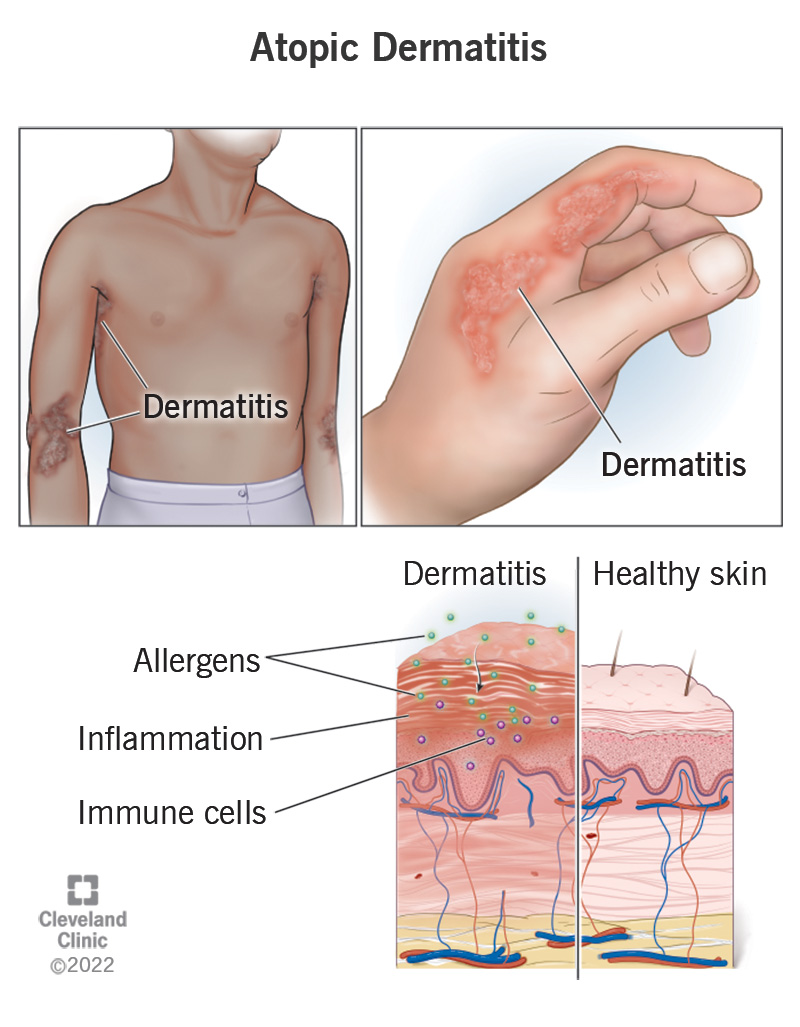
Atopic Dermatitis PP/E/CM
PP: chronic inflammatory skin disease
RF: asthma
allergic rhinoconjunctivitis
atopic disorders
food allergy (35%)
2+ household smoker
cats
E: genetic
unknown
1st world country kids→30%
1 y/o→50%
CM: pruritis
chronic exacerbations+remissions
acute: plaques
red
thin
scaly
chronic: plaques+excoriations
thick
scaly
infants
face
extensor surfaces
children
flexor surfaces
adults
localized
POC
lichenification
prurigo-like lesions
hyperpigmentation
Atopic Dermatitis TX
NP
pt education
repair skin barrier→prevent outbreaks
moisturizer after baths
decrease number+length+temperature of baths
allergen-free detergents
cotton clothing
humidifier
no food restriction diet
severe→allergist referral
MX
mild-moderate:
mild
topical hydrocortisone 2.5% BID x up to 2 weeks
moderate
topical triamcinolone 0.1% BID x up to 2 weeks
topical tacrolimus QD x up to 6 weeks
topical pimecrolimus QD x up to 6 weeks
topical ruxolitinib
cetirizine
hydroxyzine
infection
topical abx
PO abx
moderate-severe:
1st line→SQ duplimab x 2-4 weeks
2nd line:
baricitinib
abrocitinib
upadacitinib
PO prednisone
narrow band UVB x 3x/week
PO cyclosporine
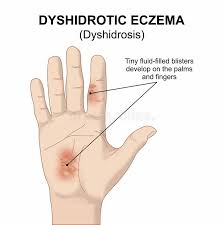
Dyshidrosis/Dyshidrotic Eczema
PP: recurrent vesicular hand eczema
thick acral skin→edema→vesicles
E: stress
allergy
irritants
CM: firm+pruitic vesicles on palms (more common)+soles (less common) on medial/lateral aspects of digits
“tapioca pudding”
DX: rule out contact dermatitis
TX:
NP
pt education
repair skin barrier→prevent outbreaks
moisturizer after baths
decrease number+length+temperature of baths
allergen-free detergents
cotton clothing
humidifier
no food restriction diet
severe→allergist referral
MX
mild-moderate:
mild
topical hydrocortisone 2.5% BID x up to 2 weeks
moderate
topical triamcinolone 0.1% BID x up to 2 weeks
topical tacrolimus QD x up to 6 weeks
topical pimecrolimus QD x up to 6 weeks
topical ruxolitinib
cetirizine
hydroxyzine
infection
topical abx
PO abx
moderate-severe:
1st line→SQ duplimab x 2-4 weeks
2nd line:
baricitinib
abrocitinib
upadacitinib
PO prednisone
narrow band UVB x 3x/week
PO cyclosporine
Lichen Simplex Chronicus
PP: chronic rubbing+scratching→beyond normal pain threshold→thick+leathery skin+exaggerated skin markings
E: neck (back+sides)
wrists
ankles
gradual insidious onset
skin site of another condition
CM: thick+leathery skin
exaggerated skin markings→lichenification
TX:
high potency topical steroid + temporary
steroid tape
intra-lesional kenalog
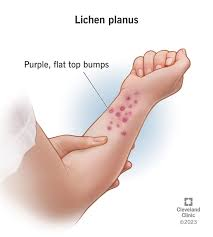
Lichen Planus
PP: inflammatory disease of skin+mucous membranes+hair follicles
mucous membranes→malignancy risk
E: T-cell mediated immune reaction
acute or chronic
Hepatitis C infection
CM: white lines→whickam striae
DX: 4 P’s
purple
polygonal
pruritic
papules
TX:
NP:
self-limiting x 8-12 months
phototherapy
MX:
superpotent topical steroids
superpotent intralesional steroids
mouth→benzocaine
systemic: isotretinoin
acitretin
cyclosporines
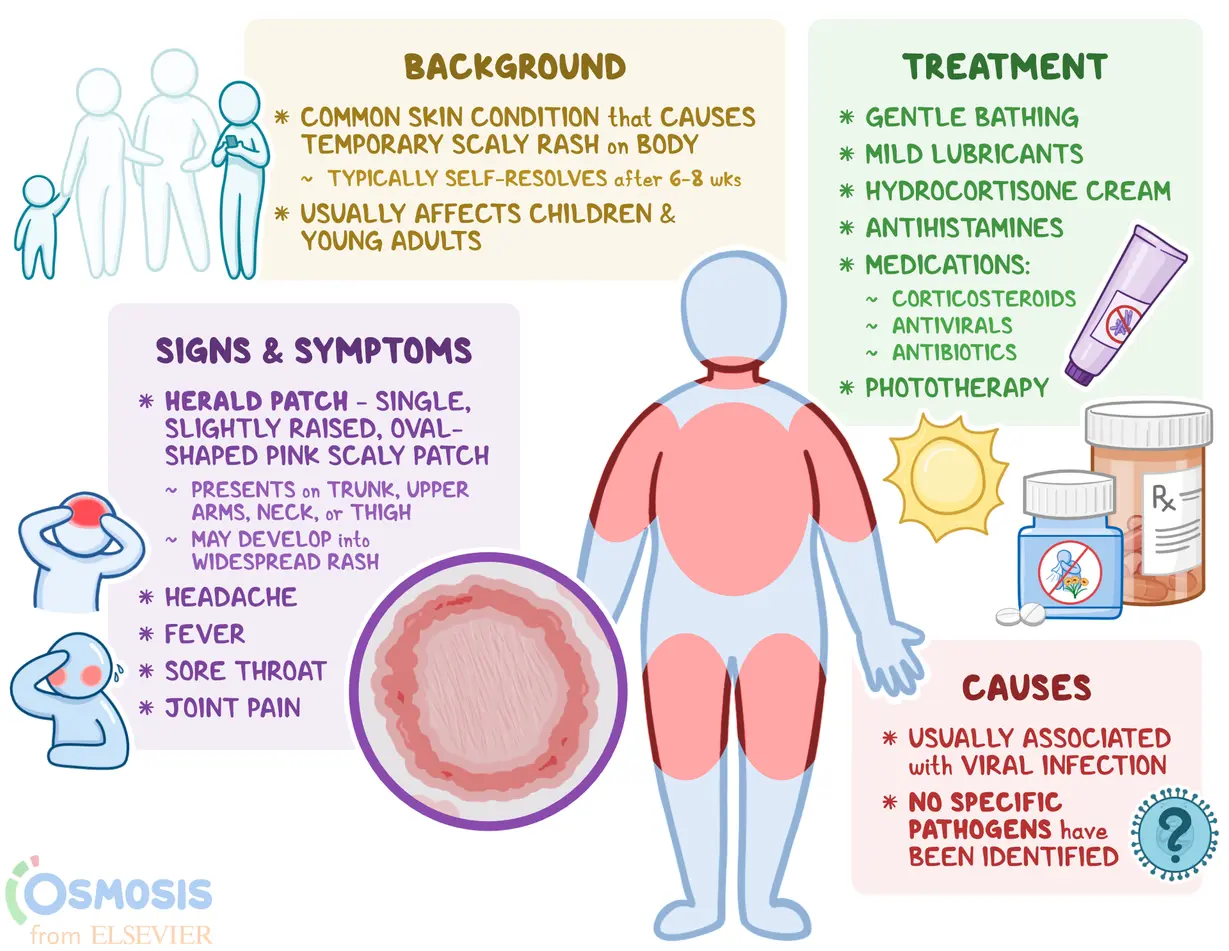
Pityriasis Rosea
PP/E: subclinical viral infection/adverse mx reaction→mild inflammatory exanthem
CM: salmon-colored+fine scale papules+macules
singular herald patch→more appear
“christmas tree” distribution pattern
TX: none
itch→topical steroid
self-limiting x after 3-8 weeks
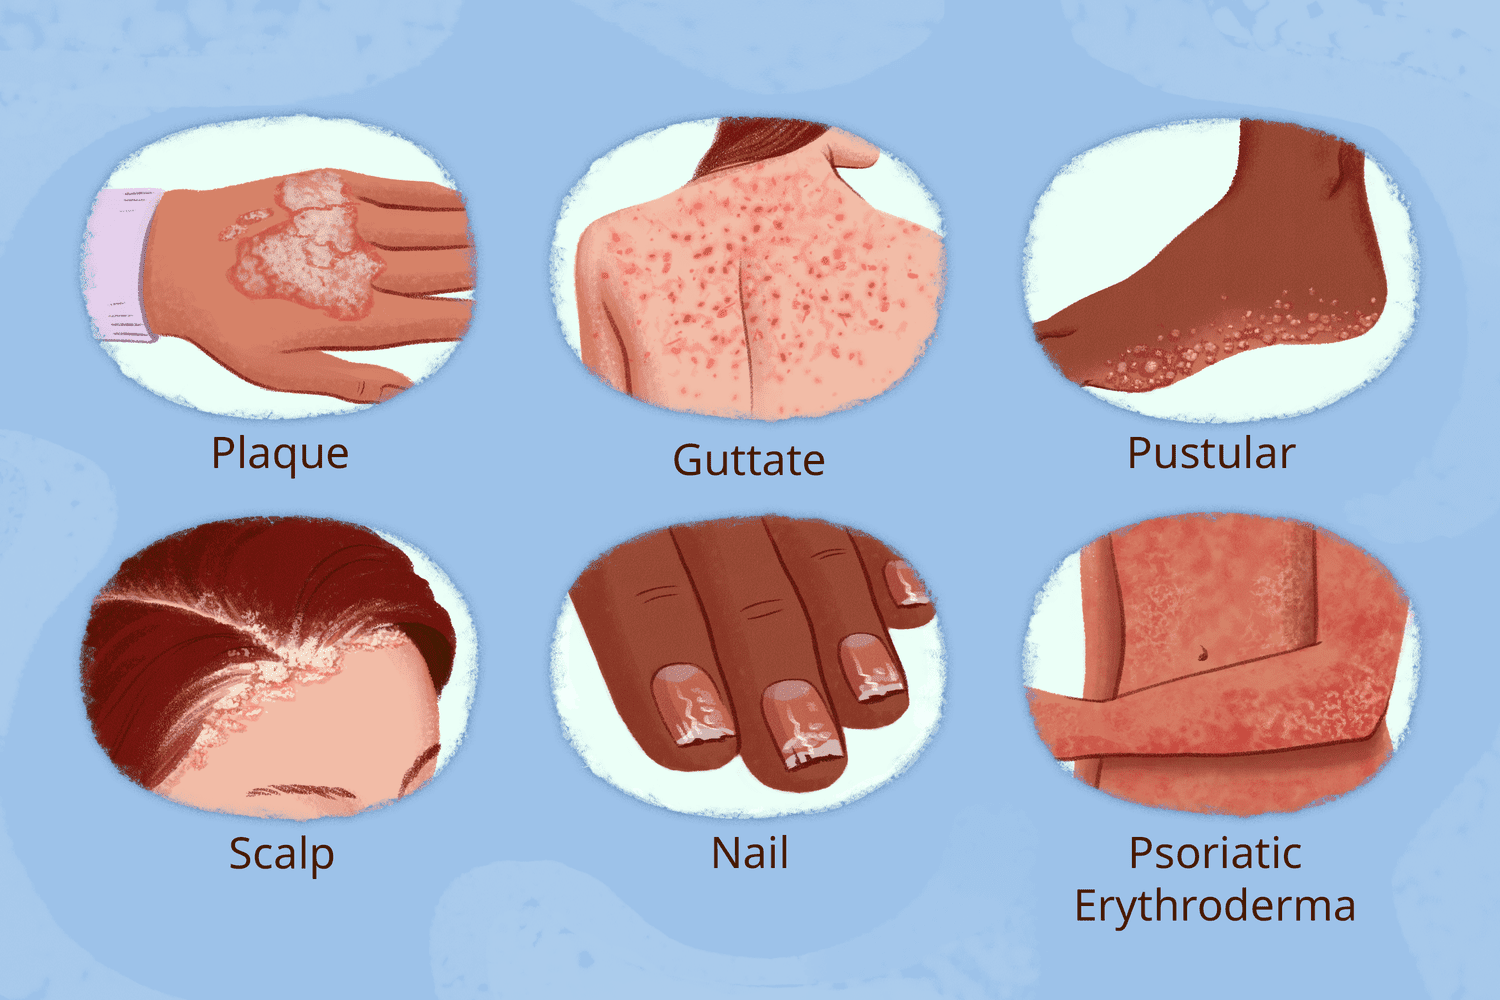
Psoriasis (General)
PP: chronic/recurrent inflammatory disease
E: common
scalp
nails
extensor surfaces
umbilical region
sacrum
1-3% of population
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
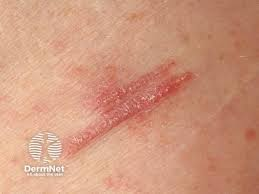
Koebner Phenomenon (Psoriasis)
PP: post-traumatic psoriatic phenomenon
E: trauma
CM: trauma to skin→plaque
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
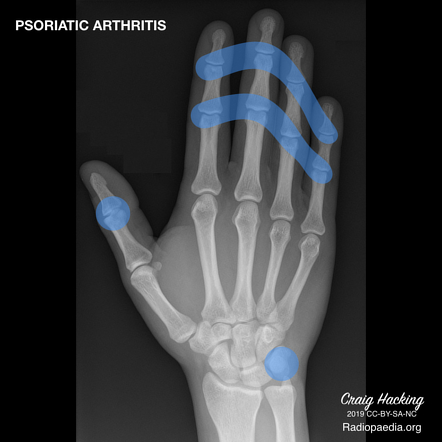
Psoriatic Arthritis
PP: arthritis+psoriasis
E: distal interphalangeal joint (DIPJ)
DX:
Xray→“pencil in a cup” deformity
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
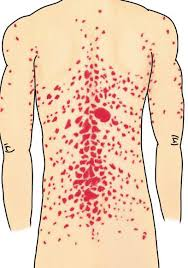
Psoriasis Guttate
PP: post group A strep pharyngitis infection→abrupt eruption
E: group A strep pharyngitis
CM:
numerous salmon pink papules+fine scale
“drop-like”
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
Inverse Psoriasis
PP: psoriasis under folds
E: folds
-ears
-axillae
-groin
-intergluteal crease
-penis
CM: mimics candida infection
Dx: KOH→negative
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
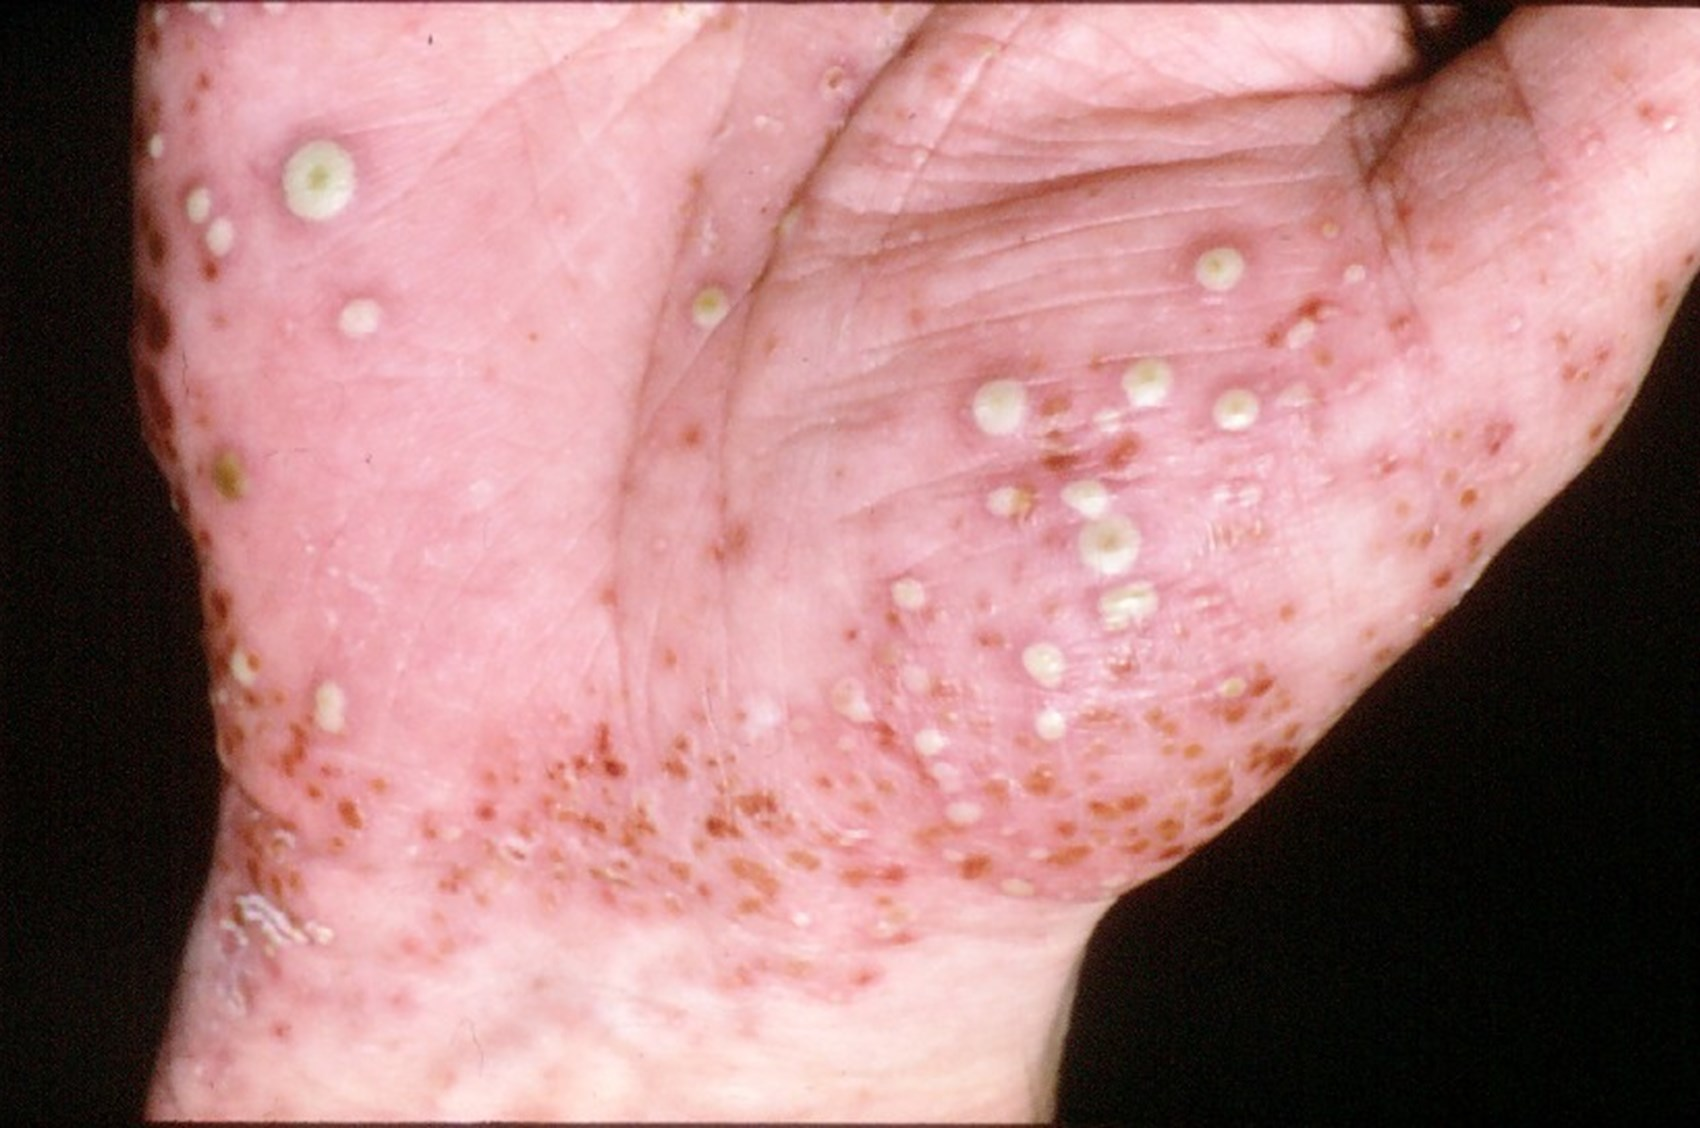
Pustular Psoriasis
PP: psoriasis+pustules
E: tobacco
CM:
sterile+red+scaly pustules
-palms
-soles
-nails
DX: “oil-drop” sign
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
Chronic Plaque Psoriasis
E: most common type of psoriasis
CM: “silvery” scaling plaques
circumscribed
erythematous
dry
extensor surfaces:
-elbows
-knees
-scalp
-sacrum
auspitz sign:
pick at silver scales→blood
TX:
topical:
1st line→topical steroids
topical calcipotriene
anthralin+coal tar
narrow band UV x 3x/week
systemic:
methotrexate
acute→cyclosporine+taper off
PO acitretin
apremilast
Biologics:
TNF alpha inhibitors:
-entanercept
-adalimumab
interleukin 12+23 inhibitor:
-ustekinumab
interleukin 17 inhibitors:
-ixekizumab
-secukinumab
interleukin 23 inhibitor:
-guselkumab
-risankizumab
-tildrakizumab
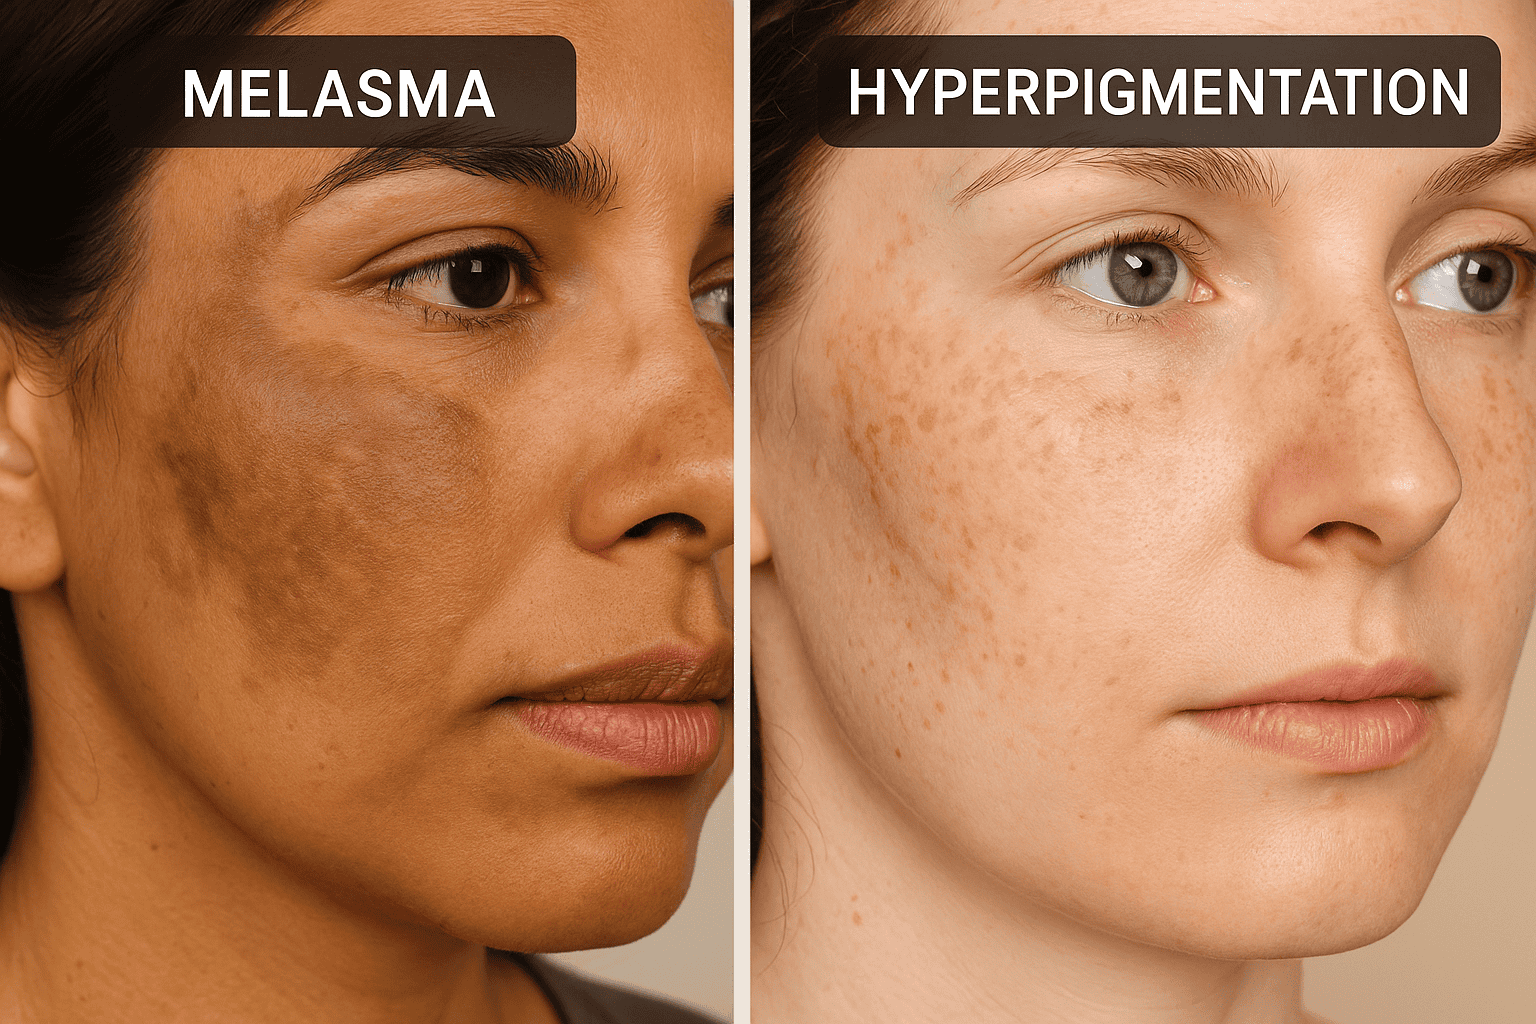
Melasma
PP: acquired symmetric hyperpigmentation
E: hormone sensitivity
birth control
pregnancy (“mask of pregnancy”)
face
sun exposure→worsens sx
TX: difficult
peels
lasers
topical hydroquinone
topical tretinoin
prophx/prevention of worsening sx→spf sun protection
Vitiligo/“Michael Jackson’s Skin Condition”
PP: acquired pigmentary anomaly
E: childhood
mx-induced
CM: depigmented white patches surrounded by normal/hyperpigmented border
DX: wood’s lamp
TX:
nontreatment option→fitzpatrick 1-2 only
NP:
narrow band UVB x 2x/week
MX:
topical pimecrolimus
topical tacrolimus
calcipotriene
topical ruxolitinib
PO baricitinib
total depigmentation (50-80% BSA gone)→monobenzone
P: psychological effect
spontaneous repigmentation→15-25% of cases

1st Degree Burn
PP: minor epidermal damage
E: m/c→scalding
CM: erythema
tenderness
no bullae
DX: hematocrit
electrolytes
BUN
creatine
urinalysis
chest radiography
arterial blood gas
EKG
electrical energy levels on the skin do not match how severe the actual injury is
TX:
NP:
chemical→stop burning
maintain ABCs
estimate % of burn
-palm of hand=1%BSA
manage shock:
aggressive fluid resuscitation
NG tube
foley catheter
MX: topical sulfadiazine
C: inhalation injury
hypovolemic shock
neurogenic shock
renal failure
multiorgan system dysfunction
infection
chronic healing wounds→malignancy to SCC
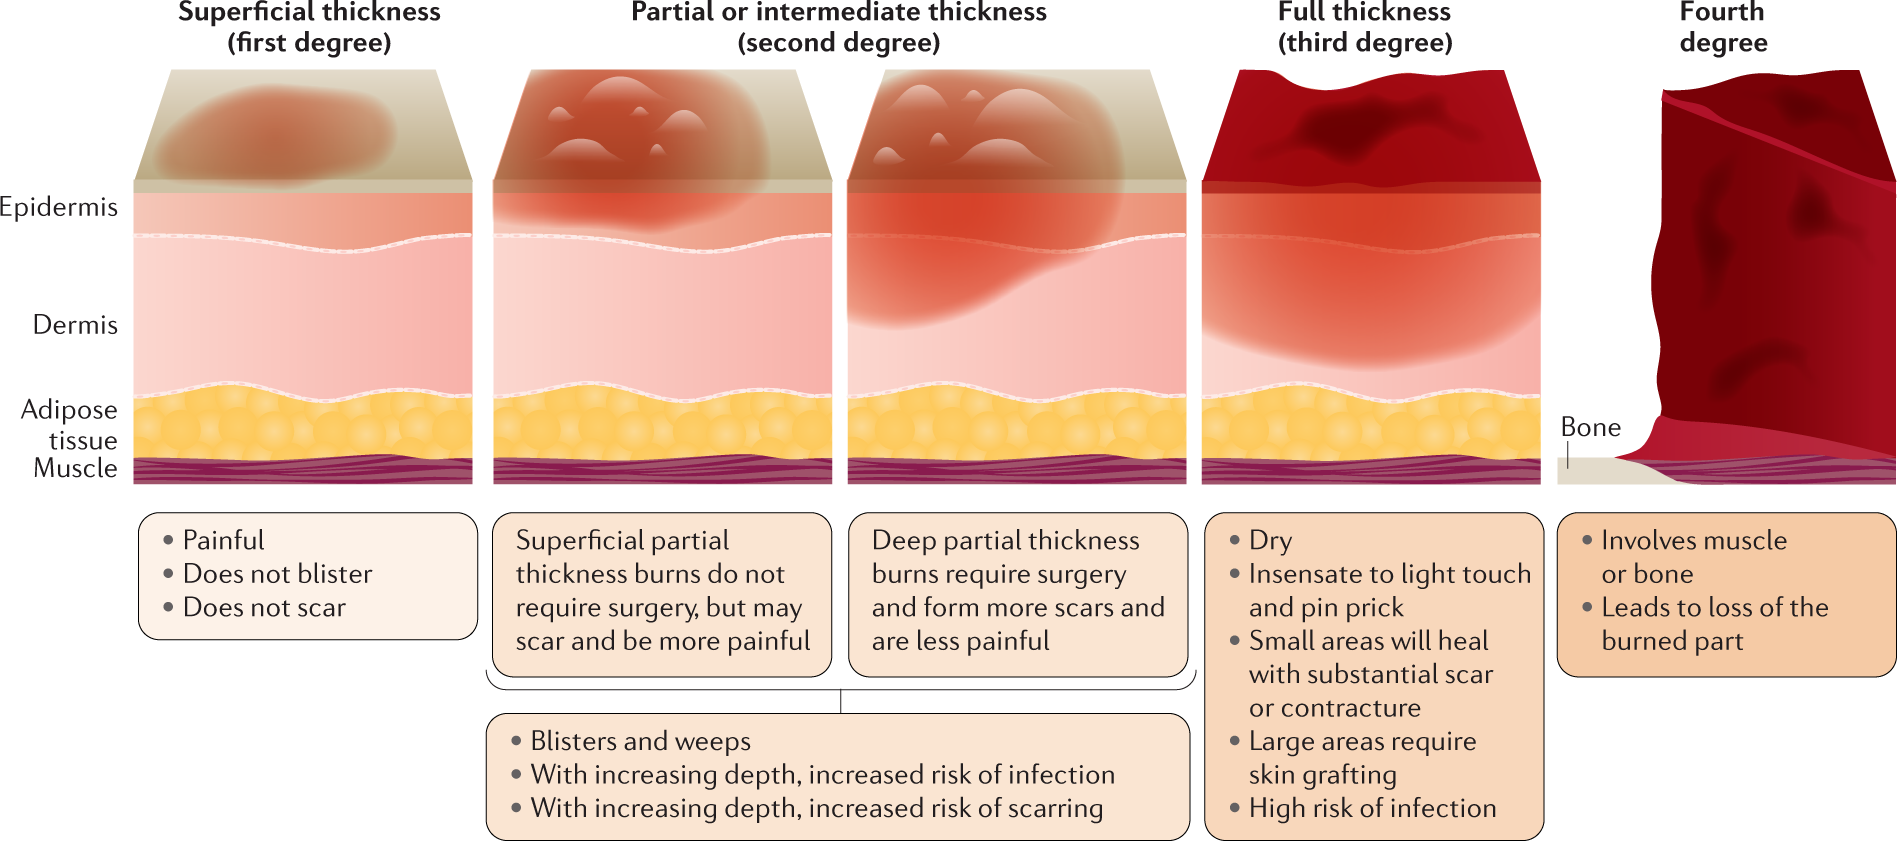
2nd Degree Burn
E: superficial partial-thickness→papillary dermis
deep superficial→reticular dermis
CM:
partial-thickness:
extends to papillary dermis
thin-walled blisters
moist
blanching
pain
deep:
extends to reticular dermis
thicker-walled blisters→rupture
erythema
pallor
pressure→pain
DX: hematocrit
electrolytes
BUN
creatine
urinalysis
chest radiography
arterial blood gas
EKG
electrical energy levels on the skin do not match how severe the actual injury is
TX:
NP:
chemical→stop burning
maintain ABCs
estimate % of burn
-palm of hand=1%BSA
manage shock:
aggressive fluid resuscitation
NG tube
foley catheter
MX: topical sulfadiazine
C: inhalation injury
hypovolemic shock
neurogenic shock
renal failure
multiorgan system dysfunction
infection
chronic healing wounds→malignancy to SCC
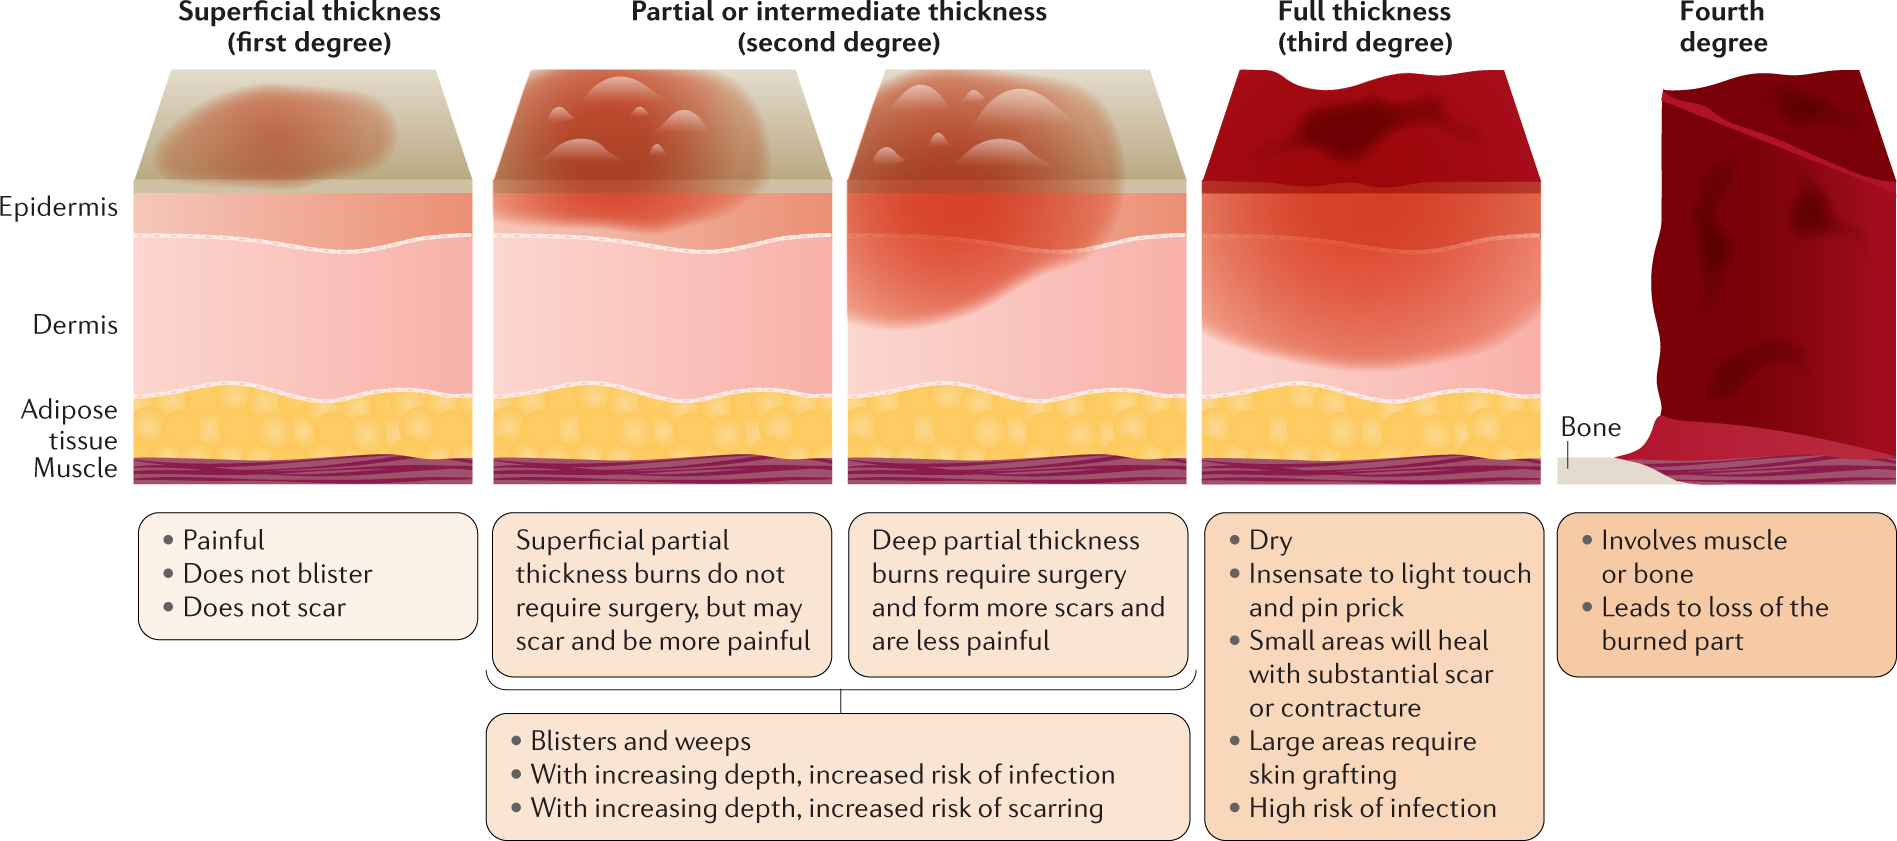
3rd Degree Burn
PP: full thickness
destroys epidermis+dermis
CM: white
leathery
or
charred
dry without sensation
DX: hematocrit
electrolytes
BUN
creatine
urinalysis
chest radiography
arterial blood gas
EKG
electrical energy levels on the skin do not match how severe the actual injury is
TX:
NP:
chemical→stop burning
maintain ABCs
estimate % of burn
-palm of hand=1%BSA
manage shock:
aggressive fluid resuscitation
NG tube
foley catheter
MX: topical sulfadiazine
C: inhalation injury
hypovolemic shock
neurogenic shock
renal failure
multiorgan system dysfunction
infection
chronic healing wounds→malignancy to SCC
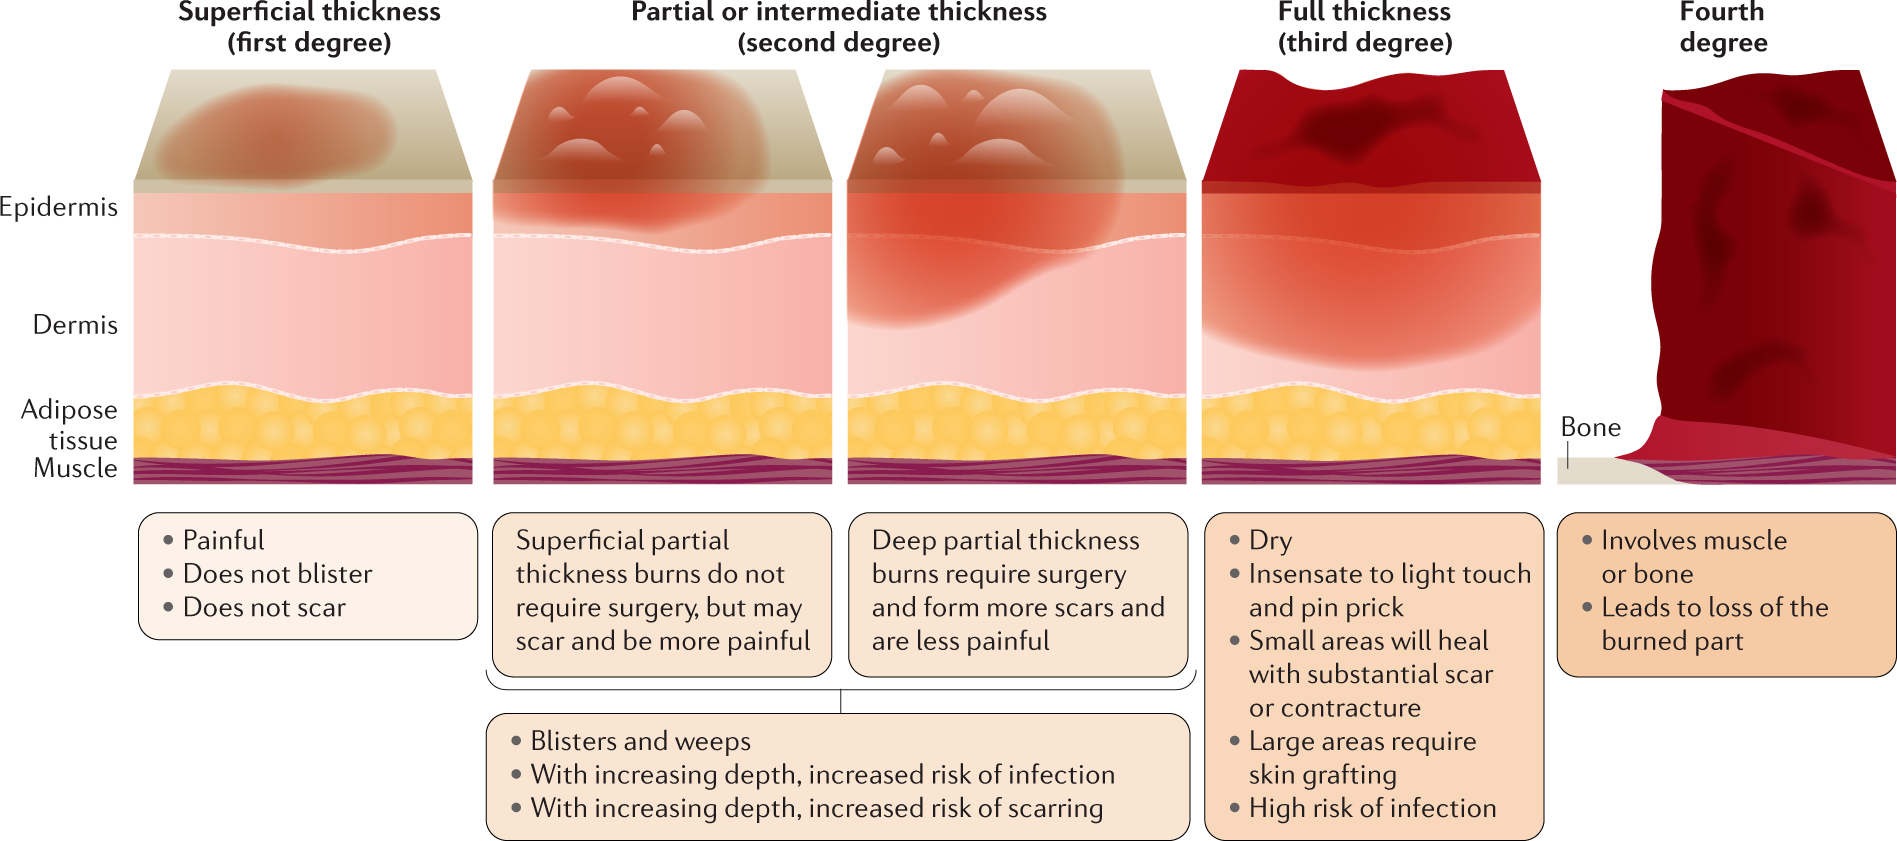
4th Degree Burn
PP: destroys skin+subcutaneous tissue
fascia/muscles/bone exposed
CM: significant charring
exposure of muscle/bone
extensive damage to nerves
little to no pain/sensation
DX: hematocrit
electrolytes
BUN
creatine
urinalysis
chest radiography
arterial blood gas
EKG
electrical energy levels on the skin do not match how severe the actual injury is
TX:
NP:
chemical→stop burning
maintain ABCs
estimate % of burn
-palm of hand=1%BSA
manage shock:
aggressive fluid resuscitation
NG tube
foley catheter
MX: topical sulfadiazine
C: inhalation injury
hypovolemic shock
neurogenic shock
renal failure
multiorgan system dysfunction
infection
chronic healing wounds→malignancy to SCC
C: inhalation injury
hypovolemic shock
neurogenic shock
renal failure
multiorgan system dysfunction
infection
chronic healing wounds→malignancy to SCC
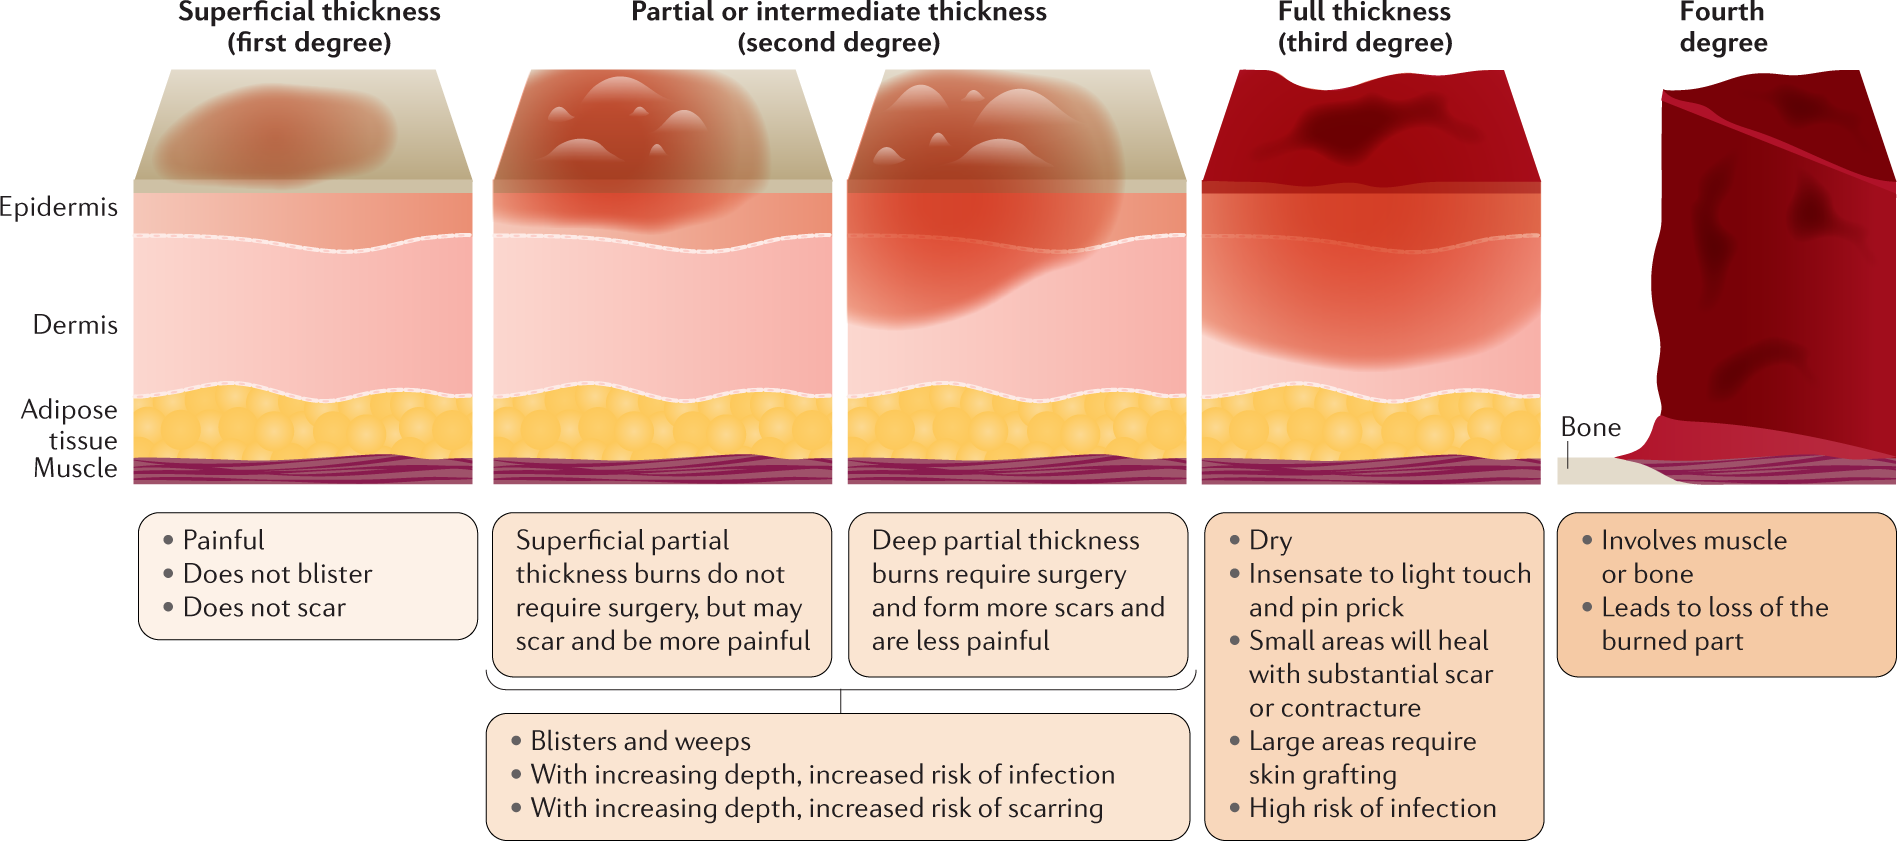
Lacerations
PP: damage penetrating under the skin
E:
laceration:
tearing of soft body tissue
irregular+jagged
often contaminated
puncture:
sharp pointy object (nail/teeth/etc.)
prone to infection
TX: stop bleeding
clean sutures
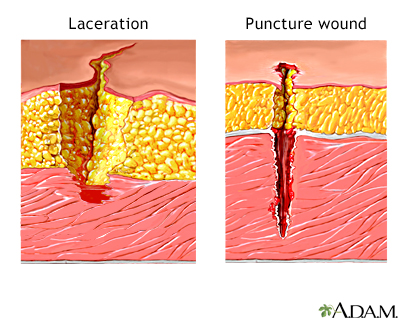
Pressure Ulcers
PP: areas of pressure+limited mobility→decubitus ulcers
E: localized pressure→impaired blood supply
sacrum
lip
CM/DX:
stage 1: nonblanching erythema of intact skin
stage 2:
necrosis
superficial/partial thickness
epidermis
±dermis
shallow ulcer
stage 3:
deep necrosis
crater ulcer
full thickness skin loss
damage/necrosis
no fascia involvement
stage 4:
full-thickness ulceration
extensive damage+necrosis to muscle/bone/supporting structures
TX:
NP: prophx
repositioning
massaging
minimize friction
ulcer:
moist sterile gauze
surgical debridement
MX: only if sx of infection are present
topical abx
PO abx
C: osteomyelitis
bacteremia
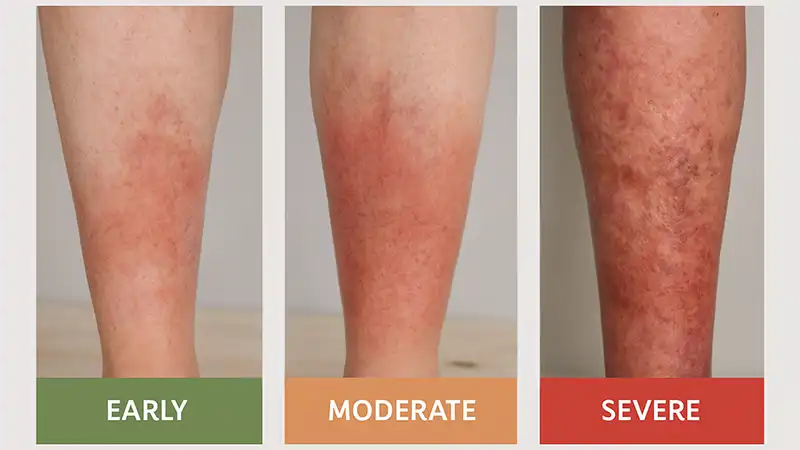
Stasis Dermatitis
PP/E: chronic venous insufficiency→edema→stasis dermatitis
CM: hyperpigmentation
ulcerations
prophx→varicose veins
PE:
heaviness+aching in legs
increased→standing
decreased→leg elevation
TX:
NP: compression stockings
vascular surgery
ulcers→chronic tx
MX: topical triamcinolone BID x 2 weeks on/off
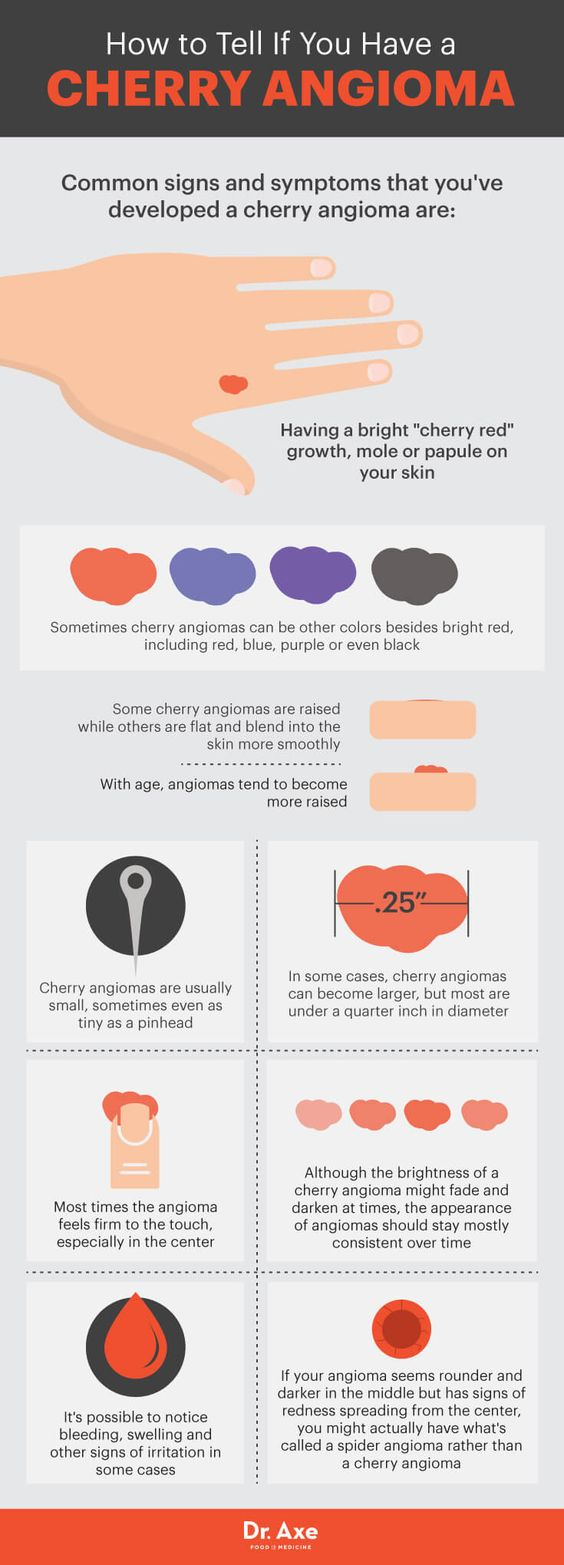
Cherry Angioma
PP: benign vascular papule
E: proliferating endothelial cells
lines the inside of blood vessels
unknown
CM: bright red papule
TX: none
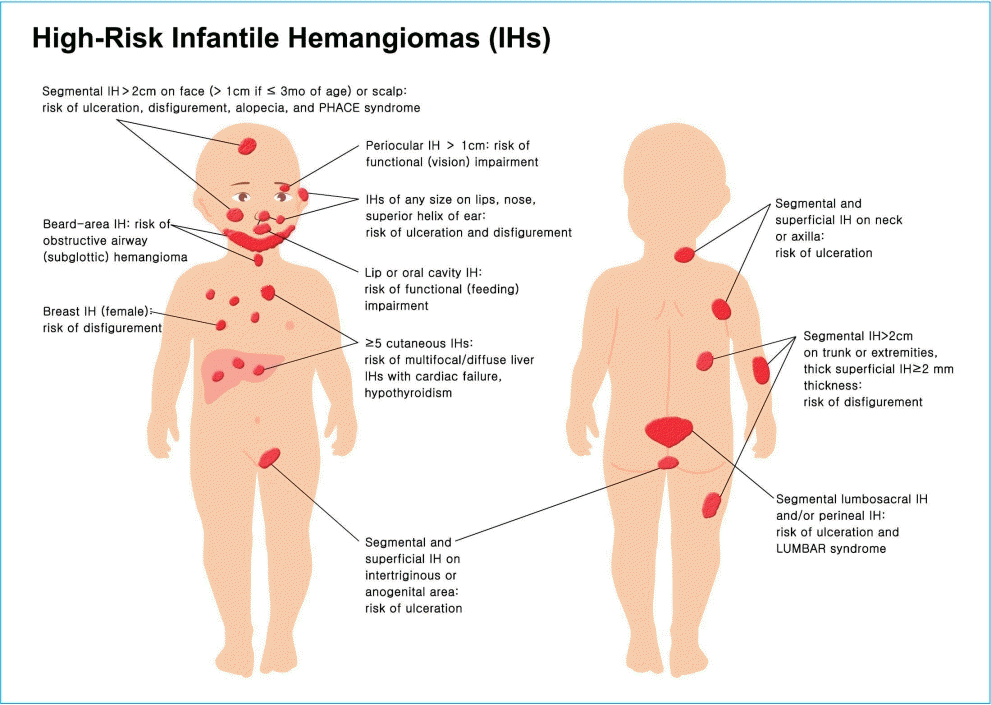
Infantile Hemangioma/Large Cherry Angioma
PP: benign vascular tumor
CM: large red papule/patch
TX:
NP:
serial observation
surgery
laser
embolization
MX:
topical timolol
PO propanolol x after feeding
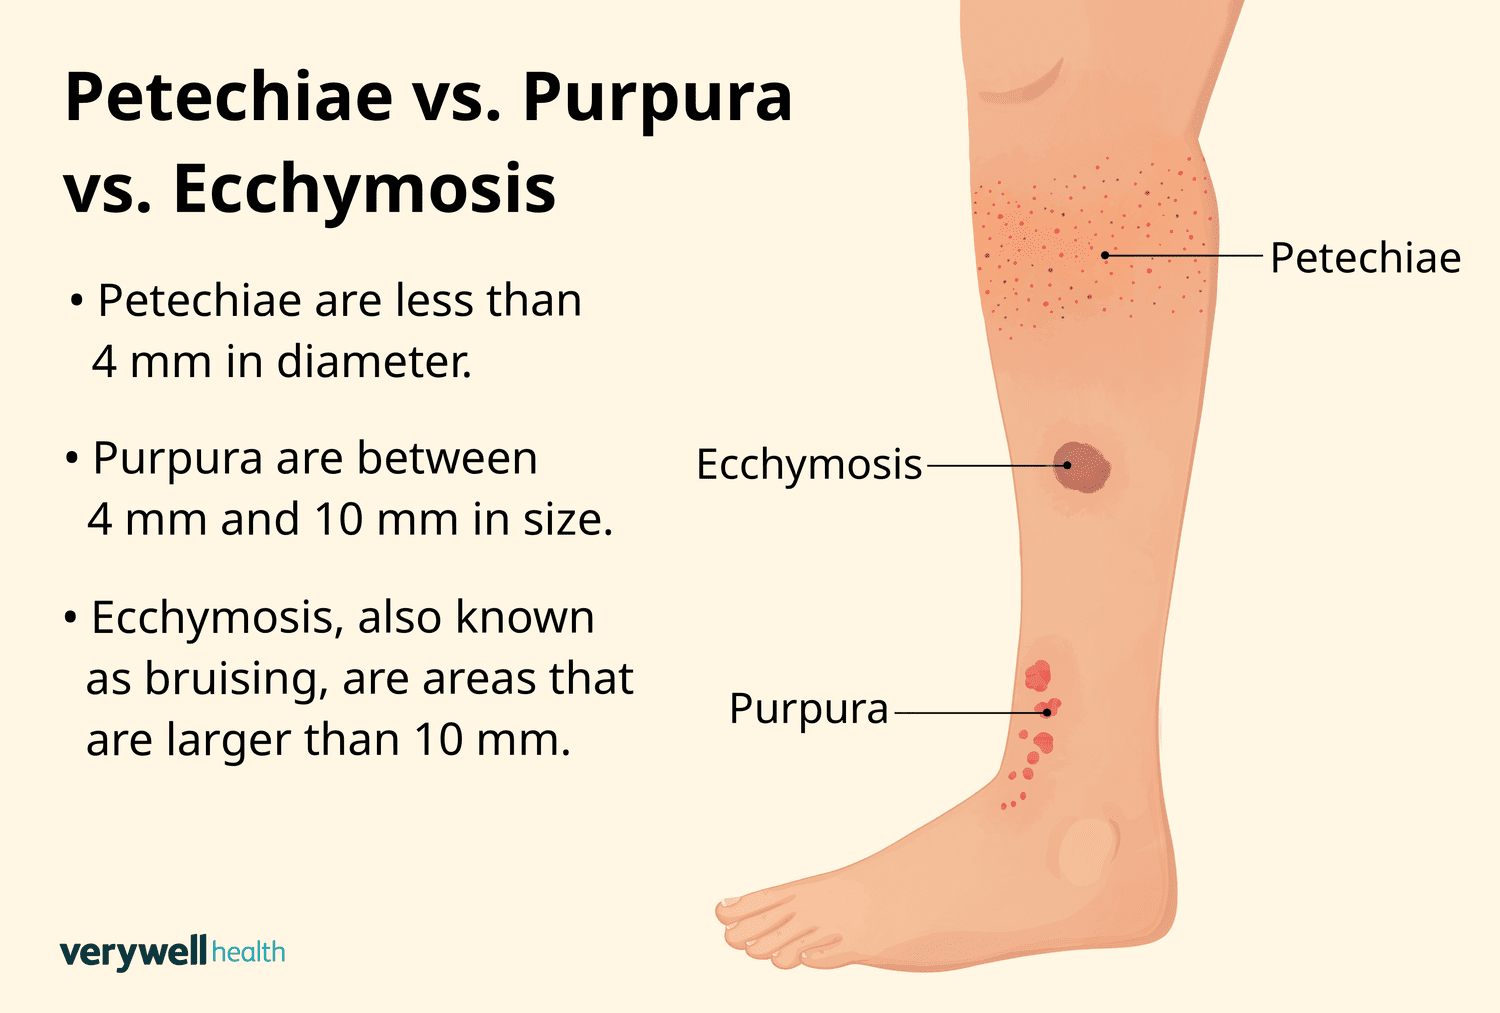
Purpura
PP: hemorrhagic lesions
E: bleeding in skin
bleeding in small blood vessels
CM:
petechiae:
pinpoint macules
1-2 mm in size
ecchymosis:
bruise
larger
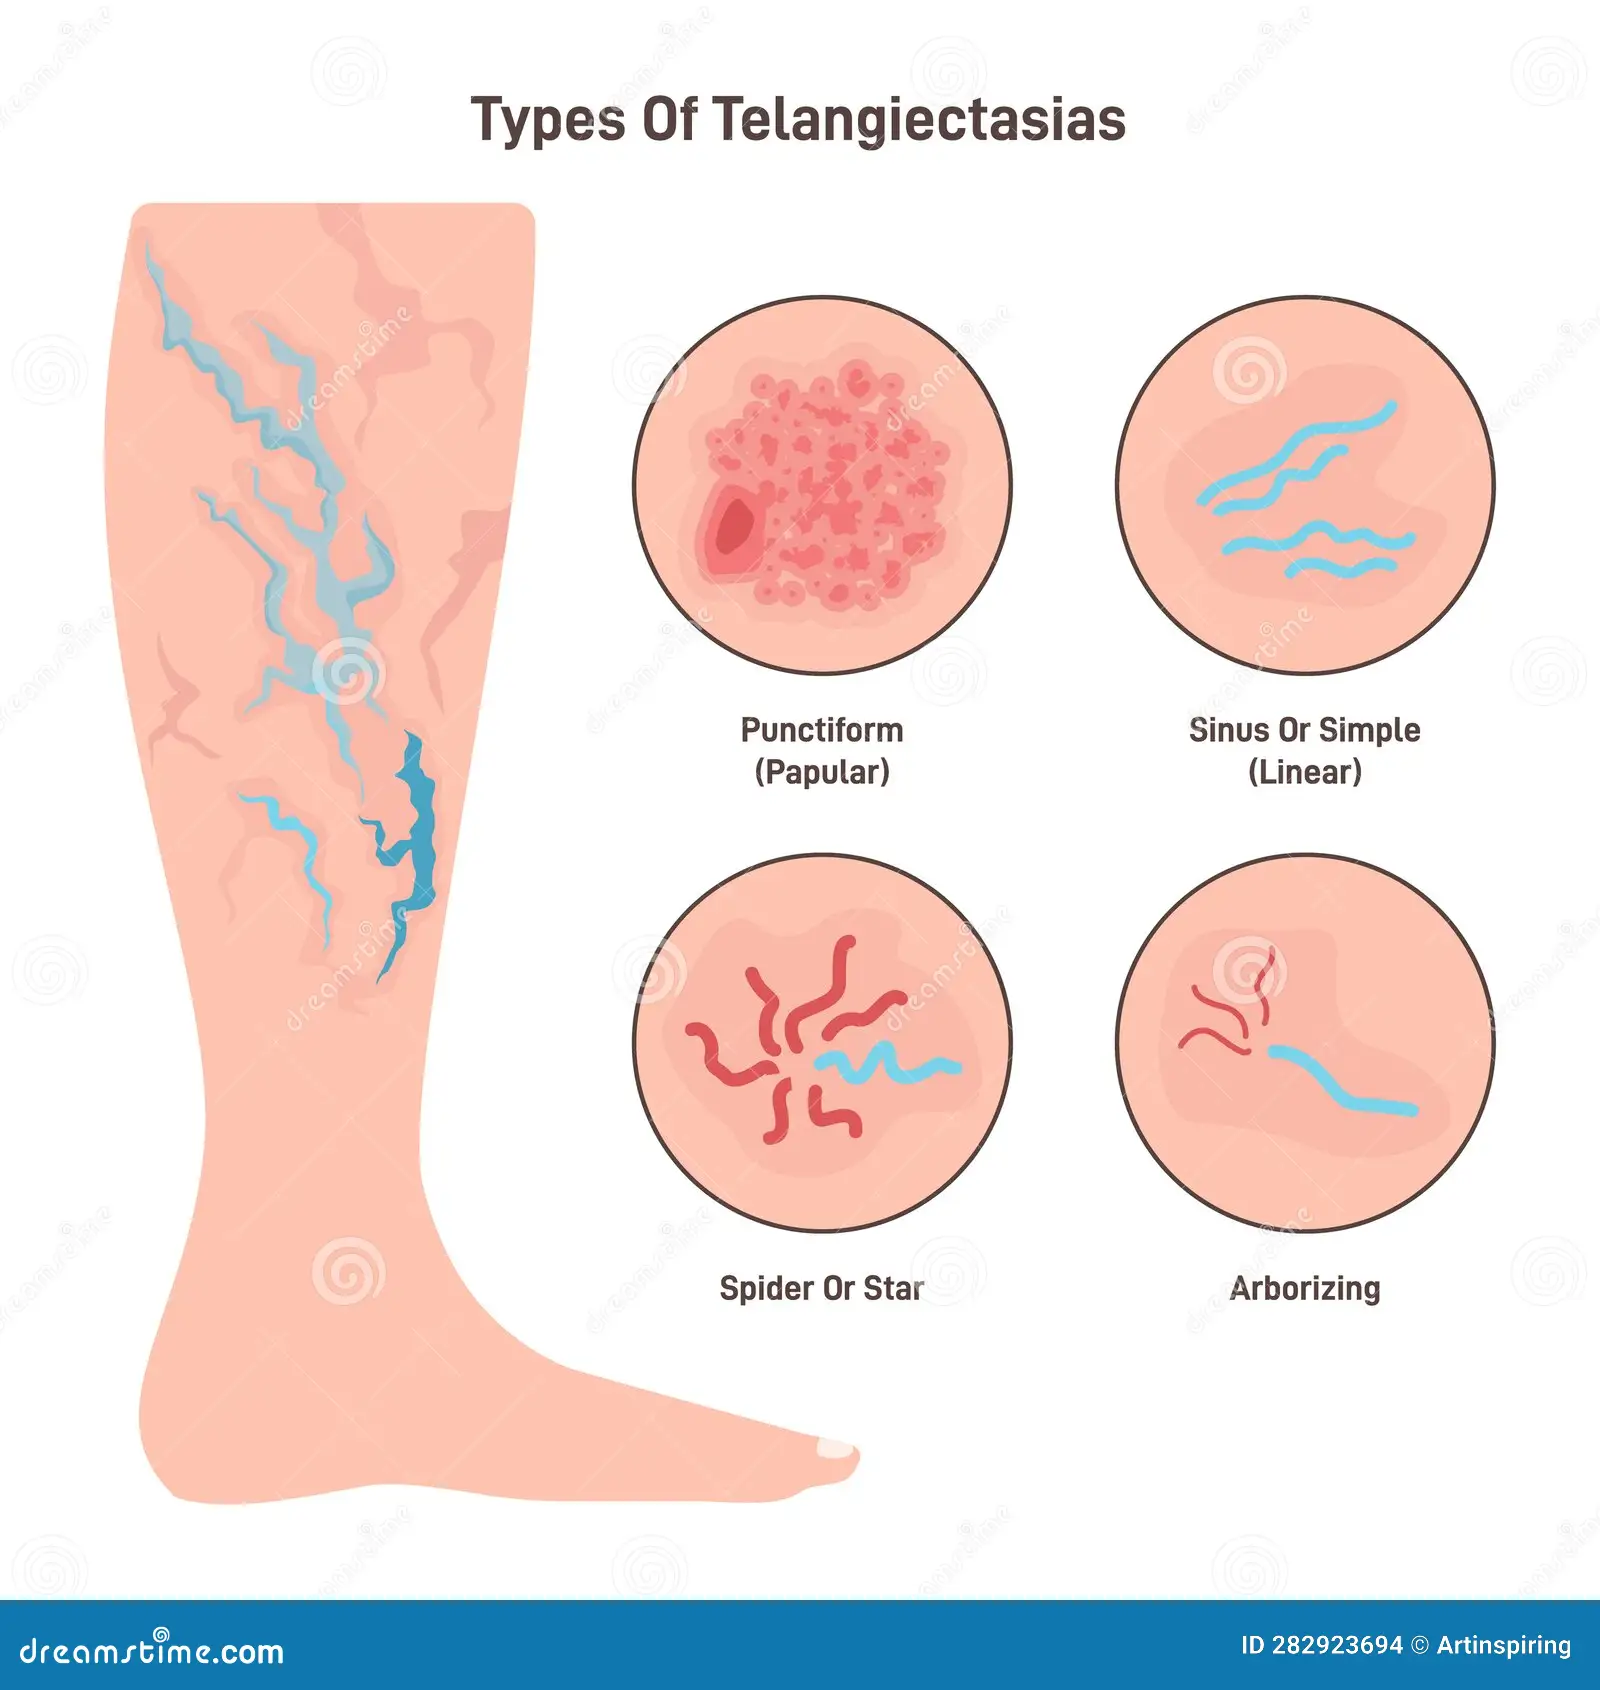
Telangiectasia
PP: small+linear broken capillaries
E: injury
topical steroids
skin cancer
CM: web-like veins
TX: none
sclerotherapy
laser treatment
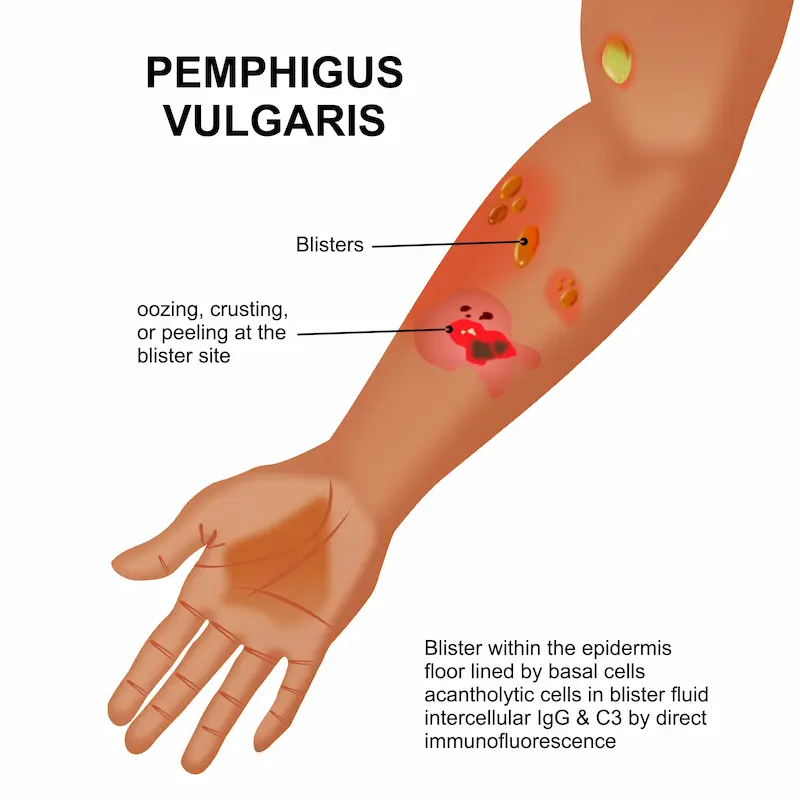
Pemphigus Vulgaris
PP: chronic autoimmune disorder
appear first in mouth+malodorous
E: unknown
CM: mucosal erosions
thin-walled bullae
easily rupture→crusts→hyperpigmented patches+no scarring
DX:
nikolsky sign:
push blister→further separation of the dermis
paraneoplastic:
non-hodgkin lymphoma
chronic lymphocytic leukemia
sarcoma
TX: high-dose PO prednisone
P: paraneoplastic→death from underlying cancer
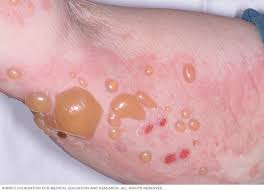
Bullous Pemphigoid
PP/E: autoimmune disorder
adverse mx reaction
RF: elderly
groin
axillae
trunk
thighs
flexor forearms
CM:
urticaria: large+tense subepidermal bullae
can persist for months.years
DX: immunofluorescence of normal skin
blister edge biopsy
nikolsky sign:
push blister→further separation of the dermis
TX: high-dose prednisone x slow taper
azathioprine
topical steroids
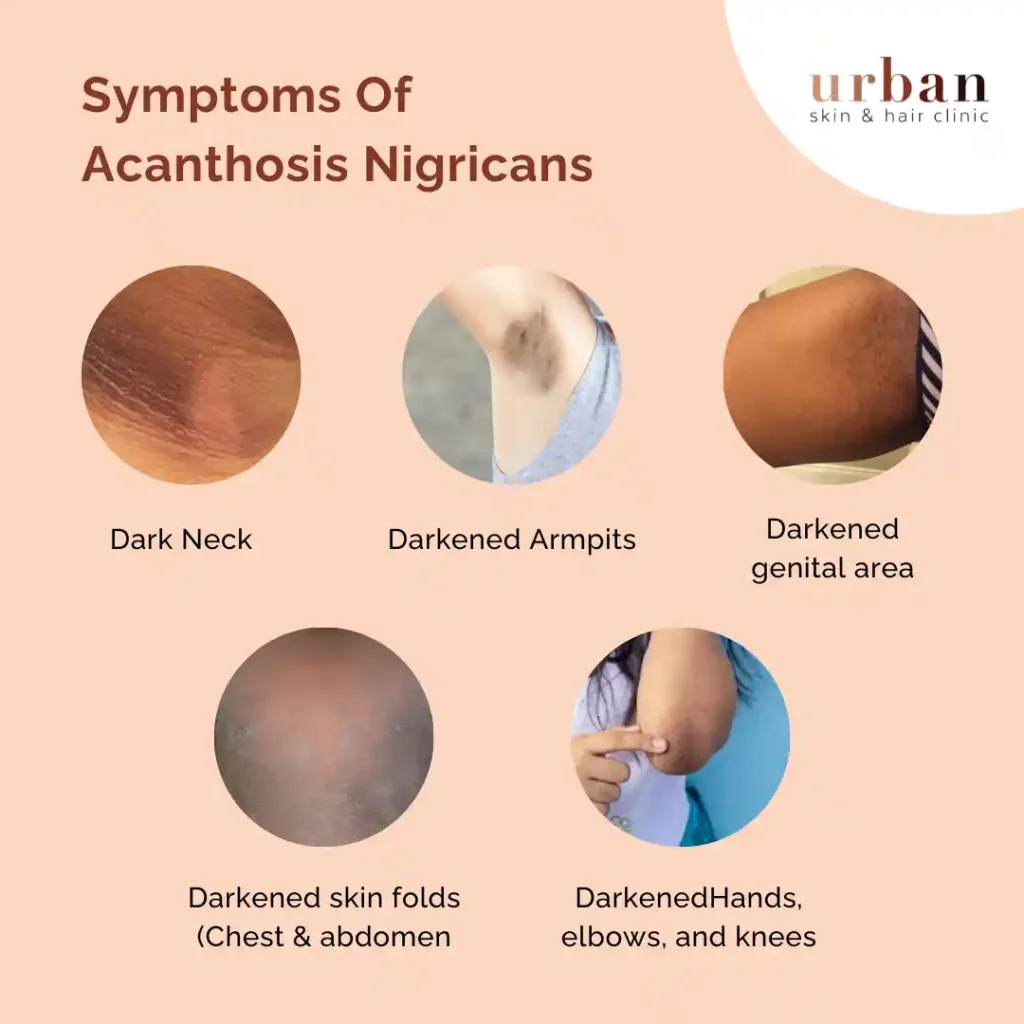
Acanthosis Nigricans
E: diabetes mellitus
non-obese aged pt over 40→GI carcinoma
CM: plaque
hyperpigmented
velvet-textured
-posterior neck
-axillae
TX:
NP: weight loss
tx underlying disorder
MX: topical retinoids
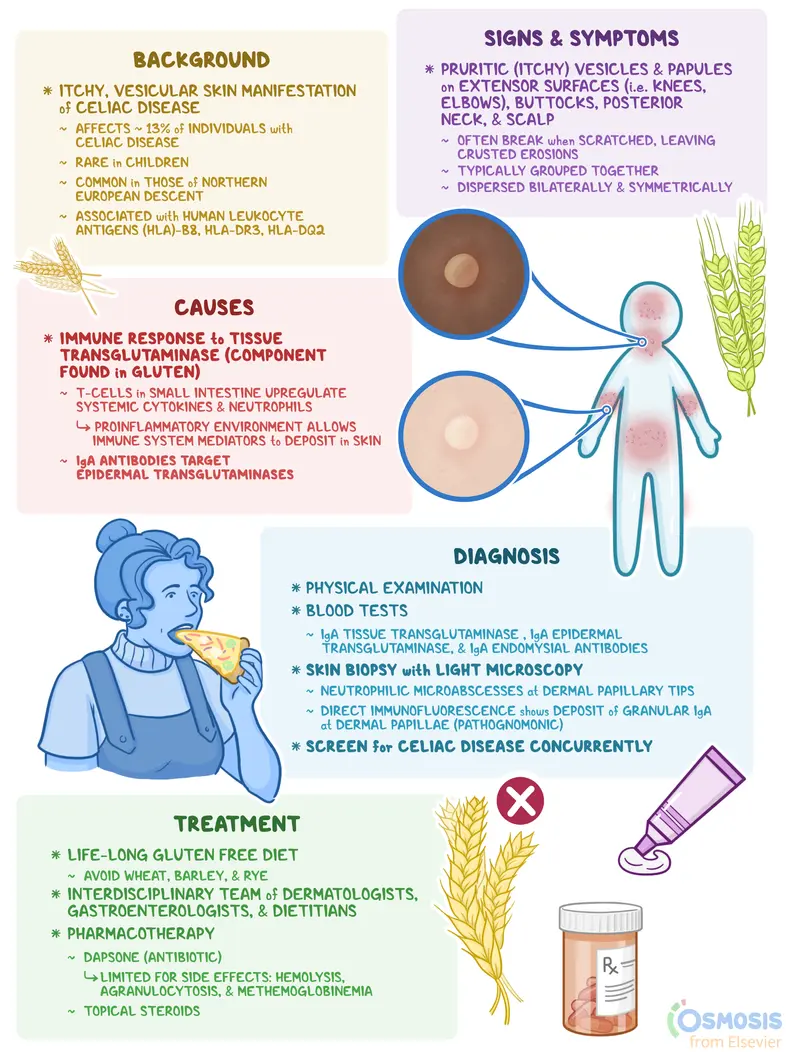
Dermatitis Herpetiformis
E: gluten
celiac disease (90% of pts)
CM: itchy papules/vesicles
-elbows
-knees
-buttock
-posterior neck
-scalp
DX: punch biopsy
celiac dx→tissue transglutamase
TX: strict gluten-free diet
PO dapsone
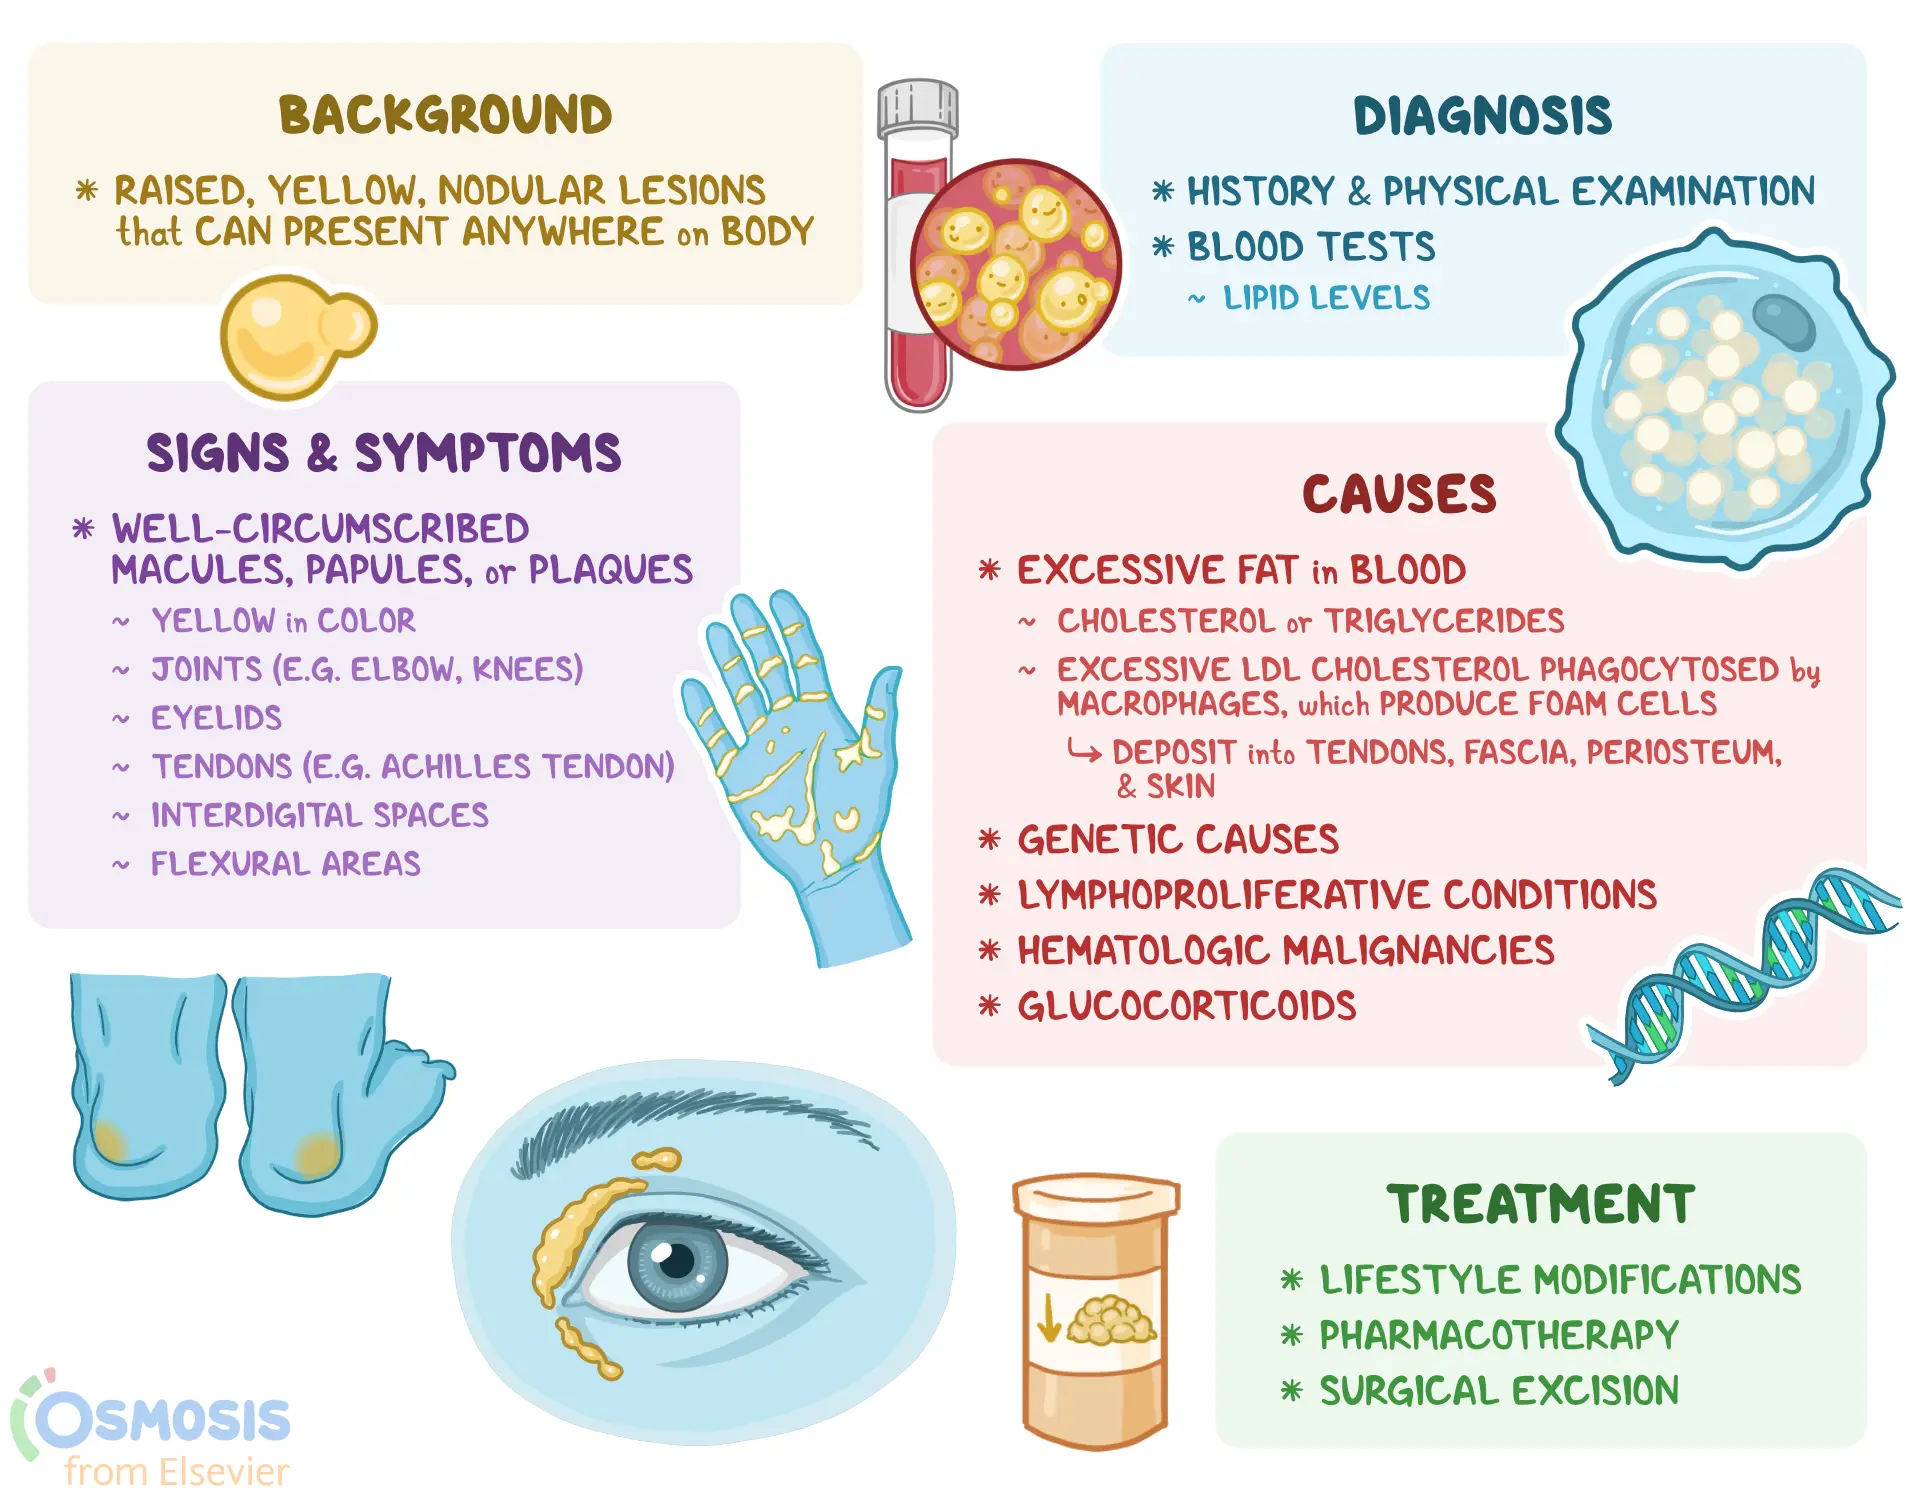
Xanthoma
PP: deposits of lipids in tissue
E: underlying dyslipidemia
DX: full lipid profile
biopsy
TX: surgery
laser
P: increased CV risk
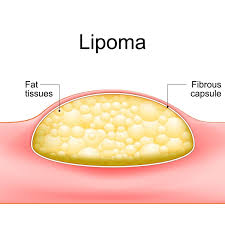
Lipoma
PP: benign subcutaneous fatty tumor
E: m/c→trunk
TX: none
surgical excision
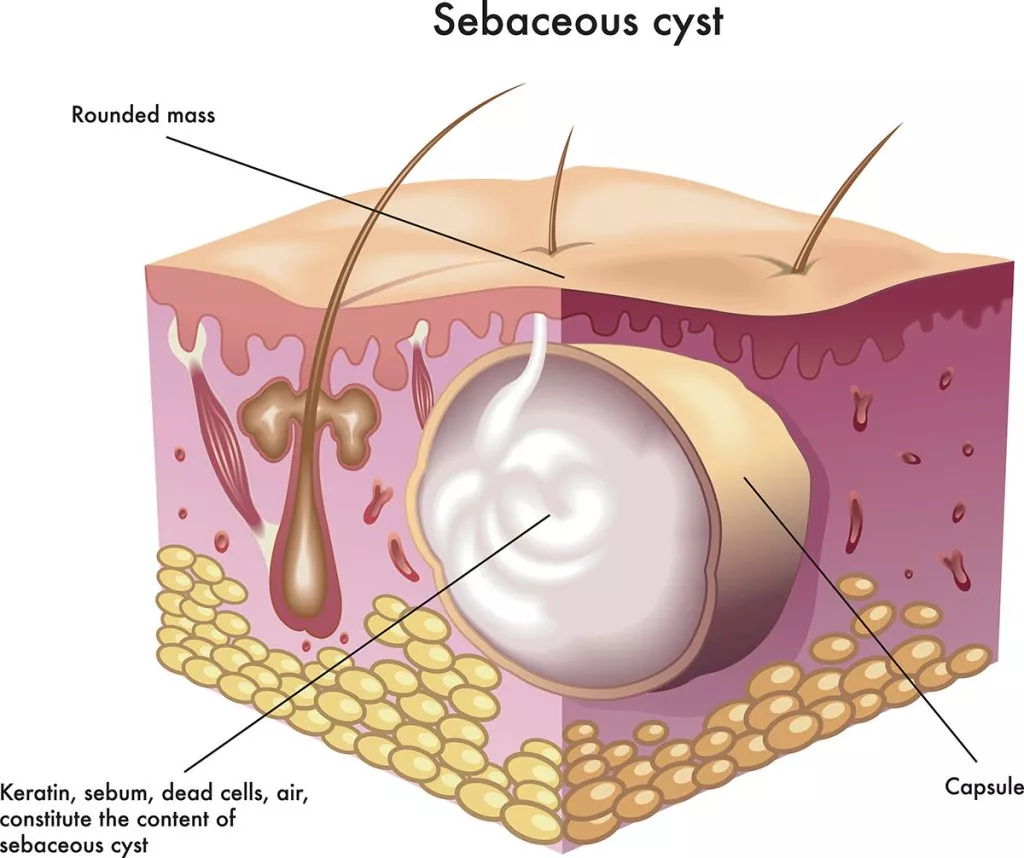
Epidermal Inclusion/Sebaceous Cyst
E: unknown
adults
men
-face
-neck
-trunk
CM: benign/round/dome-shaped/encapsulated lesion+central pore/punctum
TX: none
surgery
inflammation→intralesional kenalog
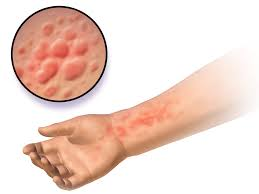
Urticaria/”Hives”
PP: histamine reaction
E: idiopathic (50%)
mx
cold/heat
foods
stress
infections
menthol
wine (sulfites)
CM: wheal (localized edema)
never lasts more than 24 hours
severe itching/sticking/prickling sensation
angioedema
anaphylaxis
hypotension
dermatographism: post scratching→raised wheal
DX: detailed hx
chronic:
CBC
LFT
ANA
thyroid screening
hepatitis screening
TX:
acute→within 6 weeks
self-relieving
antihistamines PRN
chronic→over 6+ weeks
NP: allergist referral
MX: injectable omalizumab x 1 month
antihistamines x daily (linked to dementia)
no topical steroids
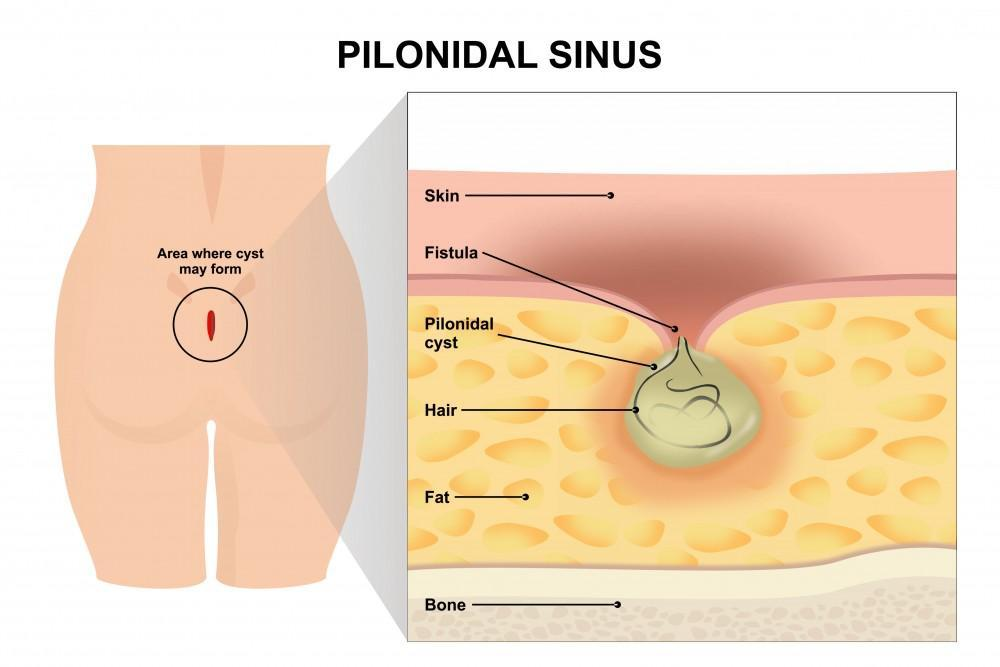
Pilonidal Disease
PP: hair follicles become blocked→chronic infection of the skin in the cleft between the buttocks near the tailbone
associated with a sinus tract
E: men
CM: cyst in upper gluteal cleft
fragments of hairs
TX: colorectal surgery
Hyperhidrosis
E: primary cortex (waking hours only)
thyroid
CM: excessive sweating
symmetric
bilateral
waking hours only→primary cortical
-axillae
-palms
-soles
-face (rare)
DX: thyroid panel
TX: aluminum chloride antiperspirants
aluminum chloride hexahydrate
PO glycopyrrolate (long term use→dementia)
botulinum toxin injections x 3-6 months