Allosteric Regulation of Hemoglobin
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/44

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
45 Terms
b/c the 4 hemes in the hemoglobin tetramer are too far apart to interact directly w/ each other, what happens instead?
the cooperative oxygen binding effects must be mechanically transmitted from one subunit to the next
what is the trigger for conformational changes that proudct cooperativity?
the motion of the ferrous iron towards the heme

when the heme is in the t-state, how far above the heme is the FeII center?
0.6 A, causing the porphyrin to have a dome-like structure
why does the t-state heme have reduced oxygen affinity?
b/c the Fe-O2 bond is stretched beyond its optimal length due to the steric repulsions between the oxygen and the domed porphyrin
as more oxygen binds to the Hb tetramer, the strain produced on the Fe-oxygen centers accumulates until the energy is sufficient to snap the molecule into the R-state
b/c of the inflexibility of the α1 β1 and the α2 β 2 interface, the shift to the R-state must occur simultaneously at both the α1 −β2 and α2 −β 1 interfaces
true or false. one subunit can independently exist in the R-state
false. no one subunit can independently exist in the R-state, nor can one αβ dimer exist in the R state. the whole tetramer has to shift simultaneously from T-R or vice versa
in the quaternary transition, what is the T-state proximal histidine F8 tightly surrounded by?
hydrophobic residues
the FeII can’t move towards the heme without…
reorienting the proximal histidine, otherwise the histidine would sterically interact w/ the porphyrin
what does the tight packing around the histidine require?
the entire F-helix to be translated by 1A across the heme
only possible if there is concerted movement of the α1 C−β2 FG sliding contacts
What contacts change upon oxygenations?
α1 −β 2 and α2 −β 1 contacts
occur between the C-helix and FG segment of α1 with the FG segment and the C-helix, respectively of β 2
quaternary shift from the T → R state
results in a 6 A shift at the α1 C−β2FG interface
for example in the T-state His-FG4 (97β) hydrogen bonds with Thr-C6(41α)
in the R-state, the same His-FG4(97β) hydrogen bonds with Thr-C3(38α), which is one complete turn back along the α-helix

how is the r-state stabilized?
by oxygen binding
which state is more stable in the absence of oxygen ligands
the t-state is more stable b/c the extensive salt bridges that electrostatically stabilize the t-state
what must the energy that causes the T-R transition overcome?
these stabilizing electrostatic interactions
the energy required comes from the formation of the Fe-O2 bond
what does the bicarbonate buffer system regulate?
plasma pH
the important buffer system of blood plasma is the bicarbonate/carbonic acid couple
𝐻2 𝐶O3 ⇄ 𝐻+ + 𝐻𝐶O3-
the pKa of carbonic acid is 3.57 at 37C
at pH 7.4, the concentration of H2CO3 is miniscule

example of an open system exchanging matter with the universe
when you exercise you generate H+, driving the equilibrium towards carbonic acid formation. this in turn increases the concentration of CO2, which in turn is equilibrium with CO2 which we exhale.
Conversely if we hyperventilate than we increase oxygen concentration, which decreases CO2 concentration which by equilibrium decreases CO2, which decreases carbonic acid which in turns decreases the H+ concentration and the bicarbonate concentration and an elevation of blood pH ensues.
how does the slow rate of bicarbonate formation impact CO2?
most of the CO2 produced in the muscles and tissues diffuses through the tissues to the plasma in the CO2

carbonic anhydrase
an enzyme in erythrocytes which catalyzes the net reaction shown above
catalyzes at the diffusion limit, meaning the rate determining step is the diffusion of CO2 to the enzyme
if not for this enzymes, the concentration of CO2 would be so high that there would be a significant concentration of CO2, and we would have bubbles of CO2 in our blood

bohr effect I
on binding oxygen, the conformational change makes the hemoglobin a slightly stronger acid.
the pKa of one or more residues is lowered, releasing protons upon binding oxygen
conversely, increasing the pH, removing the H ions, stimulates Hb to bind oxygen
bohr effect II
in the capillaries pO2 is low, the H+ generated by bicarbonate formation is taken up by the Hb. the binding of protons decreases the affinity for O2, and therefore the hemoglobin unloads its oxygen. when Hb binds protons it causes the equilibrium to stimulate more bicarbonate formation
conversely in the lungs, where pO2 is high, oxygen binding by Hb releases the Bohr protons, which then drive of the CO2
Bohr effect simple terms
the shift in hemoglobin's oxygen affinity caused by changes in pH.
the oxygen saturation curves for hemoglobin at 3 different pH values
oxygen binding to myoglobin is independent of pH

His-β146 contribution for Bohr effect
in the deoxygenated hemoglobin His-β146 is in close proximity of neighboring Asp-
β84, which stabilizes the protonated state of the histidine by electrostatic interactions. the result is the pKa of the histidine is raised from 6.0 to somewhere between 7-8
bohr effect: what happens when oxygen binds the conformational change and moves the aspartate residue away from the histidine?
the result is the pKa of the histidine decreases back to its native 6.0 and the proton dissociates because the equilibria now favors the unprotonated one

bohr effect: CO2 binds to the N-terminal amino groups of hemoglobin which lowers it oxygen affinity
this reaction results in a carbamylated N-terminus. in the capillaries where the CO2 concentration is high the equilibrium favors the carbamylation reaction shown. in the alveoli where the CO2 concentration is low the reverse reaction occurs. the carbamylated hemoglobin form salt bridges that stabilize the T-form of hemoglobin and hence reducing oxygen affiniyt of hemoglobin. the proton produces in the reaction reduces the pH and adds to the bohr effect in the capillaries
the carbon dioxide covalently attached to hemoglobin only accounts for 5% of the total carbonate of the blood plama, but it accouts to 50% of the CO2 expelled in the lungs
myoglobin curve
hyperbolic
myoglobin function
has high oxygen affinity (P50) is extremely low, so it binds oxygen tightly even at low PO2 in muscle tissue
only releases oxygen under sever hypoxia, making it ideal for oxygen storage rather than transport
pH independence: oxygen binding to myoglobin is unaffected by pH changes
hemoglobin curve
sigmoidal (S-shaped)
hemoglobin function
exhibits cooperative binding (binding one O2 molecule increases the affinity for subsequent O2 molecules)
allows it to substrate completely in the oxygen-rich environment of the lungs (PO2 = 100mmHg) and readily unload oxygen in tissue capillaries (PO2 = 20-40 mmHg)
pH dependence on the bohr effect
lower pH (6.8 - metabolically active tissues): shift the Hb curve to the right
lowers oxygen affinity, forcing hemoglobin to release more oxygen into tissues that need it most
higher pH (7.6 - lungs/resting tissues): shifts the Hb curve to the left
increases oxygen affinity, enabling Hb to pick up oxygen more efficiently
carbamylated n-terminus
a protein modification where the free α-amino group (-NH2) at the starting end (N-terminus) of a polypeptide chain non-enzymatically reacts w/ cyanate/isocyanic acid or Co2, attaching a carbamoyl or carbamate group

BPG
binds to hemoglobin and promotes oxygen release
erythrocytes normally contains about 4.5 mM BPG
roughly equivalent to the concentration of hemoglobin in the RBC

true or false. one BPG binds per hemoglobin tetramer
true. the BPG binding site is located w/in the central cavity of Hb between the four subunits. BPG has a net charge of -5 at the physiological pH and is electrostatically bound w/ positively charged functional groups
how do charged residues bind to BPG in the central cavity of Hb?
electrostatically
the bound BPG cross-links the two β- subunits which stabilizes the deoxyHb (T) form and thereby facilitating the release of oxygen in the capillaries.
true or false. in the oxy-Hb (R) state the central cavity is too small to bind BPG.
true. or stated another way when the conformational changes that occur in the transition from going from the T-state to the R-state BPG is extruded of the central cavity of Hb
what is the impact of hemoglobin stripped of BPG?
virtually saturated w/ oxygen at pO2 of only 12 torr
cannot release oxygen in the tissues, where the pO2 is typically between 20-30 torr
BPG shifts the saturation curve to the right, making Hb an O2 delivery system suited to the needs of the organism
what is the effect of the covalent yet reversible CO2 binding on the oxygen binding saturation curbe?
shifts the saturation curve to the right facilitating oxygen delivery
the combined effects of CO2 binding and BPG binding which even further enhance oxygen delivery and produce the same curves as observed in whole blood
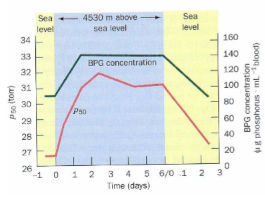
example of elevated BPG/DPG levels
people who live at high altitudes
people who smoke or suffer from anemia
marathon runners train at high altitudes
why? b/c high BPG blood concentration allows oxygen to be used more efficiently and have a distinct competitive advantage at sea level
fetal hemoglobin
fetus depends on mother to supply oxygen but has its own independent circulatory system
gas exchange occurs across the placenta
the fetus needs to absorb oxygen better than its mother
fetal Hb differs from adult Hb in that instead of two β-chains, the fetal hemoglobin has two γ-chains. Fetal hemoglobin is thus α2 γ2. The γ-chains are almost identical to the β-chains of adult hemoglobin except that the His-143 has been substituted with a serine.
the His-143 residues from both of the β-chains electrostatically interact with BPG as shown above. the two γ-chains substituted with serines at their 145 positions lack the two positive charges that histidine provided and cannot electrostatically interact with BPG. As a result BPG binds much weaker to fetal hemoglobin, and the fetal Hb has intrinsically a greater affinity for O2 .
in a fetus, what is the proximal histidine-143 replaced with?
serine
true or false. oxy- and deoxyhemoglobins have different quaternary structures
true
oxygenation causes extensive quaternary changes in Hb
if O2 is allowed to diffuse in crystalline deoxyHb the crystals shatter. the crystal structures of oxyHb and deoxyHb had to be solved independently. in both forms, the twofold symmetry of hemoglobin was preserved. All of the quaternary changes produced by oxygen binding occur across the α1 −β 2 and α2 −β 1 interfaces
true or false. The extensive hydrophobic interactions in the α1β 1 dimer (or equivalently the α2 β 2 dimer) are different during oxygen binding which provides a convenient frame of reference.
false. The extensive hydrophobic interactions in the α1β 1 dimer (or equivalently the α2 β 2 dimer) remain the same during oxygen binding which provides a convenient frame of reference. Oxygenation rotates the α1 β 1 dimer 15 o with respect to the α1 β 1 dimer such that atoms in the α1 −β 2 interface shifts by as much a 6 Å.
true or false. The T-state is the quaternary conformation of deoxyHb regardless of the ligand used to induce the state. (I.e. H+, BPG, CO2 )
true
true or false. Likewise the T-state is the quaternary conformation of oxyHb and is also independent ligand used to induce it. (O2 , CO, CN - and NO)
false. Likewise the R-state is the quaternary conformation of oxyHb and is also independent ligand used to induce it. (O2 , CO, CN - and NO)