Surgery of EQ female repro tract
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/34

There's no tags or description
Looks like no tags are added yet.
35 Terms
What can be used to examin / further diagnostics of female repro track?
Rectal, vaginal & external palpation
Hormone analysis
Biochemistry / haematology
Cytology
U/S
Hysteroscopy
Biopsy
Laparoscopy
Laparotomy
List the anatomical barriers of the repro anatomy/ conformation
Vulva
Vestibulovaginal fold
Cervix
Failure = contamination, reduced fertility
What are the features of good repro conformation?
Labia:
Vertically orientated (if horizontal oritentation → contam)
2/3rd vulvar opening below floor of pelvis
Good:
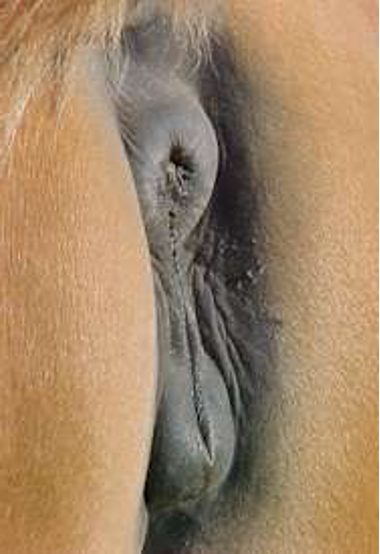
Bad:
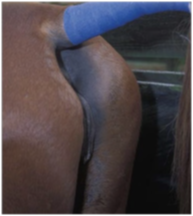
poor conformation —> acquired due to injury, age, parity, body condition
List some of the problems that can arise from conformation problems and the procedure used to treat them?
Pneumovagina
Caslicks —> improved vulvular competence (insuff alone for severe cases)
Perineal reconstruction (Gadds) —> older mares, loss of perioneal body, straight vestibule
Urovagina
Urethral extension, cd relocation of transverse fold
Cervical incompetency
Cervical repair
Delayed uterine clearance
Uterine suspension
Oviduct blockage
Oviduct lavage
Prostaglandin
How do you perform a Caslicks Procedure?
Bandage tail out the way
Stocks / against doorway
Wash perineum
Local anaesthesia
Excise thin band of mucosa each side (3-4mm)
Include dorsal commissure

Level with ischiatic tuber
Do not over suture
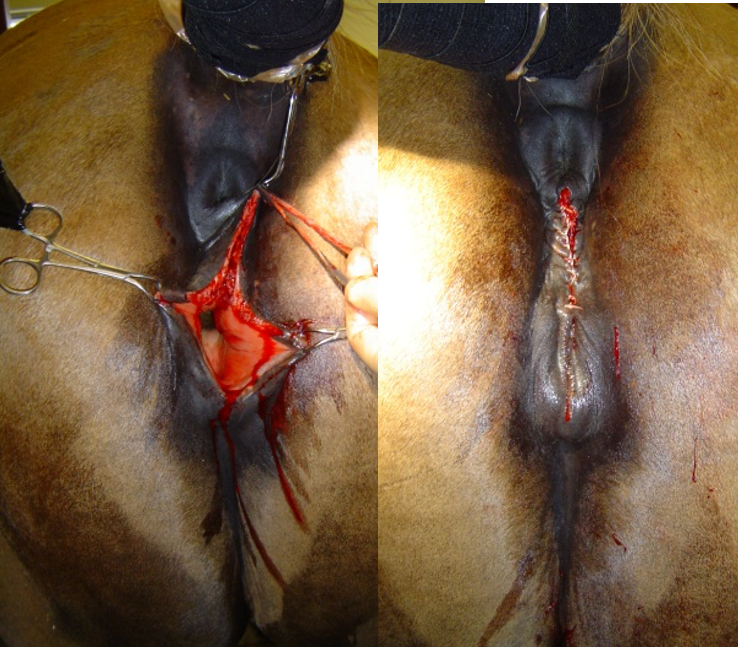
When should you remove sutures after a Caslicks procedure?
10-14 days after
Before foaling (otherwise will tear)
When is perineal body reconstruction used?
More severe cases of pneumovagina
Second degree perineal lacerations
How does urovagina present?
Usually seen in old, multiparous mares, often w/ pneumovagina
@ what stage of the cycle is urovagina usually diagnosed?
Oestrus —> confirmed by cytology
What is your Ddx of urovagina?
Ectopic ureter in young fillies
@ what stage of the oestrus cycle should you perform surgery for cervical incompetence / lacerations?
What are the post-operative complications?
Dioestrus (3 weeks post partum)
Post operative adhesions & incompetence possible
What can delayed uterine clearance lead to?
Endometritis
Post mating persistent endometritis
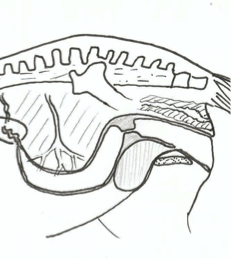
Uterus sitting too low
Describe uterine suspension (uteropexy) as tx for delayed uterine clearance
Restoration of horizontal orientation of uterine horns
Improves uterine clearance
Improves perineal conformation
May reduce urine pooling
How do you diagnose oviduct blockage?
Ovulation but no embryo/ oocyte in uterus (presumptive diag?)
How do you treat oviduct blockage?
Laparoscopic injection of prostaglandin:
Relaxes smooth muscle of oviduct
Modulates oviductal transport
When do perineal lacerations occur?
Usually during unassisted foalings in primiparous mares
What are the different grades of perineal laceration?
1st degree —> Mucosal damage
2nd degree —> Mucosa, submucosa & perineal mm.
3rd degree —> Complete disruption of rectovestibular shelf, perineal body and anus
How do you treat each degree of perineal tear?
1st —> caslick/ no surgery required
2nd —> Caslicks + reconstrution of perineal body
3rd —> Surgical repair; Delay for 4-6 weeks
What can cause a rectovestibular fistula?
Penetration of foals foot into rectum w/o progression to 3rd degree perineal laceration
Unsuccessful repair of 3rd degree laceration
What is this showing?
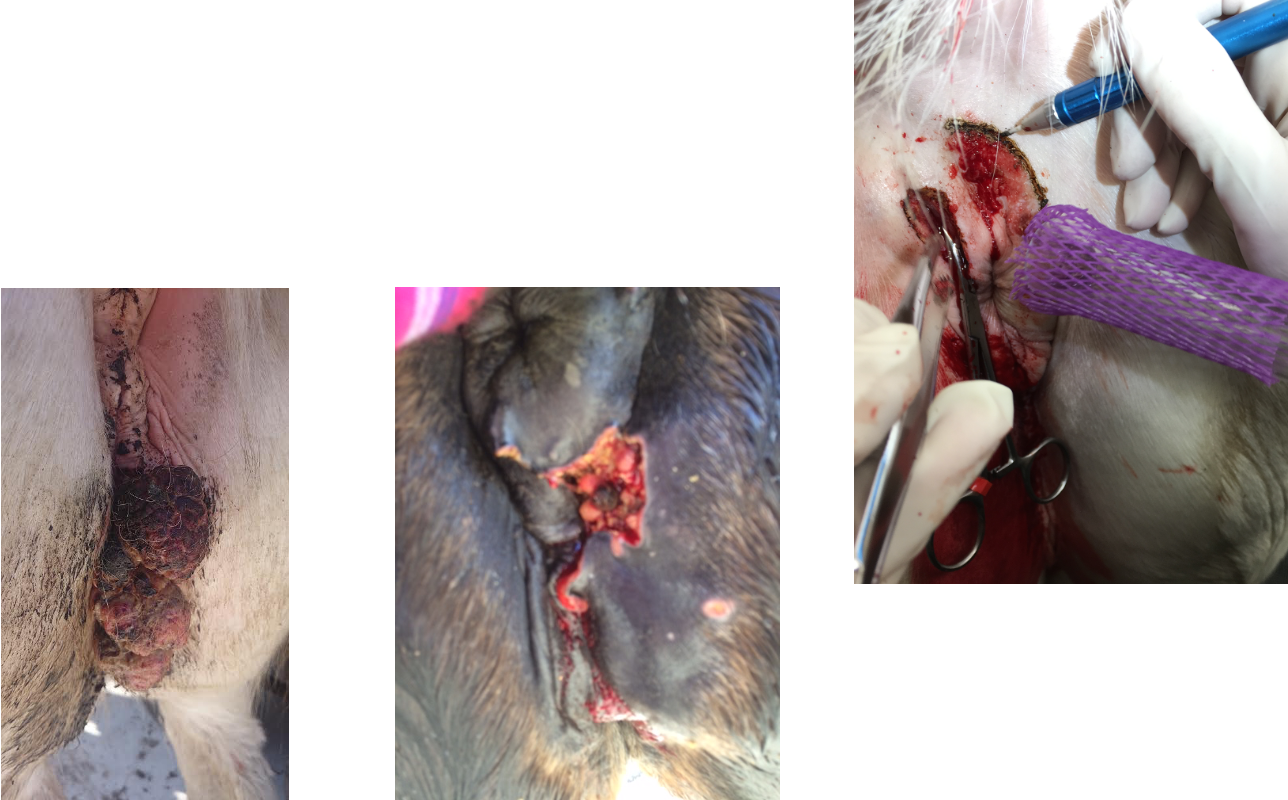
SCC of vulva & clitoris
Poor prog even w/ radical resection —> once seen externally, already v. bad internally
How do varicosities present?
Intermittent vulvar bleeding
Blood pooling
Worst @ oestrus
Most commonly @ vestibulo-vaginal junction
How are varicosities treated?
Not always necessary
Topical tx w/ astringent creams
Ligation —> ligate either side where vein comes out of tissue
Cautery
Laser photocoagulation
What is the most common neoplastic disorder of the ovaries in mare?
Granulosa (Theca) Cell Tumour (GCT)
What are the features of GCT?
Unilateral (can be bilateral)
Rarely metastasise —> stays problem of ovary & doesn’t become system-wide
Good prognosis after removal
Behavioural signs
Anoestrus/continuous oestrus
Stallion like behaviour/ aggression
How is GCT diagnosed?
Rectal exam —> enlarged ovary on affected side, contralateral usually smaller
a few cm —> inhibin of granulosa cell tumour inhibits growth of other ovary
Transrectal U/S —> honeycomb-like appearance
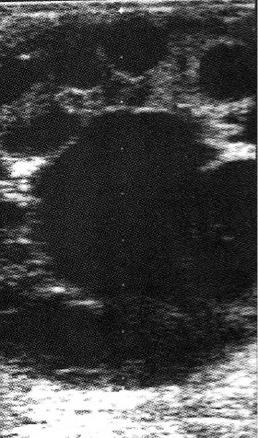
Endocrinology (hormone testing)
What endocrinology tests can be used for GCT diagnosis?
Incr anti-Mullerian Hormone —> best sens
Incr inhibin
Incr testosterone
How is GCT treated?
Ovariectomy:
Laparoscopy (standing or GA)
Laparotomy if particularly large tumours
What are the risks of colpotomy (ovariectomy technique)?
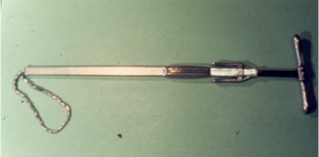
Haemorrhage
Failure to remove ovary
What is the difference between assisted vaginal delivery and controlled vaginal delivery?
Assisted —> conscious (usually standing), traction & ropes
sedation & epidural if mare straining excessively
Controlled —> GA +/- hindlimbs elevated
better to elevate HLs —> more working space
best done in referral
if in clinic = abdo should be prepped for C section @ same time
What are the basic features of a C section?
GA
Approx 1wk in hospital post-op
Give oxytocin to get expel placenta
retained placenta common following any dystocia
When would you perform a foetotomy?
Very last resort:
Only if certain foal is dead
see if moves
feel for pulse
assume alive unless certain otherwise
Only if dystocia can be resolved
Can cause considerable trauma
List some of the complications that can occur following dystocia/ parturition?
Uterine prolapse
Uterine rupture
Uterine haemorrhage
Invagination / retroflexion of the uterine horn
Retained foetal membranes
Cervical tears
Perineal lacerations / rectovaginal tears
List the uterine disorders to be aware of
Uterine prolapse
uncommon
post dystocia / straining
replacement (using rounded object) under standing sedation / GA
Uterine artery haemmorrhage
early teen mares, multiple foals
haematoma in broad lig —> long tubular shape, cr end wider
colic & evidence of haemorrhagic shock
medical management —> supportive & managed @ yard
do not move mare unless hospital tx needed
Uterine torsion
uncommon
cr to cervix on rectal palpation
L broad lig
last 2 months gestation / @ parurition
colic / dystocia
correction via surgical / rolling
Uterine rupture
clin signs evident 24-72hrs post foaling
clin signs & tx depend on size of tear —> colic, peritonitis
Uterine neoplasia
rare
partial / total ovariohysterectomy
GA / standing laparoscopic techniques

Pyometra
drainage of uterine contents pre-surgery
ovariohysterectomy (laparotomy ± laparoscopy)
chronic, less common
List the mammary disorders to be aware of
Mastitis (ABs)
Neoplasia (Poor prog, treat asap)
What is the history ass. w/ dystocia?
Prolonged discomfort & straining
Straining without appearance of amnion
Appearance of amnion / head / limb but no further progress