stable ischemic heart disease
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/135

There's no tags or description
Looks like no tags are added yet.
136 Terms
for sihd what does everyoneee get
ada or plvavix
high intesity statin
SL nitroglycerin (NTG)
flu shot lol
what is ccd
chronic coronary disease
all the obstrucitve nad nonsobutrvive cornoary artery disease
obstructive ccd
narrowing of coronary artery due to plaque deposition
nonobstructive ccd
angina with nonobstructive coronary artiers (ANOCA)
what is IHD
ischemic heart disease
lack of oxygen and/or no blood flow in myocardium
disease means imbalance between o2 supply and o2 demand
what is presenting sign of IHD
angina in 50%+ patients
define ccs
chronic coronary syndromes
can be reversible deficeit in supply/demand (stable ischemic heart disease)
can be progressive and able to destablize at any. moment— ACS!
what is included in stable ischemic heart disease
stable angina symptoms who are medically managed
angian symptoms from coronary vasospasm or microvscular angina
what are the acute coronary syndromes
unstable angina
non ST-segment elevation MI
ST segment elevation MI
the things that cannot be relieved by nitro and/or rest
how does ischemic heart disease (stable angina)
angina
coronary artery vasospasm or prinzmetal’s angina or vasospastic angina
heart failure or arrthymias
cerebrovascular accident or storke
peripheral vascular disease
what is the STRUCUTRAL reason for SIHD?
what is the functional reason for SIHD?
atheroscleorsis: damage to ENDOTHELIUM by plaque underneath (covered by fibrous cap)— can rupture which becomse UNSTABLE
coronary artery vasospasm— coronary artery spasm (literal muscle contraction)
what are two main types of coronary arteries
epicrdial coronary artieres— “conductance” vessels
intramyocardial arterioles— “resistance” vessels— branch out into capillaries— react quickly when demand for oxygen chagnes
what forms the foam cells
macrophages that have swallowed up the fatty plaque
what is the LAD
“widow maker” artery
left anterior descending— supplies a LOT of blood to heart
what two factors inside the coronary arteries cause vasodilation
nitric oxide
endothelium-derived relaxing factor
damage to endothelium means cannot release NO
what is supple and demmand like in angina? what is causing the limit in one of these facotrs
angina occurs due to increased oxygen demand in limited ability to supply o2
R1 (epicardial coronary artery) occlusion
what % occlusion of r1 (epicardial arteries) leads to UNSTABLE plaque
70%
how does body compensate for occluded r1 (epicardial artieres)
R2’s dilate
so in excericse or stress they are maxed out and cannot expand anymore to supply more blood
what determinants myocardial oxy demand
heart rate— beta blockers, ccbs
contractility — bbs, ccbs
ventricular volume (preload—stretch)
ventricular pressure (afterload—squeeze)
what is systole? diastole
systole— heart pumping
diastole— heart filing/relaxing
what is afterload
force heart is pushing against
heart works harder’
hypertrophy (the muscle GROWS)
what is preload
amount of blood returned to heart from suprieor vena cava into right atrium
increase in volume means teh muscle in left ventricle has to do more work
what are NONcardiac reasons for decreases in o2 supply
anemia (blood doesnt have enough oxygen)
hypooxemia (not getting enough oxygen into the body, ie for asthma, sleep apnea)
sickle cell disease
Sympathomimetic toxicity (overload of SNS— ie OD, tumor, etc)—— hyperthyroidism
what effects preload
long acting nitrates
venous side is preload
what are OTHER not-ascvd reasons for increases in O2 demand
aortic stenosis, hypertrophic cardiomyopathy, HTN
three big types of angina
chronic stable angina
unstable
variant

what are three big symptoms of angina? (think PPR)
pain — squeezing, suffocating/crushing sensation, pain in chest that radiate to neck
predictable — precipitated by exertion or stress
relieved— by rest or nitroglycerin
what normally causes variant angina
young, male, sometimes drug-user or smoker
cocaine association
smoking association— endothelium
how is angina presenting different in diabetics than other pops
less pain bc of neuropathy
higher risk of CV death
what are relevant labs ? what labs mostly mean?
normally are WNL— within normal limits
CRP
SCr
Hgb
Thyroid
Troponins will be negative
these things really should be normal if its truly just an angina problem
what two pops most liekly to be misdiagnosed
women— bc diagnosed as tummy troubles
elderly— bc a lot of stuff going on
diabetes— experience pain differently
what are looking for in past medical history
HTN
dyslipidemia
current smoker
DM
also look at fam history, social history (drug use)
what are some tests that can actually be done on patients to rule out or determine pt risk
cardiac specifc imaging— pet scan, ct scan
chest x-ray— see if its heart falure
ecg
ett—exercise tolerance test—- pretty clear ind of increased demand not being met by supply— can be done with medication in elderly
echo— may show ongoing myocardial injury— there is an invasive version called transesophageal
cardiac catheterization (for pts with unacceptable symptoms)
will troponins be released in SIHD? why normally released
released when myocardial damage due to lack of blood supple
NO not released
what do you need to have a MI diagnosis
positive troponins
clinical presentation of stable angina (slide 29)
chest pain/sob/fatigue IN REPONSE to stress/exertion
negative troponins
predictable (same exertion causes it every time)
relieved by nitrates (sublingual usually) or rest
how duration dif in stable vs unstable angina
10-15 minutes for stable
longer for unstable angina
what is revascularization ? is this pref in angina
NOT pref in angina
revascularization is like CABG (coronary artery bypass grafting), stent (percutaneous coronary intervention), etc
survival rates about teh same as just using meds, but can maybe have better sumptom improvement
what are some mechs by which cigs accelerate CVD
platelet adhesion
endothelial dysfunction
vasoconstriction
goals of angina treatment
symptom goal is relieve the angina
mortality goal is lit don’t die lol
so we have mortality reducing drugs, and symptom relief drugs
what statins need take with food
JUST lovastatin
what statins must take PM
fluvastatin, lovastaitn, simvastatin, lovastatin ER is bedtime
what kind of fat should be avoided in sihd
trans fat
what are exercise recs
150 min/week of moderate intensity aerobic activity OR 75 min higher-intesity aerobic activity
resistance for 2 or more days/week
set realistic goals! :)
in pts with SIHD what is goal ldl! and goal non-hdl
ldl< 70
non-hdl < 100 mg/dl
what are the 6As
ask, advicse, assess, assist, arrange, AVOID (avoid secondhand smoke)
so everyone is on statin pretty much in this patient pop. what could be added if very high risk
zetia per IMPROVE-IT
IF high risk, on max tolerated statin/ LDL-C at or less than 70 mg/dL
if STILL not controleld, can add PCSK9 inhib mAb
is ANY alcohol good for you
apparently NOT. all cancer related to imbibing (throat, gi, rectal— all the way down)
when in SIHD pts do you add icosapent ethyl (vascepa)
fasating TG’s from 150-499
if SIDHD pts at high risk, what are lipid goals (think terat-resist ASCVD pts)
LDL<55 mg/dL
non-HDL< 85 mg/dL
major ASCVD EVENTS, high risk conditions (older, diabetes, HTN, smoker, CKD)
what are classes of meds that reduce mortality risk for SIHD? what is main principle behind this
main principle behind this is that drugs are used to decrease the risk factors for SIHD
high-intensity statin (THIS IS LIT ASCVD SO)
antiplatelets— aspirin, or clopidogrel if allergic
HTN— so acei/arb if comorbid HTN/DM/CKD
T2DM— so SGLT2i/GLP-1ags— with comorbidities
what are the two high intensity statins? what are their strengths? why high intesity
high intenisyt bc decrease LDL by 50% or more
atorvastatin 40-80 or rosuvatstatin 20-40
what is FIRST LINE for SIHD for HTN management
NON-pharm!
what is BP goal for HTN management for SIHD
<130/80 mmHg
so normalyl for HTN, thiazides, DHP-ccbs, ACEis and ARBs. BUT for HTN with CV trouble, what is pref
ACEis (have more data)
then ARBs, esp if bradykinin with ACEis — cough, angioedema
which ACEi is best
nah they are all same
you see lisinopril a lot bc its once a day (ex captopril is TID so like no one uses it)
what is A1C goal for SIDH pts with T2Dm
less than 7%
BUT less than 8-8.5% for those over 65 yo
on slide 46, why is the lisinopril pref over hctz?
bc thepatient has stable ischemic heart disease
what are the two platelets used for prevention (piramry and secondary prevent)
aspriin (shortedn to ASA)
clopidogrel (for asa alllergy)
what is hte enzyme taht is required to get clopidogrel ot active form
clopidogrel !
clop dose for ½ prevention
75 mg daily
aspirin dosing for 1/ 2 prevent
75-100 mg qd (low dose which is 18 mg)
which ppi is ok to give iwth clop bc less cyp2c19 ?
pantoprazole (Protonix)
what are the two types of PCIs (stents given by catheter)
bare metal stent
drug-eluting stent
how long give dual-antiplatelet therapy after bare metal stent
DUAL antiplate for 1 month (asa AND clop)
tyring to avoid re-thombosis of coronary artery
how long give dual antiplet thearpy after drug-eluting stent? then what give?
6 monts dual
thennn given ASA or clop (usually for 6 months)
this is shown to decrease MACE and bleeding events! crazy work
what is added to ASA and clop to make triple theapry
DOAC!
when would you need TRIPLE therapy (dapt+doac which means asa+clop+riva or apix etc)
post MI or PCI WITH
a fib
mechanical heart valves
- PE/DVT
what are two HARM things from guidlines in regards to SIHD (ccd) on DAPT?
do not use prasugrel
do not use NSAIDs
when is clop useful to ADD TO aspirin
onlyyy after PCI
how is triple therapy dosed over time
DAPT for 1-3 weeks
then DOAC with clop for 6 months
then just DOAC
people using DAPT with sihd— what else can be given or protection what is this protection?
can use PPIs
to protection GI bleeding
BUT ONLY IF COMPELLING IND— esp from stress
what is ccd?
chronic coronary disease
means yes SIHD, must also includes ppl who are not currently having stable angina or myocardial ischemia but has happened in past
what do we want to do to FOR SYMPTOM REDUCTION
decrease myocardial o2 demand, or increase supply
what are the three drugs mainly for angina relief
beta blocker
CCB.
long acting nitrate
note that you also have your SL nitroglycerin
how do beta blockers affect myocardial oxygen
decrease oxygen demand by decreasing heart rate and decreasing contracility
how do ccbs affect oxygen supply and demand
vasodilation and decreased heart rate
how do LONG-ACTING nitrates affect heart oxygen supply and demand
mostly decrease oxygen demand by decreasing preload, can slighlty increase oxygen supply by vasodilation
when do you add a second anti-anginal (BB, CCB, long act nitrate)?
if you still have symptoms
try increasing dose of the first drug before you add another one
if you are on two or more anti-anginal durgs and STILL symptom, what to take
ranolazine
what are some LOW DOSE items for the anti-anginals
BBs: MS is 25 mg; aten is 25 mg; carve 3.125 mg
ccbs: amlop 2.5 mg; nife 30 mg
LAN: isosorbide mononirtaes ER 30 mg; dinitrate 10 mg
are both ccbs and NON-dhp ccbs used in chronic cornary disease
YES
how is ccb and non-dhp ccb effect different
non-dhp (verampil/dilt)
decrease demand by decreasing preload
ccb:
dipines!
mostly increase supply to heart by vasodilation of arteries — decreased afterload
ranolazine brand
ranexa
BB ad ef
bradycardia, hypotension
• Fatigue
• Dizziness
• Sexual dysfunction
which of our drugs would decrease oxygen DEMAND by decreasing HR
Beta blockers
non-DHP ccbs (verapamil, dilt )
BB mech/benefit
decrease HR by decreasing chronotrophy
decrease contractilty (decrease inotrophy)
decrease afterload/wall tension
when do beta blockers (which recall are used for symptom relief) NOT also help to reduce MACE
patietns with CCD (SIHD) wihtouttttt previous MI or LVEF under 50%
this is reduced ejection fraction heart failure
what is chronotropy
heart rate
what is inotropy
contracitilyt — how hard heart can squeeze
what are the THREE beta blockers that ppl with angina (SIHD) and LVEF (reduced) ppl can get
metoprolol succinate, carvedilol, bisoprolol
we don’t want BBs with ISA (instrict sympathomimetc acitivty— the only BB wiht this is pinodolol)
what is dromotropy
AV node conduction speed
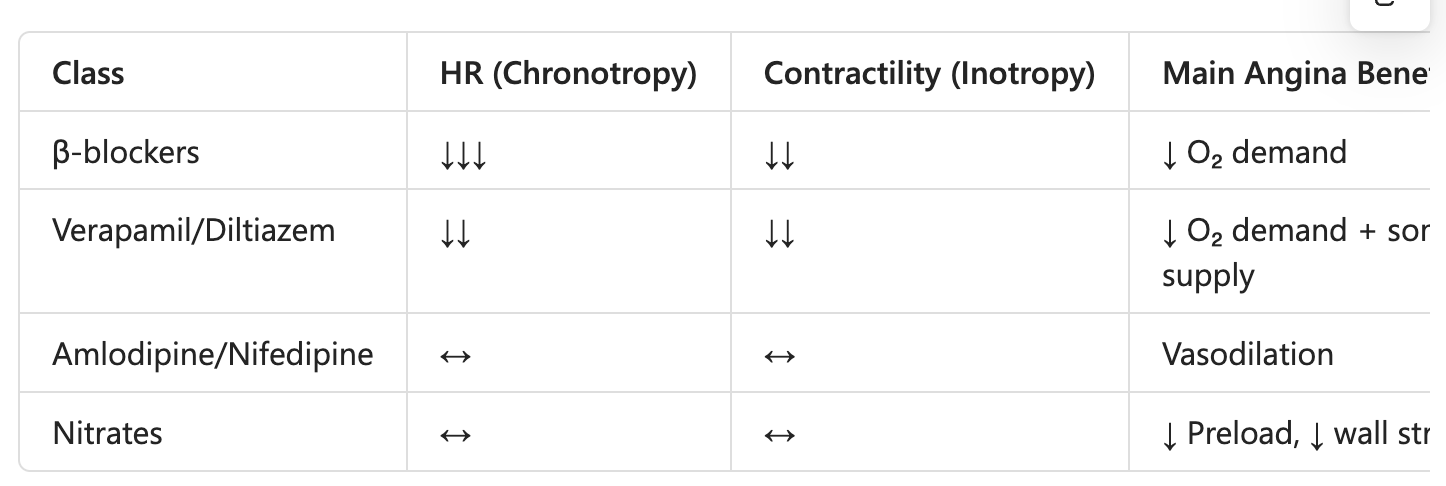
which of our drugs for symptom relief decrease chronotrophy (HR) and contractility (inotropy)
beta blocker, verapamil/diltiazem
work ON HEART
decrease O2 demand!
WHAT DO YOU NEED TO CHECK before you change BB dose
BLOOD PRESSURE AND HEART RATE
taper off as well
so how do dhp ccbs (amlodipine and others that work on periphery) and nitrates effect chronotropy (HR) and contractility (inotropy)
they DONT
its mostly vasodilation
goal heart rate if on BB (like if its lower no use)
55-60 bpm
what is CI for BBs
prinzmetal’s (vasospastic, variant) angina
can make spasm worse
names for prinzmetals
variant, vasospastic
what do the dhp do
peripheral
reduces afterload— peripheral vasodilate
what do the n-dhp do ? ad ef
negative chronotrope, inotrope
constipation, bradycardia