PHYSL 212 Lecture 9: Cardiac and Smooth Muscle (Terms)
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/30

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
31 Terms
Cardiac muscle is (striated/unstriated), and (larger/smaller) than skeletal muscle.
Unstriated, smaller
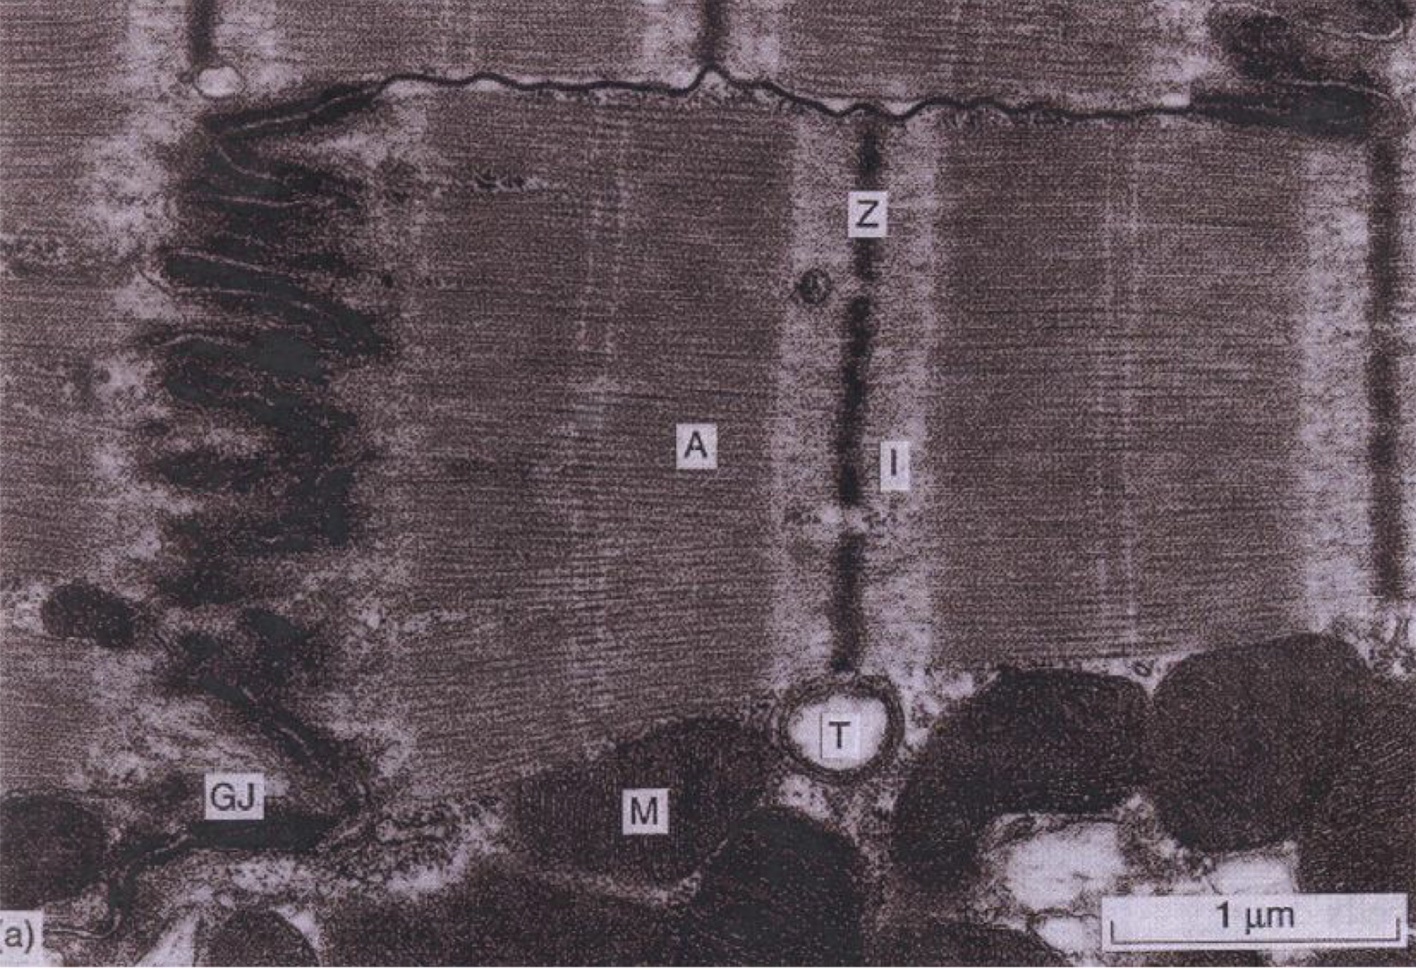
What are the elements within each intercalated disk? What are their respective roles in myocyte-to-mycoyte communication?
Desmosomes: mechanically/physically couple myocytes, holding them together
Gap junctions: electrically couple myocytes, allowing ion flow

Describe the microscopic filamentous structure of cardiac muscle (bands) in order.
In a sarcomere: z line, I band, A band (H zone and M line), I band, z line
Compare thin filaments in cardiac muscle to thin filaments in skeletal muscle.
Similar: F actin double helix, tropomysoin, troponin (TnC, TnT, TnI), nebulin
TnC has one calcium binding site in cardiac muscle, while TnC has 4 calcium binding sites in skeletal muscle
Compare thick filaments in cardiac muscle to thick filaments in skeletal muscle.
All have heavy and light myosin chains, but different isoforms
Titin (accessory protein) is different isoform, providing better elastic recoil in cardiac myocytes
Compare the T-tubule/sarcoplasmic reticulum complex in cardiac and skeletal muscle.
SR in cardiac muscles is not as well developed but equally important
T-tubules are 10x larger in cardiac myocytes
Cardiac muscle (the heart) is innervated by ___.
Autonomic nervous system: both divisions (sympathetic and parasympathetic)
Do ANS neurons trigger/turn on cardiac muscle contraction? If not, what does?
Neurons modulate cardiac muscle contraction (its always happening, they determine how fast)
Pacemaker triggers cardiac muscle contraction
Cardiac muscle expresses specific receptors for ___, which then control ___.
Circulating transmitters (epinepherine and norepinepherine), heart rate
Explain how the sarcoplasmic reticulum and t-tubule complex differs in cardiac and skeletal muscle.
Cardiac:
L-type channels (voltage gated)
Ryanodine receptors not physically coupled to channel (Ca2+ release channel)
Dyad: t-tubule only attached to SR on one side
TnC only has one low affinity binding site
Skeletal:
DHP receptors (voltage gated)
Ryanodine receptors physically coupled to channel
Triad: t-tubule attached to SR on both sides
TnC has two low affinity, two high affinity binding sites
Explain the role of extracellular Ca2+ in cardiac muscle contraction. How does this compare to skeletal muscle?
Extracellular Ca2+ is completely necessary for cardiac myocytes to contract, as the influx of calcium through L-type channels from the outside of the cell needs to happen in order for ryanodine receptor channels to open (SR releases calcium for muscle contraction)
In skeletal muscle contraction is not dependent on extracellular Ca2+, action potential arrival stimulates DHP receptor that physically opens ryanodine receptors regardless of whether or not Ca2+ flowed through L-type channels
How does contraction reaction speed of cardiac and skeletal muscle compare, and how does this explain the structure of their t-tubule SR complexes?
Skeletal muscle: quick, instant contraction upon receiving stimulus. Triad with SR on both sides of t-tubule so that intracellular Ca2+ increases very fast
Cardiac muscle: modulation of the heart is gradual. Dyad with SR on one side, intracellular Ca2+ increases slower
In CICR, where does the calcium come from? How does their differing location change their roles, and how much does each contribute?
Ca2+ from the outside of the cell (extracellular) via L-type channel: 10% of the Ca needed for contraction, initial calcium influx that causes more calcium to be released.
Ca2+ from the SR (intracellular) via ryanodine receptor: 90% of the Ca needed for contraction, amplifies the small amount of initial calcium to make up what is needed
In cardiac muscle, which pumps contribute the most to the removal of calcium from the cytoplasm to reset cross bridge cycles?
NCX and PMCA: ~10% low contribution
SERCA2A and calsequestrin: 90% high contribution
Explain the complete excitation-contraction coupling mechanism in cardiac muscle, from AP arrival to muscle contraction.
Muscle AP arrives and is propagated into T-tubule
Depolarization voltage change activates/opens L-type receptors on t-tubule membrane
Extracellular calcium enters the muscle cell via the L-type receptors
Ca2+ binds to the ryanodine receptors on the SR cisternae within the cell
Upon Ca2+ binding, calcium ions are released from storage in the SR
Conformational change in troponin, moving tropomyosin out of the way of myosin binding site
Actin binds to the myosin head, causing it to undergo cross-bridging contraction (Pi released, power stroke)
Ca2+ is removed from the cytoplasm via SERCA 2A until approximately < 10-7M to keep low enough for next cycle
Troponin resumes its original conformation and tropomyosin slips back to block the binding site

Smooth muscle is (striated/unstriated), meaning actin and myosin are (more/less) organized.
Unstriated, less
Describe the microscopic filamentous structure of smooth muscle.
Thick and thin filaments are interspersed, no organized bands

Compare the main participants of cross bridging in skeletal/cardiac muscle and smooth muscle.
Skeletal/cardiac: actin, tropomyosin, troponin, myosin
Smooth: actin, tropomyosin, myosin, calmodulin (no troponin)
No t-tubules in smooth muscle!
Smooth muscle is innervated by the __.
Autonomic nervous system
Does specialization of the membrane occur on multiunit or unitary smooth muscle? Explain.
Unitary
Each individual myocyte is innervated in multiunit → varicosities completely cover cell membrane, unable to specialize. Can’t contract together due to not being coupled
Only some myocytes innervated in unitary → areas of the muscle membrane are left open for function, not covered by varicosities. Able to contract together to perform specific functions due to gap junctions

What are the general locations that multiunit and unitary smooth muscle are found, based on their functions?
Multiunit: fine motor control and small precise movement (iris, cilliary muscle, piloerector muscle)
Unitary: specialized organ tissue (GI tract, uterus, bladder)
Smooth muscle myosin heads can only interact with actin (form cross bridges) when ___. Why?
Light chain is phosphorylated. Phosphorylation increases ATPase activity of the head, allowing it to bind to actin
Describe the slow-wave electrical activity that occurs in smooth muscle, including all contributing ions and channels.
Voltage gated calcium channels open, allowing the membrane to depolarize
An action potential spike occurs once membrane threshold is reached
Upon action potential, calcium influx into the cell due to opening of more V-gated calcium channels
Calcium dependent K+ channels open, which begins to repolarize the membrane as positive charge flows out
Because K+ channels close slowly, slow hyperpolarization occurs as more charge flows out
V gated calcium channels close, decreasing internal calcium concentration, adding to hyperpolarization
Due to decreased calcium concentration, Ca dependent K+ channels close, allowing the membrane to be repolarized

Explain the process by which MLCK is activated to phosphorylate the myosin heads in smooth muscle.
4 calcium ions bind to calmodulin, forming a Ca2+-calmodulin complex
The complex binds to MLCK, causing a conformational change that exposes an ATPase on the enzyme
ATP is hydrolyzed by the MLCK and the phosphate is added to the light chain of smooth muscle myosin heads
ATPase activity on the myosin head increases, allowing actin binding

Explain the process by which the myosin head light chain is dephosphorylated in smooth muscle. Why does this need to happen?
Myosin light chain phosphatase removes the phosphate from the myosin head light chain, which inhibits actin binding. Required for relaxation of smooth muscle

Myosin light chain phosphatase (is/is not) Ca2+ dependent. Explain.
Is not, must be able to dephosphorylate myosin heads in order to terminate contraction, which occurs in low concentration of calcium
Describe the elements of smooth muscle that allow calcium to enter upon excitation.
Voltage dependent L-type channels → allows extracellular Ca2+ to enter the cell upon action potential depolarization
Ligand-gated channels → extracellular ligands allow flow of calcium into cell
Ryanodine receptors RyR3, IP3 → release Ca2+ from the SR
Explain the complete excitation-contraction coupling mechanism in smooth muscle, from AP arrival to calcium removal and contraction termination.
Muscle AP arrives, depolarizing membrane and activates/opens V gated L-type calcium channels
Extracellular calcium enters the muscle cell via the L-type receptors
3 contributors to SR calcium store release:
G-protein receptor allows IP3 to move to SR membrane and activate Ca2+ release channels, causing calcium SR stores to be released
Ca2+ binds to the ryanodine receptors on the SR cisternae within the cell, causing SR calcium stores to be released
Calcium binding to calmodulin, forming complex
Calcium calmodulin complex activates MLCK, phosphorylating myosin light chain
Actin binds to the myosin head, causing it to undergo cross-bridging contraction (Pi released, power stroke)
Ca2+ is removed from the cytoplasm via SERCA until approximately < 10-7M to keep low enough for next cycle
MLCP dephosphorylates myosin light chain so that muscle can relax

In smooth muscle, which pumps contribute the most to the removal of calcium from the cytoplasm to reset cross bridge cycles?
Low: NCX, PMCA
High: SERCA, calreticulin
How does the latch-bridge mechanism work? Why does it happen?
Once calcium concentration drops, MLCP removes the phosphate group while the myosin head is still attached to actin, maintaining the cross-bridge as the detachment happens very slowly. The contraction is sustained without expending energy to create a new cross bridge for a new contraction
If an organ needs to be in a consistent state of contraction (ex. bladder), expending ATP to create a new bridge as soon as the old one dissipates would burn through too much energy
Compare skeletal, cardiac, and smooth muscle in terms of: method/location of excitation, primary calcium sensor, main contributors to E-C coupling, main contributors to contraction termination.
Skeletal: NMJ synapse (AP), troponin (TnC), DHP receptor physically coupled to ryanodine receptor RyRs, SERCA and calsequestrin
Cardiac: Gap junction at intercalated disc or pacemaker, troponin (TnC), L-type calcium channel and CICR of ryanodine receptor RyR2, SERCA and calsequestrin
Smooth: autonomic synaptic transmission or hormones or gap junctions between myocytes, calmodulin, V-gated calcium channels and Ca release channels modulated by IP3 and ryanodine receptor RyR3, SERCA and calreticulin and MLCP