peds exam 3 (neuro)
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/110

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
111 Terms
seizures
rapid firing of neurons in the brain that leads to kids not being aware or able to interact with the world around them
symptoms of something else happening
types of seizures
febrile
infantile
focal
drop/atonic
myoclonic
absent
generalized tonic-clonic
febrile seizures
never had a seizure before (1st time w no existing seizure disorder)
fixing fever may not stop seizure but they won’t have any more in the future
infantile seizure
looks like startle reflex

focal seizures
start in 1 area of brain and causes activity in that area
can become general tonic-clonic in the same episode
drop/atonic seizures
lose balance suddenly and fall
have to wear helmets

myoclonic seizure
sudden jerking
absent seizure
quick and unnoticeable
hardest to recognize

generalized tonic-clonic seizure
may have moaning, stiffening, and jerking

aura
having a feeling that a seizure is coming on

postictal phase
how do ppl act post-seizure?
usually: sleepy and out of it
VS in seizures
decreased RR
increased BP
goal with anti-epiletics
goal: get them down to only 1 med and taper all the others down
anti-epileptics slow everything down and make kids lethargic
usually trial and error on how many meds they have to take
when 1 med works, we slowly stop other or let them grow out of their dose
seizure precautions
side rails up
padded bedrails
low bed
pad floor with a mat incase they fall OOB
make sure O2 NC doesn’t wrap around them (if applicable)
put them on their side (usually you can’t)
turn chin to side
suction (for aspiration)
have O2 ready
clean area of anything that might hurt them
time seizure and remember what happened
alert band or necklace at all times
seizure precaution: turn chin to side
don’t hold it there
prevent aspiration
seizure precaution: time seizure and remember what happened
if a seizure goes over 5mins, they have status epilepticus and need rescue meds
ensure safety and have family monitor time so they know when to intervene at home
seizure rescue meds
nasal valium
if you’re in a room with the seizing pt, don’t leave room to get med; have someone else get them
education for meds with seizures
have rescue meds at all times
there are also daily maintenance meds
therapeutic management for seizures
fosphenytoin
fosphenytoin
Used for seizures bc its compatible w dextrose
neuro exam
Level of consciousness (LOC)
posture
Motor function
Sensory function
Cranial nerves
Reflex testing
Vital signs
neuro exam: LOC
Consciousness
unconsciousness
coma
altered LOC
consciousness
implies awareness
The ability to respond to sensory stimuli and have subjective experiences
2 components of consciousness
Alertness
Cognitive power:
2 components of consciousness: alertness
an arousal-waking state
ability to respond to stimuli
2 components of consciousness: cognitive power
ability to process stimuli and produce verbal or motor responses
unconsciousness
Depressed cerebral function
Inability to respond to sensory stimuli and have a subjective experience
levels of consciousness
Full consciousness
confusion
disorientation
lethargy
obtundation
stupor
coma
persistent vegetative state
full consciousness
Awake and alert, oriented to time, place, and person;
behavior appropriate for age
confusion
Impaired decision making
disorientation
Confusion regarding time and place; decreased LOC
lethary
Limited spontaneous movement, sluggish speech,
drowsy, falling asleep quickly
obtundation
Arousable with stimulation
stupor
Remaining in a deep sleep, slow response to vigorous and repeated stimulation or moaning responses to stimuli
coma
a state of unconsciousness from which the patient cannot be aroused even with powerful stimuli
Persistent vegetative state
– Permanently lost function of the cerebral cortex
– Eyes follow objects only by reflex or when attracted to the direction of loud sounds
– All limbs are spastic but withdraw from painful stimuli
– Reflexive grasp and groping of hands
– Facial grimace
– May be able to swallow some foods
– May groan or cry but utter no words
altered LOC
Altered LOC can be momentary or extend for hours, days, or indefinitely
assessment of LOC
LOC is determined by observations of the child’s responses to the environment
Parents can be useful in helping with this exam (how do they respond to parents calling name?)
≥ 3 years should be able to give their name
Young children may not be cognizant of place or time (ask abt time of day; breakfast/ daytime; ask abt who’s with them)
neuro assessment: how to determine LOC
pupils (especially when they don’t react to light relfexes; look for doll eyes)
interactive and paying attention
clapping and flinch reflex
reactive
appropriate verbal response
neuro assessment: how to determine LOC: pupils
Pinpoint pupils: poisoning and brainstem dysfunction
Dilated and reactive pupils: after seizures and trauma
Dilated and fixed pupils: paralysis of CN 3 due to pressure from herniation of brain; seen with hypothermia, anoxia, ischemia
Unilateral fixed pupil: lesion on same side
doll eye maneuver
normal: The eyes move in the opposite direction of the head turn. They stay focused straight ahead
abnormal: The eyes move along with the head, staying fixed in their sockets
neuro assessment: how to determine LOC (interactive and paying attention)
meaningful interaction w people and environment is good
neuro assessment: how to determine LOC (reactive)
reactive to touch, speech
follow ppl or objects
neuro assessment: Muscle tone
extended and flaccid posture= decreased tone

neuro assessment: cranial nerve 2
Yunger kid: shine light in eye (should blink)
Older kid: chart reading
neuro assessment: cranial nerve 3
Infant: shine light see if they follow
Older: 6 cardinal gazes
neuro assessment: cranial nerve 5
Infant: rooting and suck relfex
Older: touch forehead or cheeks or watch chewing
neuro assessment: cranial nerve 7
Infant: look at facial expression
Older: puff cheeks
neuro assessment: cranial nerve 8
Infant: blink when hear sound
Older: whisper test
neuro assessment: cranial nerve 9 & 10
Infant swallow and gaga
Older gag reflex
neuro assessment: cranial nerve 11
Older kids: shrug shoulders
Younger not rlly tested
neuro assessment: cranial nerve 12
Older kids: stick tongue out
Younger: sucking and swallowing
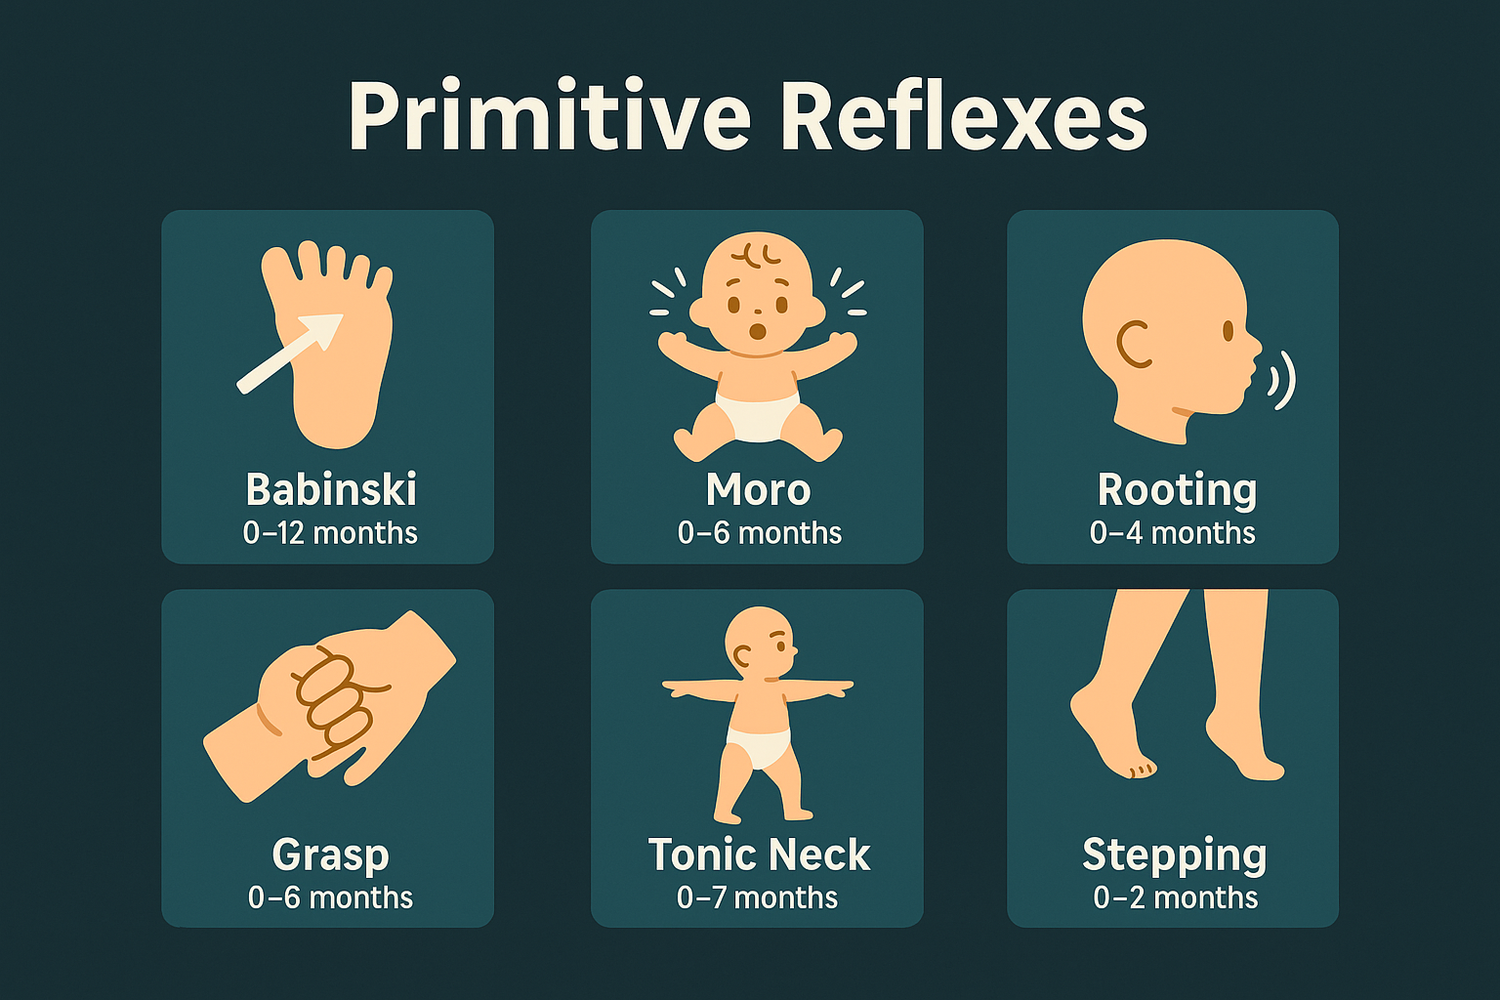
neuro assessment: reflexes (young infants)
Moro
tonic neck
withdrawal reflexes are key to neurologic health
glascow coma scale (GCS)
A scale used to standardize the description and interpretation of the degree of depressed consciousness
Assesses eye opening, verbal response, and motor response
A decrease in the GCS score indicates deterioration of the child’s condition
how to assess GCS
look at things that happen spontaneously
<1 year= open eyes to noise
spontaneous movement
younger kids= do they smile at mom?
GCS scoring
Highest score of 15 = unaltered LOC
≤ 8 = coma
lowest score of 3 = deep coma
A decrease in the GCS score indicates deterioration of the child’s condition
Reyes syndrome: patho
encephalophy in brain (swelling and irritation in brain)
causes of Reyes syndrome
bc of viral infection (Chicken pox or flu)
Risk w those 2 viruses
Aspirin causes it as well
rabies
Can cause encephalopathy and great deterioration
caused by getting bit by a rabid animal
tx for rabies
IVIG
Will die without getting immunoglobulin
botulism
Can come from honey or baby formula
Cosmetic uses: botox
Kids can become paralyzed
tx of botulism
Immunoglobulin: baby BIG
neural tube
structure in utero when baby spine is being formed as well as protection around it

neural tube defect
protection around it spinal cord grows abnormally
Usually in lumbar= no control of legs and bladder/bowel control
High up in the spine= more problems (may not be able to breathe when it gets high enough)
prevention of neural tube defect
folic acid
types of neural tube defects
Anencephaly
Myelodysplasia
neural tube defect: anencephaly
most serious congenital NTD in which both cerebral hemispheres are absent; not compatible with life

neural tube defect: Myelodysplasia:
malformation of the spinal cord and canal
Midline defects involving the failure of the osseous spine to close are called spina bifida
Spina bifida occulta
Spina bifida cystica
types of spina bifida cystica
■ Myelomeningocele
■ Meningocele
spina bifida cystica: myelomeningocele
Spina bifida cystica
prone to having chiari malformation

char malformation
brain tissue extends into spinal cord
structural defect that causes hydrocephalus
Head gets rlly big

dx of neural tube defects
prenatally (CVS, ultrasound, elevated AFP)
after birth from physical exam findings, CT, MRI, and US of brain and spinal cord
brain death protocol
apnea test
Usually transport these pts at night bc there's less traffic
brain death protocol: apnea test
done at 2 diff times w 2 physicians assessing child at same time
Kid on vent or can't breathe on own (if they're spontaneously breathing; they're not brain dead)
We take away vent and see if kid can spontaneously breathe on their own
then we get ABG to see CO2 and O2 blood test
brain death protocol: apnea test (ABG to see CO2 and O2 blood test)
PaCO2: at least 60
Rise at least 20 points higher than baseline
If yes, brain dead (organ donation questions for fam)
patho of hydrocephalus
CSF is produced and reabsorbed in ventricles
Too much CSF means accumulating in ventricles= ventricles get bigger and
2 types of hydrocephalus
Communicating and flow around
Non communication= no flow
communicating hydrocephalus
Usually a reabsorption problem
Therapuetic management of hydrocephalus
shunting to drain fluid (VP shunt)

EVD placememt
The position of the EVD would be maintained at the level of the external auditory meatus (tragus)
Bc ear is a high point of body and is working w gravity (CSF drains slow which is what we want)
Don't lay kid on side w EVD bc it can accidentally press button and cause fluid to drain
how does the placement of a VP shunt help with hydrocephalus?
Lots of tubing (back of ear w buttons you can manually take fluid out of brain and into peritoneal cavity
Drains fluid
Reabsorbs

s/s of hydrocephalus
Irritability (bc of increased ICP)
Increased head circumference rapidly
Anterior fontanel slightly bulging
Tachycardia
Fever
Increased BP
Emesis
Head lag
Decreased feeding
dx tests for hydrocephalus
CT (looks at ventricle size)
LP (looks at CSF fluid to determine infection)
look for signs of increased ICP
s/s of increased ICP in infant
Tense, bulging fontanelle
Widened sutures
Irritability and restlessness
Drowsiness
Increase sleeping
High-pitch cry
Poor feeding
Setting-sun sign
s/s of increased ICP in child
Headache
Nausea
Forceful vomiting
Diplopia, blurred vision
Seizures
Indifference, drowsiness
Decline in school performance
Lethargy
normal CSF pressure
15 mmHg
nursing care for increased ICP
Keep head positioned midline with the head of bed elevated 15-30°
Avoid activities that can cause pain or emotional stress
minimize noise
suction only as needed
routine cleansing and mouth care
strict I&O
traumatic brain injury
Injury involving the scalp, skull, meninges, or brain as a result of trauma
patho is related to force of impact
3 major causes (listed in order) of traumatic brain injury
– Falls
– Motor vehicle injuries (almost exclussively the cause in <2)
– Bike injuries
physical impacts from trauma
acceleration
deceleration
deformation
brain shape in trauma
Coup (point of impact)
Contrecoup (point brain collides with that is far removed from point of impact)

cerebral palsy
A group of permanent disorders of the development of movement and posture, causing activity limitation, that are attributed to nonprgressive disturbances that occurred in the developing fetal or infant brain
Can develop postnatally (meningitis, encephalitis, trauma)
how is cerebral palsy characterized
abnormal muscle tone and coordination
Most common permanent physical disability of childhood
classifications of cerebral palsy
Spastic (Pyramidal)
Dyskinetic (Nonpastic, Extrapyramidal)
Ataxic (Nonpastic, Extrapramidal)
mixed type
spastic cerebral palsy
persistent primitive reflexes
positive Babinski
ankle clonus
exaggerated stretch reflexes
eventual contractures
diplegia
hemiplegia
hypertonicity
Impairment of fine and gross motor skills

dyskinetic cerebral palsy
Athetoid
Dystonic-slow, twisting movements of the trunk or extremities; abnormal posture
imperfect speech
dyskinetic cerebral palsy: athetoid
chorea (involuntary, irregular, jerking movements)]
characterized by slow, wormlike, writhing movements that involve the extremities, trunk, neck, facial muscles, and tongue
dyskinetic cerebral palsy: imperfect speech
drooling and dysarthria
oral muscles involved
ataxic cerebral palsy
Wide-base gait
Rapid, repetitive movements performed poorly
Disintegration of movements of the UE when the child reaches for objects
mixed type cerebral palsy
Combination of spastic CP and dyskinetic CP