Traumatic Brain Injury
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/72

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
73 Terms
traumatic brain injury (TBI)
nondegenerative, noncongenital alteration in brain function caused by external force; often includes loss of consciousness, confusion, visual and sensory loss, and/or hemiparesis
What are some non-traumatic brain injuries?
anoxia, infections, strokes, tumors, and metabolic disorders
What are some traumatic brain injuries?
assaults, falls, accidents, abuse, and surgery; can be open brain (penetrating) or closed brain (internal pressure / shearing)
hemi-
half
-paresis
weakness
-plegia
paralysis
hyper-
increase
hypo-
decrease
-tonic
tone
How are TBIs described?
mechanism of injury (e.g., closed, penetrating, brain blast), causes (e.g., falls, motor vehicle accidents, violence/abuse, sports/work)
What are the risk factors for TBI?
age (≥75), male gender, native American / Alaskan native, African-American, low SES, drug/alcohol abuse, exposure to firearms
What are some symptoms of a mild TBI?
anxiety, balance problems, difficulty concentrating / confusion, difficulty falling asleep, dizziness, fatigue, headache, irritability, immediate loss of consciousness, memory problems, motor incoordination, early nausea/vomiting, sadness / more emotional, seizures, light/sound sensitivity, sleeping more/less than usual, vision problems
What are some symptoms of a moderate or severe TBI?
losing consciousness, hearing or vision issues, aggressiveness, trouble communicating, changes in sensory perception
How was Phineas Gage able to survive?
rod passed behind left eye and exited through the skull just behind the hairline; it missed major arteries, major optic anatomy, brainstem, and critical parts of central ventricular system; injury caused skull to “hinge” open, which relived intracranial pressure
What is the connection between Phineas Gage’s injury and his post-injury state?
rod severed connection of left frontal lobe to emotional networks of limbic system and cognitive networks of right frontal cortex → after the injury, Gage was impulsive, rude, and unreliable
primary injury
forces that occur at the time of initial injury/impact
translational injury
injury that occurs at a different location than the original impact; includes coup-countercoup injuries
coup-countrecoup injury
after the site of initial impact creates a lesion (coup injury), the brain shifts across the skull and impacts the opposite side of the skull (countrecoup injury); type of translational injury
rotational injury
occurs when the head experiences a sudden, forceful rotation or angular acceleration; brain remains stationary but the skull rotates; results in shearing injury causing diffuse axonal injuries (DAI) and deep brain injuries (i.e., to the brainstem)
Glasgow Coma Scale (GCS)
scale that rates eye, verbal, and motor responses of patients with impaired consciousness or coma; used to classify TBIs as mild, moderate, or severe
mild TBI
GCS score of 13-15, loss of consciousness for < 30 seconds, and symptoms lasting < 24 hours
moderate TBI
GCS score of 9-12, loss of consciousness between 30 minutes and 24 hours, and amnesia between 24 hours and 7 days
severe TBI
GCS score of 3-8, loss of consciousness for more than 24 hours and amnesia for more than 7 days
concussion
mild TBI induced by biomechanical forces; indicated by confusion and slow reaction time; usually not seen on scans; mild symptoms at onset steadily lesson over 2 weeks and typically resolve within 3 months
second impact syndrome
second concussion occurs before first concussion’s symptoms resolve
post-concussion syndrome
condition in which a concussion’s symptoms worsened since onset and persisted for 3 months or more
diffuse axonal injuries
type of rotational brain damage in which there are small lesions in white matter tracts of cortex; rapid shifting and rotating of brain inside skull causes long connecting fibers to be sheared

Which TBI classification scale is this?
NIH classification scale for TBI
subdural hematoma (SDH)
bleeding that occurs between the brain and the dura; associated with brain damage; most common form of hematoma in children under two
What causes subdural hematomas?
TBI, birth trauma, abuse, post-op complications
epidural hematoma (EDH)
arterial bleeding between skin and dura; may not cause brain damage if treated urgently; uncommon before age 3
What causes epidural hematomas
severance of middle meningeal artery due to depressed skull fracture
intracerebral hematoma (ICH)
bleeding into the brain tissue itself
What causes intracerebral hematomas?
TBI or rupture of a congenital vascular malformation
subarachnoid hematoma
bleeding into the subarachnoid space (between arachnoid and pia mater)
What causes subarachnoid hematomas?
TBI, abuse, rupture of CVM
intraventricular hemorrhage (AVH)
bleeding into the ventricles; can be unilateral or bilateral
How are hematomas treated?
surgical evacuation, monitoring (SAH & IVH), shunt (IVH only)
What percent of people with a concussion experience post-concussion syndrome?
15%
What are some risk factors for post-concussion syndrome?
previous head injuries, complications (i.e., skull fracture, midline shift), history of behavioral conditions, higher number of symptoms or increased severity of symptoms
What factors are associated with poor prognosis for a TBI?
older age, hispanic ethnicity, low SES, history of intracranial injury, premorbid histories of mTBI or increased pre-injury symptoms, neurological or psychiatric disorder, learning difficulties / lower cognitive ability, family and social stressors
Which scales are validated to use for diagnosing / classifying a TBI?
Post-Concussion Symptom Scale, Health and Behavior Inventory, Post-Concussion Symptoms Inventory, Acute Concussion Evaluation, Ranchos Los Amigos
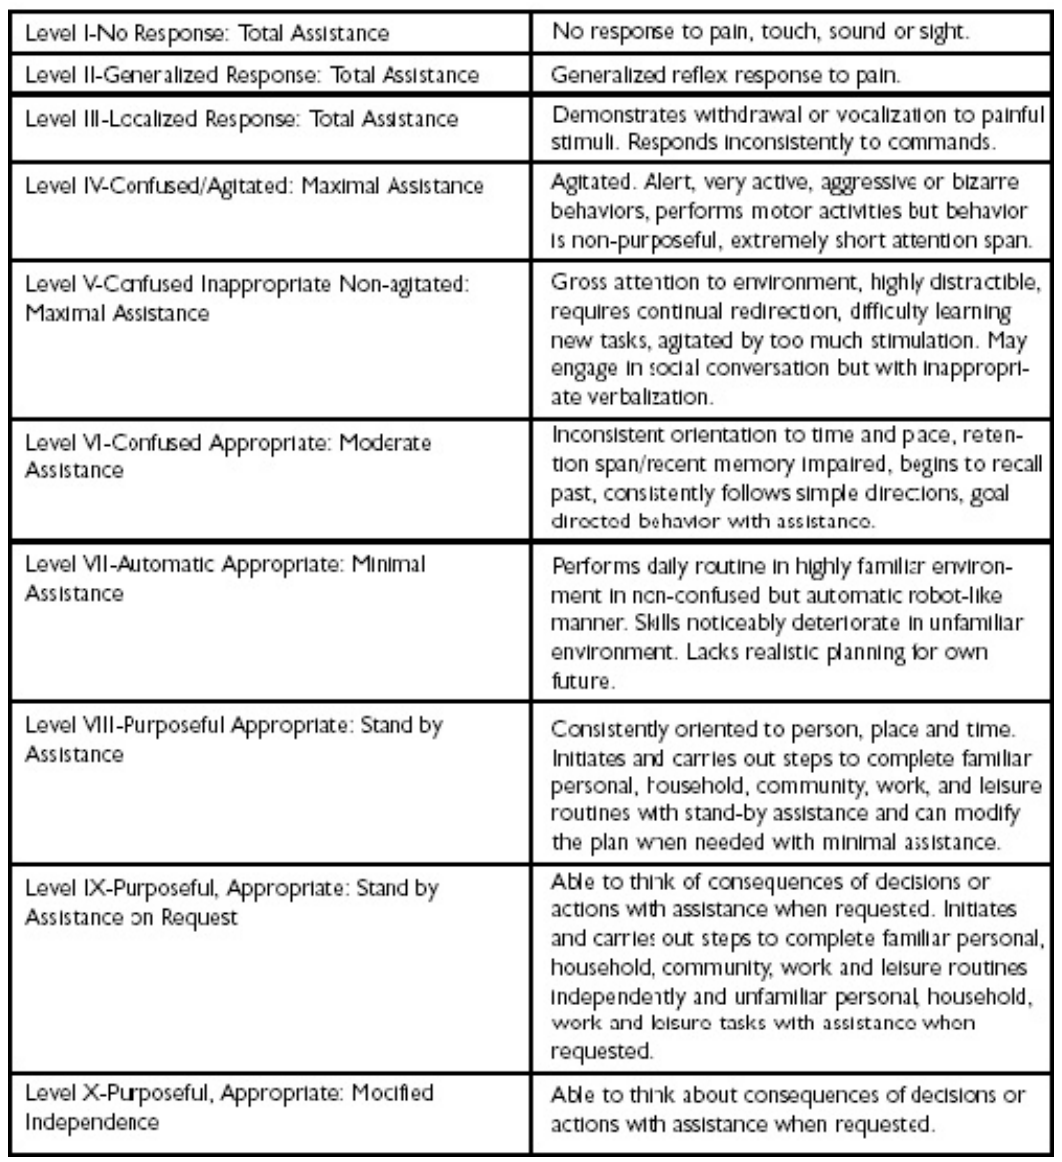
Which validated TBI scale is pictured?
Ranchos Los Amigos
What are some medical complications of TBI?
deep vein thrombosis (DVT), heterotropic ossification, cognitive and behavioral issues, peripheral nerve injuries, auditory / vestibular dysfunction, visual dysfunction, motor deficits, post-traumatic seizures, post-traumatic hydrocephalus, subdural fluid collections, fever and infections (e.g., meningitis or brain abscess)
What functional deficits may occur after damage to CN I (olfactory)?
damaged / lost sense of smell, impacted ability to taste (since this is related to smell)
What functional deficits may occur after damage to CN II (optic)?
visual impairments to one or both eyes
What functional deficits may occur after damage to CN III (occulomotor)?
droopy eyelid, changes in pupil’s response to light, abnormalities in eye movements (up-down, side-to-side)
What functional deficits may occur after damage to CN IV (trochlear)?
torsional or vertical diplopia (types of double vision), involuntary eye movement (nystagmus)
What functional deficits may occur after damage to CN V (trigeminal)?
motor and sensory dysfunction in forehead, cheeks, and jaw; impacted teeth clenching; impacted blinking
What functional deficits may occur after damage to CN VI (abducens)?
horizontal diplopia (double vision)
What functional deficits may occur after damage to CN VII (facial)?
one side of the face unable to make expressions; abnormal lip movement; droop in eyebrows, mouth, or both; altered taste
What functional deficits may occur after damage to CN VIII (vestibulocochlear)?
impacted sense of hearing, impacted balance, dizziness, difficulty walking, difficulty sitting or standing, increased risk of falls
What functional deficits may occur after damage to CN IX (glossopharyngeal)?
loss of taste sensation to posterior 1/3 of tongue, difficulty swallowing
What functional deficits may occur after damage to CN X (vagus nerve)?
difficulty swallowing (dysphagia), hoarseness, irregular heartbeat or heart palpitations, GI issues, irregular changes in blood pressure, overactive amygdala
What functional deficits may occur after damage to CN XI (accessory nerve)?
difficulty shrugging shoulders and turning head to the side
What functional deficits may occur after damage to CN XII (hypoglossal)?
issues with controlling tongue movements
What are the main roles of an OT in TBI?
prevent complications (acute phase), minimize impariment (post-acute phase), and improve function (long-term)
What do OTs assess for clients with TBI?
ADLs, functional mobility, balance, upper extremity function (e.g., ROM, tone, subluxation, pain, sensitivity), cognition (e.g., impulsivity), visual perception, communication (e.g., aphasia), psychosocial, behavioral
What types of interventions do OTs provide for clients with TBI?
ADLs (adaptations), functional mobility, balance, upper extremity function, cognition (safety), visual perception, communication, psychosocial
brain tumor
cancerous or non-cancerous growth that puts pressure on the surrounding brain tissue; classified as primary or secondary
primary brain tumor
brain tumor that develops inside the brain
secondary brain tumor
tumor that spreads to the brain, 10x more common
nonmalignant brain tumor
benign, non-cancerous brain tumor; does not spread to body tissue; can become life threatening
malignant brain tumor
abnormal cancerous cells of brain tumor spread to other tissues; glioma is the most common type in adults (81%)
medulloblastoma
brain tumor in the cerebellum caused by damage to DNA of precursor cells (blasts); most common in children (64.3% of embryonal tumors)
What causes brain tumors?
genetic risk factors, ionizing/nonionizing raditation, allergic conditions, pesticide/chemical exposure
What are the demographic risk factors for brain tumors?
caucasian (glioma), African-American (meningioma), age 75 to 84 (glioblastoma), female (meningioma)
What are the symptoms of a brain tumor?
mainly depends on location of tissue damage, but commonly includes fatigue, headache, nausea, vomiting, mood disorder, behavioral impairment, seizure, focal neurological deficits
How are brain tumors diagnosed?
sudden onset of neurological conditions, MRI (with or without contrast), CT scans, PET scans

Which brain tumor diagnostic guide is depicted here?
WHO Brain Tumor Guide
What is the prognosis for primary malignant brain tumors?
34.9% 5 year survival rate, 29.3% 10 year survival rate
7 to 15 month survival period for glioblastoma
comparatively, 90.4% for nonmalignant tumors
Almost all children and adolescents live beyond five years following diagnosis
How are brain tumors medically/surgically managed?
surgery, chemotherapy, radiotherapy, stereotactic radiosurgery (precision), steroids/antiepileptic drugs, carmustine wafers, tumor treating fields (TTFs), stress management
What areas of occupational performance do acquired brain injuries (ABIs) impact?
developing/maintaining social networks, sleep/rest, driving skills, organizing one’s own medical care, learning, engagement in health/wellness activities, toileting, feeding