chapter 24: disorder of white blood cells & lymphoid tissues
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/100

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
101 Terms
what are the two components of blood?
cellular (45%) and plasma (55%)
blood is 8% of body weight, w/ avg adult having ~4.6-6 liters
what consist of cellular components?
erythrocytes (rbc)
leukocytes (wbc)
neutrophils, eosinophils, basophila, monocytes, lymphocytes
thrombocytes (platelets)
what consist of plasma?
pale yellow fluid: ??
92% water + 8% proteins (albumin, fibrinogen, globulins)
blood transports:
oxugen, carbon dioxide, hormones, nutrients, and metabolic waste products
blood regulates what and what does it carry?
it regulates body temp and acid-base balance
carries cells + antibodies that fight infection
centrifugation
lab process that spins a blood sample at high speeds to separate it into its different parts (liquid, white cells, and red cells) based on their weight
performed in lab before blood testing
white blood cells
aka leukocytes, are also immune cells that protect body against infections, foreign substances and disease
leukocytes classified as granular and agranular
granular (leukocyte classification)
contains vesicles that appear when cells are stained
neutrophils, eosinophils, basophils
agranular (leukocyte classification)
contains no granules
lymphocytes, monocytes
what are all the leukocytes?
neutrophils, eosinophils, basophils, monocytes, macrophages, t cells, b cells, nk cells
neutrophils (leukocyte)
most abundant wbc
destroy bacteria through phagocytosis
eosinophils (leukocyte)
fight parasites
involved in allergic reactions
basophils (leukocyte)
release histamine and heparin
participate in inflammation and allergic responses
monocytes (leukocyte)
circulates in bloodsteram
macrophages (leukocyte)
form when monocytes enter tissues, engulf pathogens (phagocytosis)
t cells (leukocyte)
coordinates immune response
b cells (leukocyte)
produces immunoglobulins
NK cells
part of innate immunity
hematopoiesis
formation and developing all types of blood cells in body
pluripotent stem cells give rise to what?
give rise to lymphoid stem cells and myeloid stem cells
leukopoiesis is the process of what?
process of producing wbc (leukocytes) in bone marrow
myeloid stem cells and lymphoid stem cells involved
in leukopoiesis, myeloid stem cells produce what?
granulocytes and monocytes
in leukopoiesis, lymphoid stem cells produce what?
produce t cells, b cells, and NK cells
hematopoietic growth factors is what?
hormone-like regulatory molecules that help in survival, differentiation, and proliferation of progenitor cells
functional activation of mature cells
lineage-specific growth factors stimulate what?
development of specific WBC types
granulocyte colony-stimulating factor (lineage-specific growth factors)
stimulates production of neutrophils
macrophage colony-stimulating factor (lineage-specific growth factors)
stimulates development of monocytes and macrophages
interleukin-5 (IL-5) (lineage-specific growth factors)
promotes growth and development of eosinophils
interleukin-7 (IL-7) (lineage-specific growth factors)
supports the dev of lymphocytes, especially b and t cells
differenctial WBC count measures what?
the percentage and absolute number of each type of leukocute in blood
shift to the left refers to what in diff WBC count?
refers to increase in immature neutrophils (bands) in peripheral blood
indicates that blood marrow releases neutrophils early in respones to increase demand
whats the normal neutrophil maturation?
myeloblast → promyelocyte → myelocyte → metamyelocyte → band neutrophil → segmented (mature) neutrophil
during a left shift, the bone marrow release more:
band neutrophils (most common)
occasionally metamyelocytes and myelocytes in severe cases
lymphatic system consist of:
lymphatic vessels
lymph nodes
lymphoid tissues
thymus
spleen
four major functions of lymphatic system:
defends body against pathogens
produces and matures lymphocytes
filters lymph and blood
supports adaptive (specific) immunity
lymphoid tissues are categorized into:
primary and secondary
primary lymphoid tissues are:
where lymphocytes become mature and immunocompetent
bone marrow, thymus
bone marrow (primary lymphoid tissue)
site of dev of lymphocyte progenitor cells + maturation of immature b cells
thymus (primary lymphoid tissue)
trains and matures T-cells, which protect the body from viruses, bacteria, and infection + is the largest and most active during childhood and gradually shrinks and turns into fat after puberty
secondary lymphoid tissues are:
where lymphocytes are activated by antigens
lymph nodes, spleen, MALT
lymph nodes (secondary lymphoid tissue)
small, bean-shaped structures in your immune system that act as filters for your body's fluid??
spleen (secondary lymphoid tissue)
white pulp contains concentrated areas of b and t cells, whereas red pulp contains venous sinuses that filter blood by removing pathogens + senescent erythrocytes
MALT (secondary lymphoid tissue)
non-capsulated lymphoid tissue in GI tract, respiratory tract, and genitourinary system
non-neoplastic disorders
non-malignant disorders of WBCs are more common than malignant disorders
some disorders (neo-plastic) affect count of single type of WBC, whereas others affect:
counts of multiple or all five types of WBCs
common neoplastic disorders involve changes in:
neutrophil or lymphocyte count
-penia = deficiency, lack, or abnormal reduction in the number of something within the body
-cytosis = an abnormal increase or elevated condition in the number of cells, typically blood cells
absolute neutrophil count (ANC)
actual number of neutrophils circulating in blood
WBC = total wbc count
segs = % mature neutrophils
bands = % immature neutrophils
ex: Total WBC count = 10,000 cells/μL, Segs = 60%,
Bands = 5% : ANC=10,000×60+5/100
ANC = 6,500 cells/μL
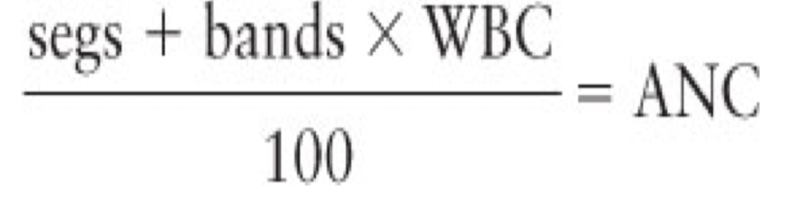
leukopenia
decrease in total number of wbc in blood
most commonly involves neutrophils, leading to neutropenia
neutropenia
a condition where you have an abnormally low number of neutrophils
ANC <1000 cells/μL
normal range: 2000-7000/μL
increased risk for infection
agranulocytosis
nearly complete absence of neutrophils
extremely high risk of life-threatening infection
types of neutropenia
congenital and acquired
congenital neutropenia
present at birth due to: genetic disorders affecting neutrophil production
acquired neutropenia
develops later in life due to: chemotherapy, viral infections, autoimmune diseases, bone marrow diseases
patients become prone to recurrent infections:
bacterial/fungal, immunosuppressed
common features of neutropenia:
frequent or recurrent infections
fever: may be only sign
treatment of neutropenia:
antimicrobial agents
specific hematopoietic growth factors
ex: GM-CSF
neutrophilic leukocytosis (granulocytosis):
abnormally increased total WBC count caused mainly by an increase in neutrophils
more than: 7500/μL
normal range: 2000-7000/μL
most common cause of neutrophilic leukocytosis:
acute bacterial infection
evident in first stages of infection or inflammation
other causes of neutrophilic leukocytosis:
inflammation, corticosteroid use, certain blood cancers, such as leukemia
if need for neutrophils increases beyond supply, then immature neutrophils are released into blood
premature release of immature leukocytes is termed a shift-to-the-left
lymphocytopenia (lymphopenia):
an abnormally low number of lymphocytes in blood
less than: 1000/μL
normal: 1000-4500/μL
common causes of lymphocytopenia (lymphopenia):
inherited genetic disorders
chemotherapy and radiation therapy
viral infections
patients become prone to recurrent infections from lymphocytopenia:
initial infections may not be fully eliminated, allowing pathogens to persist and cause repeated infections
treatment for lymphocytopenia (lymphopenia)
antimicrobial agents
IV immunoglobulins
lymphocytic leukocytosis
increased total WBC count caused mainly by increase in lymphocytes
more than: 4500/μL
normal range: 1000-4500/μL
common causes of lymphocytic leukocytosis
infectious mononucleosis: contagious viral illness known as Epstein-Barr virus that spreads through saliva and causes extreme fatigue, a severe sore throat, fever, and swollen lymph nodes
chronic immune mediated inflammation (ex: RA)
chronic lymphocytic leukemia (CLL)
treatment of lymphocytic leukocytosis:
focus on underlying cause
malignant lymphomas
solid malignant tumors originating in peripheral lymphoid tissues (typically lymph nodes)
two main categories: hodgkin’s lymphomas (HLs), non-hodgkin’s lymphomas
hodgkin’s lymphomas (HLs)
originate in single lymph node or a group of adjacent lymph nodes
neck, chest pits
non-hodgkin’s lymphomas (HLs)
originate in multiple lymph nodes or multiple groups of lymph nodes
chest, pits, abdomen, groin
non-hodgkin lymphomas are a heterogeneous:
group of cancers affecting lymphocytes at different stages of development
disruption of normal lymphocyte maturation can result in:
various NHL subtypes
exact cause remains unknown
associated infectious agents include:
epstein-barr virus (EBV)
human t-lymphotropic virus type 1 (HTLV-1)
mature b-cell lymphomas originate from:
germinal center of b cells or activated b cells that have exited the germinal center
most common subtype of non-hodgkin lymphoma (NHL)
common b-cell lymphoma subtypes include:
follicular lymphoma
diffuse large b-cell lymphoa
mantle cell lymphoma
follicular lymphoma (common b-cell lymphoma)
indolent (slow-growing)
diffuse large b-cell lymphoma (DLBCL) (common b-cell lymphoma)
aggressive, fast growing, most common btwn 60-70 years
mantle cell lymphoma
aggressive, characterized by rapid disease progression and poor prognosis
follicular lymphoma
normal lymph node architecture is replaced by malignant lymphoid follicles in a back-to-back pattern
burkitt lymphoma
highly aggressive b-cell non-hodgkin lymphoma
fast-growing tumor of jaw and facial bones = tumor of jaw distorts a child’s face
classified based on geographic distribution = endemic (african), sporadic
endemic (african) burkitt lymphoma
a fast-growing type of non-hodgkin b-cell cancer that primarily affects children in equatorial africa
closely associated w/ EBV infection (100% of patients w/ endemic african burkitt lymphoma show evidence of prev EBV infection)
sporadic burkitt lymphoma
fast-growing, rare subtype of b-cell non-hodgkin lymphoma that occurs worldwide
less frequently associated w/ EBV
NHL clinical manifestations:
localized or generalized painless lymphadenopathy
nodal enlargement + transformation over months or yrs
retroperitoneal + abdominal masses w/ symptoms of abdominal fullness and back pain
ascites (fluid in peritoneal cavity) + leg swelling
NHL diagnostic tests:
biopsy is primary means of diagnosis
hodgkin lymphoma (HL) is distinguished by:
presence of abnormal Reed-Sternberg cell
HL commonly occurs in two age groups:
young adults: most commonly affects adolescents and young adults aged 15–35 (or roughly 20–40 depending on the exact source), making it the most frequent cancer diagnosed in teenagers aged 15–19
older adults: occurs again later in life, typically in adults aged 55 and older
HL clinical manifestations:
enlarged painless neck lymph nodes
usually begins in simple lymph nodes or chain of nodes
lymphadenopathy, causing pressure or obstruction
mediastinal mass
fever, weight loss, night sweats, pruritus, fatigue
description of hodgkin lymphoma
classic reed—sternberg cell, mirror-image nuclei
“owl’s eye” two large nuclear lobes, each w/ prominent red nucleolus surrounded by clear halo
stage 1 of hodgkin lymphoma
cancer found in one lymph node region or one lymphoid organ
ex: spleen or thymus
stage 2 of hodgkin lymphoma
cancer involves two or more lymph node regions on same side of diaphragm (either above or below)
may also involve nearby extranodal site
stage 3 hodgkin lymphoma
cancer present in lymph node regions on both sides of diaphragm
may also involve spleen or nearby extranodal organ
stage 4 of hodgkin lymphoma
cancer spread widely to one or more extranodal organs, such as: bone marrow, live, lungs, bones
leukemia
malignant neoplasms of hematopoietic precursor cells
characterized by uncontrolled growth of immature wbc
these abnormal cells replace normal bone marrow cells, affecting blood cell production
approx 60k-62k new cases diagnosed annually
most common cancer in children + adolescents
accounts for approx 29% childhood cancers
leukemia means white blood, first used by rudolf virchow, which described:
the abnormal increase in wbc compared w/ rbc
leukemias are classified based on:
predominant cell type
lymphocytic (lymphoid)
myelogenous (myeloid)
disease progression
acute
chronic
french-american-british (FAB) classification identifies 4:
ALL: acute lymphocytic (lymphoblastic) leukemia
CLL: chronic lymphocytic leukemia
AML: acute myelogenous (myeloblastic) leukemia
CML: chronic myelogenous leukmeia
acute leukemia:
presence of undiff or immature cells, usually blast cells
sudden onset, rapid progression w/ short survival
symptoms severe + dev quickly
chronic leukemia
predominant cell mature but not function normally
slow, gradual onset w/ slow progression
symptoms mild or absent initially, dev over months or years
lymphocytic leukemias: origin, common sites of infiltration, and clinical consequences
origin: dev from immature lymphocytes + precusor cells in bone marrow
csoi: spleen, lymph nodes, cns
cc: impairs normal immune function + lymphocyte production
myelogenous leukemias: origin, interferes w/ maturation of, and clinical consequences
origin: arise from pluripotent myeloid stem cells in bone marrow
iwmo: granulocytes, erythrocytes, thrombocytes
cc: increase risk of infections, anemia, bleeding tendencies
exact cause of leukemia:
largely unknown
develops due to genetic + environmental factors
molecular basis for leukemia:
develops due to disruption of genes + chromosomal abnormalities controlling blood cell dev, growth, and survival
leads to uncontrolled prod of abnorm blood cells
molecular has improved w/:
diagnosis + classification into specific subtypes
targeted treatment selection
monitoring of treatment response + disease progression