Denture Anatomy, Fit, and Fabrication: Maxillary and Mandibular Principles
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/81

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
82 Terms
which frenum is the largest/ strongest?
labial frenum- this will require the most adjusting of the pt's denture
The max labial frenum is requires trimming of which part of the denture?
labial vestibule
which areas on the max CD could be sensitive and require relief?
incisive papilla
rugae\max tuberosity
hamular notches
palatal suture
which part of the maxilla resorbs quickly?
max anterior
what defines the posterior seal of the max CD?
hamular nothces
what feature of the posterior palatal seal helps with retention?
softer tissue, compression
posterior limit of the denture

where is the vibrating line located?
at the junction of movable and immovable soft palate
what are the primary stress bearing in the max?
-make stops in the CD\

which areas to avoid w/ the max CD?
buccal slops and ridges of vestibule
T/F: mand has a buccal and lingual vestibule
T
area on mand with muscle insertions and requires a relief
masseter muscle
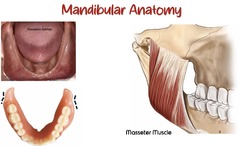
when you move the cheeks, what anatomical location will be marked on the BOMO?
masseteric notches and frenum
which area serves as good retention on the mand?
retromylohyoid fossa

what are the primary, secondary and non-stress bearing areas on mand dentures?
primary- buccal shelves
secondary- ridges
non-stress- buccal and lingual inclines of ridges and vestibules

where do you place stops on the mand denture?
buccal shelves- flat and allows for better support
where should the max denture extend to posteriorly? mand denture posterior extension?

what way does the max resorb? what way does the mand resorb?
Max: lose a lot of lip support, goes up and inward
Mand: down and outward- looks like class III because maxilla has lost bone and resorbs superiorly and posteriorly
what 3 areas could require relief on the mand as it resorbs?
-mental foramen
-mylohyoid line
-buccal shelf

what is done during the start check?
-x-rays
-Comp ex and PDI classification
-Complete denture form
-diagnostic casts

pt comes ready for denture (all teeth are ext) just needs to change denture. when can tx be presented?
same day as comp exam
pt needs FM EXTs and cannot be done in clinic, what happens next?
refer to OMFS, they can see of they need to do or TMD

pt presents w/ exostosis, needs CD, what next?
OS consult, hold off on tx plan until their assessment

pt presents w/ stomatitis, already has dentures, what happens next?
clear up the infection, express home care, may need an interim denture to wear while infection clears
Fungal infections also infect the prosthesis

why cant you deliver a final denture on extraction sites even if it were 2-3 mo prior?
bone needs to remodel and tissue shrinks, final won't fit properly. Will need an interim denture
what are the steps for having a maxillary interim denture after EXTs?
1. impression
2. lab- plans how ridges will look after surgery
3. surgery to ext teeth and deliver interim immediatly after
If DMD level wants to do a mand over denture, what is required?
DMD level (APC consult required)
who does max overdentures or fixed implant dentures?
grad prosth level
anything involving implant retention goes through....
APC
what 3 things provide good adaption?
mucosa, saliva and denture base

what is cohesion?
same molecules in the saliva provide a thin layer between denture base

Effective border seal: __ helps resist denture displacement
atmospheric pressure

Thin saliva film: __ and __ between alike molecules
cohesion and surface tension

what is the best means of retention for the max CD?
Posterior palatal seal- add more pressure to create the seal

what is the best means of retention for the mand denture?
retromylohyoid fossa- the lingual flange has a "S" shape

retention on max vs mand CD?
more area on the max to create a seal and more cohesion/ saliva for retention
how do obtain retention on very flat mand ridges?
implant

how do obtain retention on very flabby mand ridges?
refer to prostho and place additional retention (build up ridges)
what does matte surface mean on impression?
green compound and matte shows when you have a good impression

what can dislodge a denture?
-occlusion, make sure its even/ balanced and adjust occlusion so that when they do certain movements it doesn't get disoldged
-teeth are flat- no cusps so pt can slide with ease

what are the steps for implant overdenture?
1. make CD/ CD
2. use denture you made to make a surgical guide
3. place implants
4. clear implants for restoration
5. select locator abutments- blue/ metal cap goes inside the denture
6. Insterta (blue) can be changed

what are the parts of an implant that supports an mand CD?
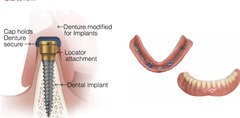
what are types of hybrids? Who does this?
zygomatic arch implants
refer to APC
referred to grad prostho
$20-40K
1st step of denture making
1. primary impressions- select correct size- key chain w/ all size options
2. apply ropewax w/ border if needed
3. alginate impressions w/ stock tray
4. pour w/ quickstone
What is the criteria for stock tray selection?
tuberosities, hamular notches and ridges are covered + space for the material you are using

why would rope wax be added?
capture the base of the ridges upto the vestibule, helps the alginate reach these areas
What is the primary purpose of a preliminary impression?
obtain diagnostic cast and provide info to make a custom tray
when should you repeat an impression?
any errors in the 1st impression, impacts the future steps
what requires an impression to be repeated?
-voids
-metal / tray showing through
-important anatomy is missing, distorted or poorly recorded
-poor extension- bubble/ thin surface where not all of the vestibule was extended
--could indicate that rope wax needs to be added--
good features of a primary cast?
-land area 4mm wide to protect vestibule and see extension of custom tray
whats the purpose of a land area?
protect anatomy


2-3mm

13-15 mm at the THINNEST SPOT

13mm
where is the thinnest spot on the mand cast?
retromylohyoid fossa (at least 13 mm)

where do we want to increase thickness on the mand cast?
retromolar pad
What is the purpose of marking primary casts?
to show how far the tray should extend and where relief/ stops should go
mand stops?
max stops?
buccal shelves
hard palate

red- depth of the vestibule
black- limits of custom tray; 2-3 mm shorter
What is the purpose of blocking undercuts?
tray can get stuck and break cast, undercuts prevents
-undercuts can also hurt
What is the purpose of adding wax reliefs?
to create space for impression material; tight on ridges = no space for impression material- only show tray

where should we place tissue stops? purpose?
hard palate
buccal shelves
maintain a consistent space for impression material
What is the purpose of making custom trays?
better adaptation
-something closer/ tighter making better impressions and thinner impression material = LESS distortion
-also fits better in pt's mouth
-uniform thickness
-accurate border molding and final impression making

its overextended and leaving insufficient space for border molding
what are the steps to custom tray try in?
1. put trays in mouth
2. hold at stops (hard plate)
3. move pt's cheeks and lips around
-trays should stay in place, if any movement this means the tray is over extended

When trying in a custom tray, what should be evaluated?
make sure the 2-3 mm clearance inside the pt's mouth
no displacement for lip, cheek and tongue movements
What is the main consequence of an overextended border on a complete denture impression?
1. can cause ulcers from pinching tissue
2. denture will not stay in place
What is the purpose of border molding?
record depth of vestibule DURING functional movements
What material is used at ULSD for border molding?
Green compound
what materials are needed for BOMO? what is the process?
-bunsen burner
-green stick compound
-heat and place in sm sections
-water bath (130-140 degrees for 4-5 sec)- DOES NOT HEAT COMPOUND- tempers it and more comfortable for the pt
If there's a fold, line or bubble in the compound, what should you do?
use flame torch to smooth
DO NOT HAVE TO TAKE COMPUND OUT OF THE TRAY
repeat until you get a soft rounded surface
What can happen if excess compound is not removed from the intaglio surface of the custom tray?
less space for impression material and interfere with the seating and accuracy of the final impression
What should be observed when border molding is finished?
Should stay in place- created a seal - should have retention
What material is used for CD master impression at ULSD?
PVS- Aquasil
What characterizes an acceptable master impression?
-have to cover all anatomical landmarks
-smooth surface- no voids/ bubbles
-no major distortions
-all BOMO covered with impression material

Compound is showing through the impression material, isthat a problem?
sm areas acceptable and large show throughs are unacceptable
What is the purpose of boxing the master impression?
-preserve full depth of vestibule
-guarantee you get the land area
-correct width and depth
consequences of not boxing?
-boxing allows for an easier cast to work w/

process of boxing? where to place the rope wax?
1. sticky wax- reheat before placing rope wax over it; 3mm from the border
2. rope wax over sticky wax
3. 15mm of pink base plate wax around

placing rope wax at the vestibule (not 3mm under) would result in what?
would eliminate the land area
where should wax sheet be placed on mand impression?

where should you spatulate the waxes?
the rope wax to the boxing wax- hold to light to make sure there is no gaps
rope wax forms the __ area
baseplate wax forms the __
land area
cast thickness