Clinical Pathology and Focused Ultrasound
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/54

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
55 Terms
Haemoglobin - HB
Most accurate and reliable measure of RBC mass
approximately 1/3 of HCT
HCT - haematocrit
calculated number, accuracy depends on RBCC and MCV values
PCV
approximately 2-3% higher than HCT
MCV
Average volume of a single erythrocyte in a population of RBC
MCHC - mean corpuscular haemoglobin concentration
average concentration of haemoglobin in a RBC
elevated MCHC not generally physiologically possible - haemolysis most likely
iatrogenic - hyponatraemic samples
lipaemia
secondary to haemolytic disorders
MCH - mean corpuscular haemoglobin
important value as MCHC and MCV are both affected by storage time and temp
reticulocytes will cause an increased MCV and decrease MCHC
under these circumstances MCH is more accurate than MCHC
RDW - Red Blood Cell Distribution Width
most sensitive marker for variability of RBC size
increased in regenerative anaemia and iron deficiency anaemia
Erythrocytosis - Causes
Relative erythrocytosis
Splenic contraction
isotonic dehydration
Absolute erythrocytosis
appropriate
chronic hypoxia → increased EPO → increased RBC production
Right-to-left shunts
chronic pulmonary disease
Inappropriate
increased EPO without systemic hypoxia
renal neoplasia
Hyperthyroidism or hyperadrenocorticism → mild, usually not enough for clinical signs of erythrocytosis
Anaemia - HCT, Hb and RBCC below normal reference interval
Regenerative anaemia
Haemolysis or haemorrhage
absolute reticulocytes (/uL) = reticulocyte % x RBC count (10^6/L)
Non-regenerative anaemia
Primary bone marrow disease
anaemia of chronic inflammation/chronic disease
decreased production of EPO
pre-regenerative
Poikilocytes
General term that describes an abnormally shaped erythrocyte
Acanthocytes
irregularly spaced, asymmetrical blunt-tipped spicules (2+), projects from the surface of a round RBC
causes:
fragmentation injury
shearing injury in DIC
fragile RBC in iron deficiency anaemia
usually accompanied by schistocytes and keratocytes
haemangiosarcoma in dogs - important blood biomarker
altered lipid metabolism
hepatic disease (dogs and cats)
others:
neoplasia - osteosarcoma, lymphoma
renal, AKI, CRF, glomerulonephritis
GIT - GE, GDV
musculoskeletal - trauma
internal haemorrhage
cardiac disease - degenerative valvular disease

Eccentrocytes
RBC’s with a transparent crescent-shaped area on one side of the RBC
causes:
oxidant-induced haemolytic anaemia (e.g., onion poisoning; Zinc toxicity)
endogenous oxidant
can occur in sick dogs without concurrent anaemia
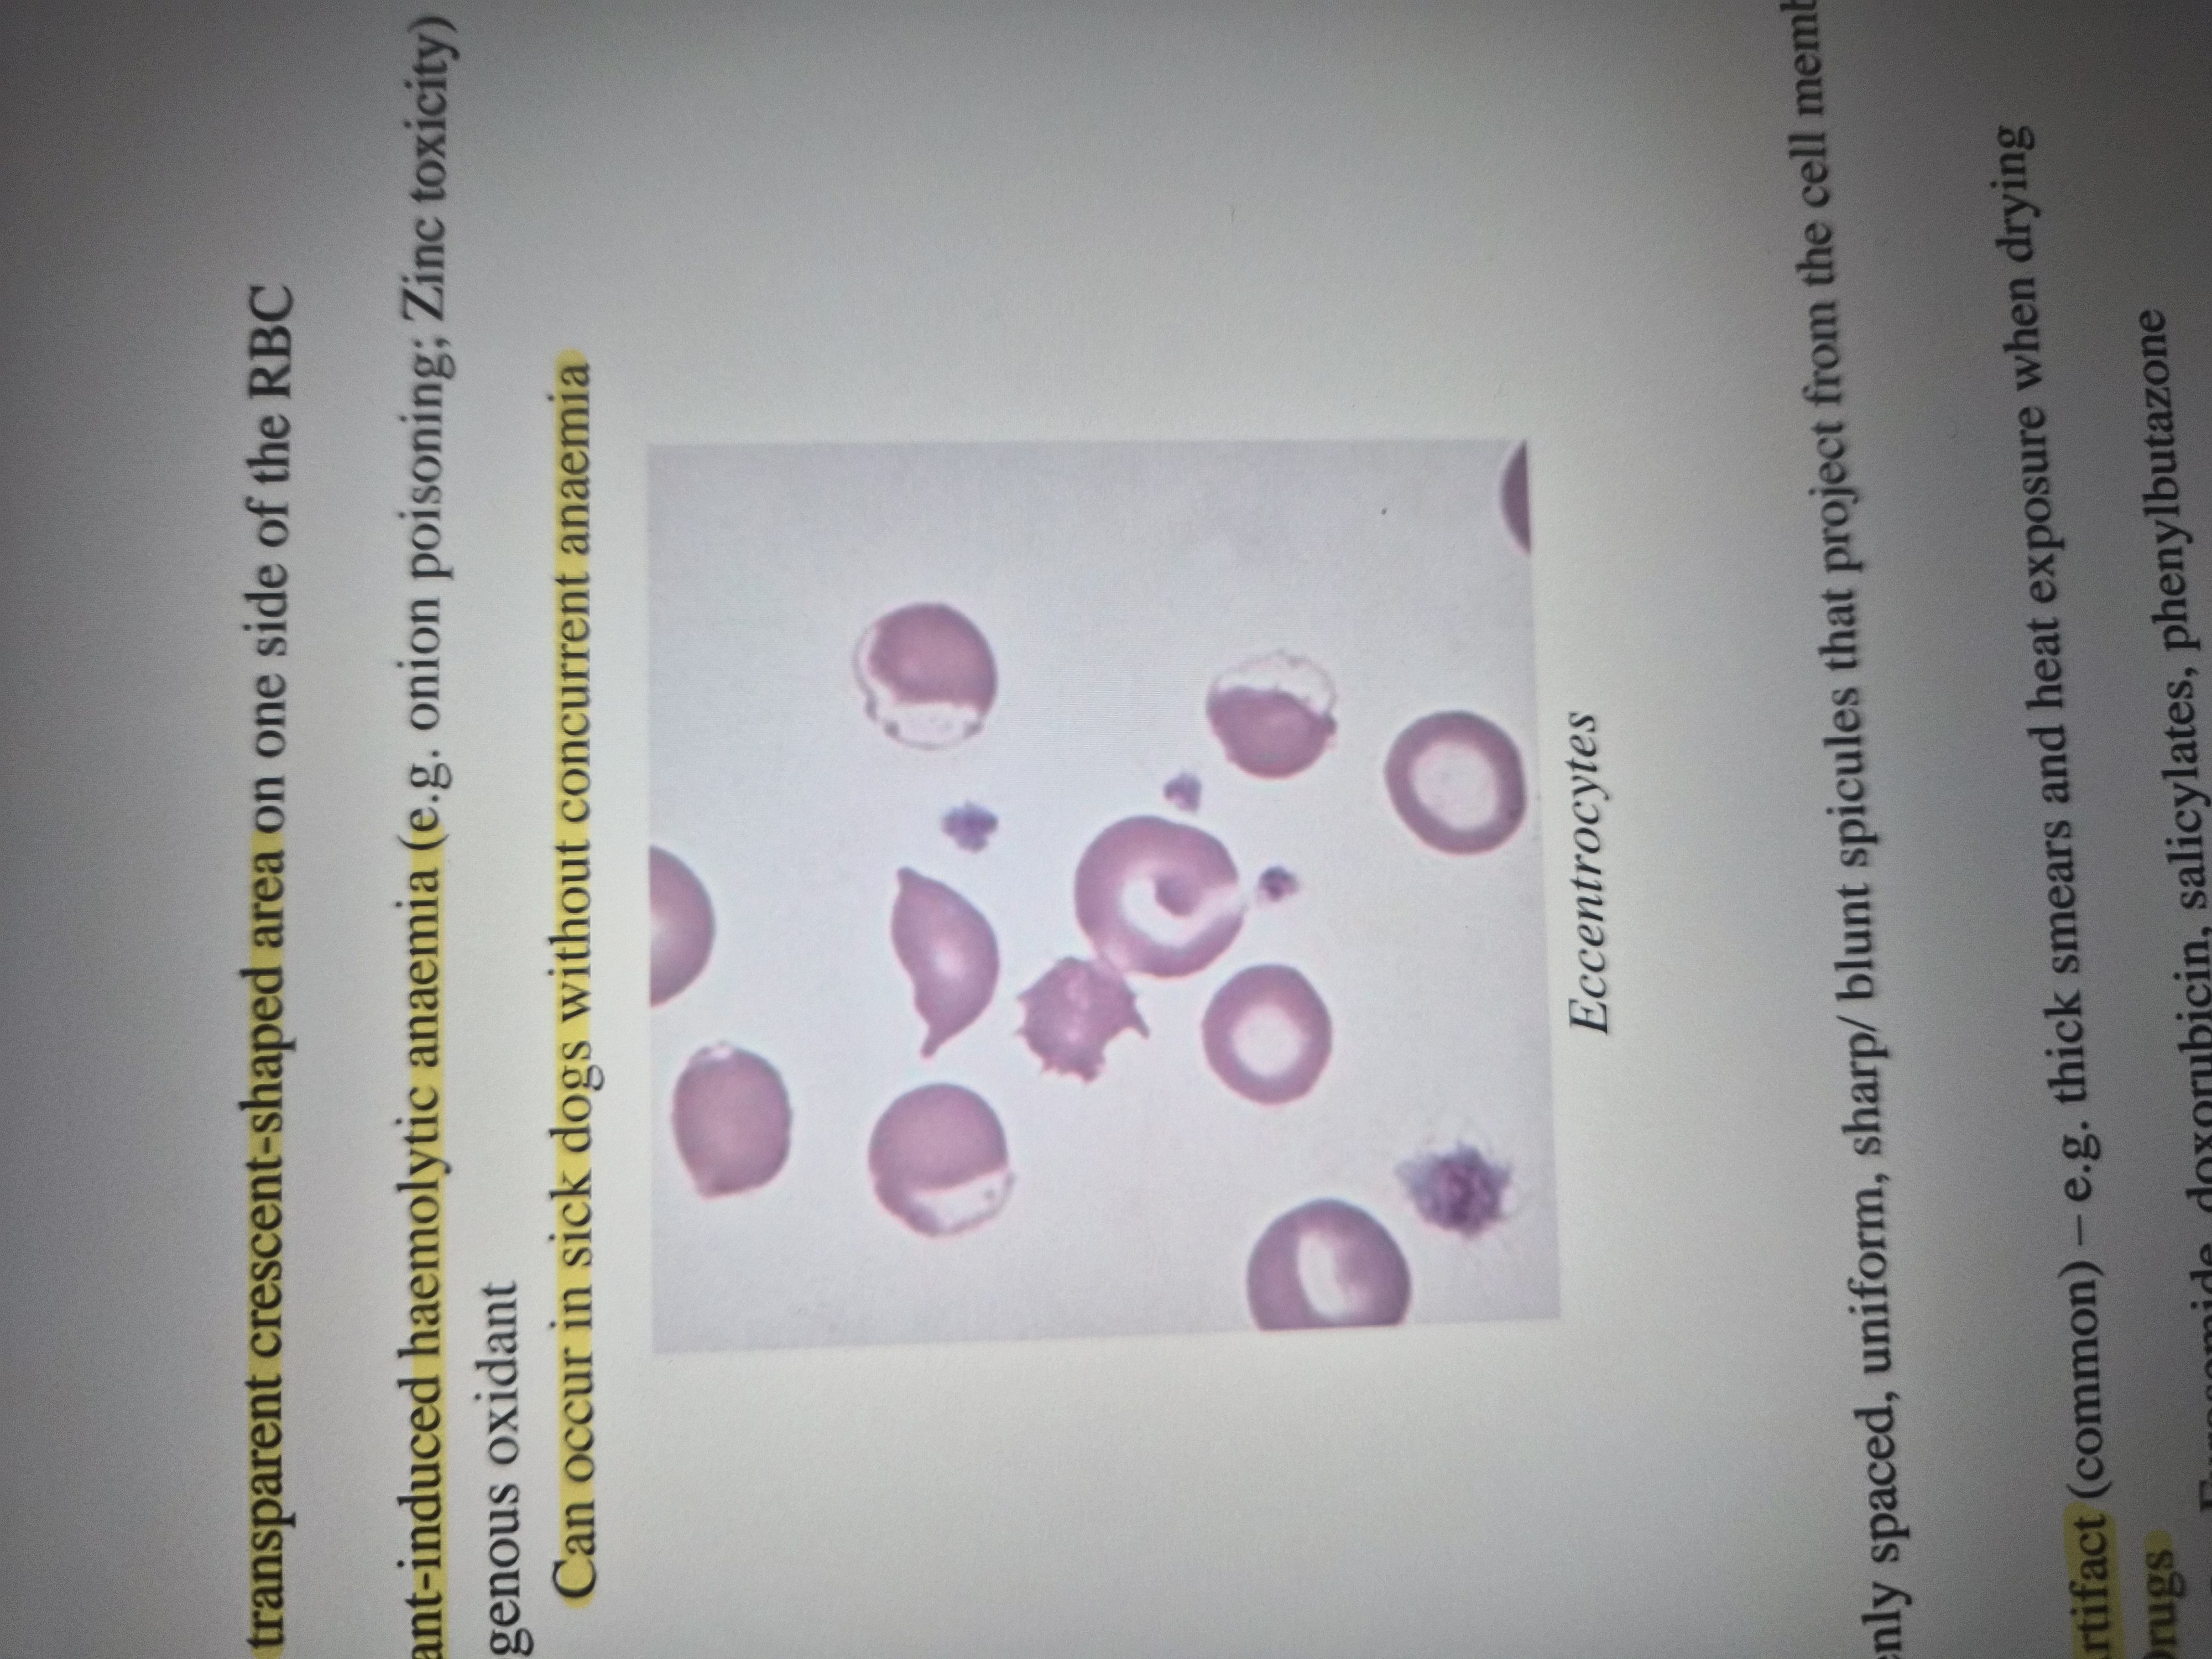
Echinocytes
Small, evenly spaced, uniform, sharp/blunt spicules
causes:
artefact - common
drugs:
frusemide
doxorubicin
salicylates
phenylbutazone
Disorders
renal disesae (glomerulonephritis; uremic toxins) (most commonly in dogs)
inherited RBC disorders
snake envenomation
neoplasia

Elliptocytes:
Elongated RBC’s
type 1: slightly oval-shaped
type 2: round to oval shaped
type 3: elongated elliptical cell
causes:
liver disease:
lipidosis (cats) - acanthocytes + type 3 elliptocytes
myelofibrosis
type I elliptocytes (dogs)
non-regenerative immune mediated anaemia
pre-cursor directed immune mediated anaemia
pure red cell aplasia
inherited/congenital RBC abnormality (rare)
neoplasia
artefact

Keratocytes (helmet cells)
Bite shaped defect - two horn like projections due to rupturing of a vesicle
causes:
fragmentation injury (DIC; HAS; Vasculitis)
oxidant injury
possibly accompanied by Heinz bodies, eccentrocytes
liver disease
hepatic lipidosis (cats)

Schistocytes
Irregular fragments of RBCs
causes:
roughing or irregulatiry of the blood vessel lining (e.g., fibrin presence)
turbulent flow
iron deficiency anaemia
drug toxicity - doxorubicin
disease processes
DIC
glomerular disease
vasculitis
PSS
vascular neoplasma
CHF
splenic torsion
rarely seen in cats - liver disease if present

Spherocytes
globoid RBCs that appear smaller than regular RBCs and lack central pallor
causes:
immune mediated anaemias
moderate to marked spherocytosis
strong regenerative response
others:
oxidative injury to RBCs
abnormal macrophage function
snake envenomation, bee stings
transfused or stored RBC’s
normal if only few are seen

Stomatocytes
Elongated central pallor (mouth like)
causes:
non-specific finding - regenerative anaemia, liver disease, lead poisoning
artefact
inherited RBC defect (dogs)

Codocytes (target cells)
resembles a bullseye due to redistribution of Hb within the cell
causes:
regenerative anaemia
iron deficiency anaemia
lipid disorders:
increase in cholesterol and phospholipid in RBC membrane
hypoT (dogs ) - high systemic cholesterol concentrations
hepatic disease
renal disease

Neutrophilia
Neutrophilia
Left shift: increased number of immature or precursor neutrophils in the circulation
non-degenerative: mature/segmented neutrophil count exceeds immature/band neutrophil count
degenerative: immature/band neutrophil count exceeds mature/segemented neutrophil count: it indicates severe inflammation
Corticosteroid response (stress leukogram)
endogenous or exogenous corticosteroid increase
Includes
neutrophilia - generally not more than 1x above reference limnit in dogs; but can be 2-3 times the upper reference limit in cats
lymphopenia
eosinopenia
monocytosis - common in dogs and rare in cats
not every patient has all of these changes - lymphopenia and neutrophilia are the 1st and 2nd most common seen respectively
biochemical changes that might be seen
hyperglycaemia - requires more chronic increase in corticosteroids
increase in ALP - in dogs with chronic corticosteroids (both endogenous or exogenous)
Adrenaline response (physiological leukocytosis)
FAS
most common cats and puppies!
immediate neutrophilia without left shift
usually accompanied with lymphocytosis, can also cause temporary hyperglycaemia
eosinophilia and basophilia may also be present in cats
Acute Inflammatory Respose
Neutrophilia in response to disease process
may feature a left shift
± toxic changes due to rapid transit time from bone marrow to circulation
concurrent lymphopenia (with or without eosinopenia) are common
causes:
infectious agents - bacteria, viruses, protozoa, fungi
immune mediated disease
neoplasia
hypoxic injury and necrosis
foreign body, e.g., migrating grass seed
Leukemoid response
marked leukocytosis secondary to strong inflammatory stimulus
>70×10^9/L dogs
>50×10^9/L for cats
associated with high mortality rate
reduced risk of mortality if infectious aetiology vs neoplasia
Toxic Changes in Neutrophils
Caused by dysplasia from accelerated granulopoiesis
most frequently associated with inflammation
characterised by:
dohle bodies - normal in low numbers in healthy cats
increased cytoplasmic basophilia
cytoplasmic vacuolation
nuclear immaturity
toxic granulation
help differentiate inflammation (present) from corticosteroid/adrenaline responses (absent)
can only be assessed via blood smear assessment
Hypersegmentation
normal aging process of neutrophils
more than 5 lobes within nucleus
increased hypersegmentation
increased lifespan - corticosteroid therapy
abnormal neutrophil production - FIV, myelodysplastic syndrome, vitamin B12/folate/cobalt deficiency
inherited condition - toy or miniature poodle with macrocytosis
Leukopenia and neutropenia
Causes:
Overwhelming demand for cells with increased migration from circulation into tissues or third spaces
pyometra, pyothorax, peritonitis, abscess
Ineffective granulopoiesis (and erythropoiesis)
myeloproliferative disorders
dysplasia of bone marrow
decreased cell survival time
viral infections:
FeLv, FIV, parvovirus
infectious agents
cryptococcus, histoplasmosis
protozoan parasites
leishmania, rickettsial infections (ehrlichia canis, rocky mountain spotted fever etc.,)
endotoxic shock or anaphylactic shock
vitamin B12 and folic acid deficiency
inherited neutropenic syndrome of collies - e.g., cyclic haemopoiesis
drug reactions
chloramphenicol
oestrogens
phenylbutazone
Lymphocytosis
Causes:
adrenaline response in the cat and puppy
protozoan infections
canine ehrlichiosis
some viral diseases
chronic antigenic stimulation or tarnsiently following vaccinations
hypoadrenocorticism
lymphoid leukaemia
monoclonal proliferation
lymphoid count >20×10^9/L
Lymphopenia
Causes:
stress/steroid response
decreased production - FIV/FeLV
loss of cells: chylothorax, lymphangiectasia
acute inflammatory response/acute phase of infection: some viral diseases, sepsis/endotoxaemia
CRF
immune mediated disorders
immunosuppressive drugs
lymphoproliferative disease
dogs with CHF
Eosinophils
Eosinophilia
IgE related hypersensitivies and migrating parasites
paraneoplastic - lymphoma cats: disseminated/intestinal mast-cell tumours
hypoadrenocorticism
idiopathic hypereosinophilic disease
Chronic eosinophilic leukemia
Cats: CRF and cardiac disease
Eosinopenia
characteristic finding in stress/glucocorticoid leukogram
Basophils:
appears in conditions associated with eosinophilia - allergies or inflammation
endocrinopathies - hypoT, DM
oestrogen administration
mastocytosis, neoplasia, myeloproliferative diseases
may also appear after fatty meal
Mast cells
mast cell neoplasia - especially if in circulation
acute inflammation - in low numbers
Thrombocytosis
An increased number of platelets
Causes:
most common - iron-deficiency anaemia/chronic GI bleeding
due to cross reactivity between EPO and TPO
Rebound following acute haemorrhage or thrombocytopenia
Reactive thrombocytosis
secondary to inflammatory state
IL-6 most important inflammatory cytokine contributing to thrombocytosis
stress/corticosteroids (common finding in Hyperadrenocorticism)
Post splenectomy
Thrombocytopenia
Four major mechanisms of acquired thrombocytopenia
increased consumption
decreased production
destruction
splenic sequestration (least common)
Can be normal or inherited in some breeds - generally asymptomatic
macrothrombocytopenia in CKCS and norfolk terriers (30-150×10^9/L)
greyhounds 80-295×10^9/L
MPV - mean platelet volume
Highly susceptible to platelet clumping
Increased:
increased thrombopoiesis
CKCS - macrothrombocytopenia:
high MPV, slightly lower than normal platelet count with normal coagulation
Hyperproteinaemia - Albumin and Globulin
Albumin and globulins both increased
Dehydration - only way this occurs
TP higher in neonates by 10% due to colostrum intake (normalises by 8 weeks)
Increased albumin, normal globulins (increased A:G)
overproduction of albumin is not possible
any increase should be interpreted as dehydration or laboratory error
most common cause is haemolysis or lipaemia
Increased globulins only
acute phase reaction
in chronic inflammation there is a concurrent compensatory decrease in albumin (negative acute phase protein)
microbial invasion, neoplasia, injury or inflammation
polyclonal gammopathy
antibodies produced in response to any inflammatory/infectious conditions
chronic bacterial infection, parasitic disease, fungal, viral infections, autoimmune disease and neoplasia. ANYTHING THAT CAUSES PERSISTANT STIMULATION OF IMMUNE SYSTEM
Monoclonal gammopathy
neoplasia of immunoglobulin producing cells - plasma cell neoplasm, lymphoma, lymphosarcoma, multiple myeloma etc.,
Hypoproteinemia
both albumin and globulin decreased!
Hemodilution
haemorrhage
excessive loss of protein
outside the body - parasitic, dermal burns
inside body cavities - 3rd space effusions/peritonitis
protein losing enteropathy - diarrhoea
protein losing nephropathy/nephrotic syndrome - glomerular disease
Decreased globulins and normal albumin
Neonatal pre-colostrum serum
less important in dogs and cats compared to large animal species
Primary immunodeficiencies
primary severe combined immunodeficiency - basset hounds, cardigan corgis, dachshunds
IgA deficiency - sharpei, beagle, airedale terriers, GSD
Breed variations - greyhounds have a lower reference range in comparison to other breeds
infectious diseases - viruses (FeLV and FIV in cats, canine distemper in dogs,) parasites (toxoplasmosis)
Decreased albumin +/- decreased globulin
Inadequate dietary intake
failure to synthesise albumin
severe hepatic disease
Decreased albumin with increased globulins
acute phase response
Lipids
Broken down into triglycerides and cholesterol
cholesterol is most readily tested in house
Increased - failure of cholesterol excretion (target cells and acanthocytes)
Decreased: reduced cholesterol production (more severe hepatic disease)
Hyperlipidaemia
post-prandial
primary hyperlipidaemia
not common in animals
idiopathic in miniature schnauzers
hypercholesterolaemia in briards, doberman, rottweilers, rough collies and shetland sheepdogs
secondary hyperlipidaemia
hypoT
DM
pancreatitis
hyperadrenocorticism
hepatic disease/cholestasis
pregnancy
obesity
nephrotic syndrome/protein-losing nephropathy
gram-negative sepsis
drug induced: corticosteroids; phenobarbitone, oestrogens, methimazole
Hypolipidaemia
no significance in most cases
significant causes:
impaired hepatic function - PSS or cirrhosis
malabsorption - EPI
protein-losing enteropathies
hypoadrenocorticism
Blood urea Nitrogen (BUN)
End product of protei metabolism
small quantities ingested
processes which induce protein catabolism
Causes of an increased BUN
Increased protein catabolism - fever, burns, corticosteroids, starvation, infection
increased protein digestion - haemorrhage into GIT, high protein meals
decreased filtration - pre-renal, renal or post-renal cause
Causes of a decreased BUN
reduced synthesis
reduced protein intake
PSS
severe hepatic insufficiency
increased loss
chronic polyuria → medullary washout
haemodilution
polydipsia
fluid therapy
Creatinine
Small amounts ingested
mostly derived from non-enzymatic breakdown of muscle phosphocreatinine
greyhounds normally have more than other species
crude estimate of GFR
Causes of increased creatinine?
pre-renal azotaemia
more common than renal azotaemia
USG >1.030 (dog) or USG >1.350 (cat) -indicates renal tubular function is most likely adquate
decreased renal perfusion → decreased GFR
shock, dehydration, cardiovascular insufficiency
maybe accompanied by increased PCV and TP
Increased protein catabolism → only mild azotaemia in that case
e.g., SI haemorrhage, infection, fever, corticosteroids
BUN will increse without a concurrent increase in creatinine
Renal azotamia
75% of nephrons must stop functioning before GFR sufficiently decreased for values to increase to above reference range
dog USG 1.008-1.029
cat USG 1.008-1.034
Post-renal azotaemia
Most commonly associated with obstruction or leakage distal to the kidneys
clinical signs: oliguria/anuria
USG - anything
Repture of LUT without significant obstruction
>1.4x increase in potassium in peritoneal fluid compared with serum
>2x increase in creatinine in peritoneal fluid compared to serum
hyperkalaemia common - reduced ability to excrete
Amylase
Causes of increased Amylase
non-specific enzyme
leakage when damage to pancreatic acinar cells - absence of which does not rule out pancreatitis
elevations >3-5 times normal can be suggestive of pancreatitis
also secondary to non-pancreatic disorders
especially intestestinal but also kidneys and uterus
hyperamylasaemia (2-3 x upper reference range) occurs in canine renal failure due to reduced excretion
not a feature of feline pancreatitis
Lipase
non-specific test
leakage enzyme when there is damage to pancreatic acinar cells
found in mainly the pancreas but also the gastric mucosa
elevations >=3-5 times normal can be suggestive of pancreatitis
absence does not rule out pancreatitis
in renal failure (3-5x upper reference range)
other causes
chronic gastritis, duodenal obstruction and other enteric disease
hepatic disease
post-abdominal
pancreatic and hepatic neoplasia
Canine pancreatitis lipase - Snap
negative test results generally rules out pancreatitis, a positive test result requires further testing to confirm the diagnosis
Alanine Aminotransferase (ALT)
Increased ALT
reflects either leakage from damaged or necrotic hepatic cells
or increases in volume of secreting tissue
and/or increased intracellular enzyme concentration
also present in heart, kidneys and muscle
mild to moderate increases in moderate to severe muscle injury (CK and AST will also be significantly elevated)
mild increases can occur with cholestasis and inflammatory gastrointestinal disease
ALT also present in RBCs - mild increases in haemolysed and lipaemic samples
hepatotoxic drugs
anti-convulsant medications (<4x increase)
phenobarbitone
glucocorticoids
doxycyline and methimazole (cats)
paracetamol
persistant increase is evidence of ongoing innury
rate of clearance is more important than magnitude of elevation
half-life is reported to range from 3hours to 4 days
hepatic derived ALT is most prolonged as it is also secreted by regenerating hepatocytes
approximately 50% reduction every 3-4 days in acute hepatopathies can be suggestive of a good prognosis - normal in 3-4 weeks
Aspartate aminotransferase - AST
found in skeletal muscle, cardiac muscle, liver and erythrocytes
used to investigate muscle damage (all species) and liver damage in some
must look at with CK
increased
elevated AST with parallel increase of ALT - hepatic
elevated AST with normal ALT - extrahepatic
ALKALINE PHOSPHATASE (ALP)
Mainly found in liver and bone (osteoblasts)
Also found in intestinal wall, kidneys and placenta - insignificant
Hepatic isoenzyme of ALP
in dogs:
sensitive indicator of cholestasis (precedes hyperbilirubinaemia and often seen with elevated GGT also)
increases in a variety of causes:
severe hepatic necrosis
anything that causes hepatocellular swelling
phenobarbital
hyperadrenocorticism
DM
hypoT
Interpretation in the cat:
short half life only 6 hours
not sensitive for cholestasis but very specific!
chronic neutrophlic cholangitis
idiopathic hepatic lipidosis
hyperthyroidism - resolves with treatment\
Bone-isoenzyme of ALP
increased in young animals (increase in osteoblastic activity)
kittens <15 weeks
puppies <6-8months
normal adult ragnes expected by 12 months of age at the latest
older animals
osteomyelitis, osteosarcoma, primary and secondary hyperPTH
Steroid induced isoenzyme of ALP
in the dog but NOT THE CAT
endogenous and exogenous glucocorticoid
prednisolone
phenobarbitone
Bilirubin
Hyperbilirubinaemia
retention hyperbilirubinaemia
primarily unconjugated
increased production (haemolysis) or hepatocellular lesion proximal to conjungation - e.g., intravascular haemolysis
regurgitation hyperbilirubinaemia
primarily conjugated
due to hepatocellular lesions distal to the conjugation step or intra- or extra-hepatic cholestasis
e.g., liver failure, obstructive biliary disease (intra-hepatic or extra-hepatic)
mixed patterns
reflects saturation of the system
most cases have mixed patterns by the time they present
Creatinine Kinase (CK)
Present primarily in skeletal muscle, myocardium and brain
Increases:
any event that causes muscle damage
myopathies
short half-life of 6 hours - indicates active or recent muscle traum
Persistent increase = ongoing myonecrosis
Excessive haemorrhage Screening Tests
CBC including platelet count
Biochemistry
PT/APTT
Prothrombin Time (PT)
Measures the activity of extrinsic (factor 7) and common pathways
low fibrinogen will prolong PT independent of other clotting factor deficiencies
must have adequate blood collected into citrate otherwise PT may be prolonged
factors need to be <30% of normal to result in prolonged clotting times
Prolonged PT, normal APTT
inherited factor 7 deficiency - reported in some dog breeds (does not cause haemorrhage)
early vitamin K deficiency
DIC especially in cats
liver failure
Prolonged PT, Prolonged APTT
multiple factor deficiencies, affecting both extrinsic and intrinsic pathays or common pathway factor deficiencies
vitamin K deficiency - e.g., rodenticide toxicity
Disseminated intravascular coagulopathy
Liver failure
Hypofibrinogenaemia
Activated Partial Thromboplastin Time (APTT)
Measures the activities of intrinsic (12, 11, 9, 10) and common pathways
low fibrinogen may prolong APTT independent of other clotting factor deficiencies
must have adequate blood collected into citrate, otherwise APTT may be prolonged\
factors need to be <30% of normal to result in prolonged clotting times
mild deficiencies in multiple factors in the intrinsic or common pathways can prolong APTT, despite individual factors not being < 30%
Prolonged APTT, normal PT
artefact - difficult venipuncture
iatrogenic unfractiouned heparin therapy
inherited deficiency - haemophilia A, and haemophilia B in dogs, factor 12 deficiency in cats (common and as not required for physiologic haemostasis will not cause haemorrhage)
DIC - especially in dogs
dogs with systemic lupus erythematosis due to anti-phosphoplipid antibodies
liver failure
Prolonged APTT, prolonged PT
Multiple factor deficiencies affected both extrinsic and intrinsic pathways, or common pathway factor deficiencies
vitamin K deficiency
DIC
liver failure
hypofribrinogenemia
activated coagulation time (ACT)
similar to APTT, except that factors need to be <10% of normal to result in prolonged clotting times
also requires platelets: <10000/uL may result in mildly prolonged diatomaceous earth-based ACT (by 10-20 seconds)