Transition of Care
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/3

There's no tags or description
Looks like no tags are added yet.
4 Terms
Define a transition of care and explain the need for managing transitions of care
Movement of a patient from one setting of care to another
Ex settings:
hospital
ambulatory care/primary care
ambulatory specialty care practice
long-term care facility
home health
rehabilitation facility

Identify and define quality measures that track transitional care management activities
Examples
Hospitalized adult patient with eart failure who were given complete written discharge instructions
Communicate about discharge information
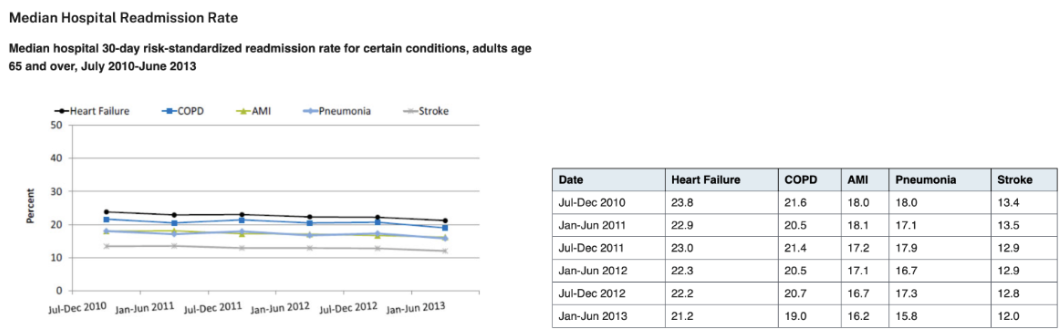
Median hospital 30-day risk standardized readmission rate
HF discharge instructions
Data from CMS
Tracked data from 2005-13
Sex, race/ethnicity
Achieved benchmark by 5 states

Discharge Communication
Measure: pt who did not receive good communication about discharge information
Lower number = better
Data from 2009-14
Disparities
“In all years, Black and Asian patients were less likely than White patients to receive good communication about discharge information”
“In all years except 2012, AI/AN patients were less likely than White patients to receive good communication about discharge information”

Readmission
Readmission refers to an unplanned admission to a hospital for any condition or procedure 30 days after discharge
Hospital readmission shortly after discharge is a marker of inpatient quality of care and a significant contributor to rising health care cost
2013 - 2/3 of US hospitals faced financial penalities from CMS because of excessively high 30-day readmission rates for acute MI, HF, and pneumonia
Lower rates = better
Readmission rate show if hospital is doing best to deliver quality care, preventing complications, and making sure pt has smooth transition where ever they are going
Describe roles for pharmacists and pharmacy technicians in managing transitions of care
Risk of adverse event can possible be from medication errors that may be preventable
Ex of transitions of care programs run by pharmacist:
Heart failure education on discharge from hospital admission with heart failure
Outcome: 30-day readmission
Medication reconciliation
Outcome: prevent adverse drug events
Primary care transitional care management
Outcome: (looking for medication discrepancies from discharge;) prevent adverse drug events
Identify and describe key components in the medication reconciliation process

Comprehensive list should include
All rx meds, herbal supplements, vitamins, OTCs
Best Possible Medication History
No perfect list
Taken by anyone in the health field. Histories taken by pharmacist or pharm techs are more complete than those taken by other healthcare professionals
Started in the ED if that is where pt entered

Process
Before EMRs, most health systems → paper forms for med recs
With EMRs → med rec section
Different health professions are responsible for different things
Nurse in ED gets initial list from pt. Sometimes there is a pharm tech that is with a pharm
Pt admitted in inpatient floor, provider receives list and reconciles what should be continued, stopped, changed or started