Week 4: Intracranial Problems and Spinal Cord Injury
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/61

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
62 Terms
Monro-Kellie Principle
the rigid skull contains brain, blood, and CSF
and increase in one requires compensation of another
exhausted compensation raises intracranial presure (ICP)
Normal Adult ICP
5-15 mm HG
Cerebral Perfusion Pressure Equation
CPP = MAP - ICP
What is Cerebral Perfusion Pressure?
calculates the net pressure gradient driving blood flow to the brain
Severe TBI Guidance Targets
60-70 mm Hg
Optimal CPP for Acutely Ill Adult?
70-100 mmHg
Critical CPP
<50 mmHg
results in permanent, irreversible neurological damage
Early Manifestation of ↑ ICP
altered LOC
restlessness
confusion
pupil changes
Late Manifestations of ↑ ICP
Cushing’s Triad
bradycardia
HTN with widened pulse pressure
irregular respirations
TBI: Primary Head Injury
occurs at the moment of impact
direct result of trauma
irreversible damage
TBI: Secondary Head Injury
occurs AFTER the initial trauma
complications
nursing care aims to limit this
TBI: Glasgow Coma Scale (GCS) Scores
Mild: 13-15
Moderate 9-12
Severe: 3-8
Glasgow Coma Scale (GCS): Considerations
GCS ≤8 requires urgent airway assessment + likely airway support
Older adults taking anticoagulants: may deteriorate despite an initially normal examination
ICP Management: Nursing Actions to Protect Cerebral Perfusion
prevent hypoxemia & hypotension
elevate HOB 30
keep the neck neutral
avoid excessive hip flexion or straining
maintain spinal precautions when needed
ICP: Reducing Stimulation Actions
provide ordered analgesia/sedation + fever control
space activities if ICP rises
suction only when needed
monitor response
monitor GCS, pupils, motor findings, V/S
ICP: Osmotic Therapy
mannitol or hypertonic saline may reduce edema
monitor sodium, renal function, fluid balance, serum osmolality, and pulmonary edema
ICP: External Ventricular Drain
level to the tragus
maintain ordered drainage height and asepsis
monitor ICP and CSF output/appearance
Refractory ICP: Intervention & Contraindication
refractory ICP may require:
CSF drainage
advanced sedtion
surgery
corticosteroids are NOT recommended
increased mortality
Concussion
sudden transient mechanical head injury
disruption of neural activity
possible LOC
no apparent structural damage
Contusion
bruising of the brain issue
within a focal area (one specific area)
possible hemorrhage
Diffuse Axonal Injury
shearing/tearing of the brain’s nerve fibers (axons)
may cause coma
often appears normal on CT
requires MRI to see “micro-hemorrhages”

Epidural Bleeding (Hematoma)
often artial
may include lucid interval before rapid decline
temporary period of apparent recovery
between the skull and the outer protective membrane (dura mater)

Subdural Bleeding (Hematoma)
involves bridging veins
blood collects between the surface of the brain and its outer covering
chronic cases may mimic dementia or stroke
Intracerebral
within brain tissue
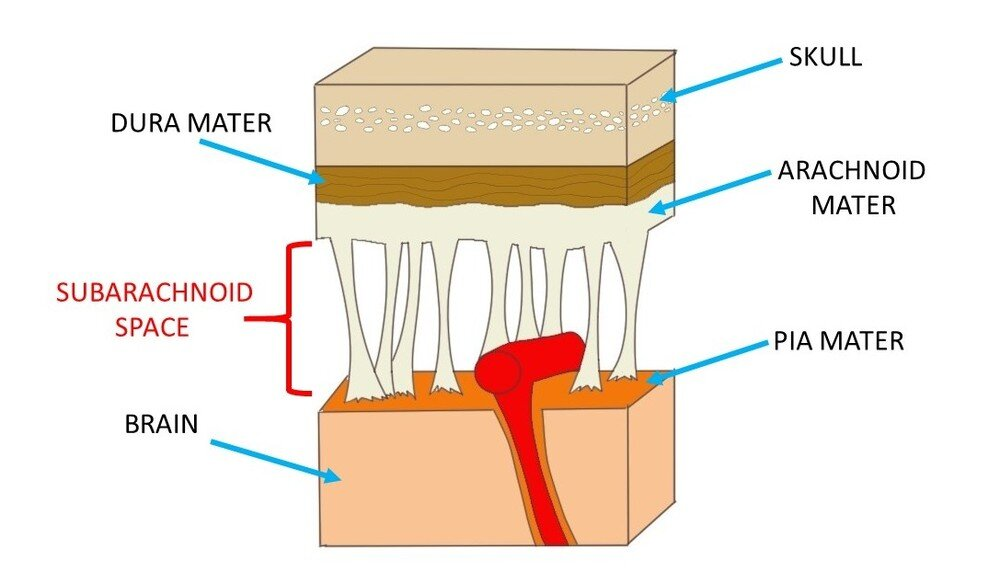
Subarachnoid
between arachnoid and pia
Intracerebral & Subarachnoid Hemorrhage: Red-Flag Manifestations
falling GCS
new pupil asymmetry
weakness
posturing required urgent escalation and imaging
decorticate posturing
Decorticate Posturing
closed hands
against chest
rigid, extended leg
feet point inward

Basilar Skull Fracture: Manifestations
raccoon eyes
battle sign
CSF rhinorrhea
CSF otorrhea (ears)
halo sign

Basilar Skull Fracture: Considerations
avoid nasal tubes/suctioning
avoid nose blowing
use a loose collection dressing
Basilar Skull Fracture: Halo Sign Diagnosis
halo/glucose findings alone do not confirm
beta-2 transferrin detects CSF
Halo Sign
CSF may leak from the ears and nose following a basilar skull fracture
creates a double ring pattern

Wired Jaw: Considerations
airway obstruction + aspiration are priorities
keep suction and appropriate emergency release tools at bedside
Wired Jaw: Emergency Management
position safely
call urgent help
cut fixation, if airway compromise requires it
cutting the wire
Spinal Cord Injury (SCI)
a neurologic condition resulting from damage to the spinal cord → disrupting motor, sensory, and autonomic pathways
Causes:
motor vechile collisions
falls
degenerative disorders
Spinal Cord Injury: Immediate Priorities
ABCs
spinal motion restriction
neutral alignment
use coordinated turns per protocol
anticipate airway support
high cervical injury can impair ventilation
Spinal Cord Injury (SCI): Essential Priority Assessments
Monitor:
motor/sensory function
respiratory effort
BP, HR
bladder function
Spinal Cord Injury: Completeness
complete: total loss of sensory & motor function below injury
incomplete: partial preservation of motor, sensory, or autonomic function below injury
Spinal Cord Injury: Perfusion + BP Goals
avoid HoTN
causes secondary ischemic injury to already compromised nervous tissue
administer ordered fluids/vasopressors
keeps BP ↑
MAP of 75-80
avoids forced augmentation (artificial BP management)
no active augmentation above 90-95 mmHg for 3-7 days
Spinal Shock
neurologic/reflex problem
temporary loss of reflexes below injury
flaccid paralysis
sudden muscle weakness, limpness, and a complete loss of muscle tone
provide supportive care and reassessment
Neurogenic Shock
circulatory problem
loss of sympathetic vascular tone
often with injury at T6 or above
watch for: HoTN, bradycardia
support perfusion (fluids, vasopressors)
Autonomic Dysreflexia
life-threatening, sudden overreaction of the involuntary nervous system that causes a dangerous spike in blood pressure
occurs after spinal shock
often occurs after spinal reflexes return and can recur
Autonomic Dysreflexia: Recognize these Signs
usually SCI at/above T6
sudden hypertension
often >20 mmHg above baseline
pounding headache
flushing/sweating above injury
possible bradycardia
Autonomic Dysreflexia: Priority Actions
sit upright and lower legs if feasible
summon help
loosen restrictive clothing
check BP/pulse every 1-2 mins until stable
Autonomic Dysreflexia: Remove The Trigger
check bladder distention and catheter obstruction first
assess bowel/skin triggers
avoid unplanned rectal manipulation that can worsen the episode
give rapid-onset, short-duration antihypertensive
Spinal Cord Injury: Prevention Secondary Complication
support cough and lung expansion
prevent VTE
prevent pressure injuries
prevent orthostatic HoTN
follow individualized: repositioning, bowel, and bladder programs
Spinal Cord Injury: Long-Term Support
rehabilitation
adaptive equipment
skin checks
caregiver training (autonomic dysreflexia)
psychosocial support
Seizure
transient, uncontrolled electrical disscharge in the brain
causes: motor. sensory, autnomic, or cognitive changes
Epilepsy
≥ 2 unprovoked seizures
1 with high recurrence risk
metabolic causes ≠ epilepsy
Focal Onset Seizure
begin in one hemisphere
person is conscious and will remember the seizuzre
altered LOC
Generalized Onset (Bilateral) Seizure
involves bilateral networks
happens without warning
loss of consciousness
Tonic-Clonic Seizure
tonic = stiffening
clonic = rhythmic jerking
classic type
Atonic Seizure
sudden loss of muscle tone → fall
common in children
high risk for head injury
Myoclonic Seizure
brief, shock-life muscle jerks
Absenece Seizures
brief impaired awareness
staring, unresponsive
During a Seizure
Stay with the patient
time the event, protect the head
clear hazards
support airway/breathing
Turn side-lying when safe
maintain spine precautions if trauma is suspected
do not restrain or place anything in the mouth.
Convulsive Status Epilepticus
seizure ≥ 5 minutes OR repeated seizures without recovery
medical emergency → treat immediately
Convulsive Status Epilepticus: Response+Treatment
activate emergency response
support ABCs
check glucose
give prescribed rescue benzodiazepine promptly
prepare further antiseizure therapy and airway support if seizures persist
After Seizure
reassess breathing
GCS
pupils
injuries
return to baseline; reorient calmly
After Seizure Documentation
duration
first body part involved
movements
awareness
recovery
ICP Management: Tier I (Foundational Care)
HOB 30-45
Suctioning: limit to 2 passes, <10 seconds
do NOT cluster care
sedation
ICP Management: Tier II (Osmotic Therapy)
Hypertonic Saline (3%)
pulls excess fluid out of the brain cells
elderly: pulmonary edema (crackles in lungs)
ICP Management: Tier III (Advanced Interventions)
Barbiturate Coma
↓ the brain's metabolic and oxygen demands
Induced Hypothermia
slows down cellular metabolism and oxygen demand
Decompressive Craniectomy
removal of a portion of the skull
allows brain to swell outward
do NOT position the patient on the operative side.