Getting Gas to the Patient (Breathing Systems - Part 1 &2)
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/37

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
38 Terms
What are the three classifications and components of breathing systems.
• Non-rebreathing systems
Lack
T-piece
Bain
• Rebreathing systems
Circle
• Hybrid systems
Humphrey ADE
What are the functions of breathing systems?
• Deliver oxygen to patient
• Deliver anaesthetic gas and/or vapour to patient
• Remove exhaled carbon dioxide
• Provide a means to ventilate patient
Reminder**
What is tidal volume?
What is respiratory minute volume?
• Tidal volume
- Volume of gas exhaled in 1 breath (AKA size of the breath)
10-20 ml/kg for most smaller patients
• Respiratory minute volume (minute ventilation)
Volume of gas exhaled in 1 minute
Tidal volume x respiratory rate
= 200 ml/kg
What is rebreathing?
What are the two types?
• Rebreathing
Inhalation of previously exhaled gas
• Two types:
- Rebreathing of exhaled gas from which CO2 has been removed (by an absorbent) is not detrimental (usually with an absorbant)
- Rebreathing of unchanged exhaled gas leads to build up of CO2 (hypercapnia), since CO2 not removed
Moderate to severe hypercapnia is detrimental causing catecholamine release, cardiac arrhythmias and acidaemia
What is equipment dead-space?
• Equipment dead-space
- Volume of breathing system that may contain exhaled gas that could be rebreathed during the subsequent breath

What are the components of the breathing system?
• Tubing
• Reservoir bag
• Adjustable pressure limiting (APL) valve
• Carbon dioxide absorbent (e.g. soda lime)
• Unidirectional valves
What is the purpose of the tubing in a breathing system?
What can alter the resistance of gas flow through these tubes?
• Tubing
- Conveys gases to and from patient
- Usually corrugated to resist kinking
Causes turbulence of gas flow which increases resistance
- Smooth internal bore reduces resistance
How are the tubes typically arranged in the breathing system?

What is the purpose of the reservoir bag in the breathing system?
• Reservoir bag
- Various sizes
Typically 0.5-6L in small animals
20-30L in horses!
- Functions include:
Reservoir
Visual aid
Means of assisting ventilation
Can be squeezed to push gas into the patient
What is the purpose of the APL valve?
• Adjustable pressure limiting (APL) valve
- "Pop-off", "spill" or "expiratory valve"
Provides a means of escape for excess gas preventing pressure build up - important that this valve is open
Connects to scavenging system for disposal of waste gases
What does “open” and “closed” refer to in the APL valve?
• "OPEN"
- ANTI-CLOCKWISE to OPEN
- "Lefty loosey"
• "CLOSED"
- CLOCKWISE to CLOSE
- "Righty tighty"

When should the APL valve be open?
• Valve should always be fully open during spontaneous ventilation
Only adjusted during intermittent positive pressure ventilation (IPPV), i.e. when we want to manually inflate the patient's lungs
If you don’t notice: pressure can damage patient lungs and cause a pneumothorax
Reservoir Bag Over-Inflation: The breathing bag fills up completely and becomes rigid and hard to squeeze because fresh gas keeps flowing in with nowhere to escape.
What are the main features of non-rebreathing systems?
Features
Advantages
Disadvantages
• Features: A non-rebreathing system is an anesthetic breathing circuit that delivers fresh oxygen and gas directly to a patient while venting all exhaled carbon dioxide out of the system rather than recycling it.
- Removal of exhaled CO2 depends on an adequate fresh gas flow (FGF)
- Each system has a recommended FGF
Using oxygen as carrier gas, then FGF = O2 flow
Oxygen + nitrous oxide (1 part O2 to 2 parts N2O)
Oxygen + medical air (30% O2 & 70% air)
• Advantages:
- Patient inspires fresh gas
High Fresh Gas Flow: It relies on a high rate of incoming fresh gas flow to physically flush out exhaled CO₂ and waste gases before the next breath.
Patient breathes gas of known composition
Anaesthetic depth can be changed rapidly
Minimal Resistance: Because there are no heavy valves or chemicals for the patient to push air through, the breathing resistance is extremely low.
• Disadvantages
- High fresh gas flow (FGF)
Increased cost
Increased potential for environmental pollution
- Fresh gas is cold & dry
Hypothermia
Respiratory dessication
How can you calculate the fresh gas flow (Method 1)?
One ways to calculate FGF:
- Use respiratory minute volume or minute ventilation (MV)
MV = resp. rate x tidal volume (10-20ml/kg)
FGF = MV x “circuit factor”
- Circuit factors:
Lack: 0.8-1
Ayre's T-piece 2.5-3.5
Bain: 1-3.5

How can you calculate the fresh gas flow (Method 2).
Second way to calculate FGF: (More common method)
• Recommended method:
- Lack: 150-200ml/kg/min
- T-piece: 400-600ml/kg/min
- Bain: 200-600ml/kg/min

Why is a calculated FGF not always sufficient?
• Normal ventilatory pattern:
Inspiration, expiration & then expiratory pause
• Expiratory pause is crucial:
Fresh gas flushes expired gas out of system
If too short there is insufficient time for expired gas to be removed & rebreathing occurs
So increase FGF in patients with rapid respiratory rates
But by how much? Capnography helps!
What is the lack system?
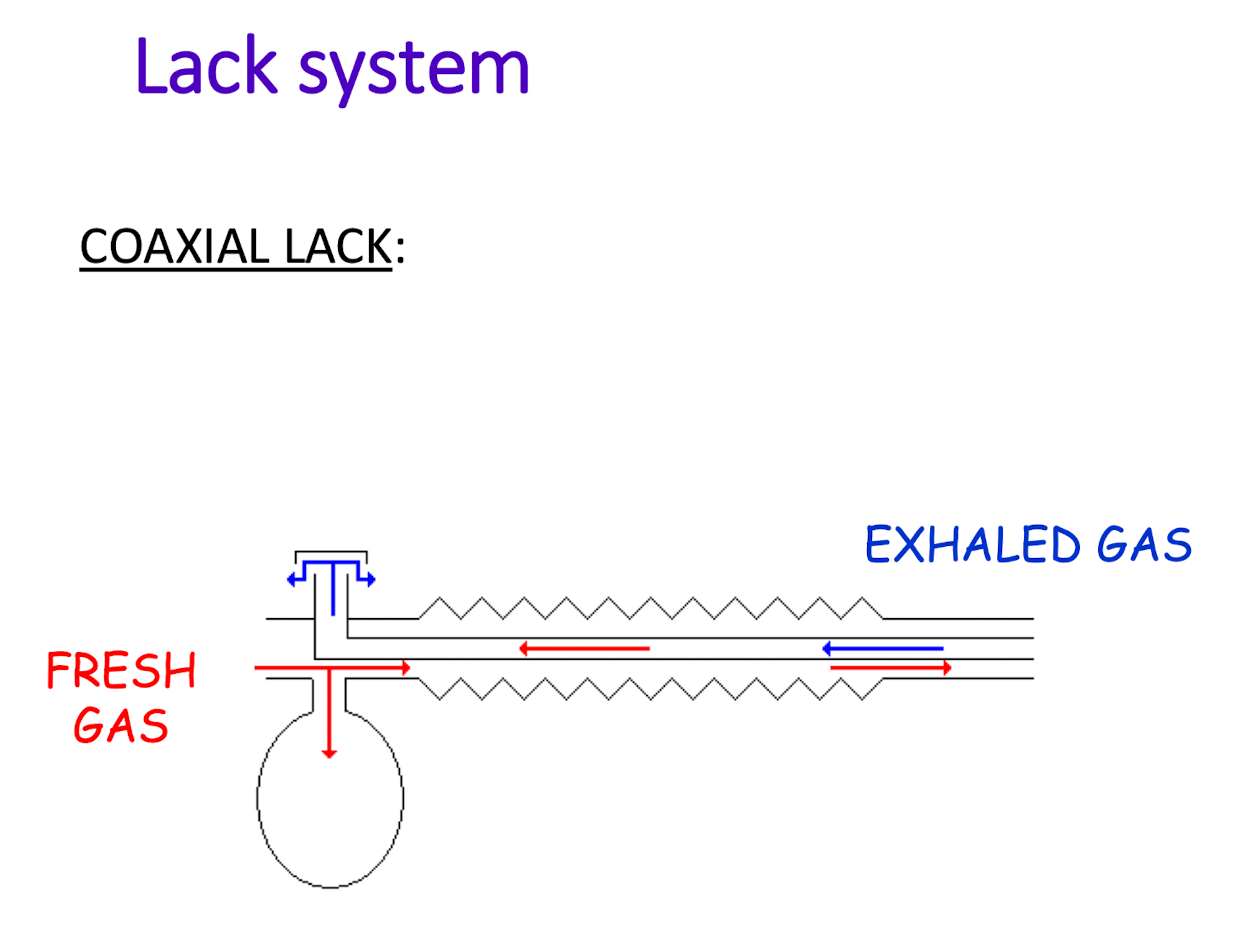
The Lack anaesthetic system is a parallel or coaxial (tube-within-a-tube) breathing circuit used to deliver oxygen and volatile anaesthetic gases to a patient while removing exhaled carbon dioxide
It is a modified version of the Magill circuit, falling under the Mapleson A classification of semi-open breathing systems.
Fresh gas flows through an inner tube to the patient, while exhaled gases travel back through the wider outer corrugated tube toward an adjustable pressure limiting (APL) exhaust valve.
The exhaust valve sits back at the anaesthetic machine end rather than right next to the patient's face.

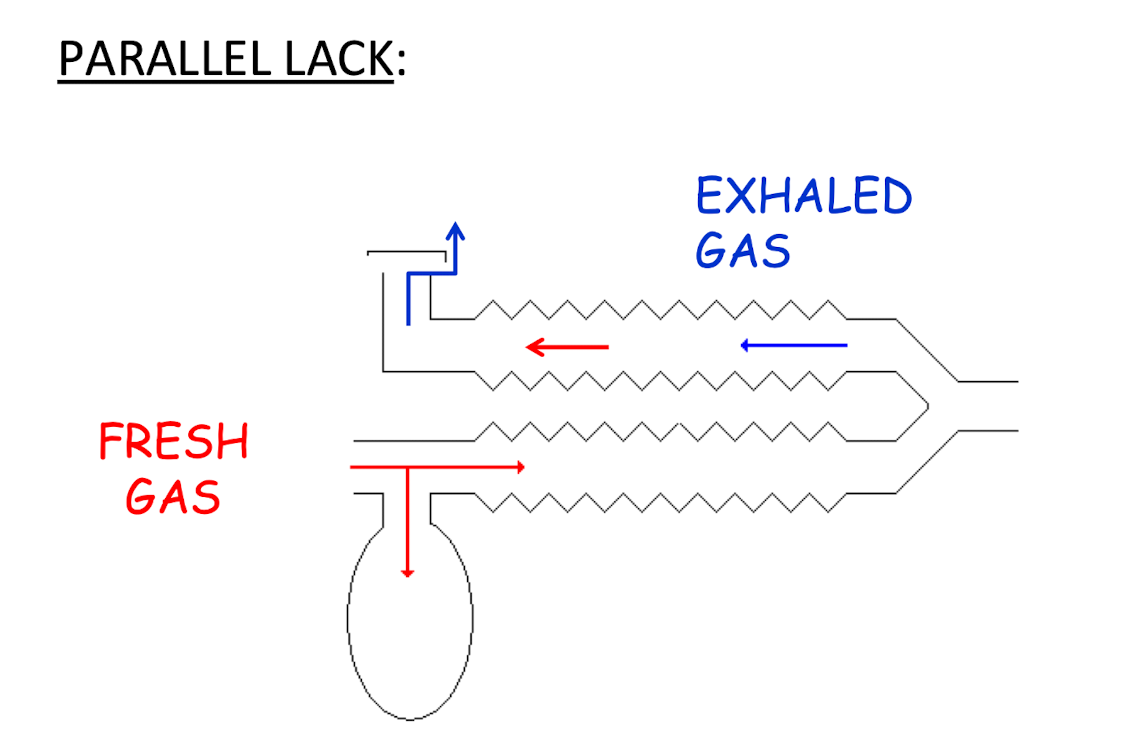
Parallel Lack
More bulky but probably safer
• More widely used
Coaxial Lack
Difficult to detect damage if inner tube is damaged but is less bulky by being a tube within a tube
Damage/disconnection of central tube leads to marked rebreathing of COz
Is a lack system useful for sustained IPPV?
NO
Alveolar Gas Push: When you squeeze the reservoir bag during IPPV with low fresh gas flows, the fresh gas cannot adequately clear the expiratory limb, forcing carbon dioxide-rich gas back into the patient's lungs.
Rebreathing Risks: Unless extremely high fresh gas flow rates (far exceeding normal recommendations) are used to continuously flush the circuit, the patient will re-breathe expired carbon dioxide, causing hypercapnia.

What patients is a parallel lack and minilack system useful for?
Parallel Lack
KEY FACTS:
• Patients 10 kg & over
• FGF 150-200 ml/kg/min
• Not suitable for prolonged IPPV
MiniLack system
Parallel Lack adapted for smaller patients
• Patients 10 kg & less
• FGF 200 ml/kg/min
• Not suitable for prolonged IPPV
What are the main features of (Basic) Ayre’s T-piece system?
Features
Advantages
Disadvantages
An Ayre's T-piece is a lightweight, valve-less anesthetic breathing system (classified as a Mapleson E or Jackson-Rees Mapleson F circuit) used to deliver oxygen and anesthetic gases

How does the Jackson-Rees Modification of the T-piece function?
Addition of an open ended bag
JACKSON-REES MODIFICATION:
• Classed as Mapleson F
• Allows observation of respiration
• Allows more control during IPPV
• BUT Difficult to scavenge
Attaching a standard scavenging tube directly to an open bag tail can easily cause the soft bag to twist, occlude, or collapse. This creates dangerous, inadvertent positive pressure or airway obstruction in small pediatric patients.

How does the Mapleson D Modification of the T-piece work?
Adaptation to facilitate scavenging
• Includes closed reservoir bag & APL valve
KEY FACTS:
• Patients up to 10 kg
• FGF of 400-600 ml/kg/min
• Suitable for IPPV

What are the main features of the Bain system?
Features
Advantages
Disadvantages
• Mapleson D
• Modification of T-piece
- Parallel or coaxial (most common)
KEY FACTS:
• Patients 10 kg & above
• FGF 200-600 ml/kg/min
• Suitable for IPPV
• NB: Modification of T-piece (FGF 400-600 ml/kg/min) but used in larger patients
Slower respiratory rate
Longer expiratory pause

What is the difference between a coaxial bain and a coaxial lack?
COAXIAL:
• Damage/disconnection of central tube leads to marked rebreathing
• BUT: we can test integrity of inner tube in coaxial Bain, cannot do so easily with the coaxial lack
Always check coaxial Bain prior to use !

What are the main features of rebreathing systems?
Features
Advantages
Disadvantages
FEATURES:
• Exhaled gases are rebreathed after removal of CO, by an absorbent
• Relatively low FGF can be used
• Patient inspires a mixture of fresh gas & exhaled gas
ADVANTAGES:
• Lower fresh gas flow
More economical - less O2, N2O and anaesthetic agent used
Less environmental contamination
• Gases are warmed and humidified
DISADVANTAGES:
• Greater resistance to breathing
Soda lime canister (CO2 absorber)
Unidirectional valves
• Unsuitable for small patients
• Patient inspires a mixture of fresh gas & exhaled gas
- Composition of inspired mixture unknown
Anaesthetic vapour
Oxygen (build-up of nitrous oxide)
- Slower to alter anaesthetic depth
What is the traditional absorbant for carbon dioxide?
• Traditional absorbent is SODA LIME
- 80% calcium hydroxide
- 4% sodium hydroxide
- 14-20% added water
- Indicator dye
Newer CO2 absorbents that lack strong bases (e.g. NaOH) are available that don't interact with sevoflurane to produce compound A.

What aspect of the soda lime changes allowing you to see exhaustion via CO2 absorption (Indicating fresh soda lime is needed)?
• pH of soda lime changes, allowing use of indicator dyes to reveal exhaustion (pink to white or white to purple)
Exothermic reaction
More water is produced than is consumed
How does FGF determine the extent of rebreathing in these anesthetic systems?
• High FGF not needed to expel exhaled COz
• Relatively low FGF can be used
• FGF used will determine extent of rebreathing
Full (complete) rebreathing
Partial rebreathing
No (minimal) rebreathing
> 200 ml/kg/min (minute volume)
What are the FGF requirements for full (complete) rebreathing?
What are some problems with rebreathing?
• Oxygen supplied is just sufficient to meet the patient's metabolic oxygen requirement
Oxygen requirement = 5-10 ml/kg/min
FGF 10 ml/kg/min generally recommended as a safe minimum
• No gas exits via the APL valve
Alternative name is "closed" system but do NOT actually close APL valve
• Maximal rebreathing occurs
Problems during use:
• Flowmeters may be inaccurate
• Vaporisers may be inaccurate
• Marked dilutional effect
Unsure of exactly what they breath, discrepancy between vaporizer and what they breath, difficult to rapidly increase or decrease what they breath due to the volume of the system
Turning up FGF will increase effects
Inspired concentrations of inhalant & oxygen may differ significantly from those set
Slow to adjust anaesthetic depth
Cannot use N2O unless inspired concentration of O2 is monitored
Advantages:
• Very economical (& sustainable)
BUT
• Difficult to use!

What are the FGF requirements for partial rebreathing?
What are some problems with rebreathing?
• Oxygen supplied is greater than that required for metabolic O, consumption but less than the minute ventilation
>10 ml/kg/min but < 200 ml/kg/min
For convenience a FGF of 1 or 2 L/min is often used
• Excess gas spills via APL valve
Alternative name is "semi-closed" system
• Partial rebreathing occurs
Compare a partial rebreathing system to a full rebreathing system.
Compared to full rebreathing mode:
• Flowmeters should be accurate
• Vaporisers should be accurate
• Less dilution effect (though it still occurs)
- Easier to adjust anaesthetic depth
- N20 can be used (relatively) safely
What is important to remember for the lung contents of a patient at the start of anesthesia (Using a rebreathing system)?
At the start of anaesthesia:
• Patient's lungs and breathing system are full of room air (79% N2)
• No circulates diluting inspired concentration of anaesthetic & oxygen
• Need to DENITROGENATE post-induction
How is denitrogenation performed?

What are the two rebreathing systems?
To & Fro System
Circle Circuit
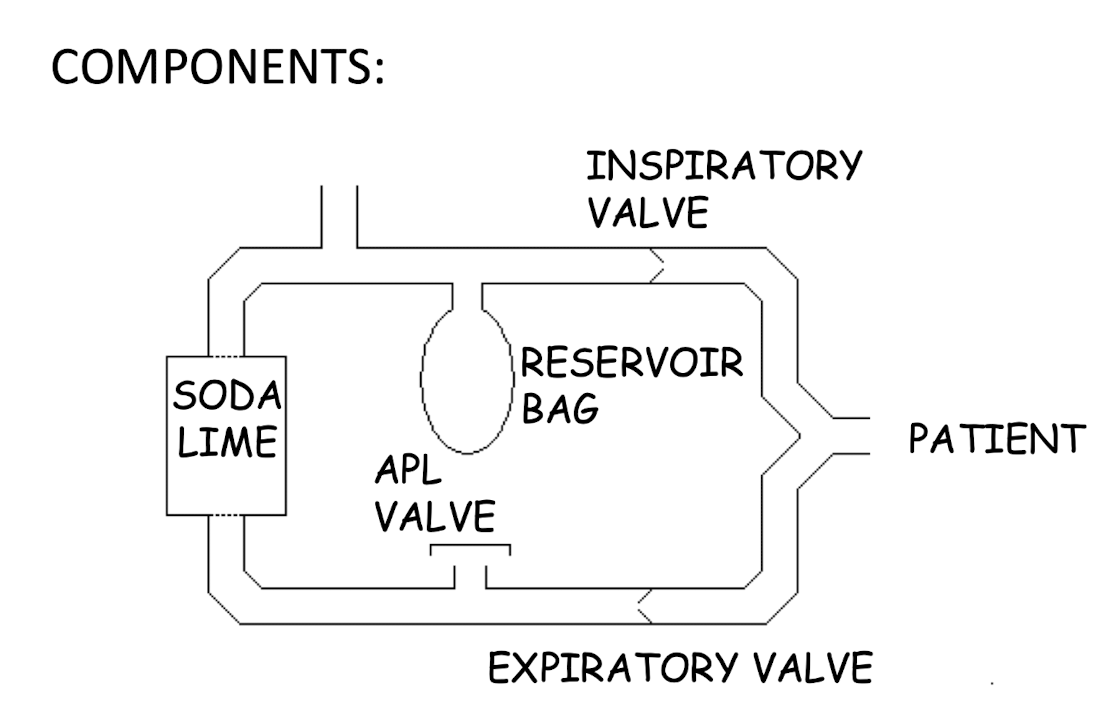
What are the main components of a circle rebreathing system?
COMPONENTS:
• Soda lime canister
• Reservoir bag
• Unidirectional valves
Flow through soda lime is unidirectional - gas needs to go in one direction
• Patient size - depends!
Human adult circle > 15 kg
Veterinary specific circles ≥ 10 kg
What governs which system you should choose for anesthesia?

Describe how the Humphrey ADE system works for different sized patients.
Pros and Cons
HYBRID SYSTEM:
• For patients 10 kg and over:
- Include soda lime canister
1. Use as a circle
• For patients < 10 kg:
- Remove soda lime & use in Non-RB mode
2. With lever up for spontaneous breathing (= MiniLack)
3. With lever down for IPPV ( = Bain/T-piece)
PROS & CONS:
• Easy to change from spontaneous breathing to IPPV (? advantage)
• Suitable for wide range of patient sizes
• Economical to run
• Expensive to purchase