Systemic Hypertension U2 L1
 Call Kai
 Learn
 Practice Test
 Spaced Repetition
 Match
 Flashcards
 Knowt Play
1/64

There's no tags or description
Looks like no tags are added yet.
Name | Mastery | Learn | Test | Matching | Spaced | Call with Kai | Chat |
|---|
No analytics yet
Send a link to your students to track their progress
65 Terms
What is blood pressure?
The pressure/tension of blood exerted on the arterial walls.
What 2 factors determine blood pressure?
Cardiac output
Peripheral vascular resistance
What is the formula for mean arterial pressure (MAP)? and another formula for MAP? - Slove: the pulse pressure SBP 145 mmHg and DBP 70 mmHg
What is the formula for Pulse pressure?
MAP = CO × TPR (total peripheral resistance)
Vasoconstriction → ↑ TPR → ↑ MAP
Vasodilation → ↓ TPR → ↓ MAP
So your blood pressure depends mainly on:
how much blood the heart pumps out (CO)
how much resistance the blood vessels create (TPR)
MAP = Diastolic pressure + 1/3 PP ( Pulse pressure )
(example the pulse pressure SBP 145 mmHg and DBP 70 mmHg, 145 -70=75
1/3 = 25, because 75 divided by 3 = 25 , DBP 70 + 25 = 95 mmHg)
Pulse pressure = SBP − DBP
What happens to blood pressure if cardiac output or vascular resistance changes?
Blood pressure will also change.
List the 3 main regulators of blood pressure.
Heart — mechanical pump
Blood vessels — resistance
Kidneys — blood volume
What blood pressure defines normal versus elevated blood pressure?
Normal: SBP <120 and DBP <80 mmHg
Elevated: SBP 120–129 and DBP <80 mmHg
What blood pressure defines Stage 1 hypertension?
Stage 1: SBP 130–139 or DBP 80–89 mmHg
What blood pressure defines Stage 2 hypertension?
Stage 2: SBP 140 or Higher or DBP 90 mmHg or higher
What blood pressure defines a hypertensive crisis?
SBP Higher than 180, DBP Higher than 120
What percentage of U.S. adults are hypertensive or take hypertension medications?
32–46%.
What type of cardiovascular risk factor is hypertension?
A modifiable and controllable risk factor for cardiovascular disease.
What is the name of the study, that does points and can show the risk of the CV event (like a stroke or heart attack) & explain how?
Framingham study:
Each 20 point rise in SBP or 10 point rise in DBP doubles risk of CV event
91% of patients diagnosed with what had a previous diagnosis of what?
91% of patients diagnosed with heart failure had a previous diagnosis of HTN
List the 10 modifiable risk factors for hypertension.
Obesity
Smoking
Stress
Diet
Physical inactivity
Sleep-disordered breathing
Diabetes
Excessive alcohol intake
Sodium intake
low potassium intake
List the 5 non-modifiable risk factors for hypertension.
Older age
Genetics — rare
Race
Male sex
Socioeconomic status (poor countries, cant afford health care, or meds, or doesnt have health food options)
Is there a specific threshold where cardiovascular risk begins with hypertension?
No threshold for risk in direct relationship between CV events and hypertension
It means there isn’t one specific blood-pressure number where cardiovascular risk suddenly begins.
Instead, as blood pressure gets higher, the risk of cardiovascular events—like MI, stroke, and heart failure—generally increases progressively. That’s what your slide means by a “direct relationship.” U2 L1 Hypertension (1)
For your notes, you could write:
No threshold for risk = CV risk gradually increases as BP increases; there is no exact cutoff where risk suddenly starts.
“No threshold for risk” = CV risk increases continuously as blood pressure increases; there is no exact BP where risk suddenly starts.
(can be low on the risk factor but still have an MI)
What is the 5-year risk of a major cardiovascular event in a 50-year-old male with a BP of 160/110 mmHg?
2.5% to 5% chance of having a major cardiovascular event within the next 5 years.
How do high cholesterol and smoking affect cardiovascular risk in hypertension?
High cholesterol → risk doubles
Smoking → risk triples
List the 3 additional cardiovascular risks of hypertension.
MI
Stroke
Heart failure
What does a widened pulse pressure increase the risk of?
A widened pulse pressure (higher SBP and lower DBP)
increases risk of Coronary artery disease (CAD).
List the 4 etiologies/types of hypertension.
Primary (essential) hypertension
Secondary hypertension
White coat syndrome
Pre-eclampsia
What percentage of hypertension cases are primary, or essential, hypertension?
90%.
Primary HTN = Essential HTN = high blood pressure without a specific known cause.
List the 3 factors associated with primary hypertension.
Endothelial dysfunction may play a role
Genetic predispositions (A genetic predisposition is an increased likelihood of developing a specific disease or trait based on inherited DNA variations,)
Environmental factors (Socioeconomic status)
What is secondary hypertension?
Hypertension related to an underlying condition.
List the 4 causes of secondary hypertension.
Renal disease
Drug-related
Endocrine disorders
Vascular disorders
(leads to High blood pressure)
What is white coat syndrome? (it is a precursor for what?)
Elevated BP in the clinical setting but normal BP when measured in the normal environment, such as at home.
(it is a precursor going to stage 1 or stage 2 HTN)
How common is white coat syndrome in hypertensive patients?
Up to 15–30%.
That “15–30% of hypertensive patients” wording on your slide means that among people who appear hypertensive in the clinical setting, a portion may actually have white coat hypertension instead.
What cardiovascular risk is associated with white coat syndrome?
It has a lower risk of cardiovascular events, but still requires close monitoring.
What is pre-eclampsia?
Hypertension that occurs 20 weeks after gestation.
Pre-eclampsia = new HTN after 20 weeks of pregnancy.
What severe complication can pre-eclampsia cause? List 2
Seizures, with a high risk of maternal or fetal mortality.
What does the slide state about the impact of pre-eclampsia on pregnancy?
It is a leading cause of maternal death and maternal and fetal morbidity.
Morbidity means illness, complications, or health problems — not death.
Why is pre-eclampsia thought to be associated with the placenta?
Because the hypertension subsides after delivery
List the 4 factors associated with pre-eclampsia.
Genetic
Immunologic
Behavioral
Environmental
Immunologic means related to the immune system.
So when your slide says pre-eclampsia may involve immunologic factors, it means the mother’s immune system may play a role in how the body responds to the placenta and pregnancy.
How does (Placental perfusion-) Placental ischemia contribute to hypertension in pre-eclampsia?
Placental ischemia causes widespread dysfunction of the maternal endothelium, which increases total peripheral resistance (TPR).
Clinical presentation
Can hypertension be asymptomatic?
Yes. It may be asymptomatic for years.
Clinical presentation
List the 4 general symptoms of hypertension.
General discomfort
Fatigue
Headache
Dizziness
Clinical presentation
What 2 acute events may be a presentation of hypertension?
Acute MI
Acute Stroke
What happens when vascular resistance increases?
Afterload increases.
What 2 compensatory cardiac changes occur in response to hypertension?
LVH
Increased LV mass
What type of dysfunction can LVH eventually cause?
Diastolic dysfunction ( the LVH isnt allowng the heart to relax, this is the later stage)
What happens when the heart can no longer compensate for hypertension?
Cardiac output decreases and heart failure develops (Eccentric hypertrophy)
HTN pathophysiology
List the 4 problems that LVH from increased peripheral pressure can cause.
Myocardial ischemia
Impaired contractility
Impaired LV filling
Ventricular dysrhythmias
Ventricular dysrhythmias = abnormal rhythms coming from the ventricles.
↑ peripheral vascular resistance → the LV has to pump against more resistance → ↑ afterload → LVH over time. U2 L1 Hypertension (1)
Increased peripheral pressure means there is more pressure/resistance in the blood vessels out in the body.
Simple version:
Increased peripheral pressure = tighter/more resistant blood vessels, so the heart has to work harder to push blood forward.
HTN pathophysiology
Which occurs first in hypertension: diastolic or systolic dysfunction?
Diastolic dysfunction occurs first. (HFpEF)
HTN pathophysiology
What type of dysfunction follows diastolic dysfunction?
Systolic dysfunction. (Later stage)
HTN pathophysiology
List the 2 findings that may occur once systolic dysfunction develops. (later stage)
Decreased LVEF (HF r EF)
LV enlargement
HTN pathophysiology
List the 4 LV geometry patterns.
Normal geometry,
Concentric remodeling,
Eccentric hypertrophy,
Concentric hypertrophy

How do normal geometry and concentric remodeling differ?
Normal geometry: Normal LV mass + normal relative wall thickness, Mass less then or equal to 0.42
Concentric remodeling: Normal LV mass + increased relative wall thickness

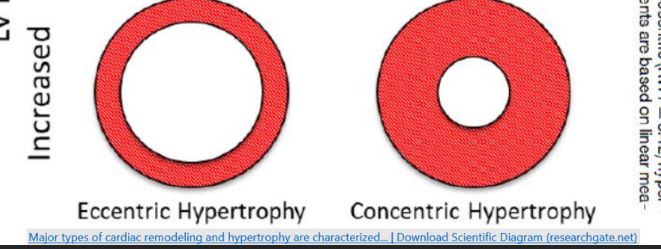
How do eccentric and concentric hypertrophy differ?
Eccentric hypertrophy: Increased LV mass + normal / thin relative wall thickness
Concentric hypertrophy: Increased LV mass + increased relative wall thickness
What relative wall thickness (RWT) value separates normal from increased RWT?
Normal: ≤0.42
Increased: >0.42
What LV mass index values indicate increased LV mass?
For Women Vs Men
Women: >95 g/m²
Men: >115 g/m²
List the 6 complications of hypertension.
Stroke
CAD
CHF
Sudden death
PVD / vascular disease
Renal dysfunction
List the 4 lifestyle changes used to treat hypertension.
Decrease body weight
Salt intake
Healthier diet
Physical activity
List the 4 antihypertensive medication classes given.
Diuretics
Calcium-channel blockers
ACE inhibitors
Angiotensin II receptor blockers (Long term regluation)
List the 4 LV-related echo findings associated with hypertension.
Increased LV mass
Concentric LVH (Thickened walls, small chamber)
Normal or hyperdynamic LV systolic function
Possible LVOT or mid-cavity obstruction
List the 5 additional echo findings associated with hypertension.
LA enlargement due to increased LVEDP
Aortic-root dilation
MAC with associated MR
Aortic-valve sclerosis
Diastolic dysfunction.
Echo findings
What type of diastolic dysfunction is seen in the Early stages of hypertension?
What would be the E/A
Grade 1 — abnormal relaxation.
E/ A less than or equal to 0.8

Echo findings
What symptoms are usually present with Grade 1 diastolic dysfunction?
No symptoms of diastolic dysfunction.
Echo findings
What type of diastolic dysfunction may occur later?
what is the E/A?
Grade 2 — pseudonormal.
E/A less then 2

Echo findings
What symptoms are associated with Grade 2 diastolic dysfunction? (rest vs exertion)
Minimal or no symptoms at rest, with symptoms during exertion.
Echo findings
What type of diastolic dysfunction occurs with significantly elevated LV pressure?
Grade 3 — restrictive., E/A greater than or equal to 2

Echo findings
What symptoms are associated with Grade 3 diastolic dysfunction?
Symptoms at rest and with exertion.
What are the normal & severely enlarged LV cavity EDV ranges? Female vs Male
Male:
Normal: 62–150 mL
Severe: >200 mL
Female:
Normal: 46–106 mL
Severe: >130 mL
What are the normal, mildly, moderately, and severely increased LV wall-thickness ranges? Male vs Female
Male:
Normal: 0.6–1.0 cm
Mild: 1.1–1.3 cm
Moderate: 1.4–1.6 cm
Severe: >1.6 cm
Female:
Normal: 0.6–0.9 cm
Mild: 1.0–1.2 cm
Moderate: 1.3–1.5 cm
Severe: >1.5 cm
HTN = LVH, increased wall thickness is assoicated with what?
Diastolic dysfunction
A patient has a cardiac output of 5 L/min and a total peripheral resistance of 18 mmHg·min/L.
The patient’s heart rate is 80 bpm, stroke volume is 62.5 mL, and systolic blood pressure is 145 mmHg.
Calculate the mean arterial pressure
CO = 5 L/min
TPR = 18 mmHg·min/L
So:
5 × 18 = 90 mmHg
✅ MAP = 90 mmHg